The Lp(a) gap: Practical steps to align primary care and lipid clinics

Vanessa Bianconi
1,*

,
Pietro Tasegian
2
,
Matteo Pirro
1
*Correspondence to:
Vanessa Bianconi, Department of Medicine and Surgery, University of Perugia, Perugia 06129, Italy.
E-mail: vanessa.bianconi@ospedale.perugia.it
Adv Lipoprotein(a) Res. 2026;1:202613. 10.70401/alr.2026.0010
Received: August 03, 2026Accepted: October 09, 2026Published: October 10, 2026
Abstract
Lipoprotein(a) [Lp(a)] is a major, independent determinant of atherosclerotic cardiovascular disease and calcific aortic valve disease, yet its integration into routine clinical practice remains fragmented. Persistent uncertainties regarding when to measure Lp(a), how to interpret assay results, and how to manage elevated Lp(a) levels in the absence of approved Lp(a)-lowering therapies continue to hinder its adoption. Meanwhile, targeted therapies, including antisense oligonucleotides, siRNA agents, and small molecules, are advancing through phase 3 trials and may soon provide evidence regarding the clinical impact of pharmacological reduction of Lp(a). This evolving landscape demands a transition from passive awareness to active implementation. Early identification of individuals with elevated Lp(a), transparent communication of its clinical implications, and structured referral pathways between general practitioners and lipid clinics for the optimization of cardiovascular prevention and preparation for future therapeutic options are crucial steps for bridging the existing Lp(a) gap. This perspective proposes a pragmatic framework for integrating Lp(a) into cardiovascular risk assessment and management across primary and specialist care, addressing operational challenges in measurement, interpretation, and treatment to support an actionable and coordinated Lp(a) clinical pathway. To this end, it formulates practical advice to orient Lp(a) management in primary care.
Keywords
Lp(a), cardiovascular, primary care, lipid clinic
1. Introduction
Lipoprotein(a) [Lp(a)] is widely recognized as an independent determinant of atherosclerotic cardiovascular disease and calcific aortic valve disease[1]. Nonetheless, its integration into clinical practice remains highly irregular and heterogeneous. This gap stems from three main challenges: persistent uncertainty about when to measure Lp(a), methodological complexity in the corrected interpretation of Lp(a) values, and the current absence of approved therapies capable of selectively lowering Lp(a) and impacting on clinical outcomes[2-4]. As a result, Lp(a) has become an emblematic example of how advanced biological knowledge can precede full clinical implementation of emerging evidence by decades.
Given the pathogenic link between Lp(a) and atherosclerotic cardiovascular disease, the most recent international guidelines and consensus statements converge on the message that Lp(a) should be measured at least once in adult life and systematically in specific high-yield clinical settings (Table 1)[1,5-11]. In addition, interest in cascade screening of elevated Lp(a) has grown in recent years, acknowledging that identifying a single index case may favorably modify the long-term cardiovascular risk trajectory of entire families[1,7,8]. At the same time, adoption of these recommendations is hindered by non-negligible technical limitations in the interpretation of Lp(a) values, including variability among immunoassays and the lack of international standardization between mass and molar units[4]. Moreover, clear communication with patients is complicated by the fact that although available evidence unequivocally shows that cardiovascular risk increases continuously with rising Lp(a) concentrations, without a sharp biological threshold, for pragmatic reasons operational cut-offs are needed to support cardiovascular risk stratification and therapeutic decision-making[7]. Finally, a crucial challenge remains the management of elevated Lp(a) in the absence of approved Lp(a)-lowering therapies[7]. Nevertheless, the future emergence of targeted therapies, including antisense oligonucleotides, siRNA molecules, and small oral agents, which are currently in advanced clinical development, opens the possibility of a paradigm shift[12].
Table 1. Recommended and possible indications for Lp(a) testing.
| Practical indication | Available recommendation | Guideline source | Class of recommendation and level of evidence |
| Universal once-in-a-lifetime testing | Yes | 2019 ESC/EAS guidelines[5] | Class IIa, Level C |
| 2022 EAS consensus[1] | - | ||
| 2022 AHA scientific statement[6] | - | ||
| 2025 focused update of EAS/ESC guidelines[7] | - | ||
| 2026 American multisociety guidelines[8] | Class 1, Level B-NR | ||
| Familial hypercholesterolemia | Yes | 2022 EAS consensus[1] | - |
| 2025 focused update of EAS/ESC guidelines[7] | - | ||
| Premature atherosclerotic cardiovascular disease | Yes | 2022 EAS consensus[1] | - |
| 2025 focused update of EAS/ESC guidelines[7] | - | ||
| Family history of familial hypercholesterolemia (first-degree relatives) | Yes | 2019 ESC/EAS guidelines[5] | Class IIa, Level C |
| 2026 American multisociety guidelines[8] | Class 1, Level B-NR | ||
| Family history of elevated Lp(a) (first-degree relatives) | Yes | 2022 EAS consensus[1] | - |
| 2025 focused update of EAS/ESC guidelines[7] | - | ||
| 2026 American multisociety guidelines[8] | Class 1, Level B-NR | ||
| Family history of premature atherosclerotic cardiovascular disease (first-degree relatives) | Yes | 2022 EAS consensus[1] | - |
| 2025 focused update of EAS/ESC guidelines[7] | - | ||
| 2026 American multisociety guidelines[8] | Class 1, Level B-NR | ||
| Ischemic stroke in the young | Yes | 2022 EAS consensus[1] | - |
| Patients at moderate risk or around treatment decision thresholds for risk reclassification | Yes | 2019 ESC/EAS guidelines[5] | Class IIa, Level C |
| 2025 focused update of EAS/ESC guidelines[7] | - | ||
| Recurrent cardiovascular events | No (suggested by available evidence)[9] | ||
| Calcific aortic valve disease | No (suggested by available evidence)[10] | ||
| Reduced response to LDL-C-lowering therapies compared to what expected | No (suggested by available evidence)[11] | ||
AHA: American Heart Association; EAS: European Atherosclerosis Society; ESC: European Society of Cardiology; LDL-C: low-density lipoprotein; Lp(a): lipoprotein(a).
In this evolving scenario, it is crucial for general practitioners and lipid clinics to collaborate in identifying patients with elevated Lp(a) levels early, informing and managing them appropriately, and facilitating access to clinical trials. This perspective aims to offer an operational and realistic framework in which integrating Lp(a) into clinical practice does not mean waiting for new drugs, but rigorously applying what we already know (when to measure, how to interpret, how to act), while preparing for a future in which Lp(a) management is hoped to finally be pharmacological. To this end, it addresses crucial issues regarding the Lp(a) clinical pathway, offering a pocket guide to orient routine practice in primary care.
2. Measurement of Lp(a)
The question of when to measure Lp(a) continues to be the subject of intense debate, given the discrepancy between its clinical significance, on the one hand, and the unavailability of pharmacological agents capable of lowering its circulating levels, on the other. Table 1 summarizes the current practical indications for Lp(a) measurement, distinguishing between the most recent formal recommendations from scientific societies[1,5-8] and possible indications for which available evidence suggests potential clinical utility without constituting a formal guideline directive[9-11].
Overall, five operational considerations may be formulated for general practitioners working in collaboration with lipid clinics. First, Lp(a) measurement should be incorporated into the routine lipid profile of any adult who has never been tested or added at the next available assessment if previous lipid profiles did not include it (Table 1). Second, Lp(a) measurement needs to be considered, if not already available, both in the young and in the adults, in the presence of specific clinical conditions, as reported in Table 1. Third, selective referral to laboratories equipped to perform Lp(a) testing should be considered, as the availability of Lp(a) assays remains heterogeneous across facilities[1]. Fourth, repeat testing of Lp(a) is unnecessary for most adults, although it may be rationally considered in specific clinical contexts where meaningful fluctuations in Lp(a) levels can occur over time[7,13,14] (i.e., in patients experiencing transient inflammatory states[15,16], in post-menopausal women particularly when pre-menopausal values are borderline[17], in patients with chronic kidney disease[18,19], in patients with liver disease[20], or during the transition from adolescence to adulthood[21]). Fifth, cascade screening should be implemented as a potentially high-yield intervention, since identifying a single index case may lead to the detection of multiple relatives whose long-term cardiovascular risk trajectory could be favourably modified.
Of note, available evidence suggests that the implementation of Lp(a) testing for cardiovascular prevention in primary care is cost-effective. Indeed, conventional assays for Lp(a) measurement are generally inexpensive and widely available, albeit their affordability still varying across healthcare systems due to reimbursement policies, laboratory infrastructure, and regional resource allocation[22]. In addition, early identification of individuals with elevated Lp(a), by enabling timely cardiovascular risk stratification and targeted referral to lipid clinics for optimization of cardiovascular prevention strategies, may reduce downstream expenditures associated with recurrent cardiovascular events and facilitate more efficient use of healthcare services[22]. Thus, integrating these operational considerations into primary care may provide potential clinical benefits for patients with sustainable resource use across the continuum of care.
3. Interpretation of Lp(a) Measurement
At least three methodological issues are known to complicate interpretation of Lp(a) measurements (Table 2). First, commercial immunoassays differ in sensitivity to apo(a) isoforms and may over- or underestimate circulating Lp(a) depending primarily on the predominant isoform, potentially resulting in substantial intraindividual variability[4]. Second, conventional Lp(a) immunoassays measure total apo(a) and may inaccurately measure Lp(a) when unbound or free apo(a) is present, which could be a relevant issue particularly if Lp(a) formation inhibitors, such as muvalaplin, will enter clinical practice in the future[23]. Third, because no internationally standardized assays and techniques exist, laboratory results may be reported either in molar units (nmol/L) or mass units (mg/dL), which are not strictly convertible into one another because the variable apo(a) isoform size makes any single conversion factor inherently inaccurate[4].
Table 2. Main issues regarding interpretation of Lp(a) measurement.
| Issue | Description | Clinical implications |
| Assay type | Immunoassays differ according to 1) the sensitivity to apo(a) isoform size (isoform-sensitive versus isoform-insensitive), and 2) the ability to measure intact Lp(a) | - Systematic measurement differences are plausible - Thresholds are assay-agnostic and guideline thresholds can be confidentially applied regardless of assay type - Analytical variability should not hinder implementation of Lp(a) measurement |
| Reporting units | - Lp(a) may be reported either in mg/dL (mass) or nmol/L (molar concentration) - No universal conversion factor exists | - Interpretation should preferentially follow the unit provided and converting between units should be preferentially avoided |
Lp(a): lipoprotein(a).
Regarding the level of cardiovascular risk attributable to Lp(a) levels, available evidence unequivocally shows that cardiovascular risk increases continuously with rising Lp(a) concentrations, without an abrupt threshold[1,7]. Nonetheless, for pragmatic reasons, clinically relevant thresholds have been proposed. The 2022 EAS consensus statement on “Lipoprotein(a) in atherosclerotic cardiovascular disease and aortic stenosis” suggests a pragmatic approach with Lp(a) cut-offs to rule out (< 30 mg/dL or < 75 nmol/L) or rule-in (> 50 mg/dL or > 125 nmol/L) increased cardiovascular risk and an intermediate grey zone (30-50 mg/dL or 75-125 nmol/L) to consider relevant in the presence of other cardiovascular risk factors[1]. In addition, the 2025 focused update of the 2019 ESC/EAS Guidelines for the management of dyslipidaemias considers Lp(a) levels above 50 mg/dL or 105 nmol/L, affecting nearly 20% of the population, as a cardiovascular risk-enhancing factor refining risk estimation across the spectrum of cardiovascular risk and a risk modifier to potentially reclassify cardiovascular risk categories in individuals at moderate cardiovascular risk or close to treatment decision thresholds[7].
Overall, three operational considerations follow for general practitioners working in conjunction with lipid clinics. First, Lp(a) values obtained using different assays and reported in different units must be interpreted cautiously. Nonetheless, the priority remains to not overshadow the fact that “Lp(a) needs to be measured”. Thus, the priority is to acknowledge assay differences without allowing them to hinder implementation of Lp(a) measurement, thereby ensuring that Lp(a) becomes a routine component of cardiovascular risk evaluation rather than an optional or deferred investigation. Second, the clinical added value of elevated Lp(a) lies in its pragmatic integration into cardiovascular risk assessment rather than in its absolute value alone. Third, patients should be appropriately informed about how their Lp(a) level contributes to refining their cardiovascular risk estimation.
4. Actionable Management of Elevated Lp(a) in the Absence of Specific Lp(a)-Lowering Drugs
To date, there is no direct evidence that Lp(a) lowering is associated with cardiovascular risk reduction, nor is the extent of Lp(a) lowering required for clinical benefit known, although specific Lp(a)-lowering medications are being tested in randomized clinical trials, including injectable RNAs and oral small molecules[12]. However, indirect evidence of cardiovascular benefit linked with low Lp(a) levels is available from large observational studies, Mendelian Randomization studies and post-hoc analyses of randomized clinical trials with other lipid-lowering drugs[1,7].
Overall, the operational approach of general practitioners working in conjunction with lipid clinics should be that of transparently discussing this point with patients with elevated Lp(a) 1) to present currently available pharmacological and non-pharmacological options for optimizing the management of cardiovascular risk, 2) to propose participation in randomized controlled clinical trials with specific Lp(a)-lowering drugs as a current potential treatment option, and 3) to create a reliable Lp(a)-lowering treatment outlook for the future. Regarding the first point, the fact remains that, in the absence of specific Lp(a)-lowering drugs, extensive cardiovascular risk factor management, with an early and tight control of modifiable cardiovascular risk factors and more intensive low-density lipoprotein (LDL-C) lowering, should be considered in the light of both absolute cardiovascular risk and the degree of Lp(a) elevation[1,8]. Of note, general practitioners have a crucial role in the primary selection of pharmacological and nonpharmacological options for optimizing cardiovascular risk management among patients with elevated Lp(a) levels (Figure 1). Nonetheless, primary care-to-lipid clinics referral for elevated Lp(a) would be crucial in specific conditions, to optimize the selection of treatment/follow-up strategy (Figure 1). Early lifestyle and pharmacological interventions aimed at controlling non-lipid modifiable cardiovascular risk factors (i.e., smoking cessation, healthful diet, physical activity, blood pressure control and glycemic control) are essential for individuals with elevated Lp(a)[8] and should be set by general practitioners. In addition, general practitioners are called upon to manage first-line lipid-lowering therapy. Although small studies have reported that statins may have a slight Lp(a)-increasing effect, individual-level data of seven randomized controlled trials do not show any significant impact of statins on Lp(a) concentrations[24]. Thus, it is unfounded to avoid statins as first-line LDL-C-lowering therapy in patients with elevated Lp(a) levels. Rather, patients with elevated Lp(a) levels should be strongly encouraged to take or continue to take statins if their risk is sufficiently high. In the JUPITER trial, high-intensity statin therapy was associated with a 30-40% relative risk reduction in cardiovascular events among individuals with elevated Lp(a)[25]. Moreover, when PCSK9 inhibitors are indicated to reach LDL-C targets in addition to a primary regimen including maximally tolerated doses of statins with or without ezetimibe, their prescription, a prerogative of lipid clinics, should be strongly encouraged for the ability of these drugs to lower Lp(a) levels by nearly 30%[26]. Lipoprotein apheresis, despite its low tolerability and relative scarcity of dedicated lipid clinics, can be considered for selected patients with familial hypercholesterolaemia and/or established atherosclerotic cardiovascular disease as a currently available nonpharmacological option for lowering Lp(a) levels by nearly 60%[27]. Although emerging evidence suggests that aspirin may reduce the risk of atherosclerotic cardiovascular disease among individuals with elevated Lp(a) concentrations[28-30], dedicated randomized clinical trials are lacking. Therefore, aspirin prescription can be considered by general practitioners only after a careful individualized assessment of the balance between potential cardiovascular benefit and bleeding risk. Regarding the second point, it is of crucial relevance to strengthen the operational network between general practitioners and lipid clinics to create preferential channels through which patients can be taken on for experimental treatments (Figure 1). Regarding the third point, it is fundamental that patients with elevated Lp(a) levels are aware of their cardiovascular risk and continue to be monitored to access specific treatment as soon as it is available.
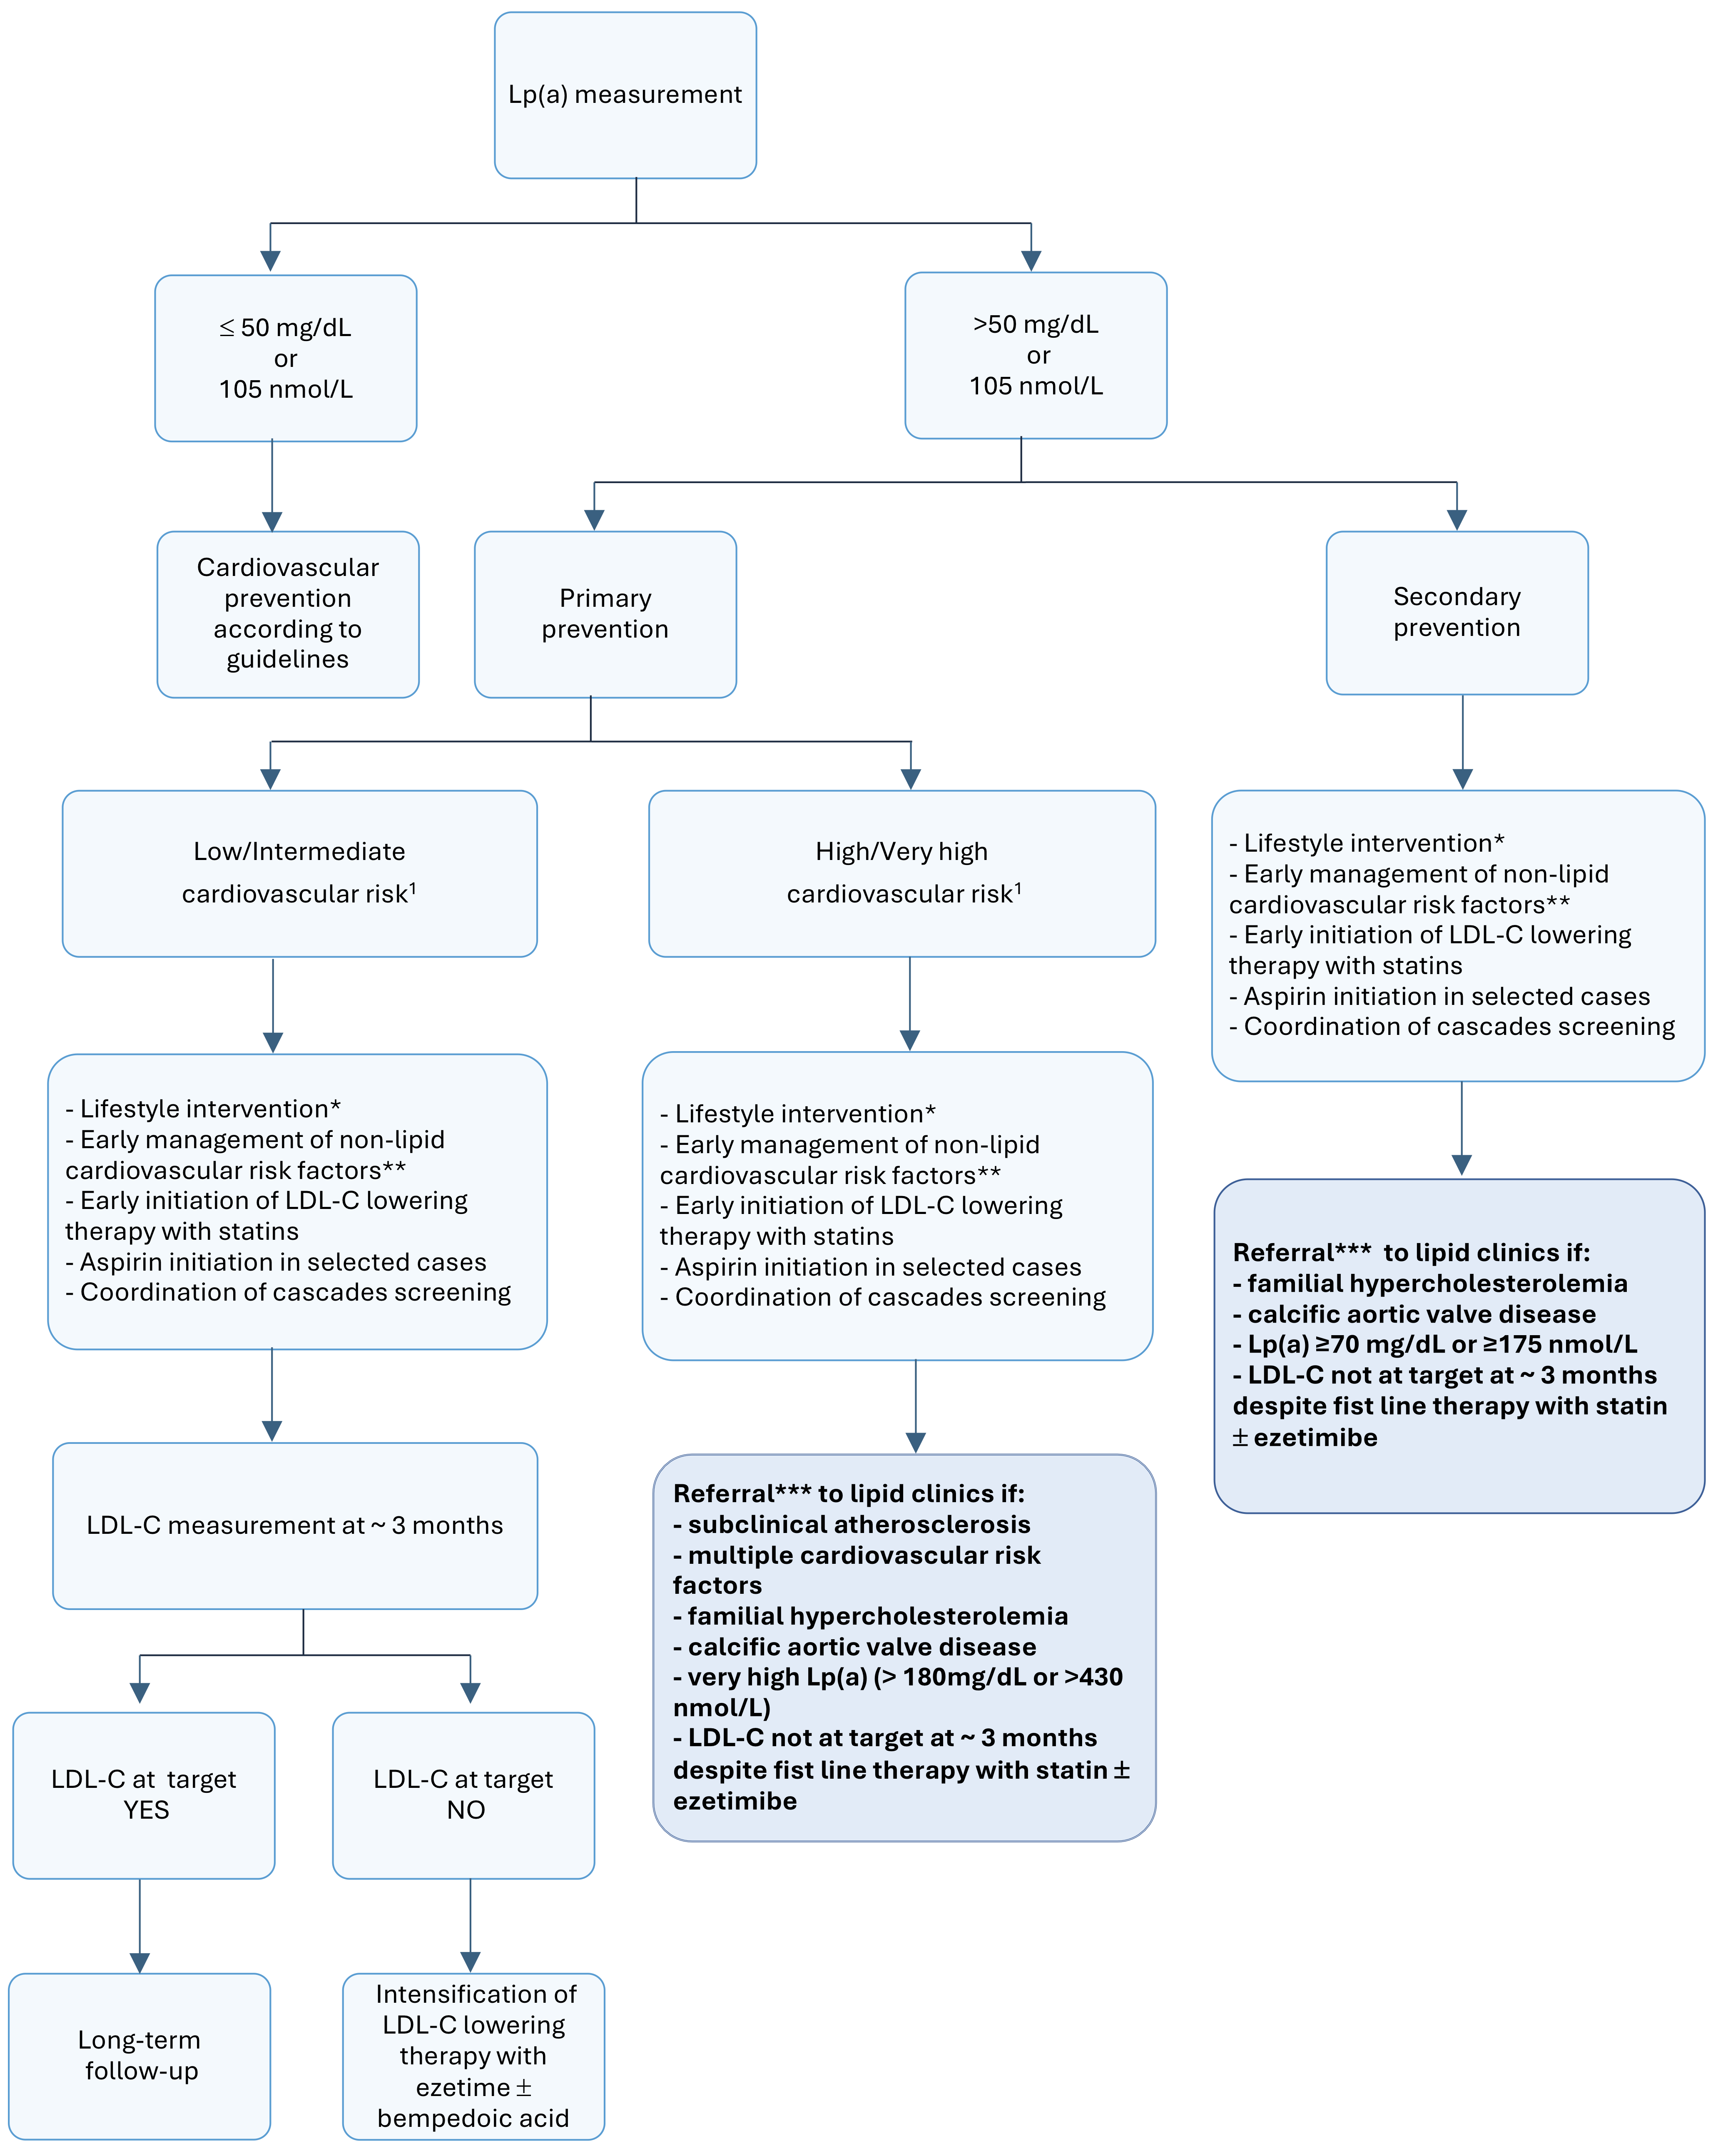
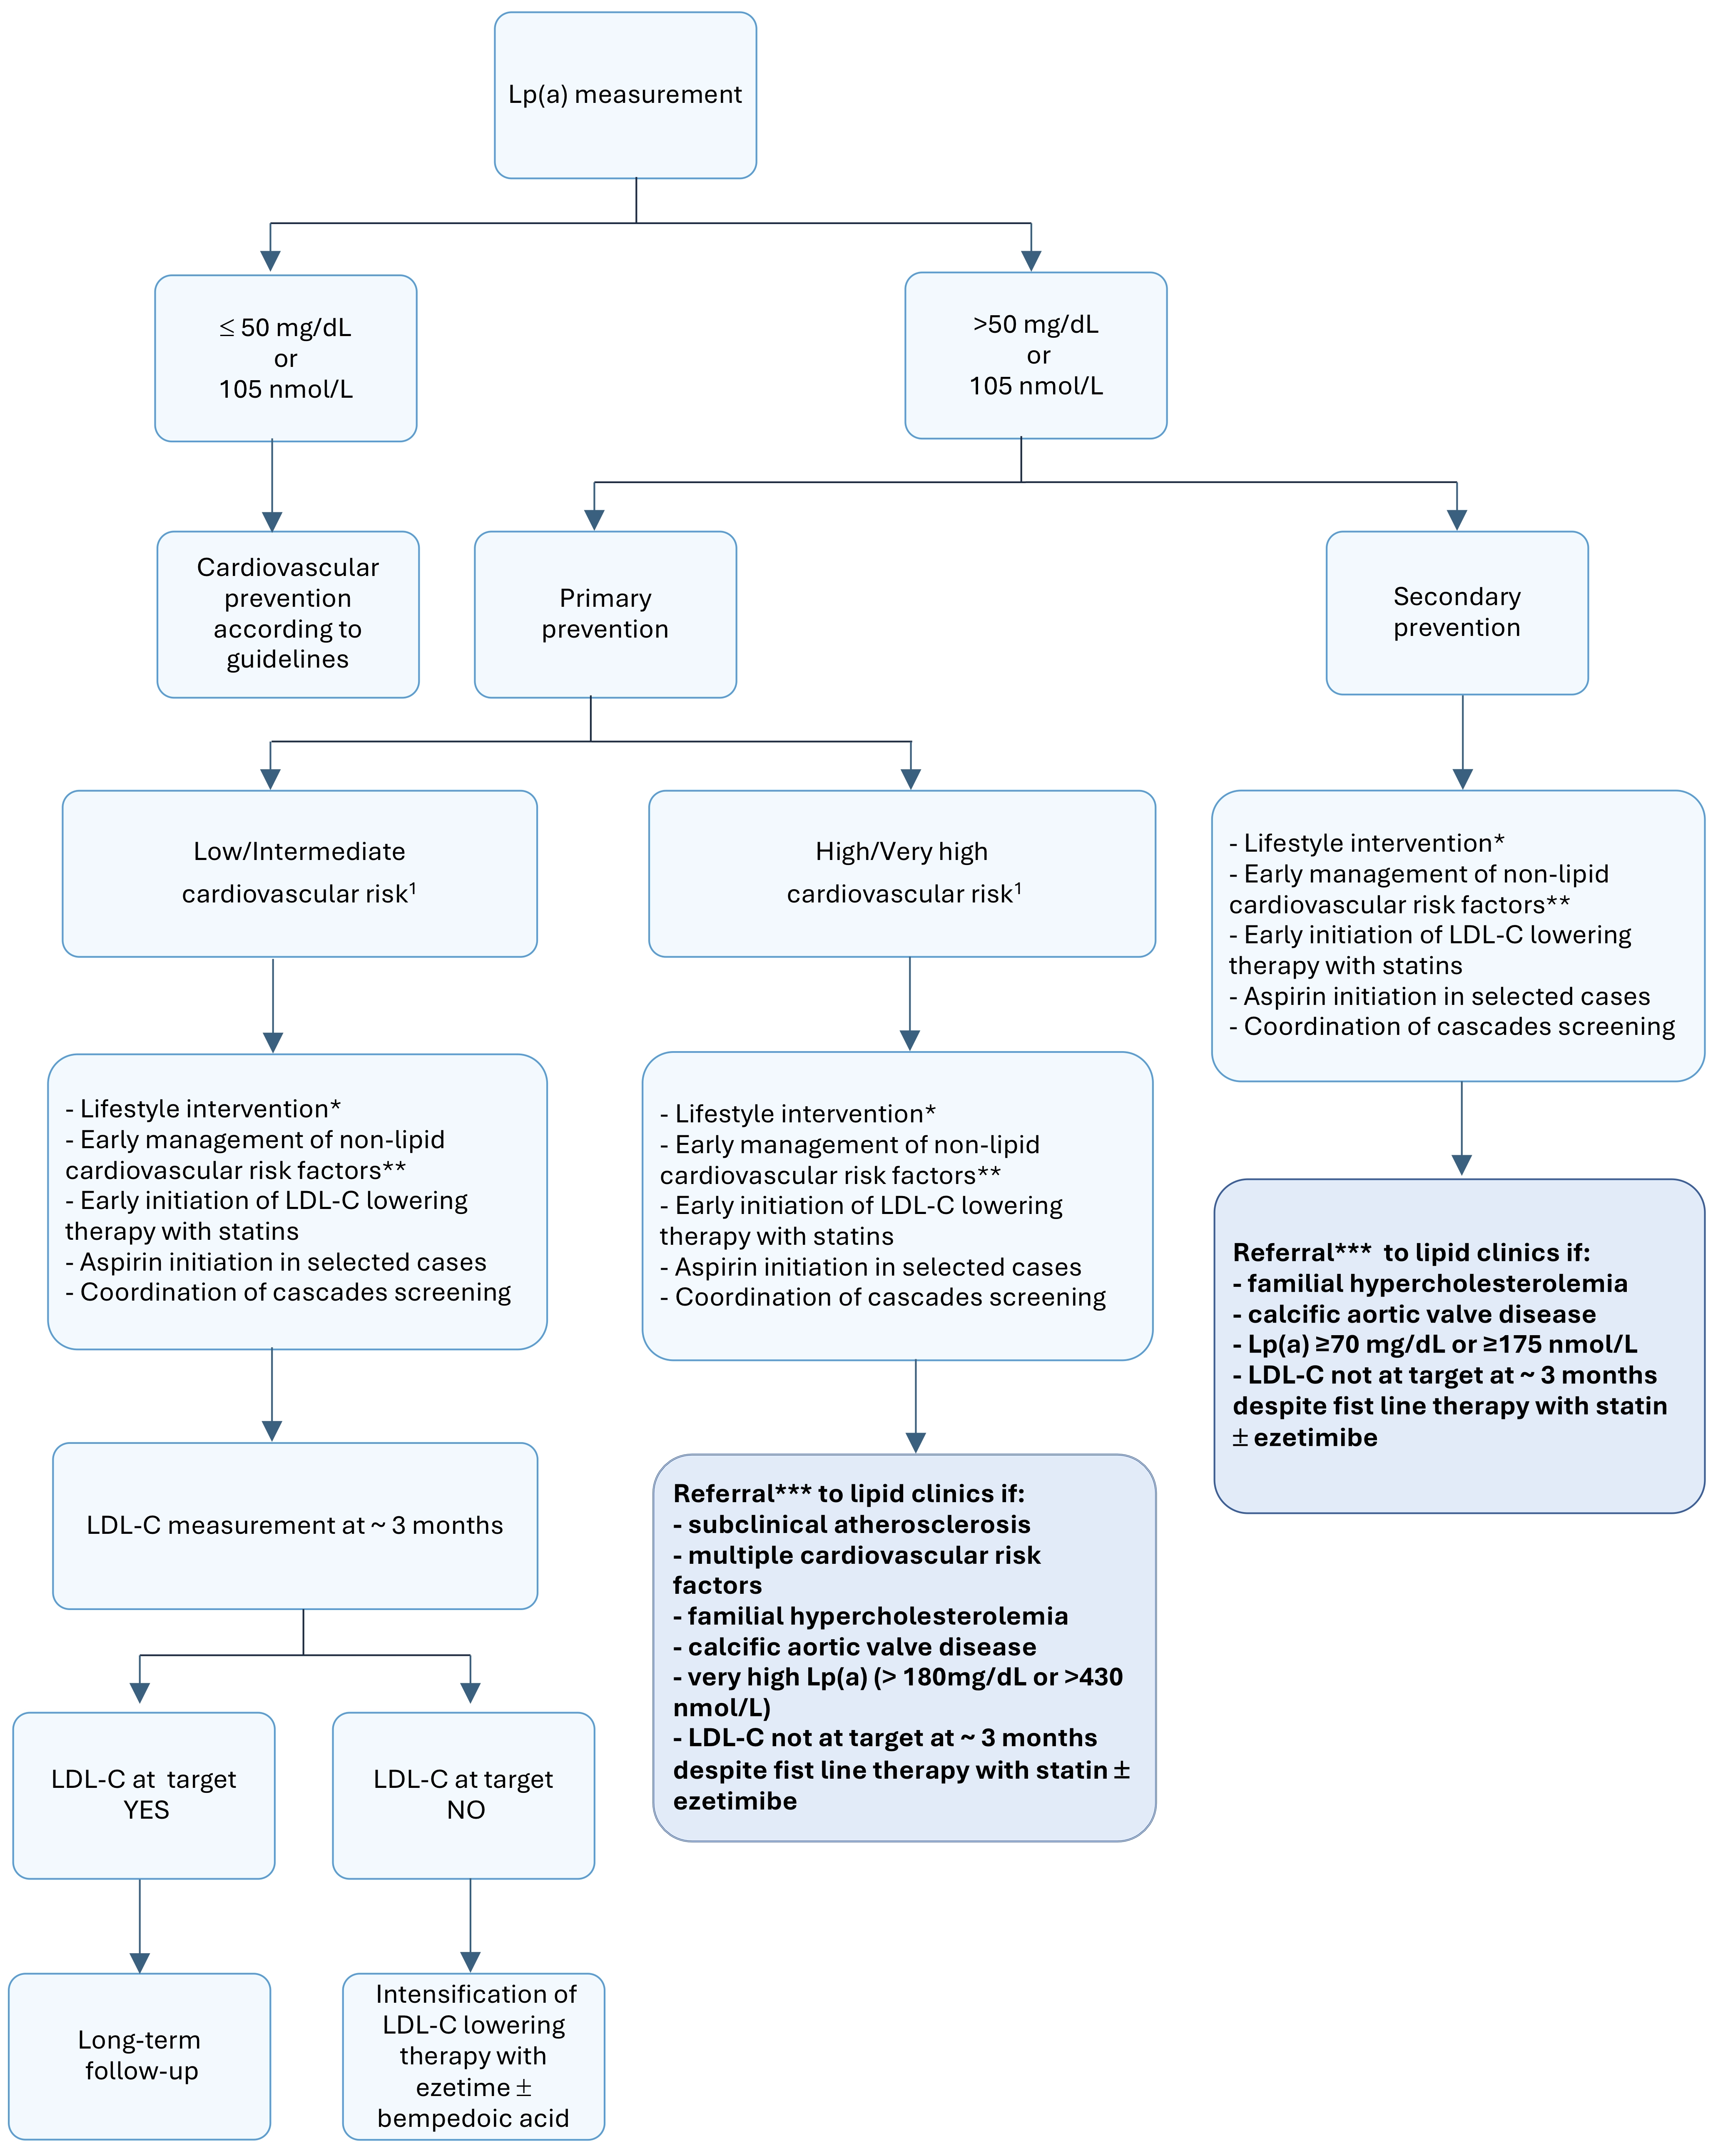
Figure 1. Primary care-to-lipid clinics referral algorithm for elevated Lp(a). Use Lp(a) > 50 mg/dL or > 105 nmol/L as a cardiovascular risk modifier; * Smoking cessation, healthful diet, physical activity; ** blood pressure control, glycemic control; *** aimed at optimizing lipid-lowering therapy (e.g., PCSK9i; lipoprotein apheresis), evaluating eligibility for ongoing randomized clinical trials, and planning appropriate follow-up. Lp(a): lipoprotein(a); LDL-C: low-density lipoprotein cholesterol.
Several investigational pharmacological approaches selectively targeting Lp(a) are currently under development, among which four have reached phase 3 (i.e., pelacarsen, olpasiran, lepodisiran, and muvalaplin). Pelacarsen (TQJ230), an antisense oligonucleotide targeting LPA mRNA, achieved Lp(a) reductions of ~ 80% in phase 2[31] and was being tested in the Lp(a)HORIZON outcome trial (ClinicalTrials.gov ID: NCT04023552) in patients with Lp(a) ≥ 70 mg/dL and a history of atherosclerotic cardiovascular disease. The study was completed on 16 July 2026, and a subsequent sponsor announcement preliminarily reported that the trial did not meet its primary endpoint[32]. However, detailed results and their full scientific interpretation have not yet been published. Therefore, the implications of these findings for the clinical impact of Lp(a) lowering and its translation into cardiovascular risk reduction remain to be fully elucidated. The complete results of Lp(a)HORIZON, together with data from other ongoing therapeutic programs targeting Lp(a), are still awaited. Olpasiran (AMG890), a small interfering RNA targeting LPA mRNA, achieved Lp(a) reductions of up to 95% in phase 2[33] and is being evaluated in the OCEAN(a)-Outcomes trial (ClinicalTrials.gov ID: NCT05581303) in patients with Lp(a) > 200 nmol/L and a history of atherosclerotic cardiovascular disease. Lepodisiran, a long-lasting small interfering RNA targeting LPA mRNA, achieved Lp(a) reductions of up to 94-95% in phase 2[34] and is being studied in the ACCLAIM-Lp(a) outcome trial in patients with Lp(a) ≥ 175 nmol/L and a history of or being at risk for atherosclerotic cardiovascular disease (ClinicalTrials.gov ID: NCT06292013). Muvalaplin, the first oral small molecule inhibitor of Lp(a) assembly, produced substantial reductions in Lp(a) levels in phase 2, with an 85-86% decrease when quantified using intact Lp(a) immunoassays, compared with approximately a 70% reduction when measured with apo(a)-based immunoassays, representing an assay dependent discordance that provides a practical illustration of the analytical considerations discussed in Table 2. Muvalaplin is currently being evaluated in the MOVE-Lp(a) cardiovascular outcome trial in patients with Lp(a) ≥ 175 nmol/L and a history of or being at risk for atherosclerotic cardiovascular disease (NCT07157774)[35]. If positive results emerge from ongoing outcome trials, it will finally be possible to determine whether, and in which patients, the selective reduction of Lp(a) might become a new cardiovascular prevention option. Thus, general practitioners are called to action in conjunction with lipid clinics to bring eligible patients into view, thereby contributing to bridging the existing gap in the implementation of cardiovascular risk management in patients with elevated Lp(a).
5. Conclusions
Current and emerging evidence on the pathogenic and clinical significance of Lp(a) demands a shift from theoretical awareness to practical implementation. Although important uncertainties persist regarding measurement, interpretation, and treatment, the evidence base is now sufficiently mature to justify systematic integration of Lp(a) into cardiovascular risk assessment pathways. Measuring Lp(a) at least once in adult life as well as in other selected clinical conditions, interpreting results within a pragmatic risk-based framework, and adopting a structured management strategy represent actionable steps that clinicians can implement immediately. In this context, the role of general practitioners working in collaboration with lipid clinics is pivotal. Indeed, a coordinated approach can ensure that elevated Lp(a) is incorporated thoughtfully into individualized cardiovascular risk stratification and that patients with elevated Lp(a) receive transparent communication regarding the implications of their Lp(a) level and the actionable management of this condition in current practice. In addition, the possible arrival of specific Lp(a)-lowering agents, which are poised to transform clinical practice, requires strengthening referral pathways between primary care physicians, who are called to proactively identify patients with elevated Lp(a), and lipid clinics, which can offer specialist expertise, including early access to clinical trials. Such an integrated approach represents a strategic opportunity to expand cardiovascular prevention by managing the residual cardiovascular risk driven by Lp(a) (Figure 2).
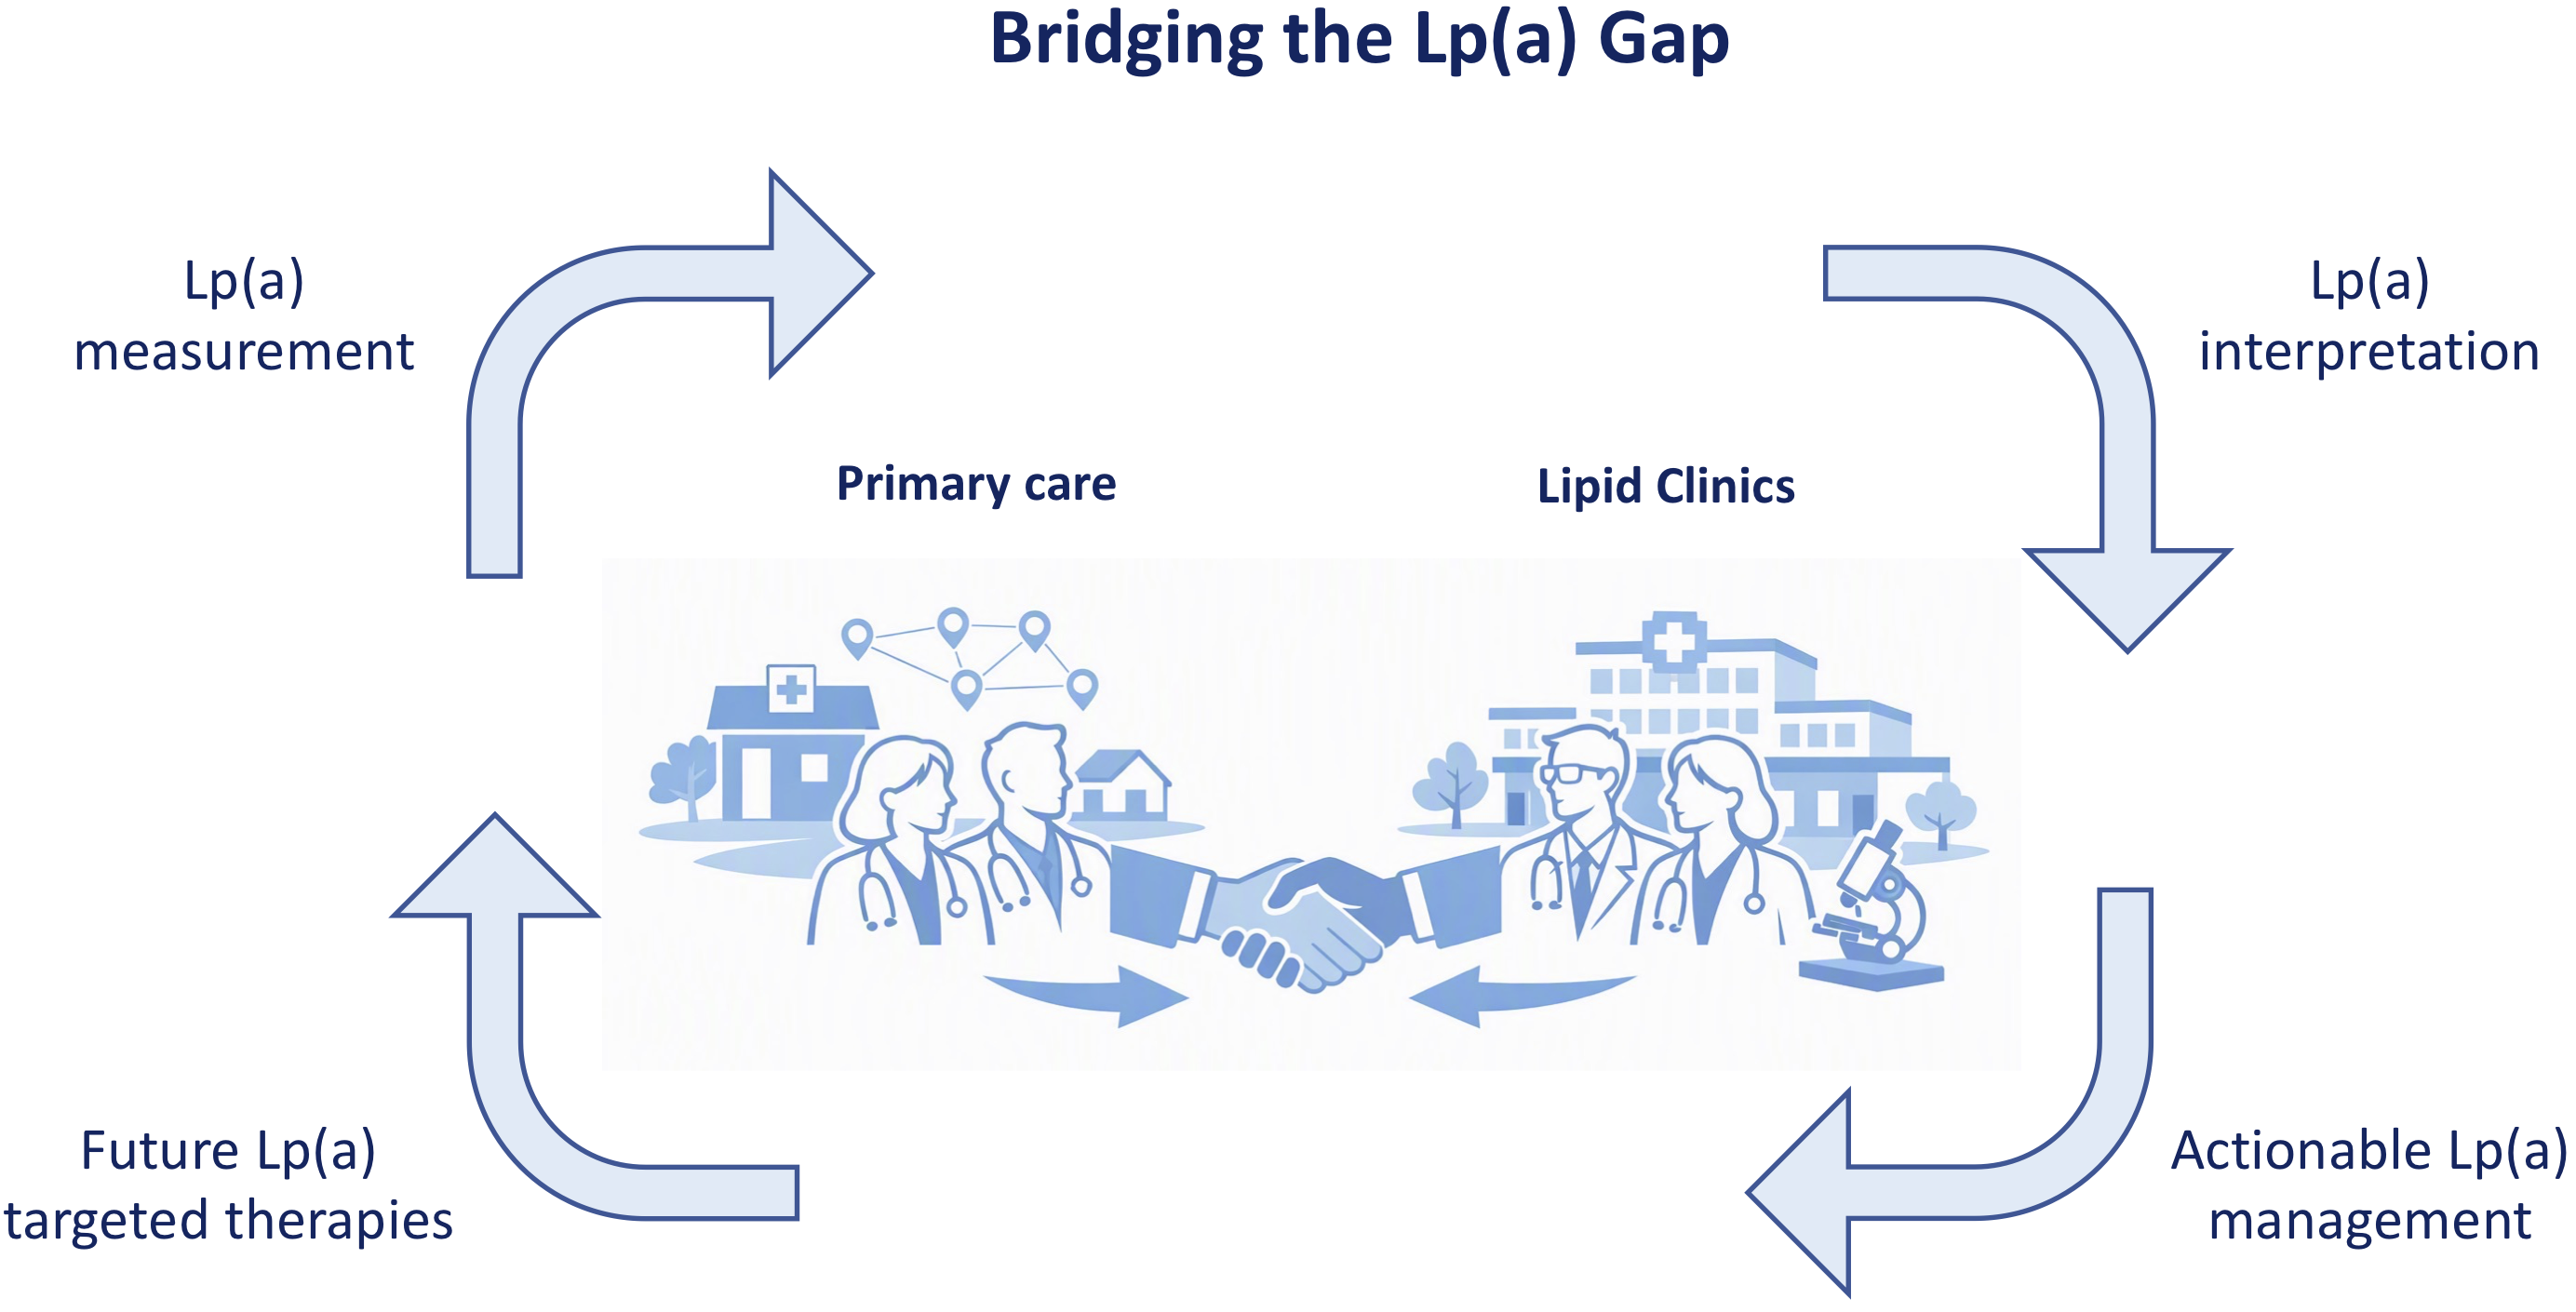
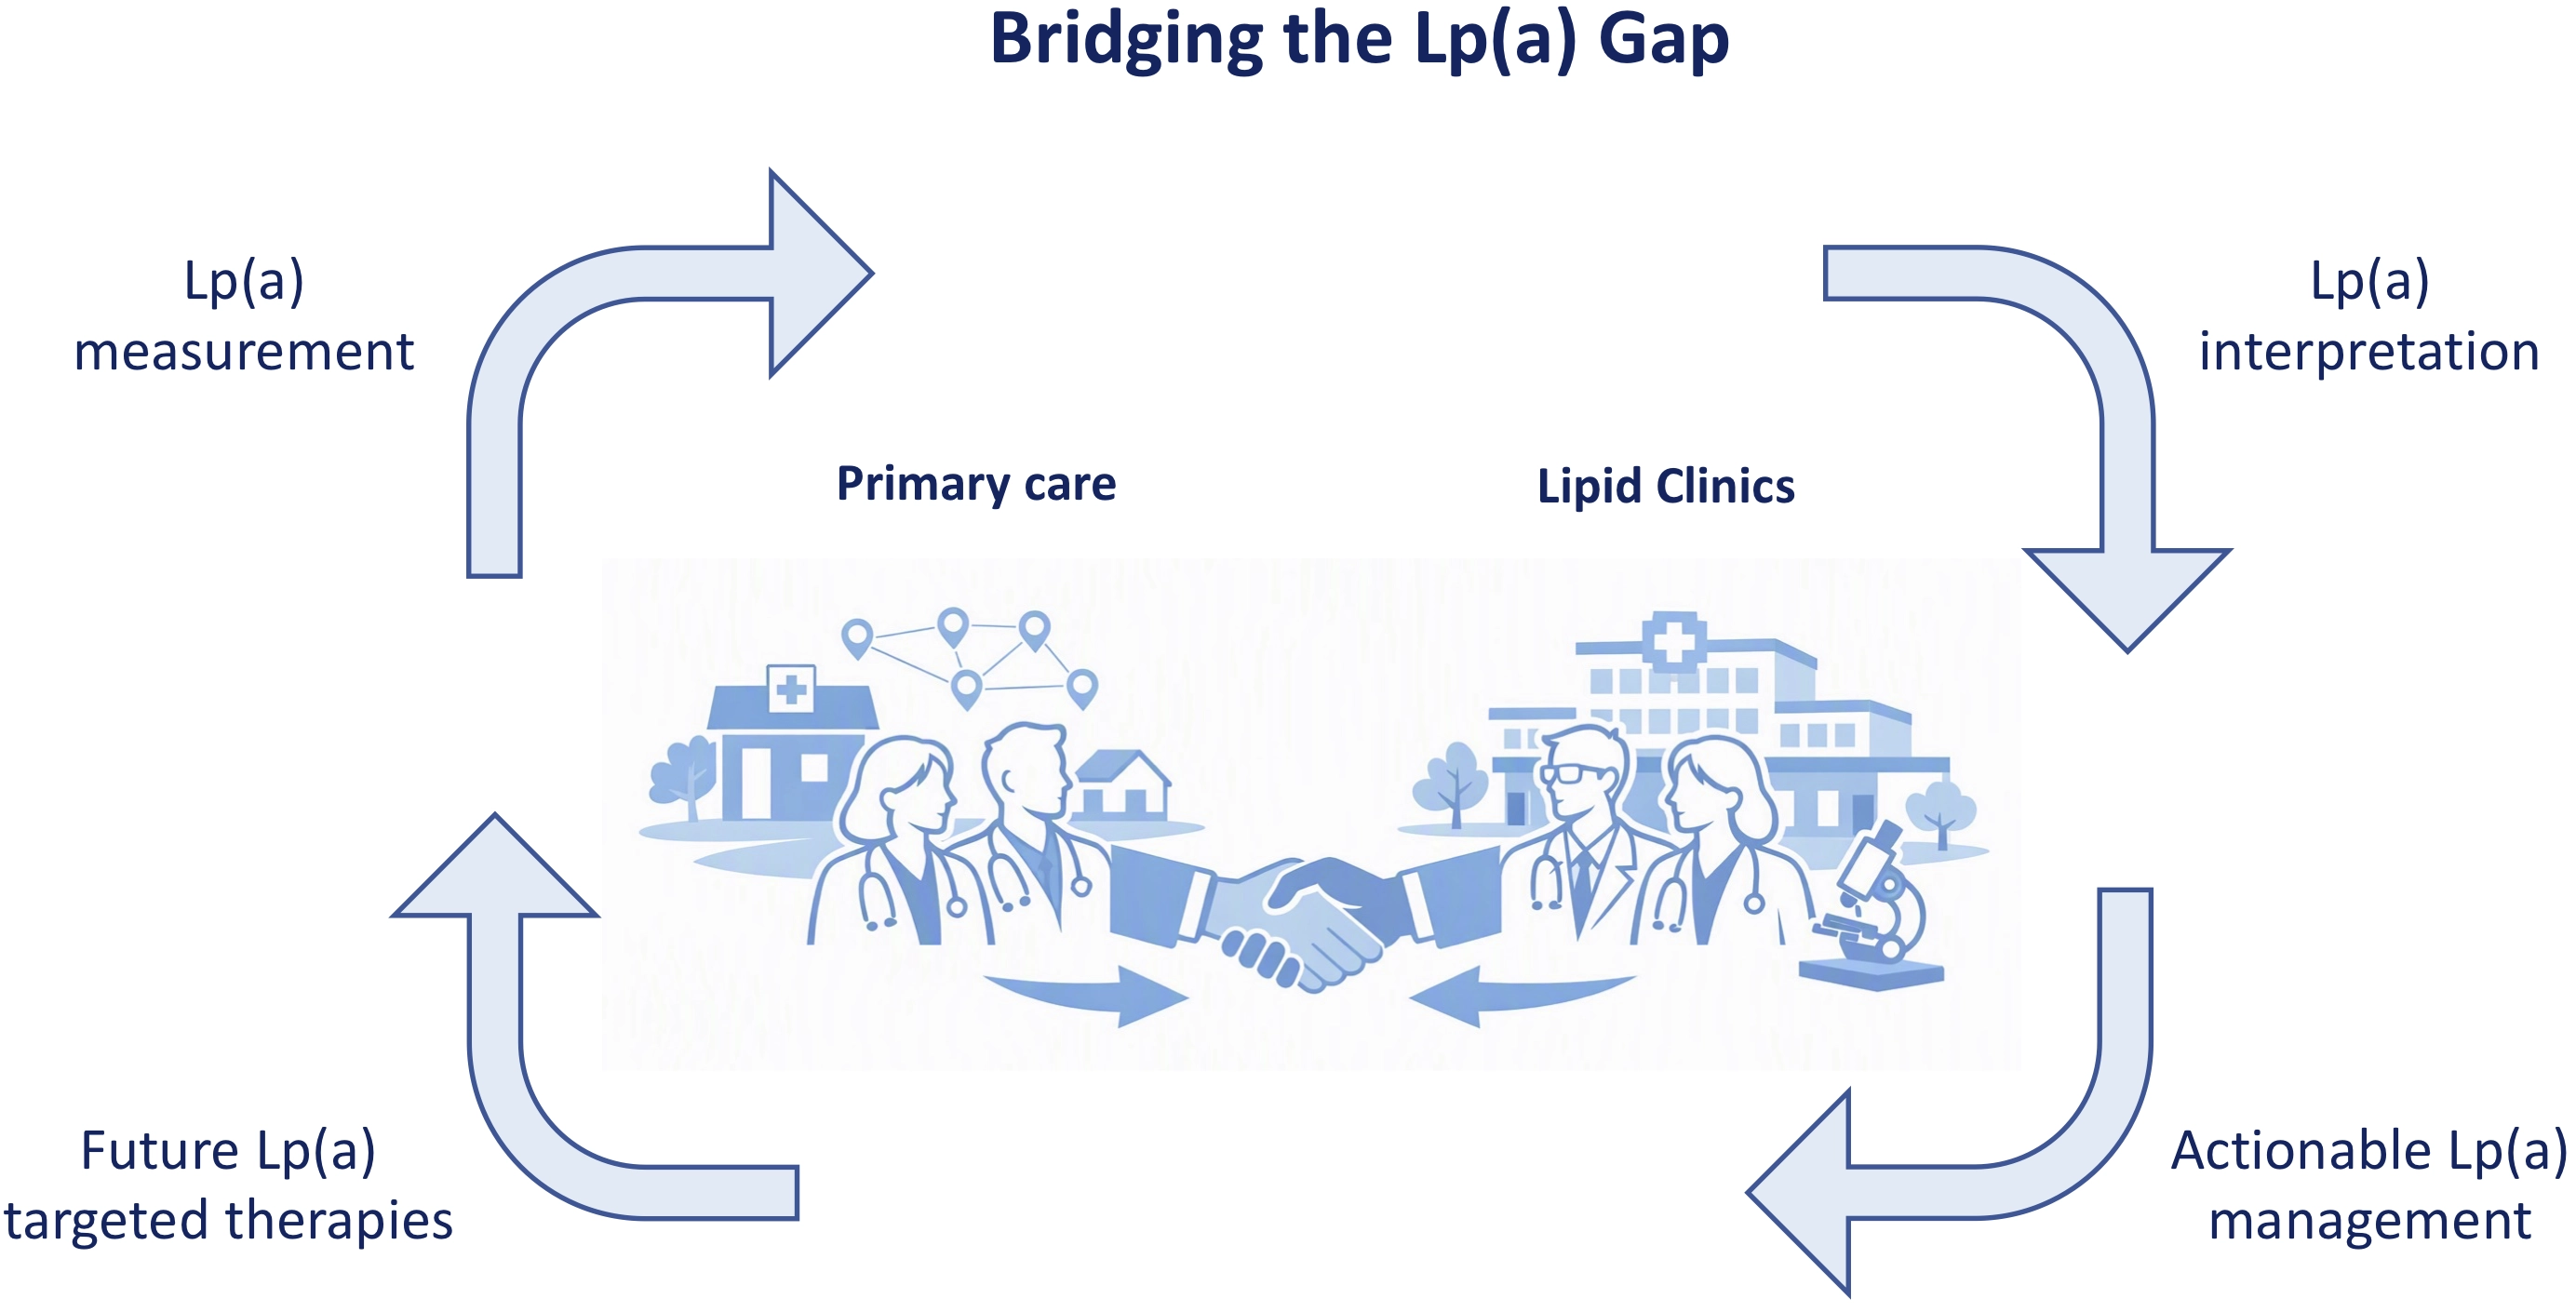
Figure 2. Implementation of Lp(a) clinical pathway. In the clinical workflow ranging from Lp(a) measurement to access to Lp(a)-targeted therapies, the collaborative interaction between clinicians operating in primary care and lipid clinics represents a key point for implementing patient care and optimizing cardiovascular risk management. Lp(a): lipoprotein(a).
Authors contribution
Bianconi V, Tasegian P, Pirro M: Conceptualization, writing-original draft, writing-review & editing.
Conflicts of interest
Vanessa Bianconi is the Youth Editorial Board member of Advances in Lipoprotein(a) Research. The other authors declare no conflicts of interest.
Ethical approval
Not applicable.
Consent to participate
Not applicable.
Consent for publication
Not applicable.
Availability of data and materials
Not applicable.
Funding
None.
Copyright
© The Author(s) 2026.
References
-
6. Reyes-Soffer G, Ginsberg HN, Berglund L, Duell PB, Heffron SP, Kamstrup PR, et al. Lipoprotein(a): A genetically determined, causal, and prevalent risk factor for atherosclerotic cardiovascular disease: A scientific statement from the American heart association. Arterioscler Thromb Vasc Biol. 2022;42(1):e48-e60.
-
7. Reyes-Soffer G, Ginsberg HN, Berglund L, Duell PB, Heffron SP, Kamstrup PR, et al. Lipoprotein(a): A genetically determined, causal, and prevalent risk factor for atherosclerotic cardiovascular disease: A scientific statement from the American Heart Association. Arterioscler Thromb Vasc Biol. 2022;42(1):e48-e60.
-
8. Blumenthal RS, Morris PB, Gaudino M, Johnson HM, Anderson TS, Bittner VA, et al. 2026 ACC/AHA/AACVPR/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA guideline on the management of dyslipidemia: A report of the American college of cardiology/American heart association joint committee on clinical practice guidelines. J Am Coll Cardiol. 2026;87(19):2624-2757.
-
25. Khera AV, Everett BM, Caulfield MP, Hantash FM, Wohlgemuth J, Ridker PM, et al. Lipoprotein(a) concentrations, rosuvastatin therapy, and residual vascular risk: an analysis from the JUPITER Trial (Justification for the Use of Statins in prevention: An intervention trial evaluating rosuvastatin). Circulation. 2014;129(6):635-642.
-
32. Novartis. Novartis announces Lp(a)HORIZON Phase III topline results for pelacarsen in patients with elevated Lp(a) and established cardiovascular disease (CVD) [Internet]. 2026. Available from: https://www.novartis.com/news/media-releases/novartis-announces-lpahorizon-phase-iii-topline-results-pelacarsen-patients-elevated-lpa-and-established-cardiovascular-disease-cvd
Copyright
© The Author(s) 2026. This is an Open Access article licensed under a Creative Commons Attribution 4.0 International License (https://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, sharing, adaptation, distribution and reproduction in any medium or format, for any purpose, even commercially, as long as you give appropriate credit to the original author(s) and the source, provide a link to the Creative Commons license, and indicate if changes were made.
Publisher’s Note
Science Exploration remains a neutral stance on jurisdictional claims in published
maps
and institutional affiliations. The views expressed in this article are solely those
of
the author(s) and do not reflect the opinions of the Editors or the publisher.
Share And Cite


Science Exploration Style
Bianconi V, Tasegian P, Pirro M. The Lp(a) gap: Practical steps to align primary care and lipid clinics. Adv Lipoprotein(a) Res. 2026;1:202613. https://doi.org/10.70401/alr.2026.0010
Tips
Copy completed.
Submit a Manuscript
Author Instructions
Cite this Article
Article Metrics
0
View
0
Download
Cited
Article Updates

- Abstract
- Keywords
- 1. Introduction
- 2. Measurement of Lp(a)
- 3. Interpretation of Lp(a) Measurement
- 4. Actionable Management of Elevated Lp(a) in the Absence of Specific Lp(a)-Lowering Drugs
- 5. Conclusions
- Authors contribution
- Conflicts of interest
- Ethical approval
- Consent to participate
- Consent for publication
- Availability of data and materials
- Funding
- References
- Copyright
 Get citation
Science Exploration Style

Bianconi V, Tasegian P, Pirro M. The Lp(a) gap: Practical steps to align primary care and lipid clinics. Adv Lipoprotein(a) Res. 2026;1:202613. https://doi.org/10.70401/alr.2026.0010
copy
Share Link
copy