Extracellular landscape of ferroptosis: A new direction to enhance anti-tumor efficacy

Wanxin Guo
1,2,#

,
Lei Qian
1,2,#
,
Susu Guo
1
,
Shiyu Qiu
1
,
Xiangfei Xue
1
,
Lifang Ma
1,2,3
,
Xiao Zhang
2
,
Yongchun Yu
2,*
,
Jiayi Wang
1,2,3,*
*Correspondence to:
Yongchun Yu, Shanghai Institute of Thoracic Oncology, Shanghai Chest Hospital, Shanghai Jiao Tong University School of Medicine, Shanghai 200030, China.
E-mail: yyc2166@sjtu.edu.cn
Jiayi Wang, Department of Clinical Laboratory, Shanghai Chest Hospital, Shanghai Jiao Tong University School of Medicine, Shanghai 200030, China; Shanghai Institute of Thoracic Oncology, Shanghai Chest Hospital, Shanghai Jiao Tong University School of Medicine, Shanghai 200030, China; Medical Science Laboratory, College of Health Science and Technology, Shanghai Jiao Tong University School of Medicine, Shanghai 200025, China. E-mail: Jiayi.wang@sjtu.edu.cn
Jiayi Wang, Department of Clinical Laboratory, Shanghai Chest Hospital, Shanghai Jiao Tong University School of Medicine, Shanghai 200030, China; Shanghai Institute of Thoracic Oncology, Shanghai Chest Hospital, Shanghai Jiao Tong University School of Medicine, Shanghai 200030, China; Medical Science Laboratory, College of Health Science and Technology, Shanghai Jiao Tong University School of Medicine, Shanghai 200025, China. E-mail: Jiayi.wang@sjtu.edu.cn
Ferroptosis Oxid Stress. 2027;3:202629. 10.70401/fos.2026.0047
Received: June 15, 2026Accepted: September 30, 2026Published: September 30, 2026
Abstract
Ferroptosis is an iron-dependent form of regulated cell death driven by the lethal accumulation of lipid peroxides. Accumulating evidence indicates that the extracellular landscape, the acellular functional subset of the tumor microenvironment (TME) comprising the extracellular matrix, soluble metabolites, cytokines, extracellular vesicles (EVs), and physicochemical conditions such as pH and oxygen content, actively determines cellular susceptibility to ferroptosis. Extracellular nutrients, acidic and hypoxic conditions modulate intracellular redox homeostasis, while ferroptosis-related signals are transmitted between cells through EVs, cytokines, and metabolites. Ferroptosis in turn bidirectionally shapes anti-tumor immunity, acting as immunogenic cell death yet also releasing immunosuppressive mediators that impair T cells. This review summarizes the canonical intracellular mechanisms of ferroptosis, highlights the bidirectional crosstalk between cells and the extracellular landscape, and discusses therapeutic strategies targeting this landscape, including reshaping nutrient availability, engineering EV-based delivery systems, and designing microenvironment-responsive nanomaterials. Key limitations of the field and perspectives are also outlined for safe and effective ferroptosis-based anti-tumor therapies.
Keywords
Ferroptosis, extracellular landscape, tumor microenvironment, anti-tumor immunity
1. Introduction
Since its formal identification in 2012, ferroptosis has emerged as a pivotal form of regulated cell death (RCD) characterized by iron-dependent accumulation of lethal lipid peroxides[1,2]. The core biochemical events of ferroptosis include the Fenton reaction catalyzed by labile iron, the peroxidation of polyunsaturated fatty acid-containing phospholipids (PUFA-PLs), and the failure of antioxidant defense systems, primarily the glutathione (GSH)-glutathione peroxidase 4 (GPX4) axis[1-4].
Unlike other RCD modalities such as apoptosis and pyroptosis, ferroptosis is essentially a metabolic imbalance-driven cell death pathway that is highly sensitive to perturbations in the cellular metabolic microenvironment[3,5]. The metabolic alterations accompanying metabolic reprogramming in tumor cells profoundly influence their susceptibility to ferroptosis, making this process a critical target for overcoming current bottlenecks in anti-tumor therapy. Certain poor-prognosis tumors upregulate PUFA-PLs, rendering them more susceptible to ferroptosis induction[6,7]. Importantly, resistance to many first-line anticancer drugs has been shown to be closely associated with decreased ferroptosis sensitivity[8-10]. Combining standard chemotherapeutics with ferroptosis inducers or antioxidant defense inhibitors produces significant synergistic anti-tumor effects both in vivo and in vitro[11,12]. Collectively, ferroptosis-based intervention strategies are gaining increasing clinical relevance in comprehensive cancer therapy.
Accumulating evidence suggests that the fate of a cell is profoundly influenced by its surrounding milieu. The tumor microenvironment (TME) is defined as a complex, dynamic, and heterogeneous ecosystem that surrounds and acts upon malignant cells[13]. Rather than being a passive structural scaffold, the TME actively participates in tumor initiation, progression, metastasis, and therapeutic responses[13]. It comprises diverse cellular components, such as immune cells and stromal cells, as well as a variety of acellular components, which engage in extensive crosstalk to establish a microenvironment that supports tumor cell survival. Building upon this overarching TME framework, we propose the concept of the extracellular landscape, which we define as a functionally oriented non-cellular subset of the TME. Distinct from the TME, which encompasses all cellular components, the extracellular landscape is composed of components secreted or released into the extracellular space by tumor cells, immune cells, and stromal cells, including the extracellular matrix, soluble metabolites, cytokines, extracellular vesicles (EVs), and physicochemical conditions such as pH and oxygen content. Serving as a medium for intercellular communication, the extracellular landscape conveys the metabolic and signaling states of donor cells to neighboring or even distant recipient cells, thereby fundamentally mediating and regulating cellular signal transduction and metabolic interactions within the TME. Recent studies have revealed that specific factors within the extracellular landscape directly determine cellular susceptibility to ferroptosis[14-17]. Furthermore, the crosstalk orchestrated by the extracellular landscape reveals a dual role in modulating anti-tumor immunity, with ferroptosis either activating or suppressing immune responses depending on the signaling cues released into the microenvironment.
This review aims to integrate intracellular metabolic pathways and extracellular environmental cues. We summarize the canonical intracellular mechanisms of ferroptosis and explore the critical role of intercellular communication. Finally, we propose a novel therapeutic strategy of targeting the extracellular landscape. By modulating nutrient availability, engineering extracellular vesicles for drug delivery, or utilizing microenvironment-responsive nanomaterials, we can potentially overcome the limitations of current therapies and maximize the efficacy of ferroptosis-based anti-tumor strategies.
2. Intracellular Molecular Mechanism of Ferroptosis
Ferroptosis is an emerging form of RCD triggered by intracellular redox imbalance, which is pathologically defined by iron overload and excessive lipid peroxidation[1,2]. Excess ferrous iron (Fe2+) catalyzes the Fenton reaction to generate toxic hydroxyl radicals, which peroxidize PUFA-PLs and disrupt membrane integrity, leading to cell death[2]. Distinct from caspase-dependent apoptosis, ferroptosis is tightly regulated by coordinated iron and lipid pathways as well as other metabolism pathways that govern reactive oxygen species (ROS) production and peroxidation substrate availability (Figure 1)[3,5].
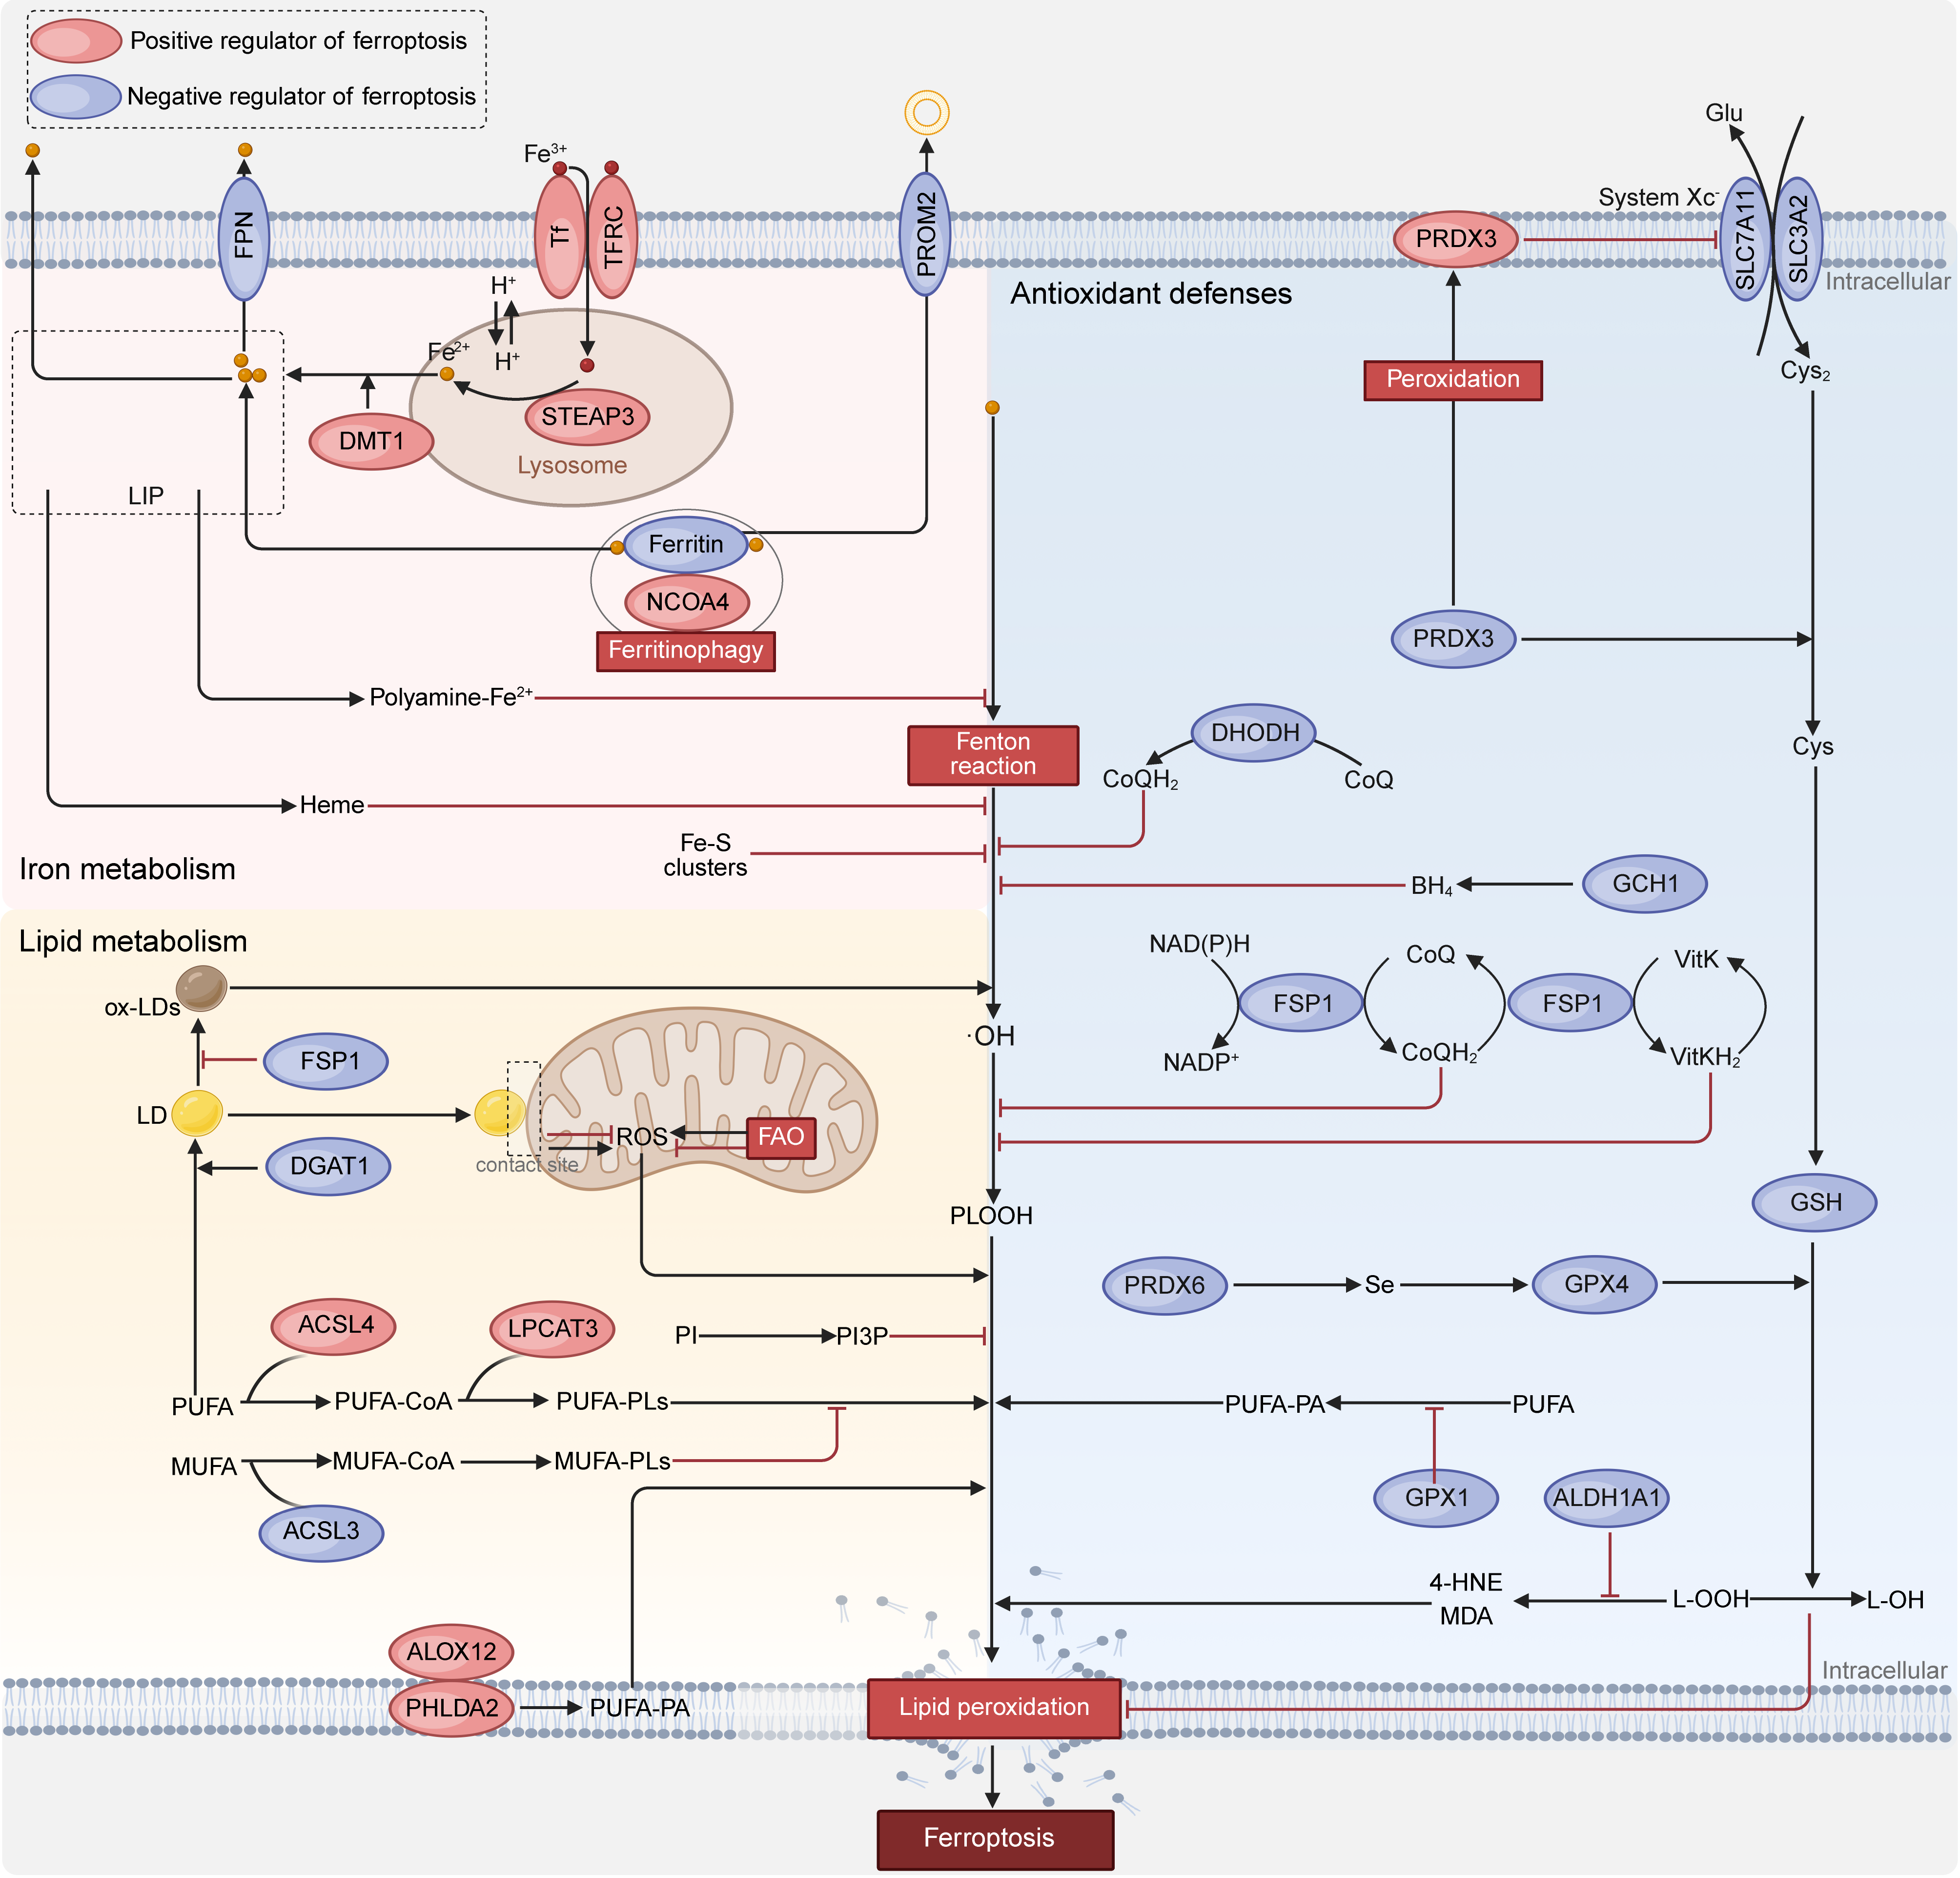
Figure 1. Intracellular regulatory network of ferroptosis. The key intracellular pathways governing ferroptosis encompass iron metabolism, lipid peroxidation, and antioxidant defense systems. Iron metabolism, including iron uptake, export, storage, ferritinophagy and mitochondrial iron metabolism, jointly controls the level of the intracellular LIP and provides iron for the Fenton reaction. Lipid-metabolism-related pathways, such as ACSL4-LPCAT3-mediated PUFA-PL synthesis and ALOX12-PHLDA2-dependent PUFA-PA production, generate substrates for lipid peroxidation, whereas LD metabolism and FAO affect PL-OOH abundance. Antioxidant-defense systems consist of the core SLC7A11-GPX4 axis, DHODH-CoQH2, FSP1-CoQH2, the GCH1-BH4 axis, and additional non-canonical antioxidant proteins. Created in BioRender. Guo, Y. (2026) https://BioRender.com/qja4b3b. FPN: ferroportin; DMT1: divalent metal transporter 1; Tf: transferrin; TFRC: transferrin receptor; STEAP3: six-transmembrane epithelial antigen of the prostate 3; NCOA4: nuclear receptor coactivator 4; LDs: lipid droplets; DGAT1: diacylglycerol O-acyltransferase 1; ACSL4: long-chain-fatty-acid-CoA ligase 4; ACSL3: long-chain-fatty-acid-CoA ligase 3; ROS: reactive oxygen species; FAO: fatty acid β-oxidation; LPCAT3: lysophosphatidylcholine acyltransferase 3; PI: phosphatidylinositol; PI3P: phosphatidylinositol-3-phosphate; PUFA: polyunsaturated fatty acid; PLs: phospholipids; MUFA: monounsaturated fatty acid; ALOX12: arachidonate 12-lipoxygenase; PHLDA2: pleckstrin homology-like domain family A member 2; PA: phosphatidic acid; PLOOH: phospholipid hydroperoxides; DHODH: dihydroorotate dehydrogenase; CoQ: coenzyme Q; Cys: cysteine; BH4: tetrahydrobiopterin; GCH1: GTP cyclohydrolase 1; NADPH: nicotinamide adenine dinucleotide phosphate; FSP1: ferroptosis suppressor protein 1; VitK: vitamin K; ALDH1A1: aldehyde dehydrogenase 1A1; 4-HNE: 4-hydroxy-2-nonenal; MDA: malondialdehyde; L-OOH: lipid hydroperoxides; GPX4: glutathione peroxidase 4.
2.1 Iron metabolism
The Fenton reaction driven by Fe2+ is a prerequisite for ferroptosis[1]. Therefore, cellular iron uptake and metabolism are particularly critical. Transferrin (Tf) carrying ferric ions (Fe3+) binds to the transferrin receptor (TFRC) and enters cells via clathrin-dependent endocytosis[18,19]. Within lysosomes, Fe3+ is reduced to Fe2+ by six-transmembrane epithelial antigen of the prostate 3 (STEAP3) and subsequently released into the cytoplasm through divalent metal transporter 1 (DMT1), supplying Fe2+ for the Fenton reaction and hydroxyl radical (•OH) generation[20,21]. The iron requirements for ferroptosis vary depending on the inducing stimulus. GPX4-deficient cells can undergo ferroptosis with basal iron levels, while Cys2 starvation-induced ferroptosis highly relies on exogenous Fe3+ uptake[19].
Lysosomes serve as a major intracellular iron reservoir, and their functional status governs ferroptosis sensitivity[22,23]. The acidic lysosomal environment at pH 4.5-5.0 is maintained by V-type H+-ATPase-mediated proton influx together with proton leakage through TMEM175 and the SLC7A11-SLC3A2 complex[23,24]. Disrupted proton homeostasis drives lysosomal iron leakage into the cytosol and fuels Fenton chemistry.
Ferritin, assembled from ferritin heavy chain (FTH) and ferritin light chain (FTL) subunits, represents another primary iron-storage complex[25]. Nuclear receptor coactivator 4 (NCOA4)-mediated ferritinophagy degrades ferritin to release free Fe2+ and thus promotes ferroptosis[26]. Besides ferritin-dependent iron sequestration, polyamines function as intracellular iron chelators to sequester labile Fe2+, curtailing the Fenton reaction and conferring ferroptosis resistance[27,28].
Mitochondrial iron homeostasis also influences labile iron pool (LIP). Cytosolic iron influx into mitochondria expands the mitochondrial LIP and aggravates ferroptosis risk[29,30]. Mitochondrial ferritin (FtMt) sequesters mitochondrial iron, while iron is also consumed for iron-sulfur (Fe-S) cluster and heme biosynthesis[31-33]. Therefore, impaired Fe-S cluster or heme metabolism increases ferroptosis susceptibility. As for iron export, ferroportin (FPN) mediates free iron efflux, whereas prominin-2 (PROM2) exports ferritin via exosome secretion to lower cellular iron load[17,34].
Taken together, LIP abundance is dynamically tuned by iron uptake, storage, mitochondrial metabolism and efflux. Targeting these processes provides feasible strategies to modulate ferroptosis sensitivity.
2.2 Lipid metabolism
Lipid peroxidation constitutes the core biochemical event of ferroptosis, in which PUFA-PLs act as major oxidation substrates. In the canonical long-chain-fatty-acid-CoA ligase 4 (ACSL4)-dependent cascade, ACSL4 converts free PUFAs to acyl-CoA esters, which are further incorporated into membrane PLs such as phosphatidylethanolamine (PE) and phosphatidylcholine (PC) by lysophosphatidylcholine acyltransferase 3 (LPCAT3). Arachidonic acid (AA)- and adrenic acid (AdA)-enriched PE/PC are vulnerable to Fenton-derived hydroxyl radicals (•OH), generating cytotoxic phospholipid hydroperoxides (PL-OOH) and causing membrane rupture[2,35,36]. By contrast, long-chain-fatty-acid-CoA ligase 3 (ACSL3)-produced monounsaturated fatty acids (MUFAs) competitively replace membrane-embedded PUFAs and partially counteract ferroptosis[15,37,38]. Multiple PL classes, including phosphatidylserine (PS), phosphatidylinositol (PI) and cardiolipin (CL) can also serve as peroxidation substrates, while certain PI-derived metabolites such as phosphatidylinositol-3-phosphate (PI3P) exert protective effects against membrane damage[35,36,39].
Lipoxygenase (LOX)-dependent oxidation drives non-canonical ferroptosis. Arachidonate 12-lipoxygenase (ALOX12), recruited by pleckstrin homology-like domain family A member 2 (PHLDA2), directly oxidizes phosphatidic acid (PA)-bound PUFAs to trigger ferroptosis[40].
Fatty acids (FAs) can be synthesized de novo or obtained through dietary intake of essential FAs. The de novo fatty acid synthesis (DNL) pathway primarily contributes to the production of both saturated fatty acids (SFAs) and MUFAs[41,42]. Since mammals lack Δ12 and Δ15 desaturases, PUFA precursors such as linoleic acid can only be obtained from dietary intake for PUFA synthesis[43]. These precursors are then gradually converted into PUFAs such as AA and AdA via the actions of enzymes like acyl-CoA 6-desaturase (FADS2) and elongation of very long chain fatty acid elongase 5 (ELOVL5)[44,45].
Lipid droplets (LDs) exert context-dependent regulatory effects on ferroptosis. LDs sequester PUFAs into triacylglycerides (TAGs) to reduce membrane-peroxidation substrates[46-48]. Diacylglycerol O-acyltransferase 1/2 (DGAT1/2)-driven LD biogenesis protects GPX4-deficient tumor cells, whereas TAG lipolysis releases stored PUFAs and facilitates ferroptosis[49-51]. Nevertheless, PUFA-rich LDs themselves are peroxidation-prone[48,52,53]. LD-localized ferroptosis suppressor protein 1 (FSP1) maintains the protective effects of LDs by converting coenzyme Q (CoQ) to the antioxidant CoQH2. Upon FSP1 dysfunction, PUFA-laden LDs become peroxidation substrates and aggravate ferroptosis[48]. LD-mitochondria contacts further shape cellular outcomes. MYC-driven contacts shuttle FAs to mitochondria for catabolism and suppress ferroptosis[53]. However, under nutrient deprivation or accumulation of oxidized TAGs, the activated AMPK pathway enhances such contacts to transfer peroxidizable lipids to mitochondria and mitochondria-associated endoplasmic reticulum (ER) compartments, resulting in propagated oxidative damage[51,54].
As one of the primary pathways for FA degradation, fatty acid β-oxidation (FAO) exhibits dual and context-dependent functions in ferroptosis. FAO can consume PUFA substrates and support mitochondrial fitness to restrict ferroptosis. Conversely, FAO-associated electron leakage generates mitochondrial ROS, and excessive FAO accelerates mitochondrial lipid peroxidation to amplify ferroptotic signals[53,55-57].
Collectively, lipid metabolism exerts context-dependent control over ferroptosis. PUFAs promote, while MUFAs mitigate lipid peroxidation. LDs buffer FAs yet rely on FSP1 for protection. Organelle contacts and FAO can either suppress or amplify ferroptosis, highlighting the necessity of metabolism-adapted therapeutic strategies.
2.3 Antioxidant defense system
Cellular ferroptosis susceptibility is governed by the balance between pro-oxidative metabolism and antioxidant defenses. Four major canonical anti-ferroptotic cascades together with diverse non-canonical mechanisms constitute the cellular anti-ferroptotic network.
The cytoplasmic SLC7A11-GSH-GPX4 axis represents the primary defensive pathway. System Xc- composed of SLC7A11 and SLC3A2, imports cystine (Cys2) for GSH synthesis. GPX4 utilizes GSH to detoxify lipid hydroperoxides (L-OOH) and terminate peroxidation chain reactions[58]. Besides, mitochondrial GPX4 (mGPX4) specifically safeguards mitochondrial compartments[59].
The second line constitutes the mitochondrial antioxidant axis, relying on inner-membrane-localized dihydroorotate dehydrogenase (DHODH), which reduces CoQ to CoQH2 for radical scavenging[60]. DHODH and mGPX4 form a core dual mitochondrial-protective module. Loss of one pathway renders cells dependent on the other, and concurrent inactivation strongly triggers ferroptosis[60,61].
The GPX4-independent FSP1 pathway uses reduced nicotinamide-adenine dinucleotide (NADH) to reduce CoQ and vitamin K (VitK) into CoQH2 and vitamin K hydroquinone (VitKH2)[62-64]. FSP1 is broadly distributed across the plasma membrane, LDs and lysosomes[48,62,65].
The fourth line is GTP cyclohydrolase 1 (GCH1)-driven tetrahydrobiopterin (BH4) biosynthesis, constituting another GPX4-independent defense. BH4 directly scavenges radicals and supports CoQ recycling to suppress ferroptosis[66].
Beyond canonical pathways, multiple non-canonical systems are involved in regulating ferroptosis. The peroxiredoxin (PRDX) family represents one critical defensive layer. PRDX6 not only promotes GPX4 biogenesis via transporting selenium (Se) but also recruits GPX4 to the membrane to directly prevent membrane PL peroxidation[67,68]. Mitochondrial PRDX3 can eliminate peroxides, but upon oxidation, hyper-oxidized PRDX3 translocates to the plasma membrane, inhibits Cys2 uptake and accelerates ferroptosis, rendering hyper-oxidized PRDX3 a valuable biomarker for ferroptosis[69]. Aldehyde dehydrogenase 1A1 (ALDH1A1) detoxifies cytotoxic aldehydes, including 4-hydroxy-2-nonenal (4-HNE) and malondialdehyde (MDA), derived from overloaded L-OOH as a secondary defensive layer[70]. Additionally, GPX1 counteracts ALOX12-PHLDA2-mediated non-canonical ferroptosis by reducing peroxidized PA[71]. Vitamin E quenches iron-catalyzed radicals and has been applied to alleviate lipid peroxidation in vivo[56,72].
Taken together, ferroptosis defense is multi-layered and compensatory. Canonical and non-canonical cascades cooperate to set cellular ferroptosis thresholds. Further dissection of pathway crosstalk will uncover therapeutic targets for ferroptosis-based interventions.
3. Regulation of Ferroptosis by Metabolic Substance Exchange between Intracellular and Extracellular Spaces
Cells do not exist in isolation as their fate is profoundly influenced by the extracellular microenvironment. The dynamic exchange of metabolic substances between the intracellular and extracellular spaces, including iron, lipids, amino acids (AAs), and glucose, constitutes a critical external mechanism that regulates cellular vulnerability to ferroptosis. Cells also continuously sense and respond to physicochemical conditions, thereby determining fate (Figure 2).
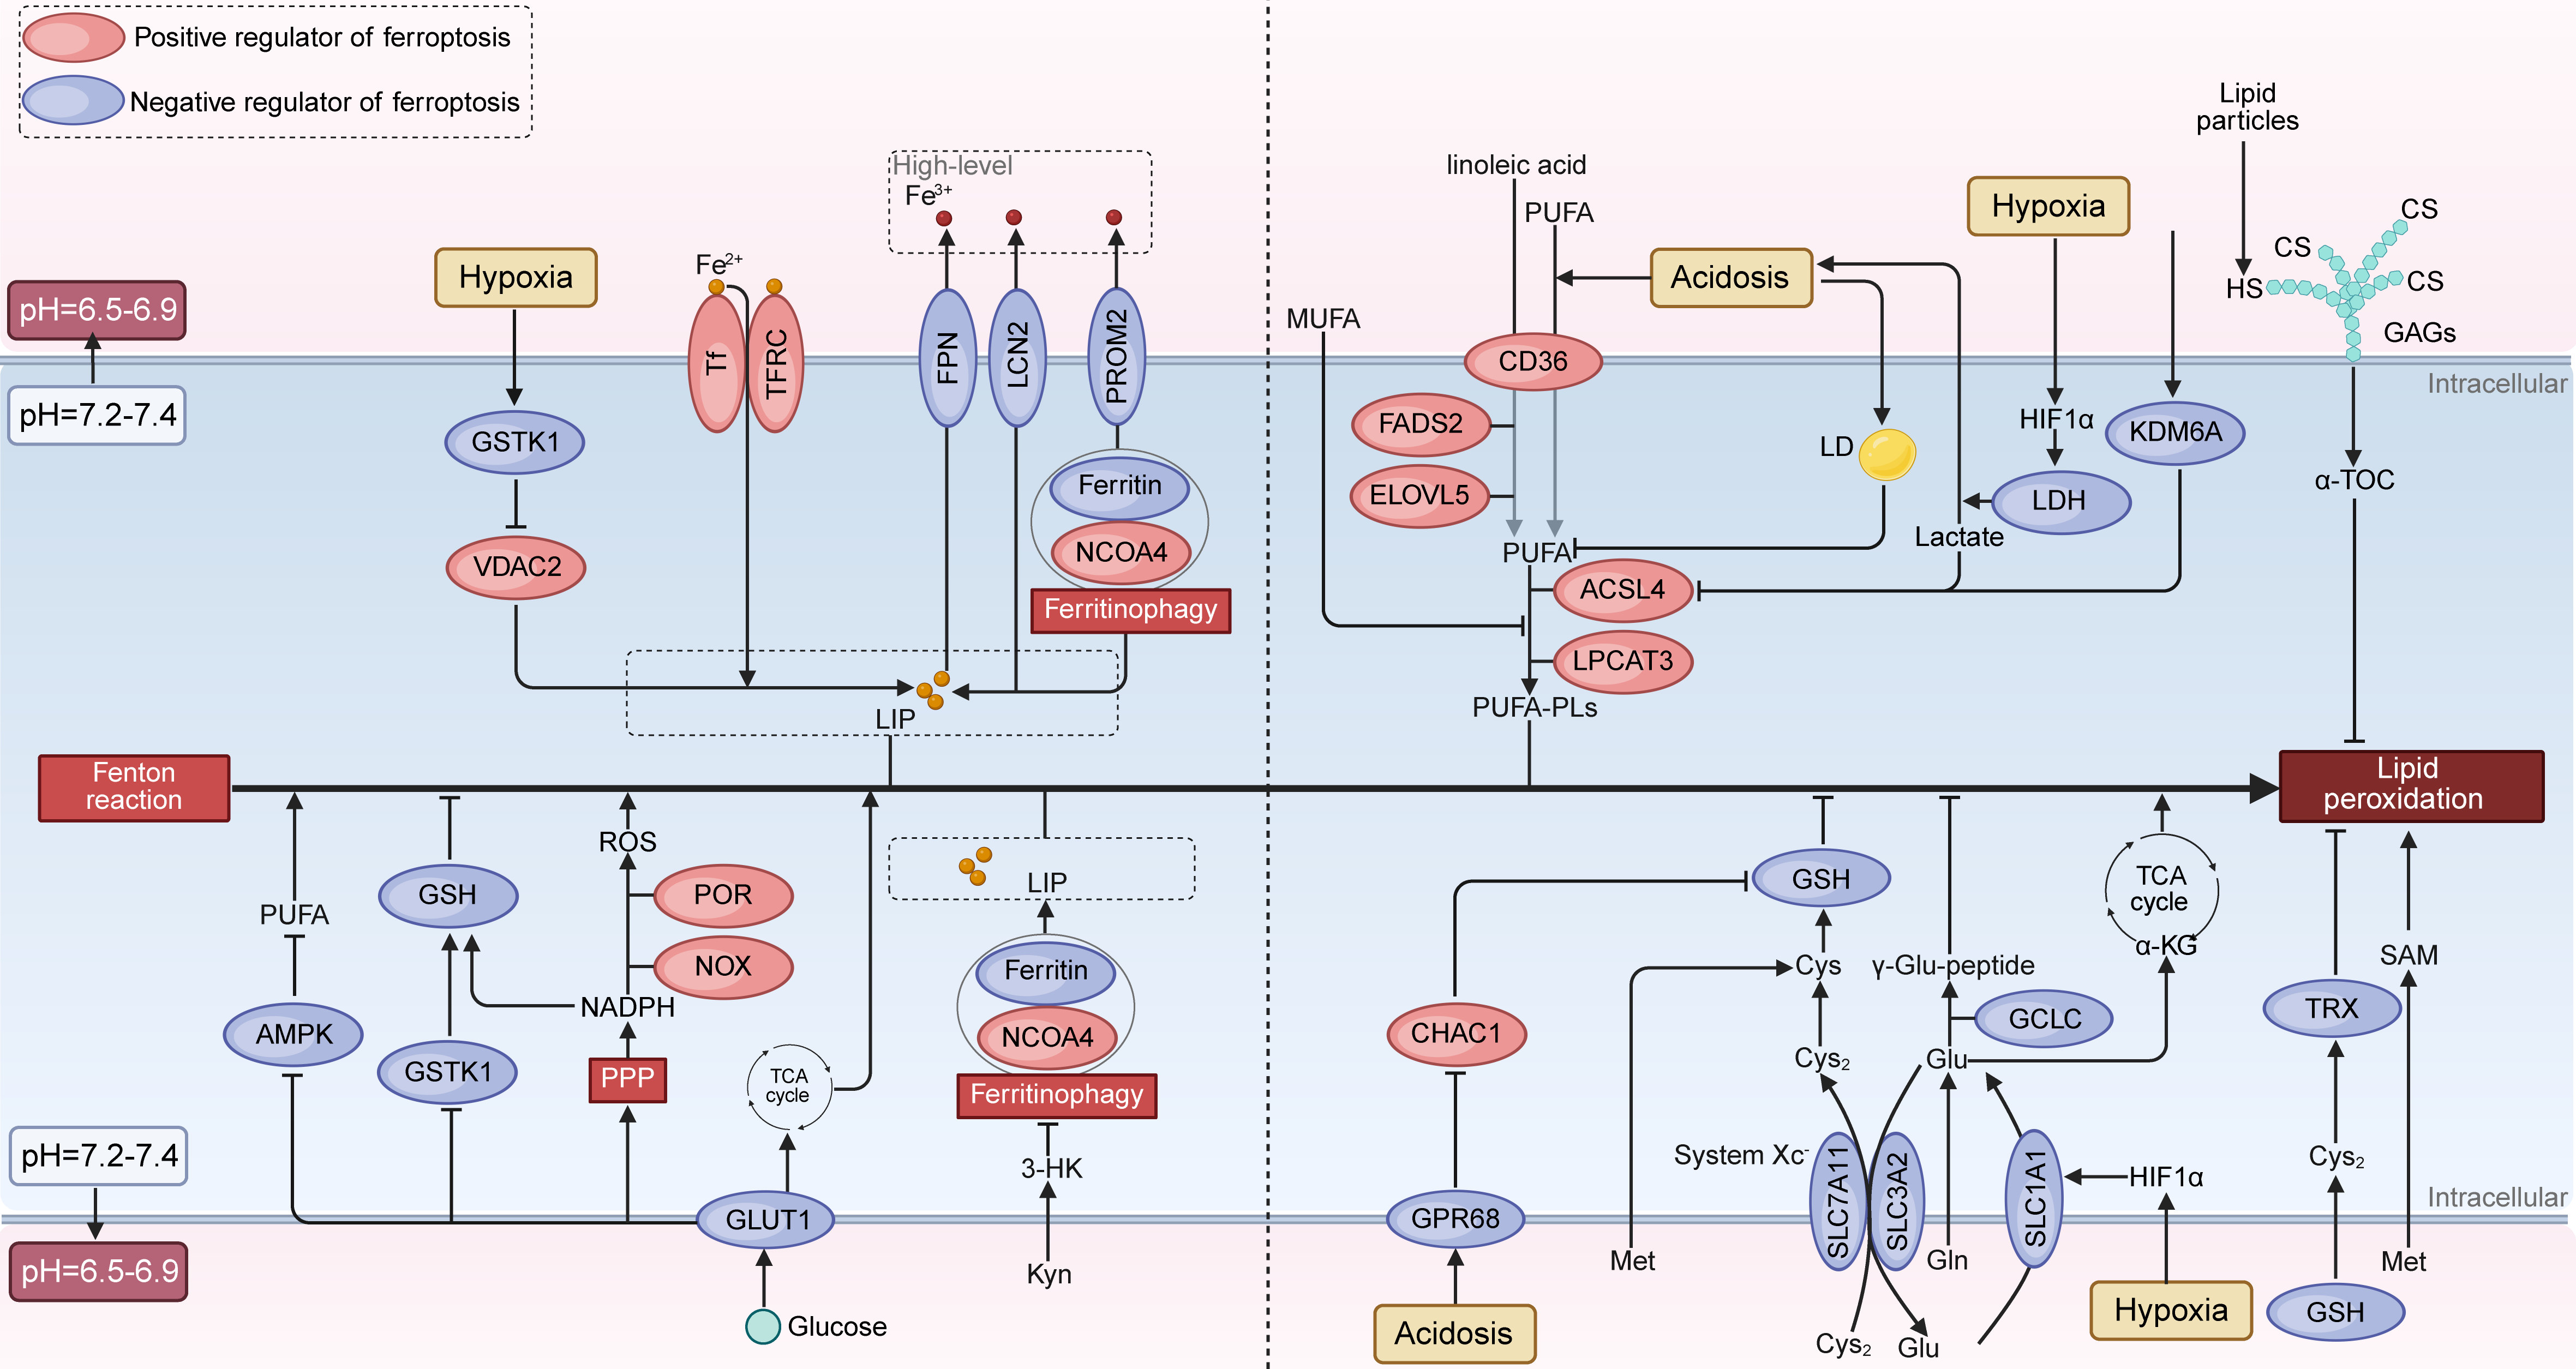
Figure 2. Regulation of ferroptosis by extracellular microenvironment cues. Extracellular microenvironmental cues, including acidosis, hypoxia, nutrient supply and bioactive metabolites, are sensed and transduced via plasma-membrane transporters and receptors to remodel intracellular iron homeostasis, lipid metabolism and antioxidant defenses. Created in BioRender. Guo, Y. (2026) https://BioRender.com/oqbp5q0. GSTK1: glutathione S-transferase κ1; Tf: transferrin; TFRC: transferrin receptor; FPN: ferroportin; PROM2: prominin-2; NCOA4: nuclear receptor coactivator 4; PUFA: polyunsaturated fatty acid; AMPK: adenosine 5’-monophosphate-activated protein kinase; GSH: glutathione; ROS: reactive oxygen species; POR: NADPH-cytochrome P450 reductase; NOX: NADPH oxidase; NADPH: nicotinamide adenine dinucleotide phosphate; PPP: pentose phosphate pathway; TCA: tricarboxylic acid; GLUT1: glucose transporter 1; 3-HK: 3-hydroxykynurenine; Kyn: kynurenine; MUFA: monounsaturated fatty acid; PUFA: polyunsaturated fatty acid; FADS2: acyl-CoA 6-desaturase; ELOVL5: elongation of very long chain fatty acid elongase 5; ACSL4: long-chain-fatty-acid-CoA ligase 4; LPCAT3: lysophosphatidylcholine acyltransferase 3; PLs: phospholipids; LD: lipid droplet; LDH: lactate dehydrogenase; HS: heparan sulfate; CS: chondroitin sulfate; GAGs: glycosaminoglycans; Cys: cysteine; CHAC1: glutathione-specific γ-glutamylcyclotransferase 1; Met: methionine; Gln: glutamine; Glu: glutamate; GCLC: glutamate-cysteine ligase catalytic subunit; α-KG: α-ketoglutarate; TRX: thioredoxin; SAM: S-adenosylmethionine.
3.1 Bidirectional transport of iron ions
The iron pool within cells primarily originates from dietary intake and the recycling of intracellular iron. Tumor cells enhance the uptake of extracellular iron by activating endocytosis[73]. At the same time, cells also possess mechanisms for exporting excess iron, mainly through FPN and PROM2, which facilitate the export of iron ions into the extracellular matrix[17,34]. Blocking iron uptake or promoting its efflux typically reduces intracellular free iron levels, thereby inhibiting ferroptosis.
However, the relationship between extracellular iron levels and cellular ferroptosis sensitivity is not simply a negative correlation. It exhibits a complex double-edged characteristic. On the one hand, FPN-mediated iron efflux reduces substrates for Fenton reactions, reflecting resistance to ferroptosis[17]. On the other hand, extracellular iron levels influence the intercellular transfer of ferroptosis signals[16]. Therefore, the assessment of ferroptosis risk cannot rely solely on extracellular iron levels but should consider the activation status of relevant signaling pathways.
3.2 Lipid exchange: A game between substrate supply and antioxidant defense
Cells take up free FAs via membrane transporters such as CD36 to regulate intracellular lipid components[14]. Linoleic acid, the precursor for PUFA biosynthesis, depends on exogenous intake[43]. Exogenous PUFAs can be directly incorporated into membrane PLs through the ACSL4-LPCAT3 pathway, becoming targets for peroxidation attack[2,7,14]. Meanwhile, SFAs can be converted into PUFAs via FADS2 and ELOVL5, posing indirect risks of ferroptosis[43-45]. Conversely, MUFAs such as exogenous oleic acid compete with PUFAs for incorporation into membrane PLs, exerting protective effects against ferroptosis[37,38].
It is worth noting that when extracellular lipids, including PUFAs, are deficient, cellular susceptibility to ferroptosis may actually increase[50]. This is because lipid restriction in the microenvironment limits the breakdown of intracellular TAGs, thereby releasing endogenous PUFAs and promoting the synthesis of PUFA-PLs, which subsequently activate ferroptosis[50]. This indicates that cells utilize internal reserves under nutrient-deficient conditions, resulting in self-inflicted damage.
Beyond the uptake of free FAs, tumor cells acquire lipoproteins and lipid particles through lipoprotein receptors and sulfated glycosaminoglycans (GAGs) to support tumor growth, among which GAGs function as major mediators for lipoprotein uptake. Low-density lipoprotein (LDL) and high-density lipoprotein (HDL) carry antioxidative α-tocopherol (α-TOC). Upon GPX4 dysfunction, lipid-rich clear-cell renal cell carcinoma takes up α-tocopherol-containing lipoproteins via GAGs to antagonize ferroptosis[72]. In glioblastoma, long-term acidosis promotes the switch of cell-surface GAGs from heparan sulfate (HS) to chondroitin sulfate (CS), forming a CS-enriched glycocalyx barrier that blocks HS-dependent lipoprotein import and thereby suppresses ferroptosis[47]. These two seemingly contradictory findings regarding GAG-mediated lipoprotein uptake in ferroptosis regulation are intrinsically reconcilable. Both studies demonstrate CS accumulation in tumor cells. CS enrichment facilitates α-TOC absorption to counteract oxidative stress, whereas the CS-abundant glycocalyx barrier may block the import of HS-dependent lipid particles loaded with peroxidation-prone lipids. Moreover, under acute stress triggered by intracellular GPX4 inhibition, the uptake of exogenous α-TOC helps preserve cellular antioxidant capacity[72]. Nevertheless, further investigations are required to clarify whether tumor cells still rely on exogenously derived α-TOC for antioxidant defense under chronically adapted microenvironments such as acidosis, as well as the regulatory roles of other specific lipid components internalized via HS- and CS-dependent pathways.
In summary, the species, abundance and uptake routes of extracellular lipids collectively determine ferroptosis susceptibility. Tumor cells dynamically tune lipid dependence by remodeling cell-surface structures to maintain redox homeostasis. These findings highlight the high context-dependence of cell-surface remodeling in governing lipid acquisition and provide important theoretical foundations for tumor therapeutic strategies targeting lipid-metabolism interventions.
3.3 Amino acid transport: The conductor of redox balance
The intracellular and extracellular exchange of AAs plays a central role in maintaining cellular redox balance. The classical system Xc- transport is responsible for importing extracellular Cys2 into the cell for GSH synthesis while simultaneously exporting intracellular glutamate (Glu)[1,2,74]. When extracellular Cys2 concentration is insufficient or Glu levels are elevated, system Xc- activity is inhibited, thereby impairing GSH synthesis and leaving the cell vulnerable to lipid peroxidation[74].
The fate of Glu differs significantly between intracellular and extracellular environments. Although intracellular Glu participates in GSH synthesis, extracellular depletion of Cys2 results in the accumulation of intracellular Glu, which tends to be converted to α-ketoglutarate (α-KG) and enters the tricarboxylic acid (TCA) cycle, thereby supplying energy to the cell and promoting FA synthesis, increasing membrane PUFA content, and triggering ferroptosis[4,75]. In lung cancer, to avoid such Glu accumulation-induced ferroptosis, glutamate-cysteine ligase catalytic subunit (GCLC), which is responsible for GSH synthesis, catalyzes the formation of γ-glutamyl peptides to consume excess Glu, thus preventing cellular damage[76].
As a key nutrient, the extracellular level of glutamine (Gln) also profoundly influences ferroptosis. After entering the cell, Gln can be further broken down into Glu to participate in ferroptosis[75]. Some malignant tumors, such as pancreatic cancer with Gln addiction, are highly sensitive to ferroptosis, and depletion of extracellular Gln directly induces cell death[77,78]. Recent studies have also revealed that the extracellular environment is remarkably rich in GSH. Tumor cells can take up and break down GSH from the microenvironment to obtain cysteine (Cys), though this Cys is not used to resynthesize GSH but instead participates in other antioxidant systems such as thioredoxin (TRX) to protect tumor cells from oxidative stress[79]. This suggests that the survival of cancer cells is determined not by endogenously synthesized GSH, but by microenvironment-derived GSH, and targeting extracellular GSH could represent a novel strategy for regulating ferroptosis.
In addition, methionine plays a dual role in ferroptosis. Cells can also take up methionine (Met) from the extracellular environment as a substrate for Cys synthesis, thereby inhibiting ferroptosis[80,81]. However, Met also contributes to S-adenosylmethionine (SAM)-derived lipid peroxidation under Cys starvation[82]. Thus, the different effects of dietary restriction of Met on ferroptosis depend on the duration of the restriction, which leads to a bias in the pathways involved.
As for other AAs, tumor cells can then take up kynurenine (Kyn) secreted from peritumoral adipose tissues, which is subsequently converted to 3-hydroxykynurenine (3-HK), a metabolite that directly binds NCOA4 and blocks its interaction with ferritin, thus inhibiting ferritinophagy and strengthening tumor cell resistance to ferroptosis[83].
Collectively, bidirectional amino-acid exchange between tumor cells and the extracellular microenvironment is a pivotal upstream regulator of ferroptosis. The system Xc--GSH axis governs ferroptosis susceptibility through Cys2 import and Glu export-driven metabolic reprogramming, while tumor cells can further scavenge microenvironmental GSH as an alternative Cys source. Gln and Met act in a context-dependent manner, and the Kyn pathway confers resistance by suppressing ferritinophagy. Thus, targeting extracellular amino-acid availability complements intracellular enzyme inhibition to sensitize tumors to ferroptosis-based therapies.
3.4 Glucose metabolism: The balance between energy supply and oxidative stress
After being imported into cells via glucose transporter 1 (GLUT1), glucose not only enters the TCA cycle to generate ROS in this process, but also produces reduced nicotinamide adenine dinucleotide phosphate (NADPH) through the pentose phosphate pathway (PPP)[84,85]. NADPH exhibits a dual role in bidirectionally regulating ferroptosis. On the one hand, it serves as a core reducing agent, providing a critical cofactor for GSH synthesis and supporting GPX4 function, thereby sustaining the cellular antioxidant defense[84]. Extracellular glucose deprivation or impaired glucose uptake reduces NADPH production, which in turn inactivates GPX4, accumulates lipid peroxides and ultimately triggers ferroptosis[84]. On the other hand, NADPH acts as a substrate for pro-oxidant enzymes including NADPH oxidase (NOX) and NADPH-cytochrome P450 reductase (POR) to drive ROS generation[86,87]. Accordingly, the net effect of NADPH on ferroptosis relies on its partitioning across distinct metabolic pathways.
Nevertheless, tumor cells engage multiple adaptive survival pathways to counteract ferroptosis within the glucose-deficient TME. Glucose exhaustion promotes mitochondrial translocation of glutathione S-transferase κ1 (GSTK1), thereby facilitating GSH-mediated ROS scavenging and mitigating oxidative stress[88]. In addition, adenosine 5’-monophosphate-activated protein kinase (AMPK) can be activated to suppress PUFA synthesis and render tumor cells resistant to ferroptosis[89].
These findings demonstrate that extracellular glucose availability not only governs cellular energy status but also fine-tunes ferroptosis thresholds by modulating NADPH partitioning between antioxidant defense and pro-oxidant processes. Under nutrient-starvation TME conditions, cells further maintain redox homeostasis by triggering adaptive programs, underscoring the critical role of metabolic plasticity in determining ferroptosis susceptibility.
3.5 Regulation and context-dependence of ferroptosis by acidic and hypoxic tumor microenvironments
The chaotic architecture of tumor neovasculature, coupled with insufficient blood perfusion and continuous competition for oxygen between tumor cells and immune cells, collectively creates a hypoxic microenvironment. Under hypoxia, tumors rely on the Warburg effect for compensatory energy production, with large amounts of lactate and protons continuously transported extracellularly, ultimately establishing a neutral intracellular pH of 7.2-7.4 and an acidic extracellular pH of 6.5-6.9[90]. Hypoxia and acidification are not merely metabolic byproducts but can also act as signals to activate downstream pathways and drive tumor progression.
Under acidosis, tumor cells can initiate multiple protective mechanisms. The first line of defense is constructed by the synergistic actions of cell surface glycocalyx remodeling and LD synthesis. Acidic stimulation drives the subtype conversion of proteoglycans on the surface of glioblastoma cells, thereby blocking the uptake of HS-dependent lipid particles. Concurrently, acidosis-induced upregulation of the DGAT1-dependent LD generation sequesters free PUFAs and reduces the intracellular pool of peroxidizable lipid substrates[46,47]. The second line relies on the acid-sensing GPR68 signaling axis. Activation of GPR68 by acidosis upregulates the transcription factor ATF4, which in turn downregulates glutathione-specific γ-glutamylcyclotransferase 1 (CHAC1), the key enzyme responsible for GSH degradation, thereby stabilizing the cellular core antioxidant system[91].
In parallel with these protective pathways, the acidic microenvironment simultaneously engages pro-ferroptotic regulatory programs. The CS-rich glycocalyx blocks HS-dependent lipid particles but does not impede the import of exogenous PUFAs. Acidosis upregulates CD36 expression and enhances its transporter activity, specifically promoting cellular uptake of n-3 and n-6 PUFAs[14]. Although the imported PUFAs can be temporarily sequestered in LDs for detoxification, once LD storage capacity is saturated or the intracellular antioxidant system dysfunctions, large amounts of free PUFAs are released to trigger ferroptosis. Cells adapted to chronic acidity exhibit significantly enhanced capacity for PUFA uptake. When exogenous PUFAs are abundant and exceed the LD buffering threshold, ferroptosis is strongly induced[14,50]. This suggests that the synthesis and storage capacity of LDs serve as a critical barrier against lipid peroxidation under tumor acidosis.
Furthermore, acute acidic stimulation elevates SLC3A2 ubiquitination levels in breast cancer cells cultured under neutral conditions, disrupting System Xc- function and enhancing ferroptosis sensitivity[92]. However, solid tumors are chronically exposed to acidosis and have undergone adaptive remodeling. Whether this short-term acidification effect remains stable in long-term acidic solid tumors requires further validation.
The seemingly contradictory ferroptosis phenotypes of the acidic microenvironment across different studies arise from the dynamic balance established by the simultaneous operation of multiple pathways. The ultimate sensitivity of cells to ferroptosis is constrained by three classes of microenvironmental conditions. The first is the form and concentration of extracellular lipids. When lipoproteins are abundant, the protective barrier effect of the CS-abundant glycocalyx dominates. When free FAs are abundant, the CD36-mediated pro-peroxidation pathway prevails. The second is the intracellular LD buffering capacity. Once LDs are saturated or their generation is impaired, the risk of lipid peroxidation rises sharply. The third is the duration of acid exposure. Short-term acidosis may stimulate ferroptosis in tumor cells, whereas persistent acid-adapted tumors stably activate various protective pathways, exhibiting an overall ferroptosis-resistant phenotype.
Hypoxia is another hallmark physicochemical microenvironment of tumors. Hypoxia-inducible factor 1α (HIF1α) is a transcription factor that responds to hypoxic stress. The hypoxic microenvironment can modulate intracellular ferroptosis levels by activating HIF1α, which in turn regulates the expression of ferroptosis-related genes. For example, HIF1α promotes lactate dehydrogenase (LDH) to produce lactate. Lactate accumulation not only causes extracellular acidosis and indirectly affects ferroptosis but can also inhibit ACSL4 through intracellular lactylation modification to antagonize ferroptosis[90,93,94]. Additionally, HIF1α can upregulate the Glu transporter SLC1A1, reclaiming extracellular Glu and enhancing the efficiency of system Xc- in taking up Cys2[94]. Beyond activating HIF1α, hypoxia can also inhibit the oxygen-dependent demethylase KDM6A, thereby downregulating ACSL4 levels to prevent PUFA-PL synthesis[95]. Hypoxia can further reinforce ferroptosis resistance in tumor cells by suppressing the generation of pro-ferroptotic molecules. The hypoxic microenvironment in hepatocellular carcinoma triggers serine/arginine-rich splicing factor 6 (SRSF6) alternative splicing, reducing tRF-E production and weakening its pro-ferroptotic function of stabilizing VDAC2 to promote mitochondrial iron accumulation and lipid peroxidation[96].
Both acidic and hypoxic microenvironments not only inhibit ferroptosis in tumor cells but also induce the formation of an immunosuppressive microenvironment. Based on this mechanism, intervention strategies that simultaneously ameliorate tissue acidification and alleviate hypoxia can effectively enhance the anti-tumor efficacy of ferroptosis inducers combined with immunotherapy. Furthermore, as hallmark features of the tumor microenvironment, hypoxia and acidification can also serve as natural responsive anchors for targeted drug delivery.
Collectively, extracellular cues do not execute ferroptosis independently. Rather, every extracellular signal is ultimately translated into an intracellular metabolic and redox state that raises or lowers the ferroptosis threshold (Table 1). Meanwhile, cells continuously remodel their extracellular milieu through nutrient consumption and metabolite export, rendering this regulation a dynamic, bidirectional exchange that underlies the context-dependent ferroptosis responses discussed throughout this section.
Table 1. Summary of extracellular factors regulating ferroptosis.
| Extracellular factor | Transporter/receptor | Downstream intracellular pathway | Effect on ferroptosis | Cancer context | Therapeutic implication | Ref. |
| Extracellular iron (dietary and recycled) | Uptake via Tf-TFRC complex and endocytosis; efflux via FPN and PROM2 | Elevate labile iron pool to fuel Fenton chemistry. | Bidirectional: uptake promotes ferroptosis while efflux reduces Fenton substrates and confers resistance | Breast cancer | Blocking iron uptake or promoting efflux inhibits ferroptosis; risk evaluation should consider the activation status of relevant signaling pathways | [17,34,73] |
| PUFA precursors such as linoleic acid | Membrane fatty-acid transporters (not specified) | PUFA synthesis mediated via FADS2 and ELOVL5. | Promote | Lung cancer | Dietary or pharmacological modulation of PUFA precursor supply | [43] |
| Exogenous PUFAs especially n-3 and n-6 PUFA | CD36 and other membrane fatty-acid transporters | ACSL4-LPCAT3-mediated incorporation into membrane PLs. | Promote | Cervical cancer, colorectal cancer and hypopharyngeal cancer | Dietary or pharmacological modulation of PUFA supply; lipid-metabolism intervention | [2,7,14] |
| Exogenous MUFAs | Membrane fatty-acid transporters (not specified) | Compete with PUFAs for incorporation into membrane PLs | Inhibit | Hepatocellular carcinoma and neuroblastoma | MUFA supplementation to displace membrane PUFAs and reduce peroxidation substrates | [37,38] |
| Lipid restriction | Transporter not specified | Promote TAG breakdown to release PUFA and enhance PUFA-PL synthesis. | Promote | Lung cancer, cervical cancer and pancreatic cancer | Lipid-restriction combined with TAG breakdown strategies | [50] |
| Lipoproteins carrying α-TOC | GAG | Delivery of α-TOC antagonizes lipid peroxidation. | Inhibit | Clear-cell renal cell carcinoma | Disrupting GAG-mediated α-TOC scavenging to re-sensitize resistant tumors via blocking GAG biosynthesis | [72] |
| Cystine | System Xc- | GSH synthesis and GPX4-mediated detoxification of lipid peroxides. | Inhibit | Pancreatic cancer | Restricting extracellular cystine availability complements intracellular enzyme inhibition | [1,2,74] |
| Glutamate | System Xc- | Elevated extracellular glutamate inhibits system Xc-. Accumulated intracellular glutamate is converted to α-KG and entering the TCA cycle to promote ROS generation or consumed by GCLC. | Promote | Lung cancer and head and neck squamous cell | Targeting intracellular glutamate-metabolic adaptations or supplement extracellular glutamate to prevent resistance | [1,2,4,74-76] |
| Glutamine | Transporter not specified | Glutaminolysis to glutamate, feeding ferroptosis-related metabolism. | Context-dependent (Glutamine depletion induces ferroptosis in glutamine-addicted tumors) | Pancreatic cancer and head and neck squamous cell | Glutamine-depletion therapy for glutamine-addicted tumors | [75,77,78] |
| GSH | Transporter not specified | Catabolized to cysteine that supports the TRX antioxidant system rather than GSH resynthesis. | Inhibit | Breast cancer | Targeting extracellular GSH as a novel strategy to regulate ferroptosis | [79] |
| Methionine | Transporter not specified | Substrate for cysteine synthesis. Also contributes to SAM-derived lipid peroxidation under cysteine starvation. | Context-dependent | Hepatocellular carcinoma, fibrosarcoma and melanoma | Duration-controlled dietary methionine restriction to bias outcomes toward ferroptosis induction | [80-82] |
| Kynurenine secreted from PAT | Transporter not specified | Converted to 3-HK, which binds NCOA4 and blocks its interaction with ferritin, inhibiting ferritinophagy. | Inhibit | PAT-associated tumors | Blocking the Kyn-3-HK-NCOA4 axis to restore ferritinophagy | [83] |
| Glucose | GLUT1 | PPP-derived NADPH supports GSH synthesis as well as NOX/POR and TCA cycle-driven ROS generation. Glucose exhaustion activates GSTK1 and AMPK-mediated suppression of PUFA synthesis. | Context-dependent | Colon cancer, ovarian cancer, breast cancer, pancreatic cancer, lung cancer and cervical carcinoma | Modulating glucose availability or uptake, combined with intervention targeting downstream intracellular metabolism pathways to enhance sensitivity | [84-89] |
| Acidosis | GPR68, GAG, CD36 and DGAT1 | Protective: glycocalyx HS-to-CS switch blocks HS-dependent lipid particles; DGAT1-dependent LDs sequester PUFAs; GPR68-ATF4 downregulates CHAC1 to stabilize GSH. Pro-ferroptotic: CD36-mediated uptake of n-3/n-6 PUFAs; ferroptosis once LD buffering is saturated. | Context-dependent | Glioblastoma, osteosarcoma, cervical cancer, colorectal cancer and hypopharyngeal cancer | PUFA supplementation combined with DGAT inhibitor to restore ferroptosis sensitivity | [14,46,47,91] |
| Hypoxia | HIF1α, SLC1A1 and KDM6A | HIF1α drives LDH-mediated lactate production, leading to ACSL4 inhibition and extracellular acidosis. HIF1α upregulates SLC1A1 to reclaim glutamate and enhance system Xc- cystine uptake. Hypoxia inhibits KDM6A to downregulate ACSL4. Hypoxia also weakens VDAC2-mediated mitochondrial iron accumulation and lipid peroxidation. | Inhibit | Hepatocellular carcinoma, bladder tumor and fibrosarcoma | Alleviating hypoxia and acidification simultaneously to boost ferroptosis inducers plus immunotherapy; hypoxia/low pH as natural anchors for responsive drug delivery | [90,93-96] |
Tf: Transferrin; TFRC: transferrin receptor; FPN: ferroportin; PROM2: prominin-2; PUFA: polyunsaturated fatty acid; FADS2: acyl-CoA 6-desaturase; ELOVL5: elongation of very long chain fatty acid elongase 5; ACSL4: long-chain-fatty-acid-CoA ligase 4; LPCAT3: lysophosphatidylcholine acyltransferase 3; PLs: phospholipids; MUFAs: monounsaturated fatty acids; TAG: triacylglycerides; GAG: glycosaminoglycans; GSH: glutathione; GPX4: glutathione peroxidase 4; α-KG: α-ketoglutarate; TCA: tricarboxylic acid; ROS: reactive oxygen species; GCLC: glutamate-cysteine ligase catalytic subunit; TRX: thioredoxin; SAM: S-adenosylmethionine; PAT: peritumoral adipose tissue; 3-HK: 3-hydroxykynurenine; NCOA4: nuclear receptor coactivator 4; Kyn: kynurenine; GLUT1: glucose transporter 1; PPP: pentose phosphate pathway; NADPH: nicotinamide adenine dinucleotide phosphate; NOX: NADPH oxidase; POR: NADPH-cytochrome P450 reductase; GSTK1: glutathione S-transferase κ1; AMPK: adenosine 5’-monophosphate-activated protein kinase; DGAT1: diacylglycerol O-acyltransferase 1; HS: heparan sulfate; CS: chondroitin sulfate; LDs: lipid droplets; CHAC1: glutathione-specific γ-glutamylcyclotransferase 1; LDH: lactate dehydrogenase.
4. Cell-to-Cell Communication: Signaling of Ferroptosis and Remodeling of the Immune Microenvironment
Ferroptosis is not an isolated cellular event. Cells undergoing ferroptosis can activate ferroptosis in other cells by releasing specific substances, and they can also serve as signals to reshape the extracellular microenvironment, thereby influencing tumor progression and the efficacy of cancer treatments.
4.1 Transmission of ferroptosis signals
Ferroptosis is not a cell-autonomous event. The sensitivity of tumor cells to ferroptosis is precisely regulated by other cells within the TME. Upon receiving signals released by neighboring cells including direct cell-to-cell contact, EV-mediated transport, metabolite exchange, and cytokine regulation, tumor cells undergo significant changes in their susceptibility to ferroptosis.
A recent study confirmed that cells can directly transmit ferroptotic signals through cell membrane contact. Lipid peroxidation and ferroptosis-related signals propagate to adjacent cells via contiguous plasma membranes, and the efficiency of this propagation is significantly influenced by intercellular distance, α-catenin-mediated adherent junctions, and extracellular iron ion concentration[16].
Tumor cells undergoing ferroptosis can also disseminate ferroptotic signals by secreting EVs. EVs are membrane-bound vesicles with a lipid bilayer structure that are secreted by cells and are capable of carrying nucleic acids, proteins, lipids, and various metabolites[97]. Although polyamines can chelate intracellular ferrous iron and reduce the LIP, excessive polyamines produce H2O2 through decomposition. Tumor cells undergoing ferroptosis upregulate polyamine synthesis, and the excess polyamines are packaged into EVs and released extracellularly. Upon uptake by neighboring tumor cells, the H2O2 generated from polyamine decomposition within the vesicles triggers the Fenton reaction with intracellular Fe2+, thereby inducing ferroptosis and enabling its intercellular propagation[98].
Meanwhile, stromal cells and immune cells within the TME can also modify the ferroptosis sensitivity of tumor cells by secreting EVs. EVs derived from macrophages/tumor-associated macrophages (TAMs) play a complex role in ferroptosis regulation. At the gene regulation level, TAMs can directly transfer mRNA of ceruloplasmin (CP) to fibrosarcoma cells, promoting iron efflux and thereby inhibiting ferroptosis in tumor cells[99]. TAM-derived exosomes enriched in annexin A3 (ANXA3) can inhibit CHAC1 expression, suppressing GSH depletion[100]. Additionally, macrophage-derived vesicles can carry the antioxidant protein PRDX6, effectively reducing lipid peroxidation levels in tumor cells and blocking ferroptosis[101]. Non-coding RNAs carried by EVs derived from cancer-associated fibroblasts (CAFs) can regulate ferroptosis sensitivity as well. CAFs secrete EVs containing miR-432-5p, which also downregulates CHAC1 expression in prostate tumor cells, and lncRNA ROR1-AS1, which regulates SLC7A11 levels in lung cancer cells[102,103]. CAFs also secrete miR-3173-5p, which inhibits ACSL4 expression in pancreatic cancer cells[104]. EVs from other cell types also contribute to ferroptosis regulation. Endothelial cell-derived exosomes carrying SLC1A5 upregulate GPX4 expression in gastric cancer cells, inducing ferroptosis resistance, while tumor-associated neutrophils deliver miR-9-3p via exosomes to downregulate ACSL4, rendering gastric cancer cells resistant to ferroptosis-based therapy[105,106]. Adipocyte-derived exosomes carrying microsomal triglyceride transfer protein (MTTP) enter colon cancer cells and upregulate the system Xc--GPX4 axis[107]. Long non-coding RNA STX17-DT reduces mitochondrial ROS production in neighboring tumor cells by modulating the mRNA stability of interferon α-inducible protein 6 (IFI6)[108].
Beyond EV-mediated indirect regulation, stromal cells and immune cells within the TME can also directly release soluble metabolites to alter tumor cell ferroptosis sensitivity. CAFs secrete cysteine, which is taken up by pancreatic cancer cells for GSH synthesis, mediating ferroptosis resistance[109]. In addition, TAMs release various metabolites such as itaconate (ITA), L-carnitine, and taurine, all of which can induce ferroptosis resistance in tumor cells[110-112]. Upon uptake, ITA activates the nuclear factor erythroid 2-related factor 2 (NRF2)-SLC7A11 pathway in tumor cells, enhancing antioxidant defense[110]. TAM-derived L-carnitine inhibits erastin-induced ferroptosis by decreasing ACSL4 expression[111]. Taurine secreted by M2 macrophages promotes MUFA synthesis, thereby mediating ferroptosis resistance in tumor cells[112].
Cytokines secreted by immune cells also serve as important mediators in the microenvironmental regulation of tumor cell ferroptosis. CD8+ T cells primarily rely on interferon-γ (IFNγ) to regulate the ferroptosis sensitivity of tumor cells. IFNγ functions as a well-characterized ferroptosis inducer, suppressing SLC7A11 expression to limit Cys2 uptake and upregulating ACSL4 expression to promote PUFA-PL synthesis, thereby inducing ferroptosis[113,114]. However, IFNγ can also activate phosphoserine aminotransferase 1 (PSAT1) to maintain the stability of GPX4 resulting in ferroptosis evasion[115]. Cytokines secreted by macrophages also play complex regulatory roles. For example, the expression level of interleukin-34 (IL-34) is positively correlated with ferroptosis resistance in pancreatic cancer cells[116]. Transforming growth factor β (TGFβ) from TAM or other immune cells sensitizes tumor cells to ferroptosis by increasing the ratio of PUFA:MUFA[43].
Of note, ferroptosis in tumor cells is not a cell-autonomous event. The transmission of ferroptosis signals depends not only on direct cell-to-cell contact and EV transport but also on the precise regulation by cytokines and metabolites secreted by stromal and immune cells within the TME. Notably, the majority of regulatory effects exerted by stromal and immune cells in the TME on tumor cell ferroptosis are inhibitory as they enhance the antioxidant defense capacity of tumor cells and promote a ferroptosis-resistant phenotype by releasing antioxidant proteins, metabolites, or modulating ferroptosis-related gene expression. This suggests that targeting these endogenous protective mechanisms within the TME may represent an important strategy for sensitizing tumors to ferroptosis-based therapy. Together, these signals constitute a complex intercellular communication network that collectively determines the sensitivity of tumor cells to ferroptosis and maintains the homeostasis of the TME (Figure 3).
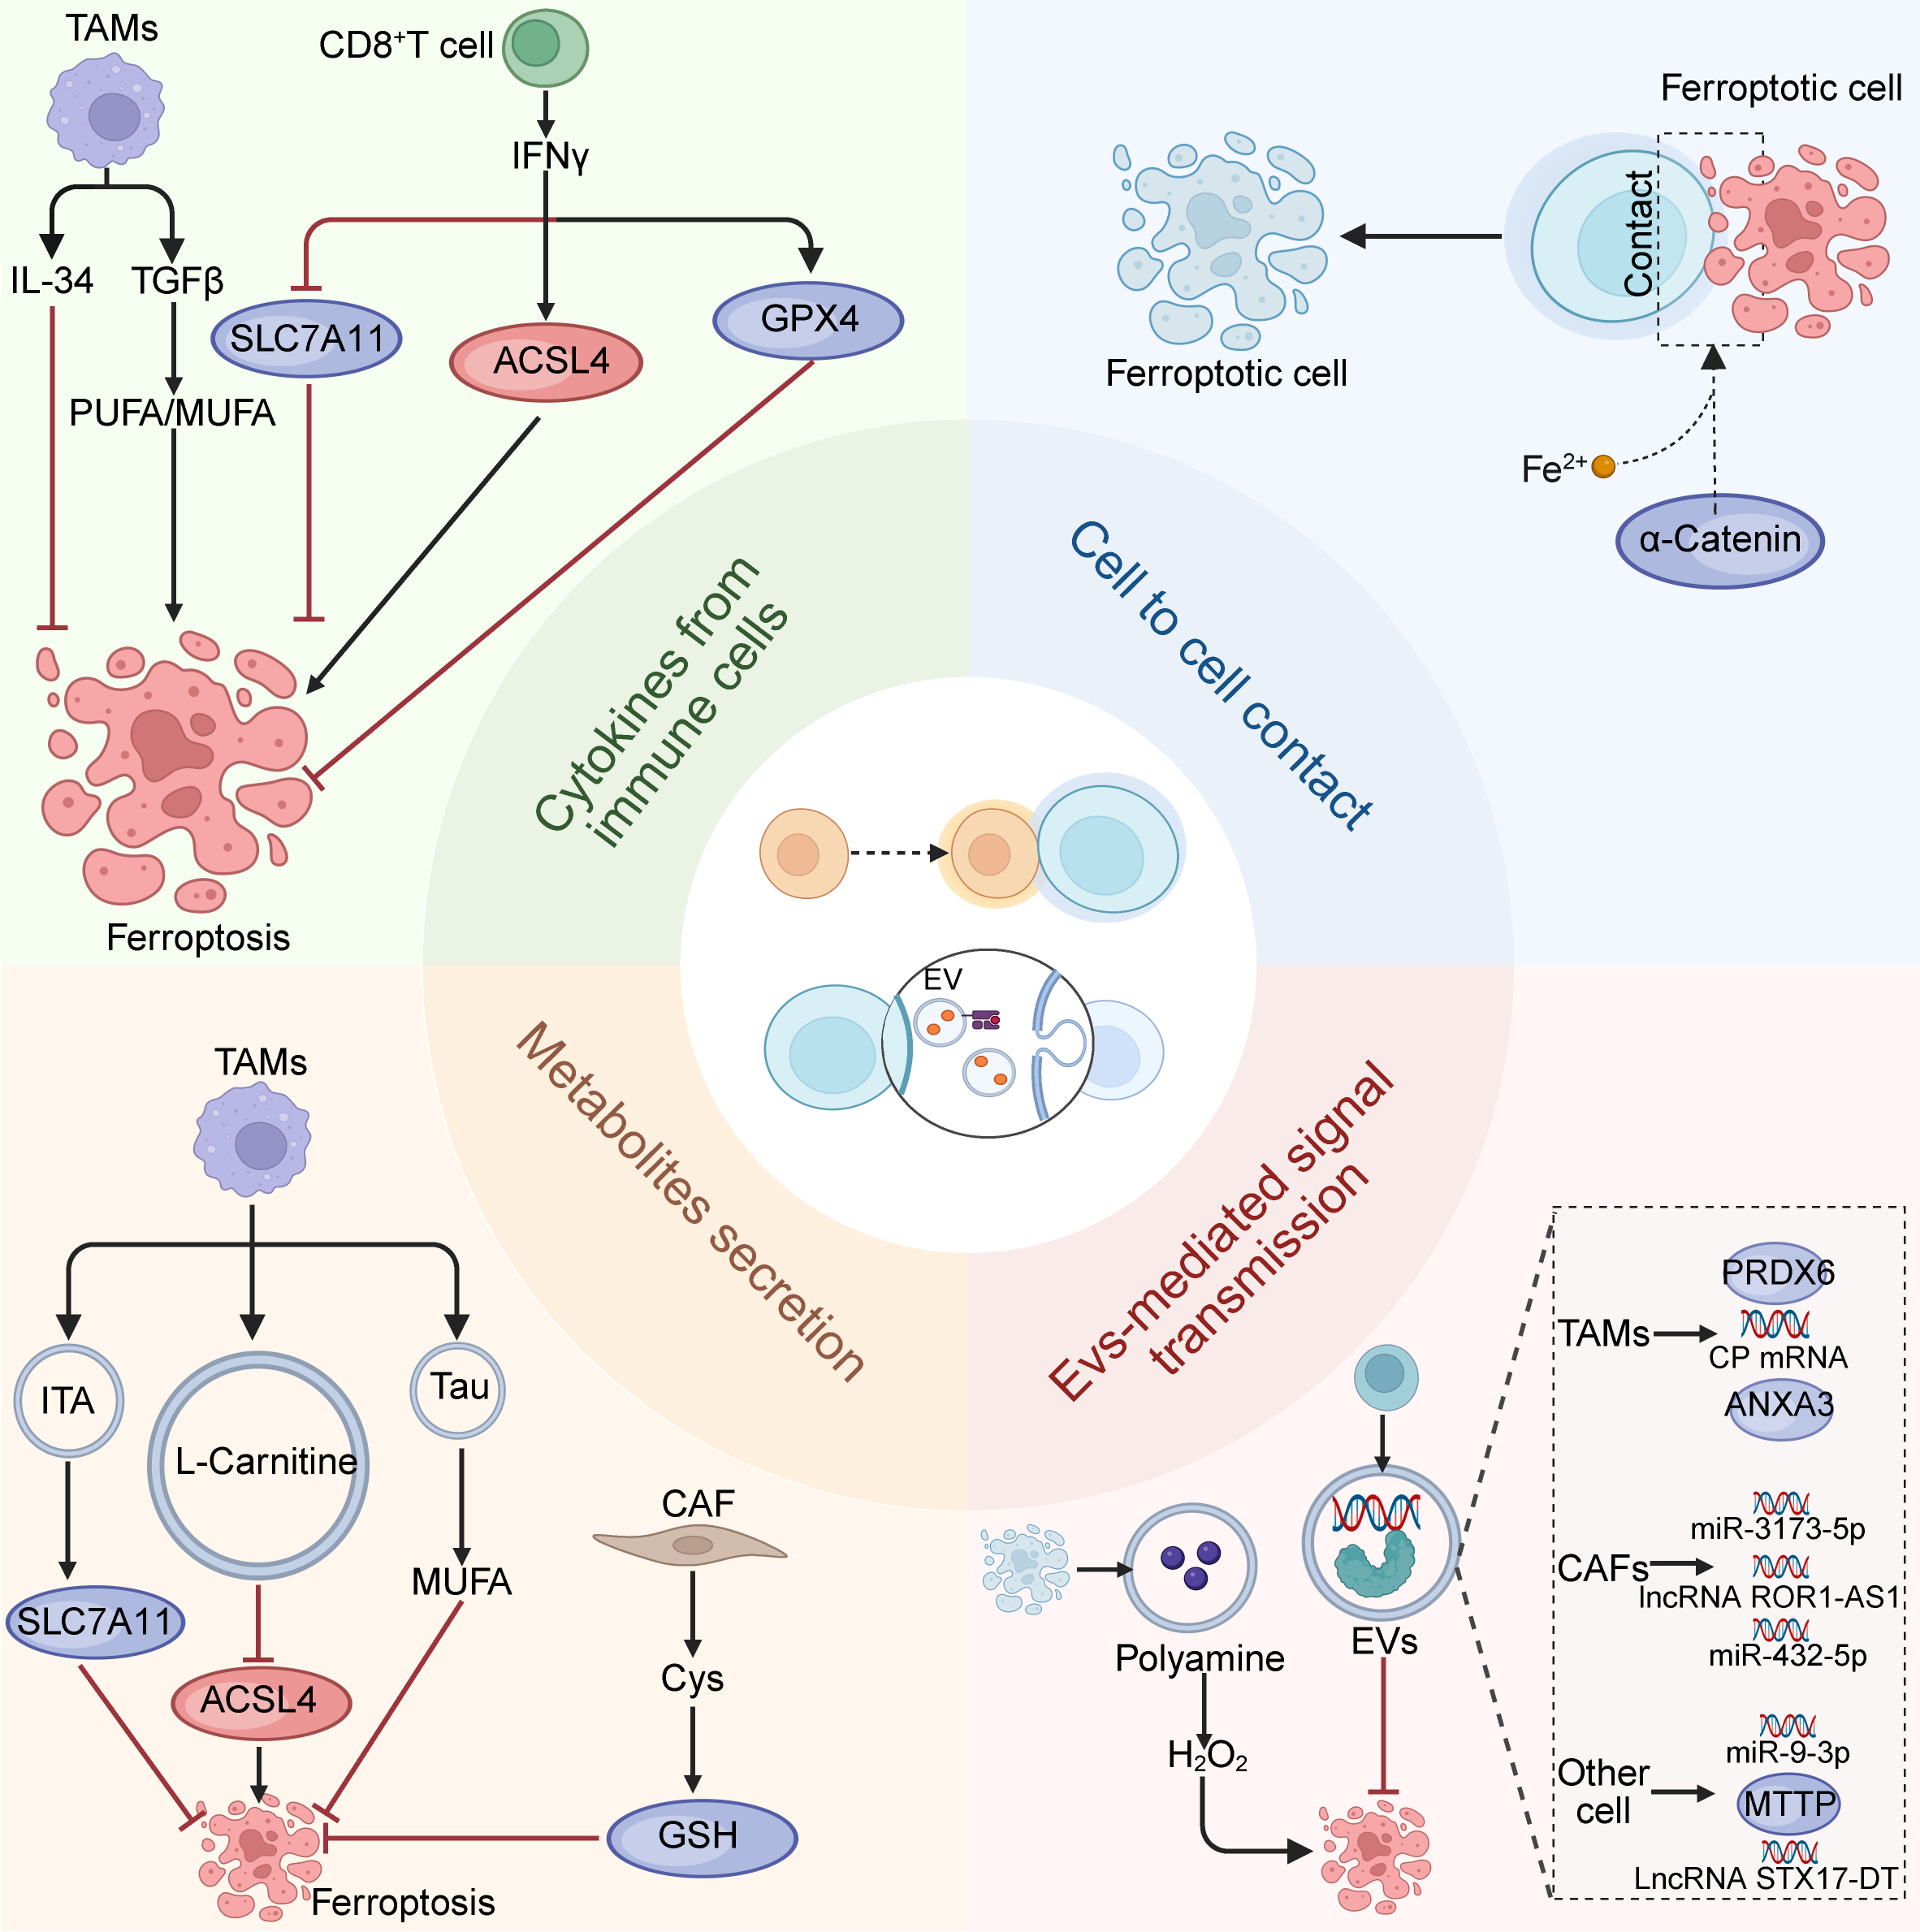
Figure 3. Intercellular communication-driven transmission and regulation of ferroptosis within the tumor microenvironment. Regulatory signals for ferroptosis can be transmitted between cells within the tumor microenvironment via four major pathways. Ferroptotic signals can spread through direct cell-to-cell contact. EVs carrying bioactive cargoes such as RNAs and proteins act on recipient tumor cells to modulate ferroptosis progression. In addition, target-cell ferroptosis susceptibility can be altered by uptake of metabolites secreted by neighboring cells and cytokines released from immune cells. Created in BioRender. Guo, Y. (2026) https://BioRender.com/t8kz28k. TAMs: tumor-associated macrophages; IL-34: interleukin-34; TGFβ: transforming growth factor β; PUFA: polyunsaturated fatty acid; MUFA: monounsaturated fatty acid; IFNγ: interferon-γ; ACSL4: long-chain-fatty-acid-CoA ligase 4; GPX4: glutathione peroxidase 4; ITA: itaconate; Cys: cysteine; GSH: glutathione; EVs: extracellular vesicles; CP: ceruloplasmin; ANXA3: annexin A3; CAFs: cancer-associated fibroblasts; MTTP: microsomal triglyceride transfer protein.
4.2 The interaction between ferroptosis and the immune microenvironment
Immune cells can regulate ferroptosis in tumor cells by secreting vesicles, metabolites, and cytokines. Conversely, ferroptosis can also reshape the immune microenvironment. Immunogenic cell death (ICD) is a stress-driven, specialized form of regulated cell death that can induce adaptive immune responses against antigens from dying cells[117,118]. Cells undergoing ICD release damage-associated molecular patterns (DAMPs), which are recognized by dendritic cells (DCs) to promote their maturation and antigen presentation, thereby activating specific anti-tumor immunity[117,119]. DC vaccines prepared from lysates of ferroptotic tumor cells can enhance CD8+ T cell infiltration and cytotoxicity, confirming the immunogenicity of ferroptosis[120,121]. Following ferroptosis, tumor cells can reshape the immune microenvironment via DAMPs and metabolic signaling (Figure 4a).
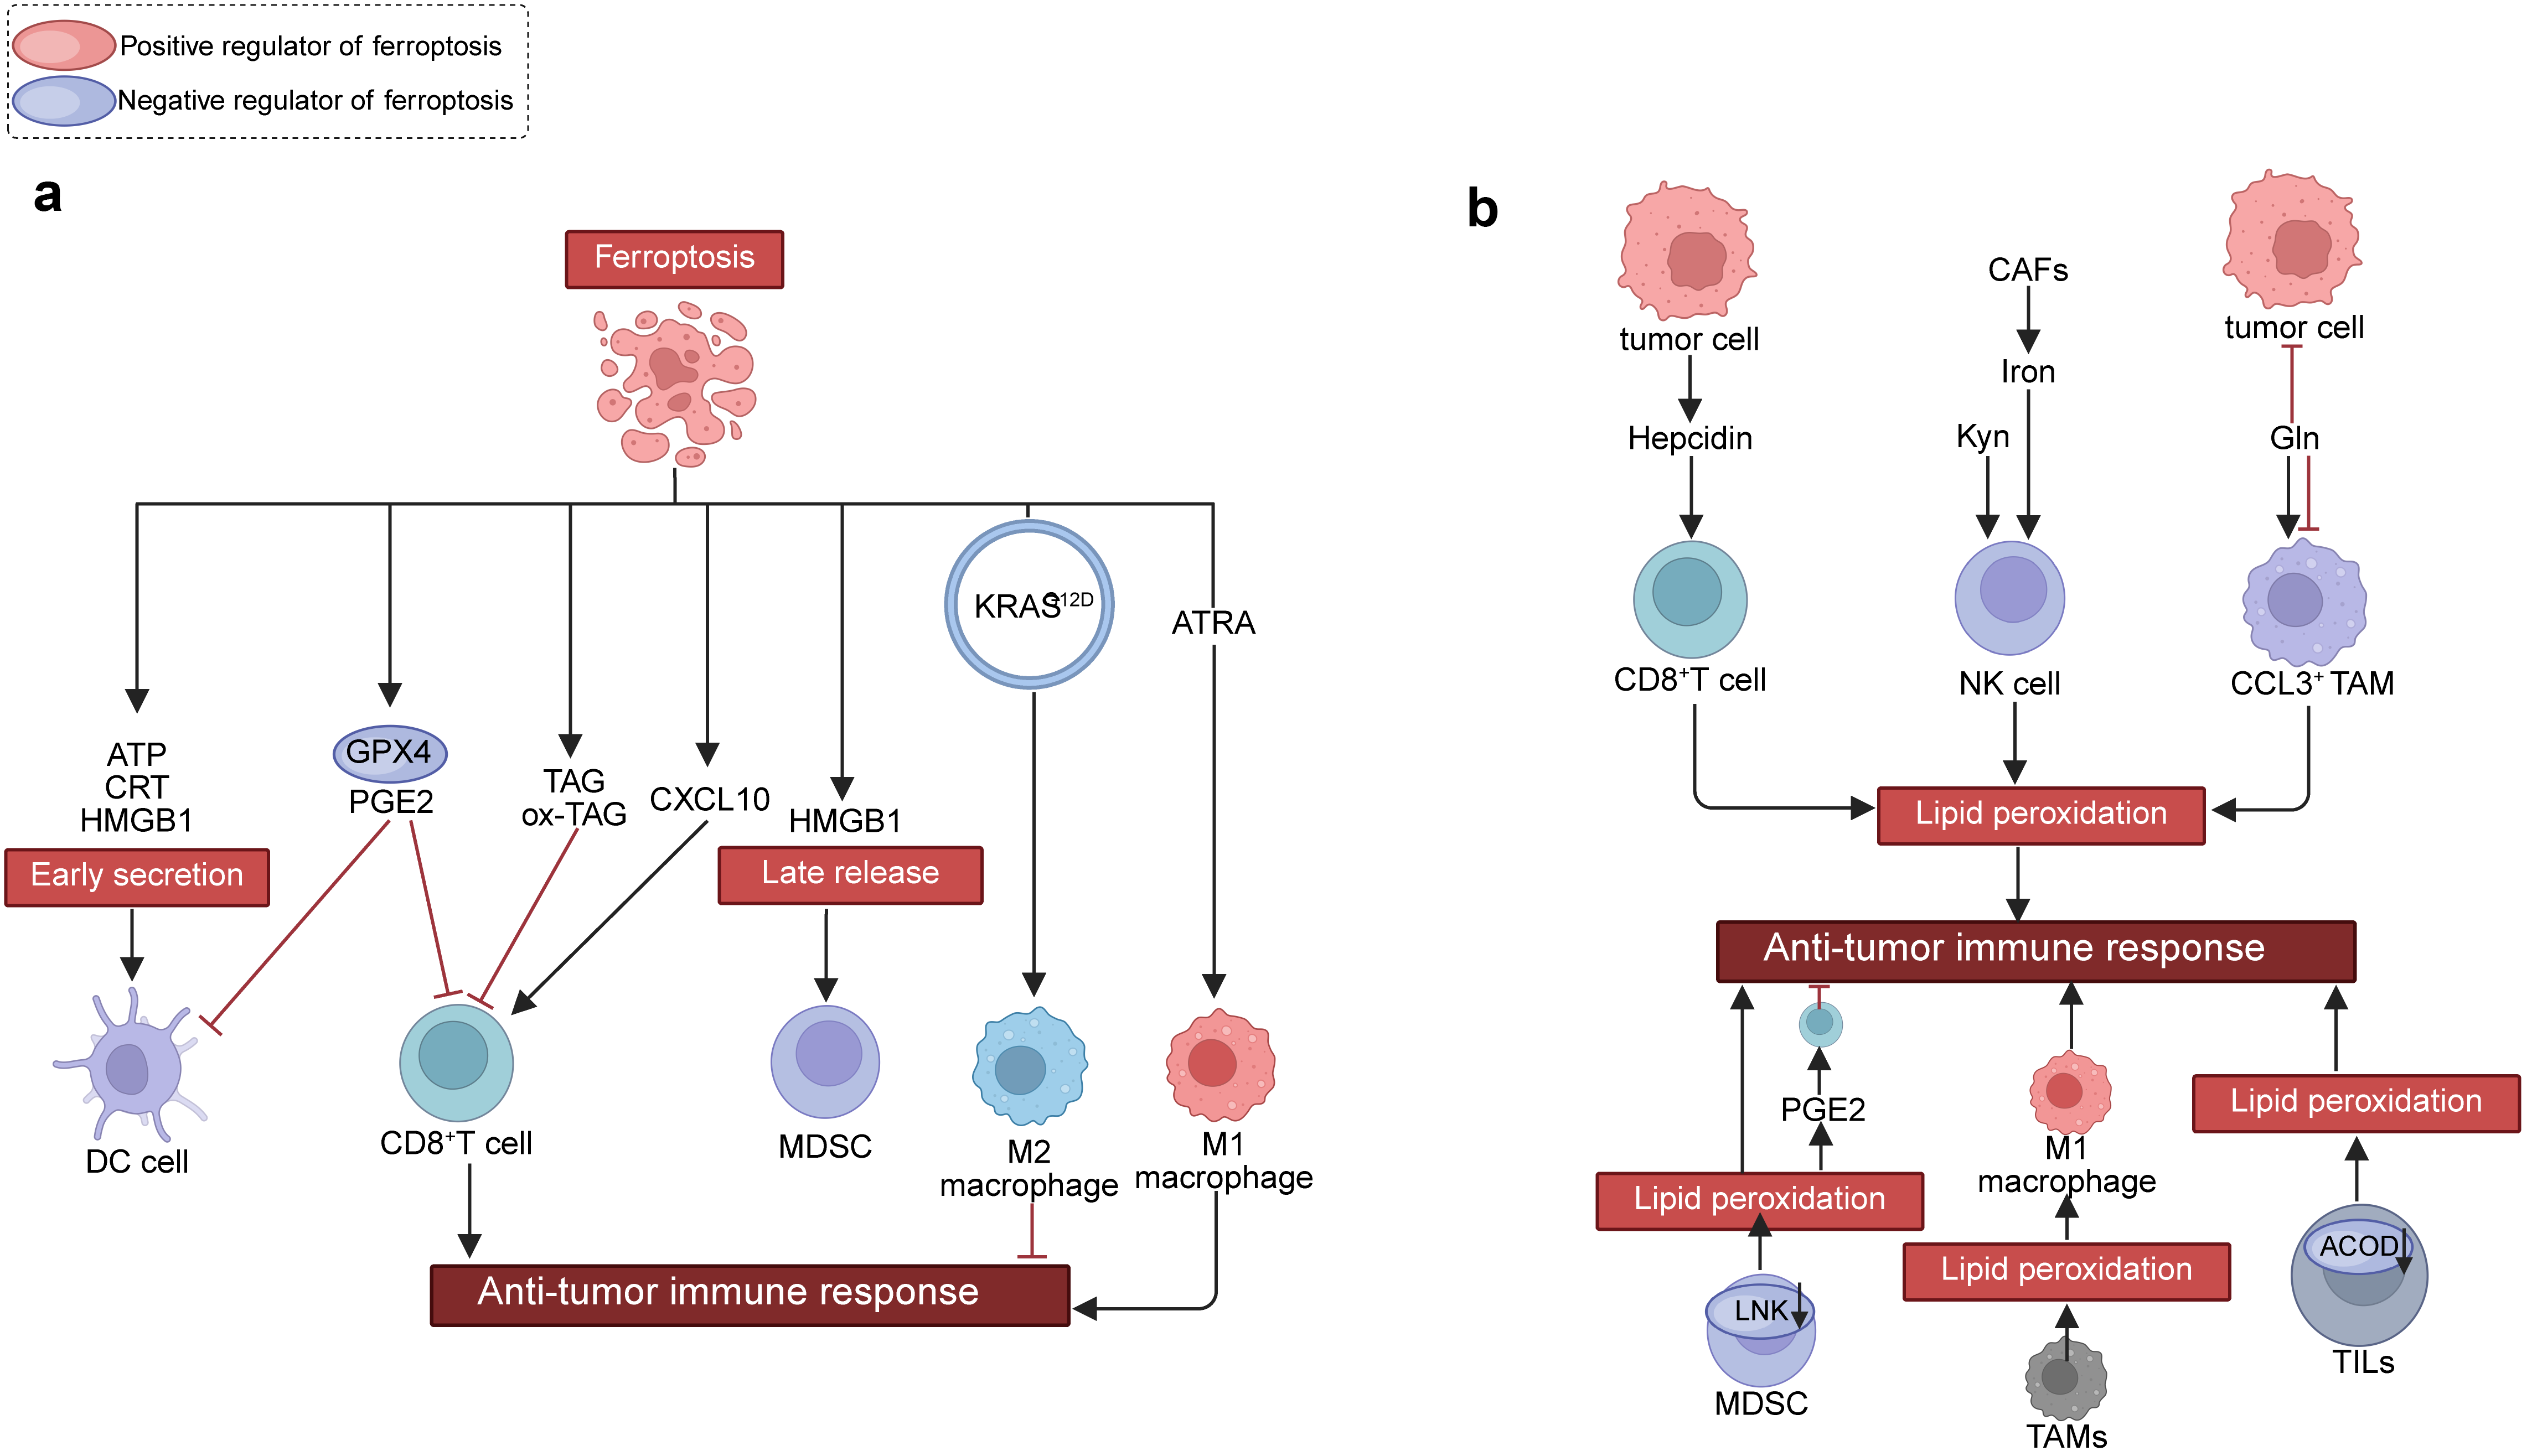
Figure 4. Bidirectional crosstalk between ferroptosis and anti-tumor immunity. (a) Ferroptotic tumor-derived DAMPs and metabolites remodel the immune microenvironment with dual immunomodulatory effects; (b) Immune-cell ferroptosis is regulated by the extracellular landscape and consequently affects anti-tumor immunity. Created in BioRender. Guo, Y. (2026) https://BioRender.com/opcpo8m. CRT: calreticulin; HMGB1: high mobility group protein B1; DC: dendritic cell; GPX4: glutathione peroxidase 4; PGE2: prostaglandin E2; TAG: triacylglycerides; CXCL10: C-X-C motif chemokine ligand 10; MDSC: myeloid-derived suppressor cell; ATRA: all-trans retinoic acid; CAFs: cancer-associated fibroblasts; Kyn: kynurenine; NK: natural killer; Gln: glutamine; TAM: tumor-associated macrophages; LNK: lymphocyte adaptor protein; TILs: tumor-infiltrating lymphocytes; ACOD: aconitate decarboxylase; DAMPs: damage-associated molecular patterns.
Various DAMPs released by ferroptotic cells participate in immune regulation. The externalization of calreticulin (CRT) is a hallmark of ICD which can activate DCs and cytotoxic T cells. DAMPs such as high mobility group protein B1 (HMGB1) and ATP can also activate DCs to enhance anti-tumor immunity[120,122,123]. Hepatocellular carcinoma cells undergoing ferroptosis induced by GPX4 deficiency secrete C-X-C motif chemokine ligand 10 (CXCL10) to recruit CD8+ T cells[124]. However, the immune effects of ferroptosis are temporally dependent. Co-culture with late-stage ferroptotic cells inhibits DC proliferation, suggesting that these cells may release inhibitory DAMPs to mediate immune evasion[125]. For instance, HMGB1 released early in ferroptosis promotes DC antigen presentation, whereas HMGB1 passively released following membrane rupture can recruit myeloid-derived suppressor cells (MDSCs), antagonizing CD8+ T cell cytotoxicity[120,124]. Ferroptotic tumor cells also secrete prostaglandin E2 (PGE2), which attenuates the response of CD8+ T cells to IL-2 and reduces T cell infiltration[126,127]. Additionally, autophagy-mediated ferroptotic tumor cells can release exosomes carrying KRASG12D, driving TAMs toward an M2 immunosuppressive phenotype[128]. Furthermore, GPX4 released during ferroptosis can bind to the zona pellucida glycoprotein 3 (ZP3) receptors on the surface of DCs, inhibiting DC antigen presentation and hindering CD8+ T cell activation, highlighting the complexity of ferroptosis that transcends ICD under specific circumstances[126].
Ferroptotic tumor cells also regulate anti-tumor immunity through metabolites. All-trans retinoic acid (ATRA) released by ferroptotic cells enhances the antigen-presenting capacity of M1-TAMs and promotes T cell activation and infiltration[129]. Conversely, tumor cells undergoing ferroptosis due to GPX4 deficiency secrete TAG and ox-TAG as key mediators that drive CD8+ T cell exhaustion, upregulate inhibitory molecules such as PD-1, and foster an immunosuppressive microenvironment[130].
Not only does ferroptosis in tumor cells alter the immune landscape, but ferroptosis in immune cells themselves profoundly affects immunotherapy responses, a process also strictly regulated by the extracellular landscape (Figure 4b). In the TME, CD8+ T cells are highly susceptible to ferroptotic threats. Tumor-derived hepcidin or iron overload in the microenvironment causes iron accumulation in T cells, triggering lipid peroxidation and mitochondrial damage[131]. Clinically, the decline in chimeric antigen receptor T cell (CAR-T) therapy efficacy is closely linked to ferroptosis induced by serum iron accumulation[132]. Upregulated CD36-mediated uptake of PUFAs such as AA exacerbates intracellular PUFA accumulation and peroxidation in CD8+ T cells, leading to ferroptosis, reduced secretion of cytotoxic cytokines, and impaired anti-tumor immunity[133]. Additionally, citraconate depletion makes CD8+ T cells more sensitive to ferroptosis by increasing ALOXs expression[134]. Tumor-secreted PGE2 can also induce ferroptosis in tumor-infiltrating lymphocytes (TILs) via mitochondrial damage, suppressing their function[135]. In the gastric cancer microenvironment, both Kyn and CAF-derived iron drive ferroptosis in natural killer (NK) cells, and upregulating GPX4 or using iron chelators can restore NK cell cytotoxicity[136,137]. Tumor cells with high heme binding protein 2 (HEBP2) expression consume extracellular Gln, inducing ferroptosis in Gln-dependent CCL3+ pro-inflammatory macrophages and mediating immune resistance[138].
Ferroptosis in immune cells exhibits bidirectional effects and is not merely detrimental to anti-tumor immunity. For example, inducing ferroptosis in TAMs can promote their reprogramming toward an M1 phenotype, improving therapeutic outcomes in liver cancer[139]. Ferroptosis in lymphocyte adaptor protein (LNK)-deficient MDSCs can relieve their suppression of CD8+ T cells[140]. However, ferroptotic MDSCs can also release PGE2 to inhibit TILs[141]. Therefore, simultaneous neutralization of PGE2 is required to achieve optimal anti-tumor efficacy. Deficiency of aconitate decarboxylase 1 (ACOD1) in tumor-infiltrating neutrophils (TINs) promotes ferroptosis and thus inhibits breast cancer progression[142].
In summary, ferroptosis in tumor cells and immune cells forms a complex bidirectional regulatory network. Inducing ferroptosis in tumor cells or immunosuppressive immune cells like MDSCs and TAMs, while protecting effector immune cells such as CD8+ T cells and NK cells from ferroptosis, is a crucial strategy for enhancing immunotherapy. Furthermore, given the temporally dependent, dual immune activities of factors like DAMPs released by ferroptotic cells, they represent highly promising therapeutic targets. It is worth noting that current research on ferroptosis in immune cells largely relies on lipid peroxidation markers and pharmacological rescue experiments using ferroptosis inhibitors like Ferrostatin-1. There is a lack of genetic intervention evidence targeting core regulatory molecules such as GPX4, ACSL4, and FSP1, making it difficult to completely distinguish ferroptosis from cell death mediated by general oxidative stress. Given the current absence of exclusive, specific biomarkers for ferroptosis, future research urgently needs to integrate genetic interventions targeting core molecules and establish combined pharmacological and genetic evidence to further clarify the true biological roles of ferroptosis in immune cells.
5. Tumor Therapeutic Strategies Based on the Extracellular Landscape
Currently, various strategies have been developed to enhance ferroptosis in tumor cells for improved therapeutic outcomes. However, the bidirectional regulation between ferroptosis and the immune microenvironment suggests that enhancing tumor-specific targeting is essential for improving efficacy and preventing immune escape in ferroptosis-based therapies. Furthermore, the regulation of tumor cell ferroptosis by the extracellular landscape provides important insights into improving the specificity and feasibility of targeted interventions (Figure 5).
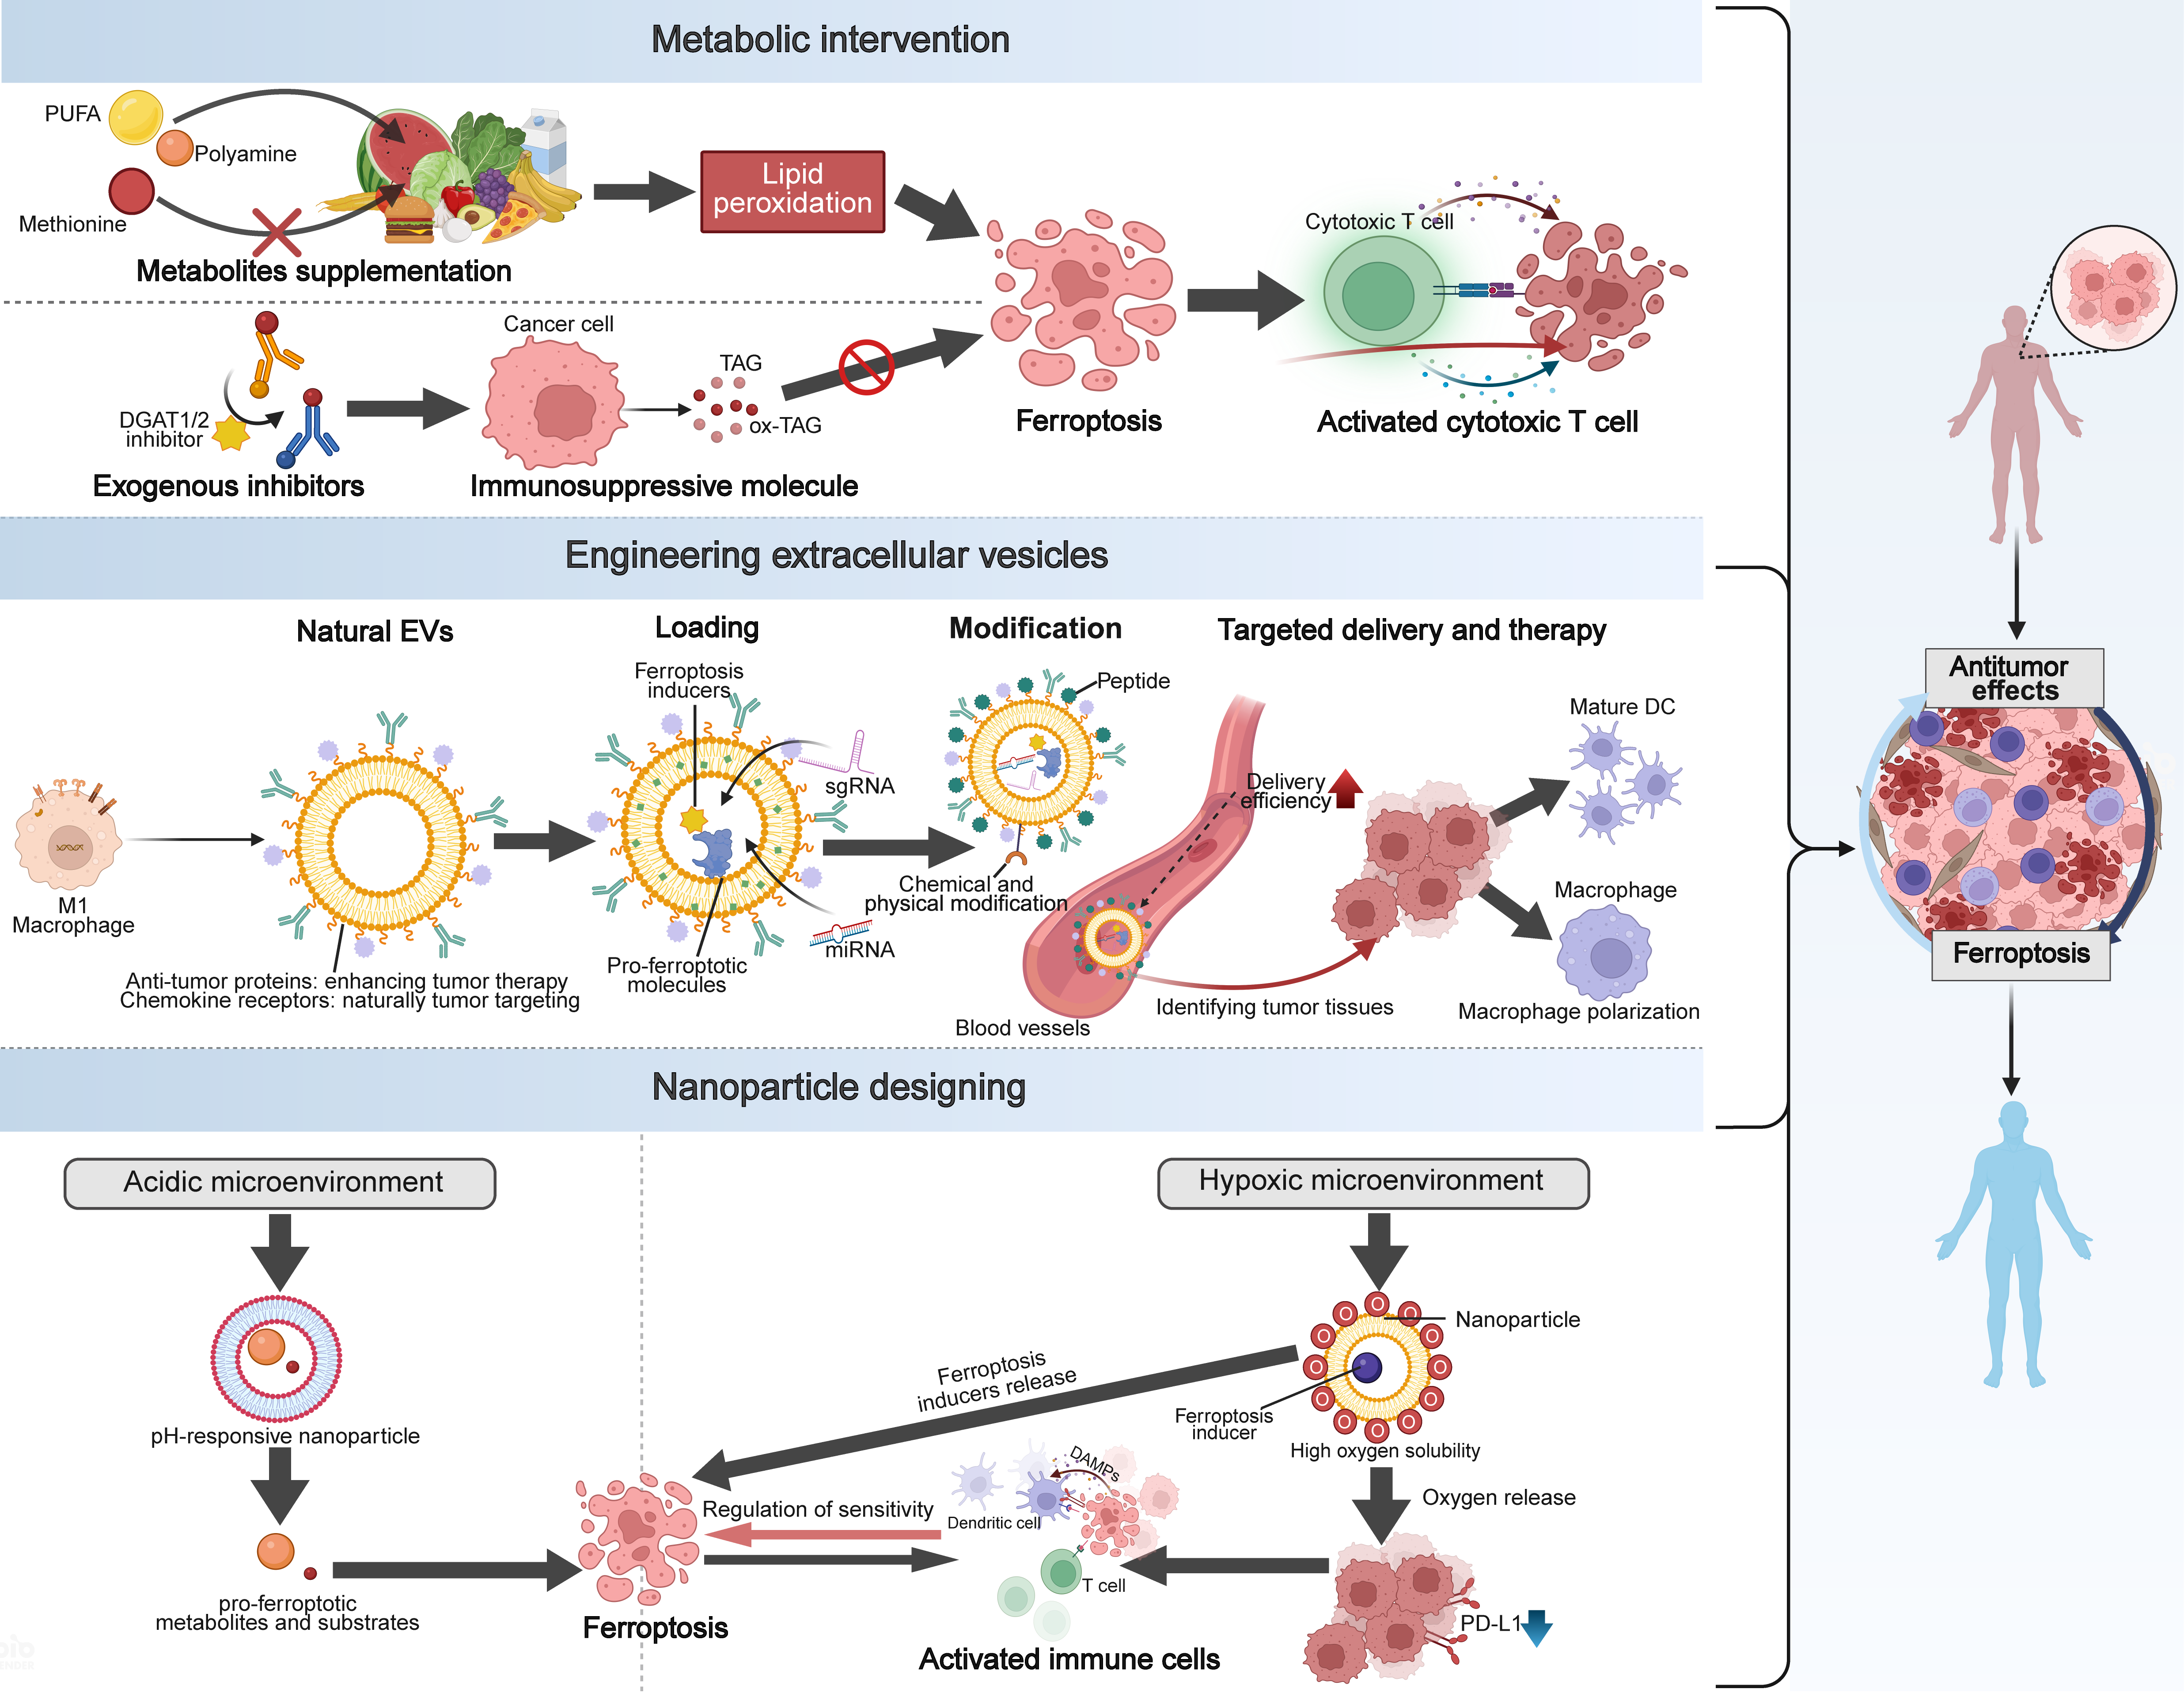
Figure 5. Overview of three extracellular-targeted ferroptosis therapeutic strategies for anti-tumor immunotherapy. Three classes of intervention strategies are summarized: metabolic intervention, engineered EV-based delivery, and tumor-microenvironment-responsive nanoparticles. Metabolic intervention promotes lipid peroxidation, whereas engineered EVs deliver ferroptotic cargoes for precise tumor targeting. pH- and hypoxia-responsive nanoparticles target and reverse adverse microenvironmental features to enhance ferroptosis-based immunotherapy. All three approaches activate anti-tumor immune responses via DAMP release and achieve final antitumor effects. Created in BioRender. Guo, Y. (2026) https://BioRender.com/appbonj. EVs: extracellular vesicles; DAMP: damage-associated molecular pattern; PUFA: polyunsaturated fatty acid; DGAT1/2: diacylglycerol O-acyltransferase 1/2; TAG: triacylglycerides; DC: dendritic cell.
5.1 Metabolic intervention: Reshaping the extracellular nutrient environment
The survival of tumor cells depends on the uptake of nutrients from the extracellular environment. By intervening in the diet or supplementing specific metabolites externally, it is possible to alter the extracellular metabolic landscape, thereby depleting tumors or inducing oxidative cell death.
Exogenous supplementation with specific metabolites can directly activate ferroptosis in tumor cells. Adjusting the ratio of PUFAs to MUFAs in the diet, or increasing the intake of PUFA synthesis substrates such as linoleic acid, can elevate intracellular levels of PUFAs, thereby providing ample substrates for lipid peroxidation[15,43]. In addition, overburdened polyamines synthesized within EVs produce H2O2, which participates in Fenton reactions in the cytoplasm, and thus exogenous polyamine, such as spermidine and spermine supplementation can significantly enhance the effectiveness of radiotherapy and cisplatin[27,98]. Meanwhile, restricting the intake of specific nutrients can disable the antioxidant defense system of tumor cells. For instance, studies have shown that limiting Met in the diet not only inhibits tumor progression by triggering GSH depletion-induced ferroptosis but also exhibits a synergistic effect when combined with PD-1 inhibitors, enhancing T-cell-mediated anti-tumor immunity[80,143]. However, given the inherent ferroptosis-promoting properties of Met, dietary methionine intervention warrants careful evaluation of tumor metabolic preferences and potential circadian disruptions, among other factors.
In addition to promoting ferroptosis, blocking the immunosuppressive molecules released by ferroptotic cells also represents an important direction for metabolic intervention. The application of DGAT1/2 inhibitors can not only induce ferroptosis by blocking LD synthesis, but also prevent tumor cells from secreting TAG and ox-TAGs, thereby relieving their inhibitory effects on T-cell function[51,130]. Although DGAT1/2 inhibitors have not yet been applied in clinical trials for cancer treatment, they have entered Phase II clinical trials for metabolic diseases, providing a strong theoretical and feasibility basis for their subsequent application in inducing ferroptosis to enhance the responsiveness of cancer immunotherapy[144].
5.2 Engineered extracellular vesicles: Precise delivery of ferroptosis signals
EVs, as natural messengers for intercellular communication, exhibit low immunogenicity and an exceptional ability to traverse cellular membranes. Through engineered modification, EVs have emerged as a powerful tool for delivering ferroptosis-inducing agents and reshaping the immune microenvironment.
For nucleic acid delivery, genetic engineering techniques can be employed to load otherwise membrane-impermeable nucleic acids into EVs. EVs loaded with miR-150-3p can trigger ferroptosis in melanoma cells via the YAP signaling pathway[145]. EVs loaded with Cas9 sgRNA targeting BRAF knockout inhibit autophagy of TFRC in thyroid cancer cells, increase intracellular LIP levels, and reverse vemurafenib resistance[146]. Furthermore, EVs loaded with sgRNA targeting glutathione synthetase (GSS) or circ_0004872 have shown potential to sensitize gliomas to radiotherapy and osteosarcomas to chemotherapy, respectively[147,148].
EVs also excel in protein and drug delivery. EVs secreted by irradiated tumor cells and loaded with ferroptosis inducers, can directly trigger ferroptosis while simultaneously promoting DC maturation and M1 macrophage polarization[149,150]. Exosomes derived from glioblastoma cells encapsulating arsenic trioxide (ATO) can induce ferroptosis in syngeneic tumor cells and release DAMPs and ox-mtDNA, thereby reversing the immunosuppressive microenvironment[151]. Particularly noteworthy is that EVs derived from M1 macrophages have become a research hotspot due to their ability to carry anti-tumor proteins and exhibit natural tumor-targeting properties through chemokine receptors[152-154]. Engineered M1-EVs can release Fe3+ within tumors to initiate ferroptosis or deliver HSC70 to promote GPX4 degradation[155,156]. Such delivery of engineered M1-EVs not only directly kills tumors but also foster TAM polarization toward the M1 phenotype, thereby reversing immunosuppression in the TME and demonstrating preclinical translational potential.
Though M1-EVs exhibit tumor-targeting properties, to strengthen the targeting specificity of EVs, researchers often modify their EVs’ membrane surfaces with tumor-targeting peptides such as the trans-activator of transcription (TAT) peptide, which can penetrate dense tumor tissues[157]. Tumor metastasis targeting peptide 1 (TMTP1) targets thyroid cancer[146]. The RS17 peptide exhibits specific affinity for CD47 on tumor cells[158]. Additionally, engineered vesicles functionalized with internalizing RGD (iRGD) can specifically recognize integrins αvβ3 and αvβ5, which are highly expressed on melanoma cells and tumor vasculature[145]. Furthermore, surface modification of EVs can enhance their vascular penetration capability and increase delivery efficiency. Addition of NGR peptide enables targeting of endothelial cells[148]. Glycosylation modification, altering the composition of PLs, or adding polymers such as polyethylene glycol (PEG) to the surface can modulate the binding of vesicles to vascular endothelial cells and reduce vascular injury induced by immunogenicity, thereby enhancing the penetration ability of vesicles[159-161].
5.3 Bio-nanoparticles that respond to tumor microenvironment characteristics
The TME of solid tumors is characterized by hypoxia, acidity, and high levels of ROS. These features not only serve as barriers to tumor survival but also provide inspiration for the design of nanomedicines for targeted delivery to tumor tissues.
In response to the hypoxic microenvironment, researchers have developed a fluorinated prodrug-engineered nano-reconstructor named FJSO NA. This nanomedicine exhibits high oxygen solubility and can release oxygen specifically at the tumor site, thereby alleviating hypoxia, downregulating PD-L1 expression, and simultaneously releasing sorafenib to induce ferroptosis and ferroptosis-evoked ICD[162]. Another hypoxia-responsive nanoplatform loaded with Fe2+ and Mdivi-1 triggers ferroptosis by promoting mitochondrial damage and boosting the Fenton reaction to improve anti-tumor immunotherapy[163].
For acidic microenvironments, pH-responsive nanomaterials have become a research focus. pH-responsive cinnamaldehyde is released only in acidic environments and produces H2O2 to promote ferroptosis[164]. The spermidine/Fe2+ hydrogel releases spermidine and Fe2+ in an acidic environment, inducing ferroptosis and releasing DAMPs to activate CD8+ T cells[165]. Moreover, iron nanoparticles loaded with proton pump inhibitors can both inhibit proton efflux from tumor cells, thereby alleviating extracellular acidosis-induced immunosuppression, and lower intracellular pH to trigger the Fenton reaction, thus activating anti-tumor immunity through both microenvironmental improvement and direct cytotoxicity[166,167]. FeS nanosheets utilize their unique redox properties to generate Fe2+ and H2S under the acidic tumor microenvironment, inducing ferroptosis while scavenging ROS in neutral normal tissues, thus achieving highly effective and low-toxicity precision therapy[168]. Regarding increased ROS levels in the TME, a ROS-responsive nanoparticle was designed to release Fe3O4 and tuftsin to activate ferroptosis and reverse the immunosuppressive TME when dissolved by extracellular H2O2[169].
5.4 Challenges for clinical translation
Although extracellular landscape-based strategies show promise in preclinical studies, several critical challenges remain before clinical translation.
Metabolic intervention can induce tumor ferroptosis, yet dietary approaches and systemic metabolic inhibitors lack tumor specificity. They may cause systemic toxicity, damage normal tissues, and inadvertently trigger ferroptosis in cytotoxic immune cells within the TME, thereby undermining anti-tumor immunity[133]. These strategies also face pharmacokinetic limitations and scarce clinical validation. Moreover, ferroptosis sensitivity is highly dependent on the metabolic context. Distinct tumor regions may respond heterogeneously to the same intervention, making precise intratumoral metabolic modulation difficult to achieve through conventional systemic approaches.
Engineered EVs can be modified with targeting peptides and membrane engineering to improve tumor targeting and delivery efficiency. However, their clinical translation is limited by substantial heterogeneity across cell sources, inconsistent cargo loading, variable pharmacokinetics, and the absence of standardized isolation, purification, and quality control protocols. Some native EV surface molecules may exert pro-tumorigenic effects, and the immunogenicity of engineered EVs remains difficult to predict[170,171]. Most evidence remains preclinical, and large-scale good manufacturing practice (GMP)-grade EV manufacturing remains technically challenging.
Synthetic nanomaterials offer precise design, controllable drug loading, and scalable production. Nevertheless, the in vivo delivery efficiency is often limited by immunogenicity, poor tissue penetration, and cellular barriers, resulting in insufficient accumulation within the TME[172,173]. In vivo safety, pharmacokinetics, and off-target effects must also be rigorously evaluated before clinical application.
Based on these limitations and the research evidence (Table 2), metabolic intervention appears most readily implementable, supported by accessible small-molecule inhibitors, dietary modulation, and nutrient restriction strategies that enable rapid preclinical combination studies with ferroptosis inducers and immunotherapy. DGAT1/2 inhibitors have entered phase II trials for metabolic diseases, providing preliminary safety reference for potential oncology applications, although anti-tumor efficacy in humans remains unverified[144]. Their systemic nature raises risks of off-target ferroptosis in cytotoxic immune cells and limits precision due to spatial metabolic heterogeneity. Tumor microenvironment-responsive nanomaterials have the most robust preclinical evidence, with in vivo studies demonstrating immunogenic ferroptosis induction and immune microenvironment remodeling, along with mature material design and scalable fabrication. However, risks of in vivo accumulation, immunogenicity, and off-target toxicity cannot be fully excluded, requiring further long-term safety and pharmacokinetic evaluation. Engineered EVs, represented by M1-EVs, show dual preclinical potential for tumor homing and immune modulation, but their translational feasibility remains limited due to cargo heterogeneity, lack of standardized quality control, GMP-scale production challenges, and incomplete tumor-specific delivery, necessitating systematic validation before therapeutic development.
Table 2. Summary of extracellular landscape-targeting therapeutic strategies.
| Strategy category | Therapeutic approach | Mechanism of ferroptosis induction | Stage of evidence | Ref. |
| Metabolic intervention | Dietary PUFA enrichment (adjusting PUFA:MUFA ratio and linoleic acid supplementation) | Elevates intracellular PUFA levels, providing ample substrates for lipid peroxidation. | Preclinical (in vivo) | [15,43] |
| Exogenous polyamine supplementation | Polyamine oxidation generates H2O2 that fuels cytoplasmic Fenton reactions. | Preclinical (in vivo) | [27,98] | |
| Dietary methionine restriction | Triggers GSH depletion-induced ferroptosis and suppresses tumor progression. | Preclinical (in vivo) | [80,143] | |
| DGAT1/2 inhibitors | Block LD synthesis to induce ferroptosis and prevent secretion of TAG and ox-TAGs. | Phase II clinical trials for metabolic diseases but not yet tested in tumor patients | [51,130,144] | |
| Engineered EVs | EVs loaded with miR-150-3p | Trigger ferroptosis via the YAP signaling pathway. | Preclinical (in vivo) | [145] |
| EVs loaded with Cas9-sgRNA targeting BRAF | Inhibit TFRC autophagy to increase intracellular LIP. | Preclinical (in vivo) | [146] | |
| EVs loaded with sgRNA targeting GSS | Knockdown GSS to inhibit GSH synthesis. | Preclinical (in vivo) | [147] | |
| EVs modified with ascular-targeting peptide NGR and carrying circ_0004872-109aa | Promote autophagy-dependent ferroptosis in osteosarcoma. | Preclinical (in vivo) | [148] | |
| EVs derived from irradiated tumor cells and loaded with ferroptosis inducers | Directly trigger ferroptosis in recipient tumor cells. | Preclinical (in vivo) | [149,150] | |
| ATO-encapsulating exosomes | Induce ferroptosis in syngeneic tumor cells. | Preclinical (in vivo) | [151] | |
| M1-EVs loaded with Fe3+ | Release Fe3+ to initiate ferroptosis. | Preclinical (in vivo) | [155,156] | |
| M1-EVs loaded with HSC70 | Deliver HSC70 to promote GPX4 degradation. | Preclinical (in vivo) | [155,156] | |
| TME-responsive bio-nanoparticles | Hypoxia-responsive: fluorinated prodrug-engineered nano-reconstructor (FJSO NA) | High oxygen solubility Releases O2 at the tumor site to alleviate hypoxia and simultaneously releases sorafenib to induce ferroptosis. | Preclinical (in vivo) | [162] |
| Hypoxia-responsive: nanoplatform embedding Mdivi-1 and Fe2+ | Fe2+ triggers ferroptosis and Mdivi-1 promotes mitochondrial damage. | Preclinical (in vivo) | [163] | |
| pH-responsive: cinnamaldehyde-based nanomaterials | Cinnamaldehyde is released only in acidic environments and generates H2O2 to promote ferroptosis. | Preclinical (in vivo) | [164] | |
| pH-responsive: spermidine/Fe2+ hydrogel | Acidic environment triggers release of spermidine and Fe2+ to induce ferroptosis. | Preclinical (in vivo) | [165] | |
| pH-targeting: iron nanoparticles loaded with the NHE inhibitor Cariporide | Inhibit NHE-mediated proton extrusion to alleviate extracellular acidosis and lower intracellular pH to Release Fe2+. | Preclinical (in vivo) | [166] | |
| pH-targeting: iron nanoparticles loaded with the proton pump inhibitor pantoprazole | Inhibit proton efflux to alleviate extracellular acidosis and lower intracellular pH to trigger the Fenton reaction. | Preclinical (in vivo) | [167] | |
| pH/redox-responsive: FeS nanosheets | Generate Fe2+ and H2S in the acidic TME to induce ferroptosis and also scavenge ROS in neutral normal tissues. | Preclinical (in vivo) | [168] | |
| ROS-responsive nanoparticles | Dissolved by extracellular H2O2 to release Fe3O4 and tuftsin, activating ferroptosis. | Preclinical (in vivo) | [169] |
PUFA: polyunsaturated fatty acid; MUFAs: monounsaturated fatty acids; GSH: glutathione; LD: lipid droplet; DGAT1/2: diacylglycerol O-acyltransferase 1/2; TAG: triacylglycerides; EVs: extracellular vesicles; TFRC: transferrin receptor; GSS: glutathione synthetase; ATO: arsenic trioxide; NHE: Na+/H+ exchanger; GPX4: glutathione peroxidase 4; TME: tumor microenvironment; ROS: reactive oxygen species.
Moving forward, spatial transcriptomics, spatial metabolomics, and multiplex imaging should be leveraged to map regional ferroptosis susceptibility and guide the rational design of spatially targeted therapies. Rigorous preclinical in vivo evaluation of biosafety, off-target effects, targeted delivery, and pharmacokinetics is essential. Multicenter clinical trials integrating multi-omics technologies and standardized workflows will ultimately be required to achieve precise clinical translation of ferroptosis-based therapy.
In summary, tumor treatment strategies based on the extracellular landscape that reprogram metabolism to reshape nutrient availability, leverage engineered EVs for precise signal delivery, and design nanoparticles responsive to microenvironmental cues provide a novel approach for overcoming tumor drug resistance and immune evasion. Notably, ferroptosis exhibits a close bidirectional interplay with the immune microenvironment. Given that ferroptotic cells also secrete immunosuppressive signals, blockade of this transmission pathway represents an additional therapeutic strategy for tumor treatment. Future research should further elucidate the molecular mechanisms underlying this interactive network and develop more combination therapies targeting the extracellular landscape, so as to achieve synergistic enhancement of ferroptosis and immunotherapy and bring patients with cancer longer-lasting survival benefits.
6. Discussion and Perspective
Traditionally, ferroptosis has been largely viewed from the perspective of intracellular metabolic networks. However, accumulating evidence indicates that the extracellular landscape, including nutrient availability, the physicochemical milieu, intercellular communication via EVs and soluble factors, and the cellular composition of the TME, profoundly shapes cellular susceptibility to ferroptosis. This extracellular perspective expands the druggable space of ferroptosis regulation and offers intervention strategies complementary to canonical intracellular targets, such as reshaping the metabolic microenvironment, engineering intercellular communication, and developing microenvironment-responsive delivery systems.
Preclinical studies have begun to explore this direction. Dietary modulation of the PUFA:MUFA ratio or Met availability can systemically sensitize tumor cells to ferroptosis[15,80,143], while engineered EVs and TME-responsive nanomaterials aim for spatiotemporal control of ferroptosis induction[145,146,148,155,162,165,166]. However, such interventions are highly context-dependent. Short-term Met restriction induces ferroptosis via GSH depletion, whereas chronic restriction maintains GSH homeostasis via inhibition of CHAC1 degradation, thereby suppressing ferroptosis, necessitating temporal optimization of Met-restricted diets[80]. Similarly, exogenous polyamines can promote ferroptosis through H2O2 generation yet simultaneously act as intracellular iron chelators to inhibit ferroptosis, requiring compensatory designs such as Fe2+-polyamine co-delivery or controlled dosing to saturate their chelation capacity[27,98,165]. The engineering of vesicles and the synthesis of nanomaterials must be tailored to specific tumor types and microenvironmental contexts. These examples reflect a general feature of the field: most regulatory mechanisms and therapeutic hypotheses were established in vitro or in simplified mouse models, and their actual effects in the complex human TME may deviate substantially from preclinical predictions.
Importantly, any ferroptosis-based strategy should fully account for the bidirectional interplay between ferroptosis and anti-tumor immunity. Ferroptosis can function as ICD, releasing DAMPs that activate dendritic cells and CD8+ T cells, yet ferroptotic cells also release immunosuppressive mediators such as PGE2, TAG, and ox-TAG, which suppress T cell function and promote exhaustion[120,122,123,126,127,130]. Moreover, in the lipid- and iron-rich TME, effector immune cells themselves are susceptible to ferroptosis, undermining the very anti-tumor immunity on which these therapies depend[131-133,137]. Therefore, an ideal extracellular ferroptosis intervention should not merely maximize tumor cell or immunosuppressive cell killing, but also selectively induce ferroptosis in tumor cells while sparing cytotoxic T and NK cells and controlling the temporal release of immunogenic versus immunosuppressive signals. If necessary, combining ferroptosis inducers with checkpoint inhibitors, PGE2-neutralizing agents, or DGAT1/2 inhibitors to sustain anti-tumor immunity may also be beneficial. These requirements substantially raise the bar for the specificity and controllability of future interventions.
Although targeting the extracellular landscape opens new avenues for ferroptosis-based cancer therapy, several key limitations remain, as detailed in the preceding sections. First, ferroptosis-specific biomarkers are still lacking, as most in vivo studies rely on lipid peroxidation markers, iron accumulation, and pharmacological rescue with ferroptosis inhibitors. Thus, ferroptosis, especially in immune cells, lacks direct in vivo evidence. Second, ferroptosis susceptibility is highly heterogeneous across tumor types, spatially distinct intratumoral niches, and immune cell populations, making it difficult to predict responses in specific patients, tumor regions, or cell subsets. Third, the dynamic, locally acting nature of extracellular signals renders in vivo validation technically demanding, necessitating rigorous studies combining genetic manipulation of core regulators such as GPX4 and ACSL4 with pharmacological approaches. Fourth, clinical translation is constrained by the absence of prospective clinical trials, the limited tumor specificity and potential immune toxicity of systemic interventions, and the manufacturing and safety challenges of engineered EVs and nanomaterials.
Overall, this review systematically outlines the multiple modes by which the extracellular landscape regulates ferroptosis, the strategies developed to exploit this space, and the contradictions that remain. Shifting focus from intracellular enzymes to the extracellular landscape opens new directions for ferroptosis-based cancer therapy, yet the field remains in its early stages. Future progress will depend on discovering ferroptosis-specific biomarkers, dissecting tumor and immune heterogeneity, rigorous in vivo validation, and rationally designed combinations that induce tumor cell ferroptosis while preserving and enhancing anti-tumor immunity. Only through such efforts can extracellular ferroptosis modulation be translated into safe and effective clinical therapies.
Acknowledgements
All figures were created with BioRender.com. The authors declare that DeepSeek was used solely for language polishing during the manuscript preparation process. The central theme, organization, arguments and conclusions of this review and the creation of figures and tables are original and were not generated using AI tools. The authors reviewed, revised, and approved the final manuscript and take full responsibility for its content.
Authors contribution
Guo W, Qian L: Conceptualization, visualization, writing-original draft, writing-review & editing.
Guo S, Qiu S, Xue X, Zhang X, Ma L: Writing-review & editing.
Yu Y, Wang J: Conceptualization, writing-review & editing.
Conflicts of interest
The authors declare no conflicts of interest.
Ethical approval
Not applicable.
Consent to participate
Not applicable.
Consent for publication
Not applicable.
Availability of data and materials
Not applicable.
Funding
None.
Copyright
© The Author(s) 2026.
References
-
39. Song X, Zhou Z, Liu J, Li J, Yu C, Zeh HJ, et al. Cytosolic cytochrome c represses ferroptosis. Cell Metab. 2026;38(3):633-634.[DOI]
-
139. Hao X, Zheng Z, Liu H, Zhang Y, Kang J, Kong X, et al. Inhibition of APOC1 promotes the transformation of M2 into M1 macrophages via the ferroptosis pathway and enhances anti-PD1 immunotherapy in hepatocellular carcinoma based on single-cell RNA sequencing. Redox Biol. 2022;56:102463.
-
165. Nie T, Fang Y, Zhang R, Cai Y, Wang X, Jiao Y, et al. Self-healable and pH-responsive spermidine/ferrous ion complexed hydrogel co-loaded with CA inhibitor and glucose oxidase for combined cancer immunotherapy through triple ferroptosis mechanism. Bioact Mater. 2025;47:51-63.
Copyright
© The Author(s) 2027. This is an Open Access article licensed under a Creative Commons Attribution 4.0 International License (https://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, sharing, adaptation, distribution and reproduction in any medium or format, for any purpose, even commercially, as long as you give appropriate credit to the original author(s) and the source, provide a link to the Creative Commons license, and indicate if changes were made.
Publisher’s Note
Science Exploration remains a neutral stance on jurisdictional claims in published
maps
and institutional affiliations. The views expressed in this article are solely those
of
the author(s) and do not reflect the opinions of the Editors or the publisher.
Share And Cite


Science Exploration Style
Guo W, Qian L, Guo S, Qiu S, Xue X, Ma L, et al. Extracellular landscape of ferroptosis: A new direction to enhance anti-tumor efficacy. Ferroptosis Oxid Stress. 2027;3:202629. https://doi.org/10.70401/fos.2026.0047
Tips
Copy completed.
Submit a Manuscript
Author Instructions
Cite this Article
Article Metrics
0
View
0
Download
Cited
Article Updates

- Abstract
- Keywords
- 1. Introduction
- 2. Intracellular Molecular Mechanism of Ferroptosis
- 3. Regulation of Ferroptosis by Metabolic Substance Exchange between Intracellular and Extracellular Spaces
- 4. Cell-to-Cell Communication: Signaling of Ferroptosis and Remodeling of the Immune Microenvironment
- 5. Tumor Therapeutic Strategies Based on the Extracellular Landscape
- 6. Discussion and Perspective
- Acknowledgements
- Authors contribution
- Conflicts of interest
- Ethical approval
- Consent to participate
- Consent for publication
- Availability of data and materials
- Funding
- References
- Copyright
 Get citation
Science Exploration Style

Guo W, Qian L, Guo S, Qiu S, Xue X, Ma L, et al. Extracellular landscape of ferroptosis: A new direction to enhance anti-tumor efficacy. Ferroptosis Oxid Stress. 2027;3:202629. https://doi.org/10.70401/fos.2026.0047
copy
Share Link
copy