Beyond ferroptosis induction: Defining ferroptosis vulnerability in glioblastoma

Jenna K Minami
1,#

,
Jennifer J Salinas
1,#
,
Caitlyn E Loo
1
,
Weaverly Colleen Lee
2
,
Scott J Dixon
2,†
,
David A Nathanson
1,†,*
*Correspondence to:
David A Nathanson, Department of Molecular and Medical Pharmacology, University of California, Los Angeles, CA 90095, USA.
E-mail: DNathanson@mednet.ucla.edu
Ferroptosis Oxid Stress. 2027;3:202637. 10.70401/fos.2026.0048
Received: July 14, 2026Accepted: September 30, 2026Published: October 01, 2026
Abstract
Glioblastoma (GBM) is the most lethal primary brain tumor, with minimal therapeutic progress over the past two decades. A defining feature of GBM is its intrinsic resistance to apoptosis, prompting interest in activating alternative cell death pathways such as ferroptosis, an iron-dependent process driven by lipid peroxidation. In GBM, ferroptosis represents a context-dependent vulnerability that arises directly from tumor-specific lipid metabolic reprogramming. Here, we outline a unifying framework in which ferroptosis sensitivity is governed by three interdependent axes: availability of oxidizable lipids, redox buffering, and iron handling. Genetic alterations common in GBM, such as CDKN2A loss, EGFR amplification or mutation, and PTEN loss, reshape these axes to either suppress or promote ferroptotic cell death. This susceptibility is further modulated by cellular state and the tumor microenvironment. Effective therapeutic targeting will require biomarker-driven patient stratification, rational combination strategies, and the development of brain-penetrant agents with tumor-selective activity. Together, this framework positions ferroptosis not as a universally inducible death pathway in GBM, but as a context-dependent vulnerability that can be therapeutically exploited in tumors already poised near the ferroptosis threshold.
Keywords
Glioblastoma, lipid metabolism, ferroptosis, cell death
1. Introduction
Glioblastoma (GBM) is one of the most treatment-resistant human cancers, with survival largely unchanged despite decades of progress in understanding the molecular basis of this disease[1-3]. Classified as a World Health Organization (WHO) grade 4 astrocytic tumor in the 2021 CNS classification, primary GBM is almost exclusively isocitrate dehydrogenase (IDH) wildtype and is defined by various molecular alterations, including Epidermal Growth Factor Receptor (EGFR) amplifications, Cyclin Dependent Kinase Inhibitor 2A/B (CDKN2A/B) homozygous deletion, and Phosphatase and Tensin homolog deleted from chromosome ten (PTEN) loss[4-7]. The current standard of care for newly diagnosed GBM is maximal tumor resection followed by concurrent and adjuvant chemotherapy combined with radiotherapy, which has extended median overall survival from 3-4 months to 14.6 months[1], a figure that has remained largely unchanged for nearly two decades. In part, this therapeutic stagnation may reflect a disconnect between treatment mechanisms and tumor biology. Radiotherapy and most conventional chemotherapies rely on the induction of apoptosis[8,9], whereas GBM exhibits profound resistance to apoptotic cell death[10]. Multiple mechanisms contribute to this resistance, including disruption of tumor protein 53 (TP53) signaling, overexpression of anti-apoptotic B-cell lymphoma 2 (BCL2) family members, and the persistence of quiescent, therapy-refractory glioma stem-like cells[11]. Compounding this challenge, GBM exhibits profound inter- and intra-tumoral heterogeneity. Tumors differ substantially between patients at the intertumoral level in their genetic, transcriptional, and metabolic programs[12], resulting in variable therapeutic vulnerabilities. Furthermore, individual tumors contain diverse cellular populations that recapitulate distinct neurodevelopmental lineages, as determined using single-cell profiling, each with unique functional properties and treatment sensitivities[7,13-15]. Together, cellular heterogeneity and apoptotic resistance limit the efficacy of conventional therapies, suggesting that alternative, non-apoptotic forms of regulated cell death may offer a more effective therapeutic strategy.
Considering these findings, ferroptosis has emerged as a compelling candidate for GBM. Ferroptosis is an iron-dependent form of cell death caused by the accumulation of toxic lipid peroxides, linking its execution directly to lipid metabolism[16-21]. This is highly relevant in GBM, where genetic and non-genetic remodeling of lipid metabolism contributes to tumor progression and therapeutic resistance[12,22,23]. Importantly, not all GBMs are equally sensitive to ferroptosis. Rather, tumors exist along a spectrum of sensitivities defined by their proximity to a ferroptosis threshold[12,18,24-27], the point at which lipid peroxide accumulation overwhelms antioxidant defenses and triggers cell death.
How should we think about ferroptosis sensitivity in GBM? In this review, we propose a unifying framework in which ferroptosis sensitivity in GBM is governed by three axes: lipid availability, redox buffering, and iron handling. We apply this framework to examine how ferroptosis vulnerability is established and modulated in GBM. We discuss how GBM-specific molecular lesions, transcriptional states, and tumor microenvironmental factors converge on the three core axes to position tumors along the ferroptosis threshold (Figure 1). We further explore how this conceptual model can inform biomarker-driven patient stratification, rational combination therapies, and the development of brain-penetrant, tumor-selective therapeutics. By framing ferroptosis as a context-dependent vulnerability rather than a universal mechanism of cell death, we aim to provide a conceptual framework for identifying clinically actionable strategies to overcome apoptotic resistance in GBM.
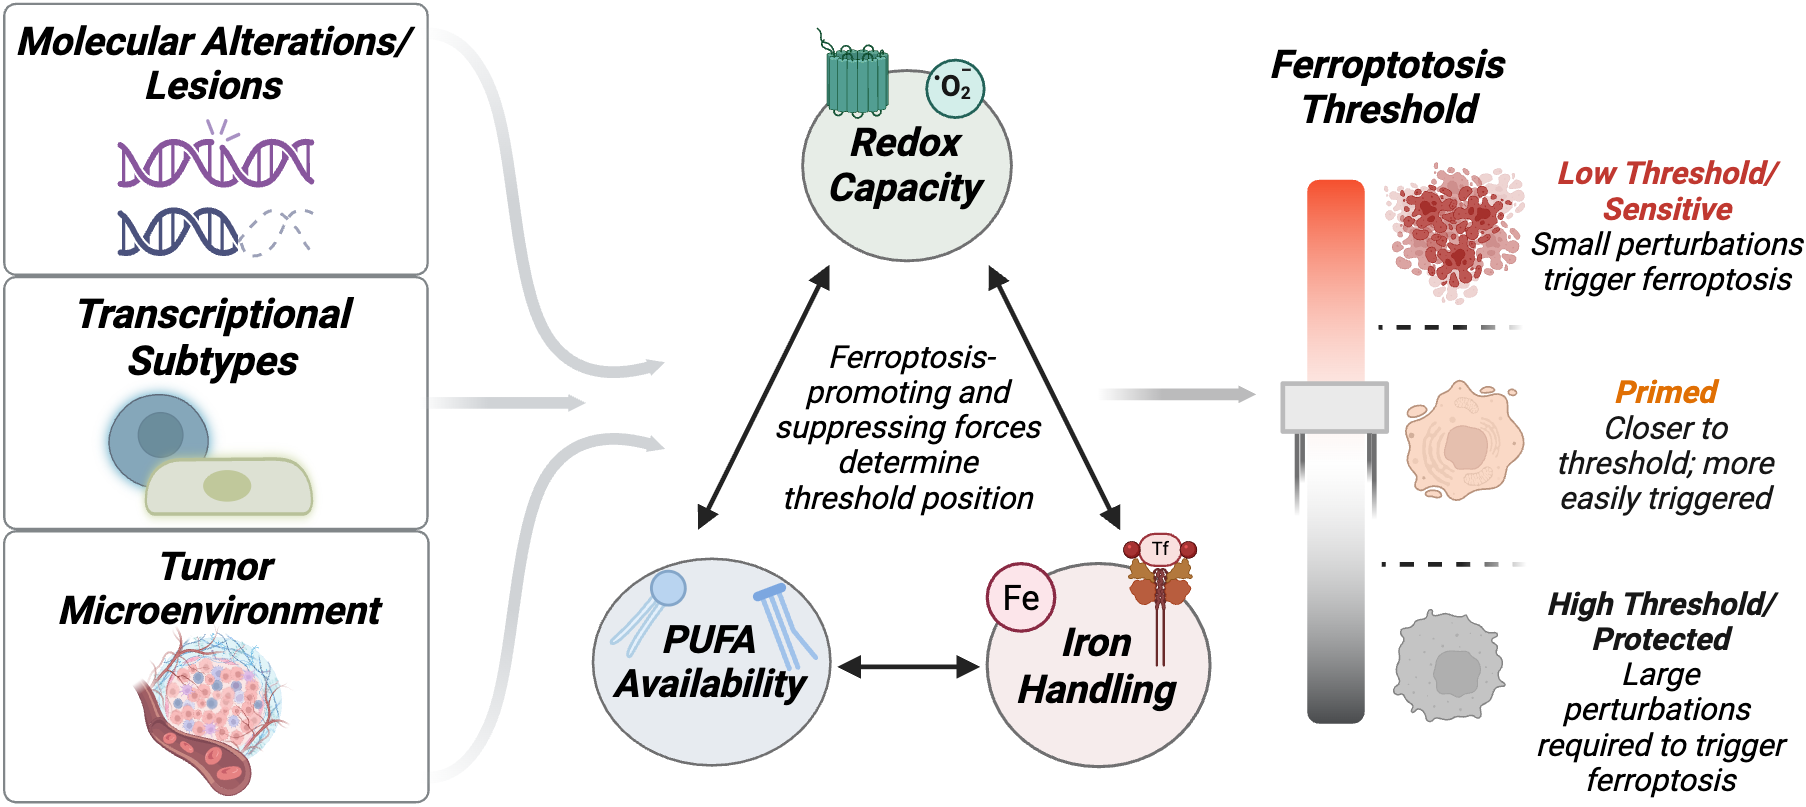
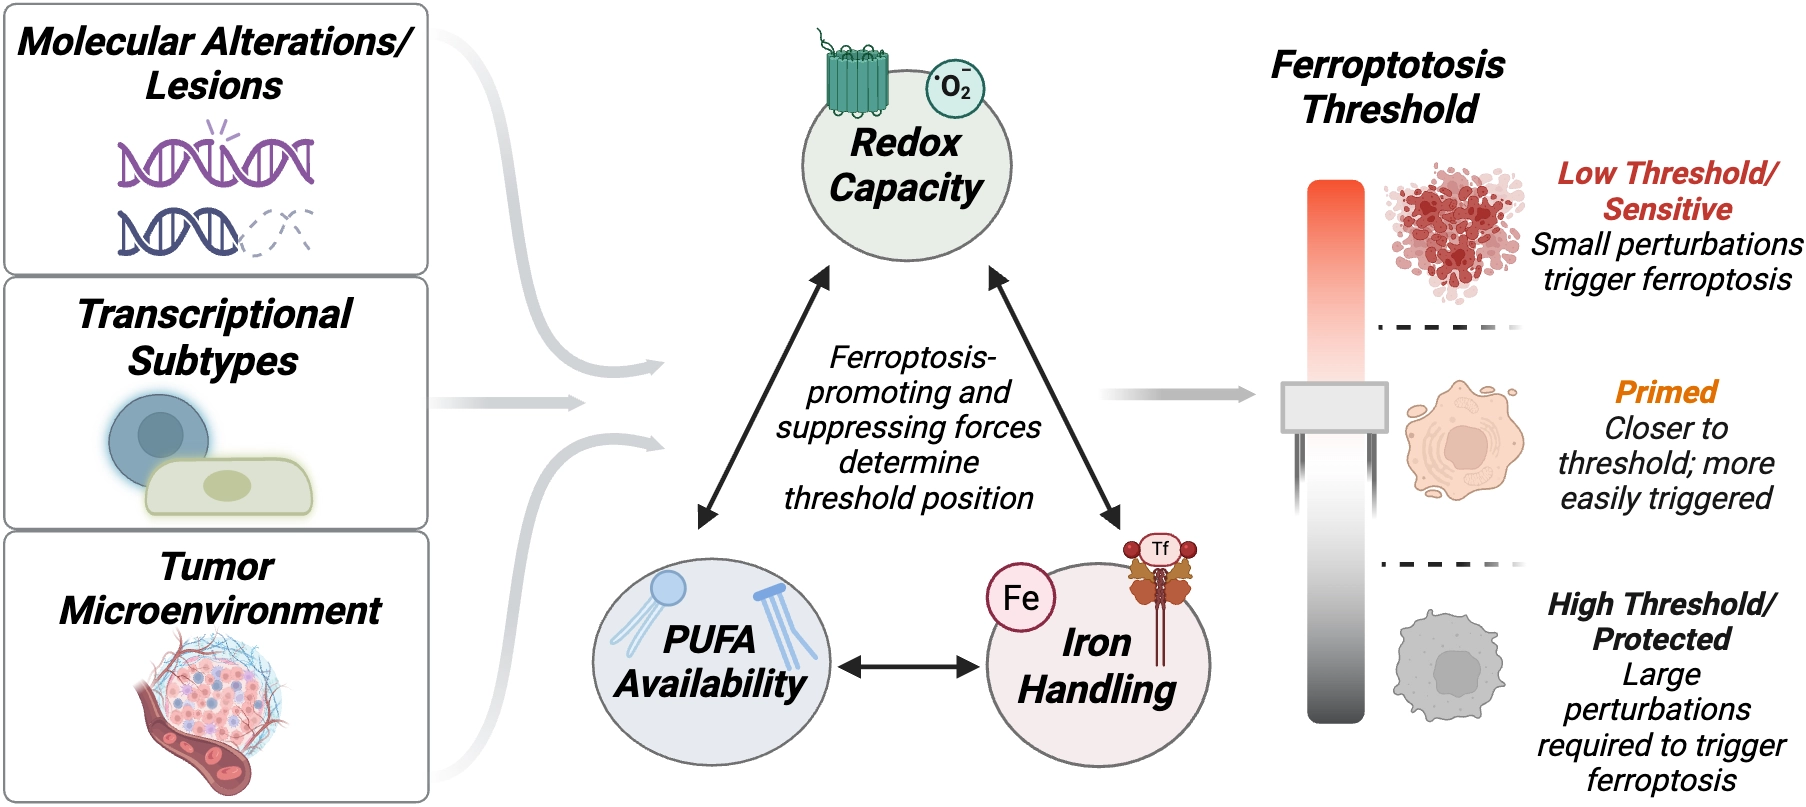
Figure 1. Determinants of the ferroptosis threshold in Glioblastoma. Conceptual model illustrating how upstream tumor features converge on three interdependent axes, Oxidizable Lipid (PUFA) Availability, Redox Capacity, and Iron Handling, to set a cell’s ferroptosis threshold. Molecular alterations/lesions, transcriptional subtypes, and the tumor microenvironment (left) feed into this triad, where opposing ferroptosis-promoting and -suppressing forces dynamically determine threshold position. The net output (right) places tumor cells along a continuum of ferroptotic susceptibility: a low threshold/sensitive state, in which minor perturbations are sufficient to trigger ferroptosis; a primed intermediate state, positioned closer to the threshold and more readily triggered; and a high threshold/protected state, requiring large perturbations to induce ferroptosis. Created in BioRender. Salinas, J. (2026) https://BioRender.com/vea0ke4. PUFA: polyunsaturated fatty acid; Tf: transferrin.
2. Intrinsic Determinants of the Ferroptosis Threshold in GBM
First, we will describe the cell autonomous regulators that contribute to ferroptosis in GBM. Across the three axes of the framework proposed in this review, GBM-specific metabolic enzyme expression, genetic alterations, and transcriptional programs collectively determine where a tumor sits relative to the ferroptosis threshold (Figure 2), a point at which pro-ferroptotic pressures (oxidizable lipid abundance, labile iron pool) exceed the protective capacity (antioxidant buffering, lipid sequestration), thus sensitizing cells to ferroptosis-induced cell death. Critically, these determinants are not uniformly distributed: they vary between GBM molecular subtypes, between individual tumors, and between cell populations within a single tumor. Understanding this intrinsic heterogeneity may help identify patients who are most likely to respond to ferroptosis-inducing therapy and predict resistance mechanisms that could be co-targeted.
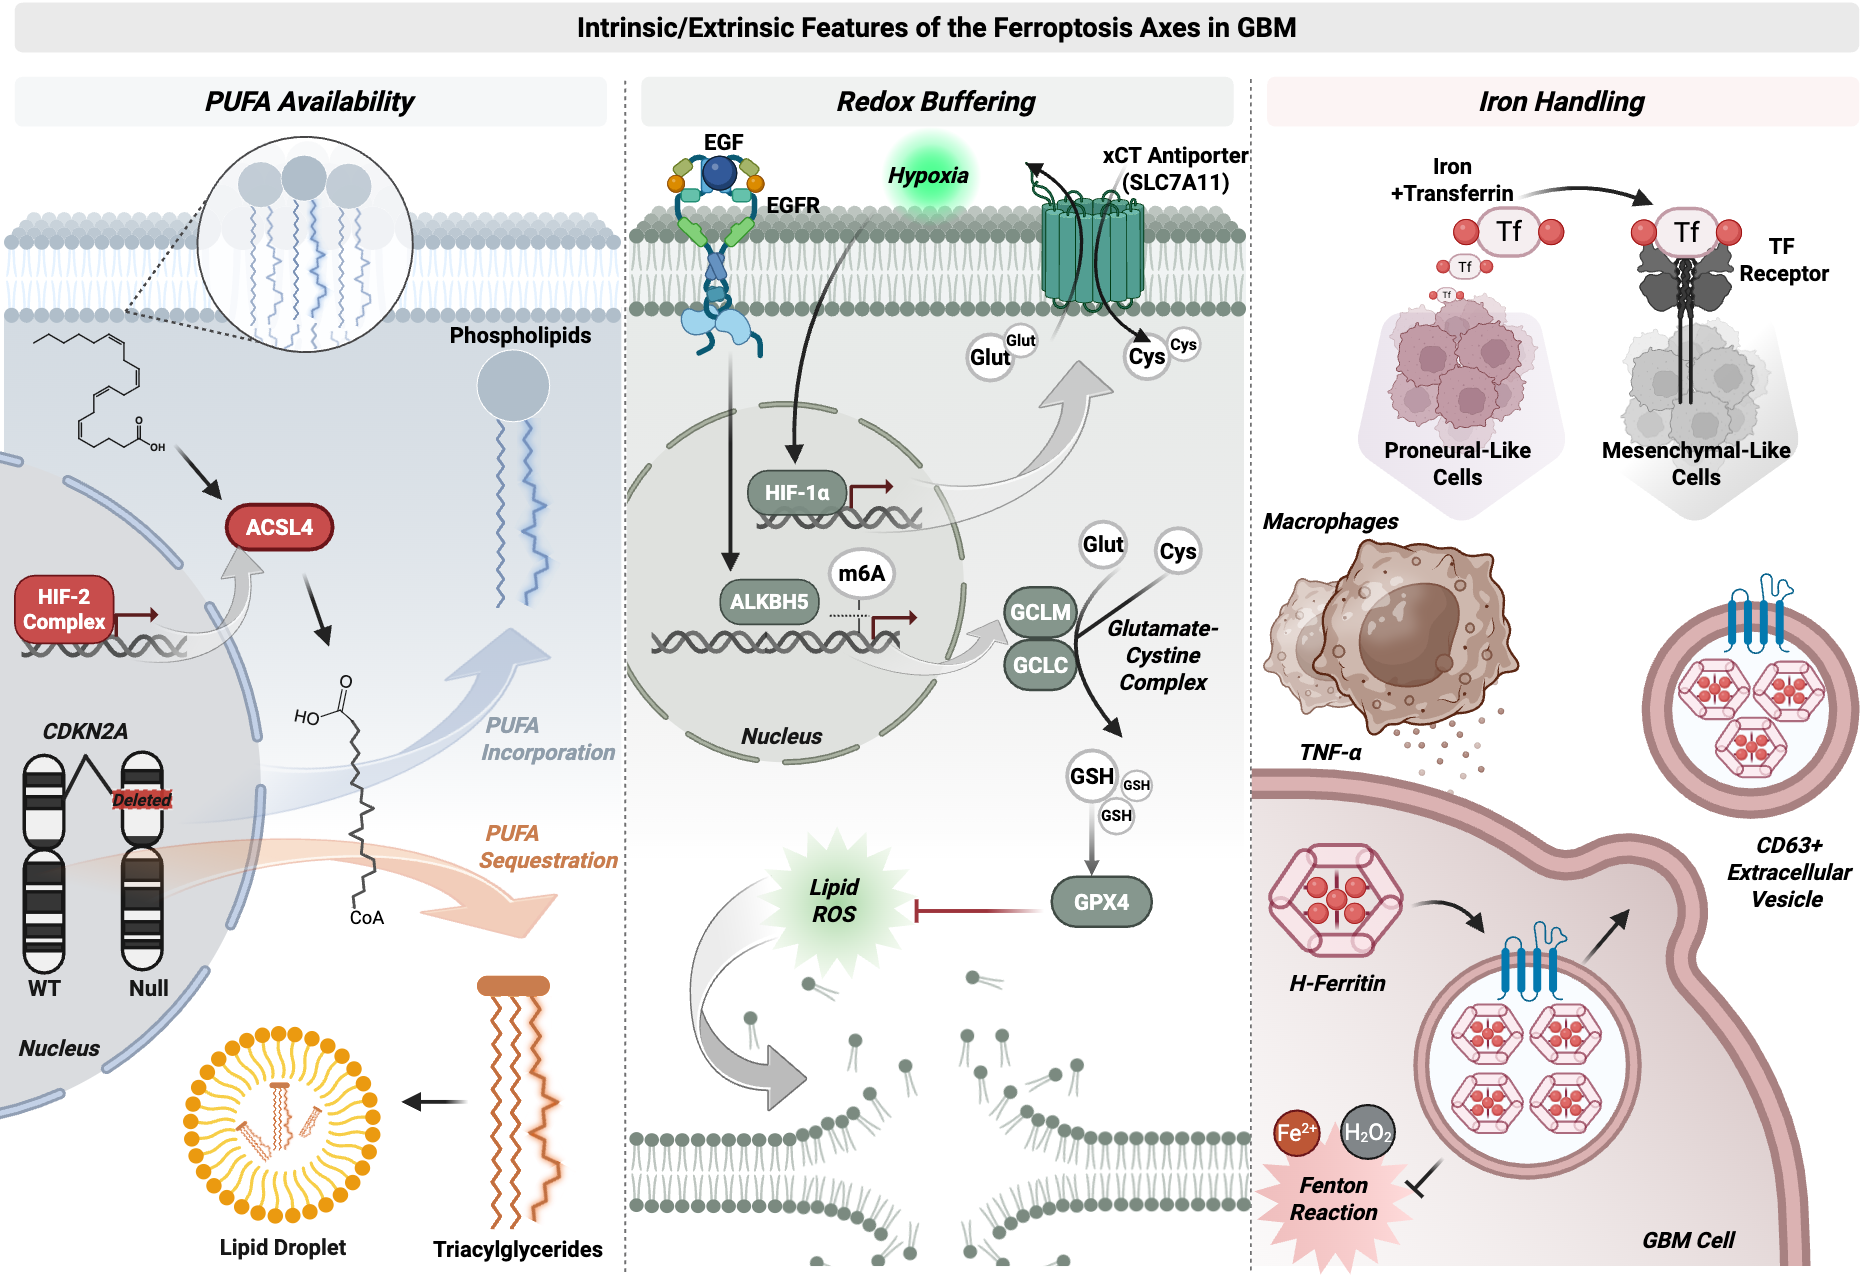
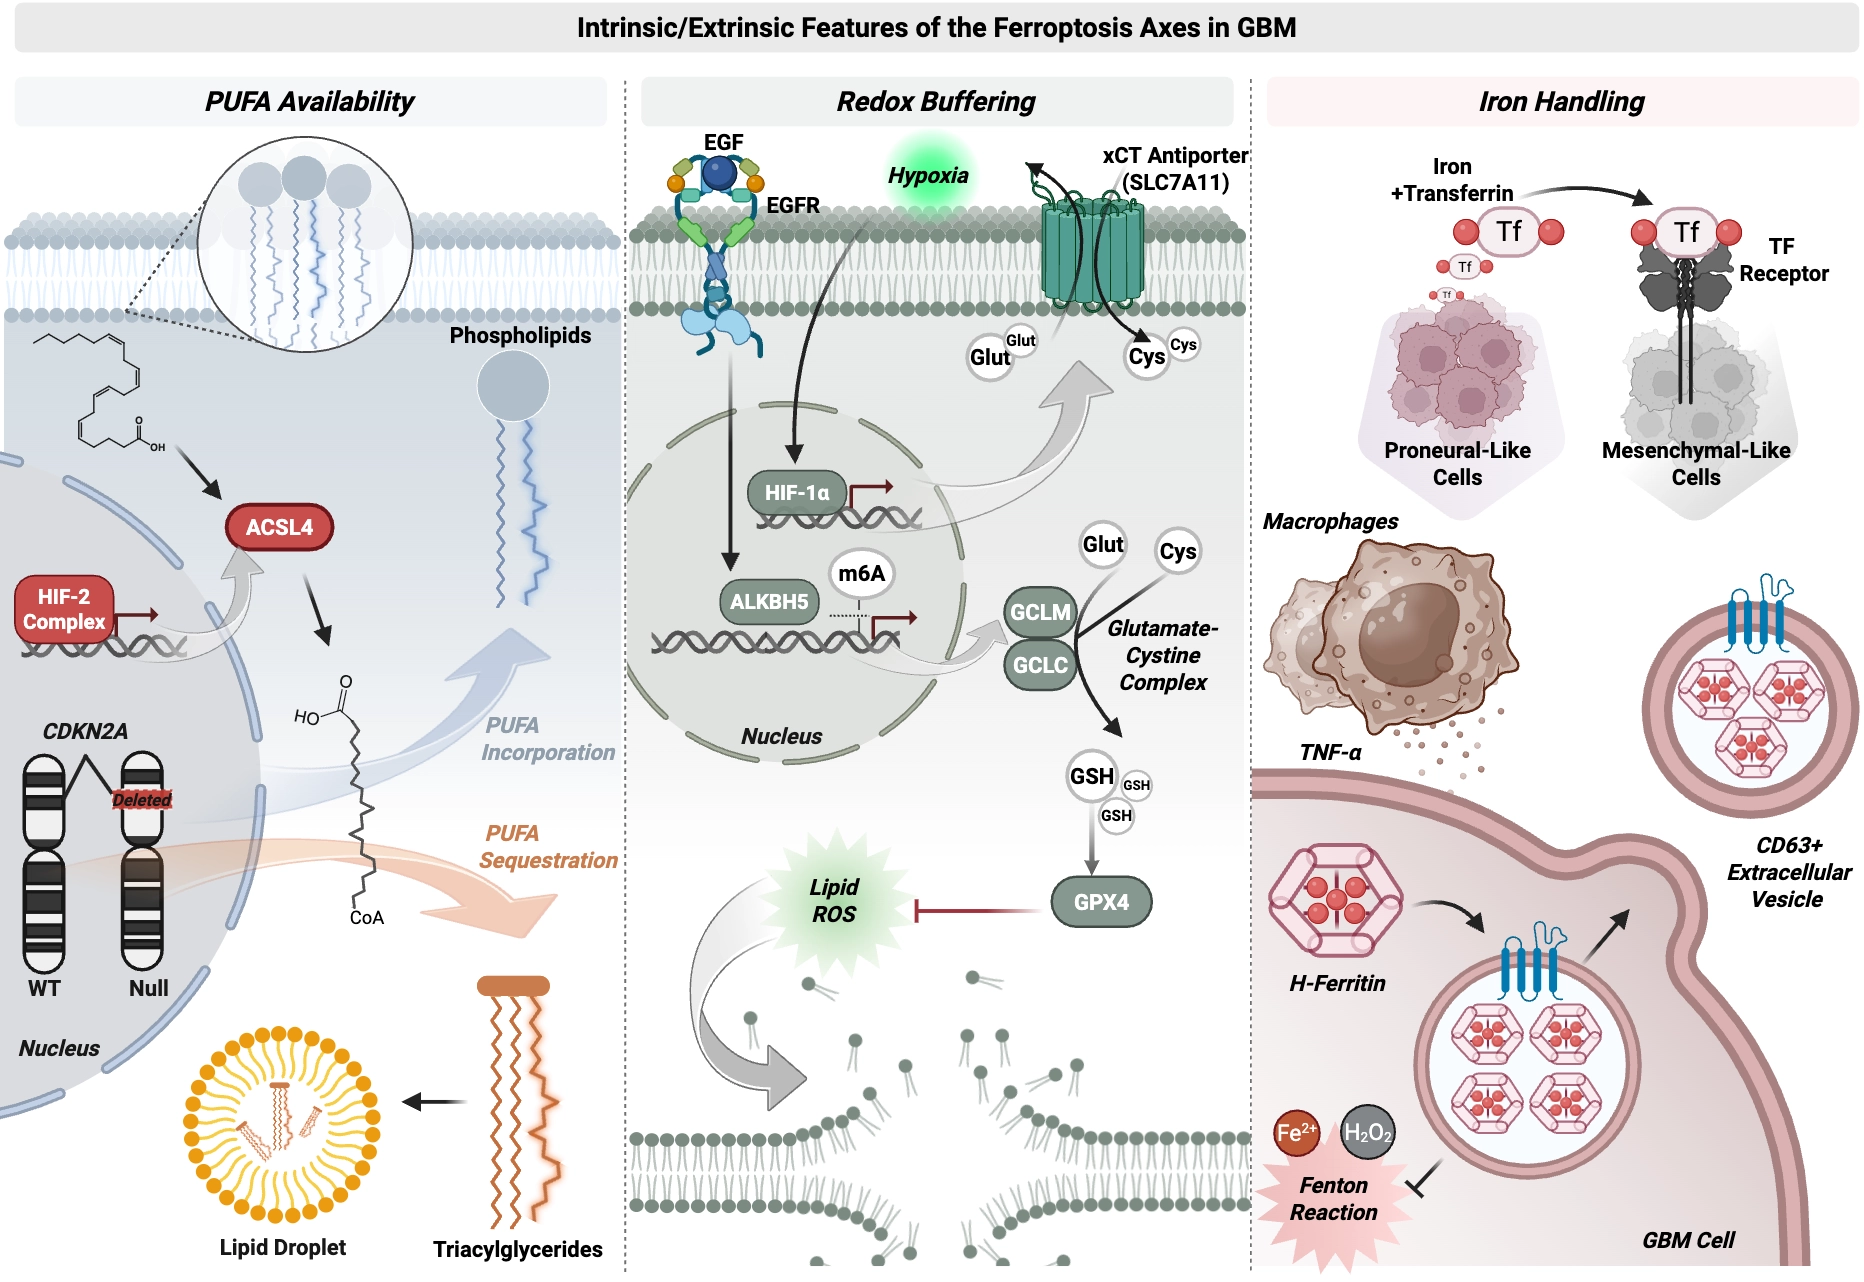
Figure 2. Intrinsic and extrinsic regulators of ferroptosis susceptibility in Glioblastoma. Schematic overview of the major regulatory axes that collectively establish the ferroptosis threshold in GBM, organized by oxidizable lipid availability, redox buffering, and iron handling. Lipid availability (left): GBM cells regulate ferroptotic susceptibility through control of PUFA metabolism and membrane lipid composition. ACSL4 promotes PUFA-CoA activation and incorporation into phospholipids, enhancing substrates for lipid peroxidation, whereas alternative sequestration of PUFAs into TAGs within lipid droplets limits ferroptotic propagation. This lipid partitioning program is influenced by oncogenic alterations, including CDKN2A loss and HIF-2–dependent transcriptional regulation. Redox buffering (center): GBM cells maintain protection from ferroptosis through coordinated antioxidant systems that limit lipid ROS accumulation. Hypoxia-responsive pathways regulate redox adaptation, including glutamate-cystine transport, GSH synthesis, and GPX4-mediated detoxification of lipid peroxides. Iron handling (right): Iron availability represents a critical determinant of ferroptotic sensitivity, with GBM cell states exhibiting distinct mechanisms of iron uptake, storage, and utilization. Tf-mediated iron acquisition, ferritin-based sequestration, and regulation of the labile iron pool influence iron-dependent lipid peroxidation, which can be modulated by the TIME or cellular subtype. Together, these interconnected axes establish the ferroptotic threshold of GBM cells and represent potential therapeutic vulnerabilities for selectively inducing ferroptotic cell death. Created in BioRender. Salinas, J. (2026) https://BioRender.com/1corsnp. GBM: glioblastoma; PUFA: polyunsaturated fatty acid; HIF: hypoxia inducible factor; ACSL4: acyl-CoA synthetase long-chain family member 4; CDKN2A: cyclin dependent kinase inhibitor 2A; EGFR: epidermal growth factor receptor; m6A: N6-methyladenosine; GSH: glutathione; ROS: reactive oxygen species; GPX4: glutathione peroxidase 4; Tf: transferrin; TAGs: triacylglycerides; TIME: tumor immune microenvironment.
2.1 Lipid availability, redox buffering, and iron handling
A key requirement for ferroptosis is the presence of oxidizable phospholipid substrates[16,17,28]. Consequently, GBM susceptibility is influenced by metabolic programs that determine the availability or generation of oxidizable fatty acids that are incorporated into phospholipid membranes or sequestered in neutral lipids[29,30]. Acyl-CoA synthetase long-chain family member 4 (ACSL4) activates the polyunsaturated fatty acids arachidonic acid (AA, 20:4) and adrenic acid (AdA, 22:4) to CoA thioesters[31], which are then esterified into membrane phospholipids, thus generating oxidizable substrates for lipid peroxidation[17,19,32,33]. ACSL4 is required for ferroptosis when glutathione peroxidase 4 (GPX4) is inactivated, at least in cultured cells[34]. Likewise, GBMs may exhibit resistance to ferroptosis due to reduced ACSL4 expression across a panel of human glioma tissues and cells[26]. This ferroptosis resistance correlated with elevated GPX4 expression and reduced 12/15-hydroxyeicosatetraenoic acid (HETE) lipid peroxide levels. Overexpression of ACSL4 decreased expression of GPX4, increased 12/15-HETE lipid peroxide levels, and decreased cell viability[26]. These findings position ACSL4 as a key determinant of whether GBM cells accumulate polyunsaturated fatty acid (PUFA)-containing phospholipid substrates.
In contrast to ACSL4-mediated membrane PUFA loading, GBM cells can actively buffer ferroptosis susceptibility by sequestering oxidizable lipids away from plasma membrane phospholipids in lipid droplets[12,35]. Lipid droplets (LDs) serve as a protective store for PUFAs that have been sequestered into neutral triacylglycerides (TAG) and are physically compartmentalized away from phospholipid incorporation that may occur via ACSL4, suppressing ferroptosis[35-37]. Lipid droplet accumulation is a key feature of GBM[38-40]. Under periods of energy deprivation (low glucose conditions), GBM cells deplete TAG-containing lipid droplets to release fatty acids for mitochondrial oxidation. Furthermore, inhibiting fatty acid oxidation or autophagy leads to increased accumulation of TAG-containing lipid droplets[38,40]. Thus, GBM cells do not simply lack the ability to execute ferroptosis, but instead these tumors have a lipidome that reflects the sequestration of lipids away from peroxidation-susceptible membrane components and towards protective lipid droplets.
Another mechanism of protection that GBM tumors exhibit against ferroptosis is reduced mitochondrial lipid peroxidation. Unbiased RNAi screening in GBM patient-derived orthotopic xenografts (PDOXs) identified medium-chain acyl-CoA dehydrogenase (MCAD) as important for GBM tumor growth[36], with immunohistochemistry confirming heightened expression of MCAD in GBM tumors compared to normal brain[41]. MCAD catalyzes the first step of medium chain FA (MCFA) oxidation. Depletion of MCAD induced lipid peroxidation and oxidative stress via accumulation of unmetabolized MCFAs in the mitochondria in both in vitro and in vivo systems. This led to structural damage within the mitochondria, and ultimately cell death that was rescued with the ferroptosis-specific small molecule inhibitor ferrostatin-1, implicating MCFA oxidation as a potential ferroptosis-buffering strategy in GBM[41]. These findings suggest that mitochondrial fatty acid oxidation may act as a metabolic sink to prevent the accumulation of peroxidation prone lipid species in GBM.
While lipid availability determines the availability of ferroptosis substrates, ferroptotic execution additionally depends on whether antioxidant systems can effectively neutralize the accumulation of oxidizable lipid species. Outside of lipid-level defenses (e.g., decreased oxidizable PUFAs in the phospholipid (PL) membrane, increased TAG-containing LDs), tumors also possess multiple enzymatic antioxidant systems that are relevant to GBM biology. The cystine/glutamate antiporter xCT (SLC7A11) exchanges extracellular cystine for intracellular glutamate at the plasma membrane[42,43]. Inside the cell, cystine is reduced to cysteine and used to synthesize glutathione (GSH), a critical antioxidant[43]. GBM tumors exhibit increased SLC7A11 expression, thus enabling resistance to oxidative stress[44,45]. In GBM patients, increased SLC7A11 expression correlated with poorer prognosis, with high-SLC7A11 patients having both shorter progression-free and overall survival[45]. Wild-type p53 negatively regulates SLC7A11 expression, with stabilization of p53 leading to decreased ferroptosis sensitivity in response to cystine deprivation[46]. This was found to be associated with slower depletion of intracellular glutathione and reduced accumulation of reactive oxygen species (ROS)[46]. These observations suggest that GBM cells may protect themselves against ferroptosis through cystine-dependent glutathione buffering.
In addition to cytosolic glutathione buffering, GBM cells can also engage mitochondrial antioxidant systems to influence ferroptosis susceptibility. Dihydroorotate dehydrogenase (DHODH), a mitochondrial enzyme involved in de novo pyrimidine synthesis, regulates mitochondrial lipid peroxidation[47-50]. DHODH reduces ubiquinone to ubiquinol within the inner mitochondrial membrane and may limit mitochondrial lipid peroxidation and ferroptosis under certain conditions[51,52]. In GBM, depletion of proline-rich protein 11 (PRR11) sensitized recurrent tumor cells to temozolomide (TMZ) by disrupting PRR11-mediated stabilization of DHODH, increasing lipid peroxidation and ferroptotic cell death[53]. These findings suggest that DHODH may contribute to ferroptosis resistance in at least a subset of GBMs and may be particularly relevant in recurrent or therapy-resistant disease.
Iron handling represents a third major determinant of the ferroptosis threshold in GBM through regulating catalytic iron required for lipid peroxidation. Ferritin-mediated sequestration serves as a protective mechanism, with disruption of ferritin regulation increasing iron-dependent oxidative stress. In GBM models, tripartite motif-containing protein 7 (TRIM7) regulates nuclear receptor coactivator 4 (NCOA4)-mediated ferritinophagy, with loss of TRIM7 leading to enhanced ferritin degradation, increased intracellular iron availability, and increased lipid peroxidation[54]. These factors sensitized GBM cells to ferroptosis-mediated cell death[54]. Similarly, alterations in ferritin heavy chain 1 (FTH1)-mediated iron sequestration increase ferroptosis sensitivity[55]. Mechanistically, disruption of FTH1 regulation was associated with increased iron-dependent oxidative stress, elevated lipid peroxidation, and impaired tumor cell survival under ferroptotic pressure[55].
Viewed through the lens of the three-axis framework, these findings reveal that GBM suppresses ferroptosis through coordinated regulation of both lipid availability and redox buffering. Oxidizable PUFAs are diverted away from peroxidation-susceptible membrane phospholipids and into protective storage or metabolic clearance pathways, while glutathione-dependent antioxidant systems, together with other mitochondrial redox pathways, help neutralize lipid peroxide accumulation. Together, these mechanisms maintain GBM cells below the ferroptosis threshold and constitute major determinants of intrinsic ferroptosis resistance.
2.2 Gene regulatory programs shaping ferroptosis sensitivity in GBM
In GBM, ferroptosis sensitivity is not exclusively determined by a single enzyme. Coordinated transcriptional and post-transcriptional programs can also regulate the antioxidant systems that define the redox buffering axis, thereby influencing how close tumor cells are to the ferroptosis threshold. These regulatory networks frequently contribute to resistance against both standard therapies and ferroptosis-inducing agents.
Among the transcriptional regulators of ferroptosis, the NFE2-like bZIP transcription factor 2 (NFE2L2, NRF2) pathway represents a central mechanism by which GBM coordinates redox defense, with NRF2 acting as a key regulator in redox-dependent events[56-58]. Under oxidative stress, NRF2 uncouples from Kelch-like ECH-associated protein 1 (KEAP1) and translocates to the nucleus, where it induces the transcription of genes containing antioxidant response elements (AREs)[57]. Compared to non-cancerous brain tissue, GBM tissue exhibited elevated NRF2 levels, which correlated with poorer clinical outcomes and overall reduced survival[59]. Genetic activation of NRF2 or loss of KEAP1 increased SLC7A11 expression and promoted glioma cell proliferation, whereas NRF2 suppression sensitized glioma cells to ferroptosis through increased ROS accumulation[59]. SRC proto-oncogene, non-receptor tyrosine kinase (SRC) signaling promoted NRF2 stabilization by activating the mTORC1-p62-KEAP1 (mechanistic target of rapamycin complex 1-p62-KEAP1) axis, leading to transcriptional upregulation of ferroptosis-defense genes including SLC7A11 and GPX4[27]. SRC inhibition with dasatinib, a multi-tyrosine kinase inhibitor, released the sequestration of KEAP1 and sensitized GBM cells to ionizing radiation (IR)-induced ferroptosis[27]. Collectively, these findings suggest that NRF2 functions as an important regulator of ferroptosis resistance in GBM by reinforcing antioxidant capacity and cystine-dependent redox buffering, although the specific contribution of individual downstream ferroptosis regulators remains context-dependent.
Beyond transcriptional regulation, GBM cells employ post-transcriptional mechanisms that influence ferroptosis-associated pathways, including regulation of RNA stability, protein expression, and antioxidant capacity. These mechanisms can alter the ability of tumor cells to maintain redox homeostasis and survive oxidative stress. For example, Fragile-X mental retardation autosomal 1 (FXR1), an RNA-binding protein, bound and stabilized GPX4 mRNA in TMZ-resistant glioma cells[60]. Increased FXR1 expression was associated with TMZ resistance, whereas FXR1 silencing reduced GPX4 expression and sensitized glioma cells to TMZ treatment, accompanied by increased ferroptotic vulnerability[60]. These findings suggest that post-transcriptional regulation of antioxidant defense pathways may contribute to ferroptosis resistance in therapy-resistant GBM states. NF-κB activating protein (NKAP), another RNA binding protein, was also found to modulate ferroptosis sensitivity in GBM by stabilizing SLC7A11 mRNA[61]. NKAP knockdown sensitized cells to ferroptosis both in vitro and in vivo, while overexpression of NKAP promoted resistance to ferroptosis through positive regulation of SLC7A11. This regulation was weakened in a post-transcriptional manner, with NKAP regulating SLC7A11 mRNA splicing through N6-methyladenosine (m6A) modifications[61].
Solute carrier family 10 member 3 (SLC10A3) is upregulated in low-grade gliomas (LGG) and GBM patient tissue and is correlated with poorer patient prognosis[62]. SLC10A3 regulated glioma growth and ferroptosis sensitivity via signal transducer and activator of transcription 3 (STAT3) phosphorylation and downstream GPX4 suppression. Silencing of SLC10A3 induced ferroptosis in GBM both in vitro and in vivo[62]. Finally, selenoprotein P (SeP), a selenium-containing protein, was associated with ferroptosis sensitivity through suppressing GPX4 in GBM[63]. Knockdown of SeP in cultured GBM cells decreased GPX4 protein levels and increased RSL3-induced cell death. This cell death was rescued by supplementing cells with selenite, suggesting that SeP regulates GPX4 by acting as a selenium storage system in GBM[63]. Together, these transcriptional and post-transcriptional programs constitute an important redox buffering axis in GBM. Whether through NRF2-driven transcriptional amplification of SLC7A11 and GPX4, SRC-mediated KEAP1 sequestration, GPX4 mRNA stabilization by FXR1, or selenoprotein P-dependent selenium supply to GPX enzymes, the net effect is the same: GBM cells maintain a constitutively elevated antioxidant capacity that raises the lipid peroxide accumulation required to trigger ferroptosis.
2.3 Genetic alterations rewire the ferroptosis axes
Canonical GBM driver alterations promote proliferation and survival and at the same time establish baseline ferroptosis susceptibility by regulating lipid metabolism, antioxidant capacity, and iron utilization. Among recurrent genetic alterations in primary GBM, cyclin-dependent kinase inhibitor 2A (CDKN2A) deletion has emerged as an important determinant of ferroptosis sensitivity[12]. Through integrated lipidomic, transcriptomic, and genomic profiling of more than 150 patient-derived GBM tumors, CDKN2A deletion was associated with redistribution of oxidizable PUFAs from protective TAG-containing lipid droplets into peroxidation-susceptible membrane phospholipids. As a consequence, CDKN2A-null GBMs exhibited elevated basal lipid peroxidation and increased ferroptosis sensitivity, whereas CDKN2A wild-type tumors remained comparatively resistant due to PUFA-TAG buffering. The CDKN2A locus encodes several different products, including p16 and p14. Re-expression of p16, but not p14, restored the CDKN2A wild-type lipid phenotype and ferroptosis resistance, revealing a link between a canonical cell-cycle regulator and the ferroptotic lipid landscape[12]. Together, these findings identify CDKN2A loss as both a mechanistic determinant and a potential biomarker of ferroptosis sensitivity, demonstrating that this common tumor suppressor alteration positions GBM cells closer to the ferroptosis threshold through lipidome remodeling.
In contrast to CDKN2A-mediated lipid remodeling, other GBM driver alterations may regulate ferroptosis by modulating redox buffering pathways. For example, epidermal growth factor receptor (EGFR) amplification, present in ~ 50% of GBM tumors[64], reduces ferroptosis sensitivity by enhancing glutathione synthesis and boosting redox buffering pathways[65]. EGFR signaling repressed m6A mRNA levels in GBM cells grown in culture, whereas genetic and pharmacologic suppression of EGFR signaling elevated m6A levels. Mechanistically, EGFR promoted ferroptosis resistance by increasing the nuclear localization of the RNA demethylase ALKBH5. Nuclear ALKBH5 reduced m6A levels and post-transcriptionally regulated GCLM, a rate-limiting enzyme in glutathione synthesis. Depletion of ALKBH5 and GCLM led to ferroptosis, establishing a link between EGFR signaling, m6A demethylation, and ferroptosis[65].
Phosphatase and tensin homolog deleted from chromosome ten (PTEN) loss occurs in ~ 36% of primary GBM tumors[66]. This mutation constitutively activates the PI3K/AKT/mTOR pathway[67]. There is no evidence linking PTEN status to ferroptosis susceptibility in GBM. However, in other tumors, PTEN loss promotes ferroptosis resistance by reinforcing redox buffering pathways. In non-GBM models, PTEN deletion increased SLC7A11 expression and reduced ferroptosis sensitivity, an effect reversed by AKT inhibition through suppression of NRF2 and SLC7A11 expression[68]. Consistent with a role for PI3K/AKT signaling in ferroptosis regulation, inhibition of the AKT/mTOR pathway in GBM using the sterol regulatory element-binding protein (SREBP) inhibitor Fatostatin induced ferroptosis by suppressing GPX4 synthesis[69]. Together, these findings suggest that PTEN loss may influence ferroptosis susceptibility, at least in part, through AKT-NRF2-SLC7A11-mediated regulation of antioxidant defenses.
Gain of function mutations in IDH produce the oncometabolite 2-hydroxyglutarate (2-HG)[70] and reshape multiple processes relevant to ferroptosis, including lipid metabolism, NADPH utilization, and oxidative stress responses. IDH mutations are present in approximately 80% of grade II/III gliomas, as well as a subset of secondary GBMs[71], and have context-dependent effects on ferroptosis susceptibility that remain incompletely resolved.
Mutant IDH may promote ferroptosis sensitivity in some cancers. Consumption of NADPH by the mutant IDH protein compromises de novo lipogenesis, resulting in increased dependence on exogenous lipids for growth[72]. Consistent with this concept, HT-1080 fibrosarcoma cells, a commonly used ferroptosis model harboring an endogenous IDH1 mutation, had reduced ferroptosis sensitivity following deletion of mutant IDH1 and re-sensitization following re-expression of mutant (but not wild-type) IDH1[73]. Furthermore, 2-HG itself appeared to mediate this phenotype, as pharmacologic inhibition of mutant IDH1 or overexpression of D-2HG dehydrogenase reduced ferroptosis sensitivity[73]. These findings suggest that mutant IDH can create a metabolic state permissive for ferroptosis at least in some cellular contexts.
However, this relationship is not universal, and in other settings the metabolic and signaling consequences of mutant IDH can instead suppress ferroptosis. Gene expression profiling of LGG harboring the IDH mutation identified elevated PI3K/AKT activation as a critical node in these tumors[74]. AKT activation suppressed NRF2-dependent oxidative stress responses and reduced lipid peroxidation, whereas AKT inhibition enhanced TMZ-induced ferroptosis[74]. Similarly, IDH-mutant gliomas were resistant to oncolytic herpes simplex virus (oHSV)-induced ferroptosis because they failed to engage reductive carboxylation and lipid biosynthetic programs observed in IDH-wildtype tumors[75]. Pharmacologic inhibition of mutant IDH restored this metabolic flexibility and enhanced oHSV efficacy[75]. Collectively, these findings suggest that IDH mutations do not exert a uniform effect on ferroptosis susceptibility. Rather, mutant IDH appears to influence ferroptotic vulnerability through complex effects on lipid metabolism, redox homeostasis, and metabolic substrate utilization, with the ultimate outcome dependent on cellular and therapeutic context.
Together, these findings suggest that common GBM driver alterations establish baseline ferroptosis susceptibility by reshaping lipid metabolism, redox buffering, and metabolic state. Consequently, ferroptosis sensitivity may emerge not as a universal property of glioma, but as a genetically encoded vulnerability that varies across molecular subtypes and therapeutic contexts. Rather than inducing ferroptosis indiscriminately, greater opportunity may lie in identifying tumors already positioned near the ferroptosis threshold and selectively pushing them beyond it.
2.4 Cell state identity as a determinant of ferroptosis sensitivity in glioma
Beyond genetic lesions, ferroptosis susceptibility may also relate to transcriptional cell state identity. GBM transcriptional subtypes and cellular states are associated with distinct metabolic programs, antioxidant capacity, and iron utilization, suggesting that ferroptosis vulnerability may shift as tumors transition between developmental and therapy-induced states. Initial work highlighted three main subtypes in GBM: proneural (PN), classical (CL), and mesenchymal (MES)[7]. PN gliomas express neural development genes, CL gliomas have high levels of EGFR amplifications, EGFRvIII mutations, and deletions of CDKN2A, and MES gliomas are defined by high expression of immune-associated genes and immune cell infiltration[7]. Further single-cell RNA sequencing (scRNA-seq) has uncovered more nuanced cellular states at the intra-tumoral level, with seminal work defining four primary, highly plastic transcriptional states mirroring different neural developmental stages[13,14,76,77]. These states include the neural progenitor-like (NPC-like) state, the oligodendrocyte progenitor-like (OPC-like) state, the astrocyte-like (AC-like) state, and the MES-like state, with newer refinements expanding on this work[13-15,78]. Collectively, these subtypes and states contribute to tumor plasticity, treatment resistance, and recurrence.
Molecular factors are important for maintaining tumor heterogeneity between the PN and MES subtypes of GBM. For example, PN glioma cells secreted dopamine (DA) and transferrin (TF), thus inducing proliferation of MES cells but sensitizing them to ferroptosis[79]. In cell culture, PN glioma-derived TF stimulated MES glioma proliferation in an iron-dependent manner. Furthermore, DA acted in an autocrine manner by inducing PN-glioma growth while inducing TF-receptor 1 expression in MES glioma cells to increase iron uptake, thus enhancing susceptibility to ferroptosis[79]. In an independent study, PN and MES GBM cell lines were exposed to ferric ammonium citrate (FAC)-mediated iron overload and erastin[24]. The PN cell line increased metabolic turnover, while the MES cell line did not show any significant changes. The MES cell line had higher basal levels of glutathione and could upregulate GPX4 levels after FAC treatment relative to the PN cell line[24]. While these observations suggest that PN, not MES, GBM may be more sensitive to ferroptosis, it is important to note that only two cell lines were examined in the absence of inter-tumoral crosstalk. These apparently conflicting findings may reflect differences in experimental systems, iron availability, and the relative engagement of lipid availability, redox buffering, and iron handling programs rather than a fixed ferroptosis phenotype associated with any single transcriptional subtype.
Recent work has expanded on the link between transcriptional identity and ferroptosis vulnerability. In genetically engineered mouse models of glioma, patient-derived cell lines, and ex vivo slice cultures generated from patient-derived GBM samples, Notch activation upon tumor initiation induced a quiescent AC-like glioma phenotype[80]. This phenotype was accompanied by alterations in mitochondrial function, increasing ROS generation, increased lipid peroxidation, and ultimately sensitivity to GPX4-inhibition-mediated ferroptosis[80]. The association between AC-like gliomas and ferroptosis vulnerability has also been found in diffuse midline gliomas, a pediatric brain tumor with a median survival of 9-12 months from diagnosis[81]. Gene set enrichment analysis revealed that AC-like diffuse glioma cells were enriched for genes associated with the epithelial-mesenchymal transition (EMT) and immune cell signaling. Treatment of these cells with RSL3 induced lipid peroxidation and cell death, which was rescued by ferrostatin-1[81]. Critically, the transcriptional subtype data reveal that the three axes of ferroptosis sensitivity are not independent features of individual genetic alterations but are co-regulated as integrated phenotypic programs. The MES state simultaneously upregulates redox buffering (NRF2/GPX4/GSH) and lipid storage (lipid droplet formation), while the PN and AC-like states exhibit comparatively lower antioxidant tone and higher membrane lipid peroxidation susceptibility[80,81]. This suggests that the ferroptosis threshold is not simply the sum of individual molecular alterations but an emergent property of larger transcriptional states and profiles.
3. Extrinsic Signals Dynamically Shift the Three Ferroptosis Axes in GBM
Although intrinsic programs establish baseline ferroptosis susceptibility, GBM cells exist within a highly dynamic tumor microenvironment (TME) that continuously reshapes lipid metabolism, antioxidant defense, and iron availability (Figure 2). Each of the extrinsic signals reviewed in this section may dynamically recalibrate one or more of the three primary axes. Hypoxia and HIF signaling mainly modulate the redox buffering axis through transcriptional regulation of SLC7A11. The immune microenvironment acts on all three axes simultaneously: tumor associated macrophages (TAMs) sequester iron to suppress the iron handling axis, IFN-γ from CD8+ T cells suppresses SLC7A11 to reduce redox buffering, and ferroptotic damage associated molecular patterns (DAMPs) reshape immune cell composition in ways that feed back onto lipid oxidation. Standard-of-care therapies have also been proposed to engage this framework: TMZ has been proposed to expand labile iron pools (iron handling) while depleting GSH (redox buffering), and radiation amplifies ROS-driven lipid peroxidation (lipid availability). Recognizing which axis each extrinsic input targets is essential for designing combination approaches that achieve convergent, rather than redundant, pressure on the ferroptosis threshold.
3.1 Hypoxia and hypoxia inducible factor (HIF)
Hypoxia is a common feature of GBM tumors and has been observed in the necrotic tumor core and pseudopalisading regions[82-84]. The relationship between hypoxia and ferroptosis is context-dependent, showing opposite effects depending on the degree and duration of HIF activation.
Chronic hypoxia suppresses ferroptosis via the PI3K/AKT/HIF-1α axis, with HIF directly binding to the SLC7A11 promoter and upregulating SLC7A11 expression, thus increasing cystine import and glutathione biosynthesis[85]. This mechanism was validated in GBM cell lines and orthotopic xenograft models, where hypoxia significantly decreased the potency of erastin and sulfasalazine, an antirheumatic drug that inhibits SLC7A11 function. Combined inhibition of HIF and SLC7A11 synergistically increased ferroptosis sensitivity[85], which could be of therapeutic relevance given the hypoxic nature of GBM tumor cores.
Prolyly Hydroxylase (PHD) hydroxylates HIF, targeting it for degredation. Roxadustat is a PHD small-molecule inhibitor, thus stabilizing HIF[86]. Treatment of GBM cells with Roxadustat both in vitro and in vivo induced ferroptosis[87]. Cell death was accompanied by increases in lipid peroxidation and cellular iron but was blocked by ferrostatin-1 and glutathione. Interestingly, cells that were resistant to TMZ-induced apoptosis appeared exceptionally susceptible to Roxadustat-induced ferroptosis, whereas TMZ-sensitive cells were more resistance to Roxadustat[87]. Mechanistically, Roxadustat drove ferroptosis via HIF-2α (but not HIF-1α), which upregulated lipid regulatory genes involved in PUFA-phospholipid generation[87]. These results illustrate how HIF-driven ferroptosis may be isoform dependent, with HIF-1α suppressing ferroptosis via SLC7A11 and HIF-2α promoting ferroptosis sensitivity through modulation of lipid metabolic genes. Taken together, the effect of hypoxia illustrates how a single microenvironmental factor can simultaneously modulate all three ferroptosis axes.
3.2 The tumor-immune microenvironment (TIME)
Ferroptosis susceptibility in GBM is not determined solely by tumor-intrinsic programs but is continuously reshaped by the TIME. Immune cells, inflammatory signaling, and metabolic competition within the TIME dynamically modulate the three major ferroptosis-regulatory axes, lipid metabolism, redox buffering capacity, and iron handling, thereby shifting tumor cells toward or away from the ferroptosis threshold. TAMs comprise roughly 30-50% of tumor cellular mass, with 15% of that mass derived from microglia and 85% from peripheral-derived monocytes recruited by tumor-derived cytokines[88,89]. One mechanism by which the TIME suppresses ferroptosis in GBM is through reinforcement of tumor antioxidant defenses and redox buffering capacity. Ferroptosis-related gene expression in GBM tumor cells positively correlates with M2 macrophage infiltration in scRNA-seq and with The Cancer Genome Atlas (TCGA)/The Chinese Glioma Genome Atlas (CGGA) bulk expression data[90]. Eight ferroptosis-related risk genes are upregulated in high-risk GBM, with three of those genes (Aurora A kinase (AURKA), heat shock factor binding protein 1 (HSBP1), and nicotinamide N-methyltransferase (NNMT)) promoting the polarization of M1 macrophages to M2 macrophages and inhibiting ferroptosis in GBM cells[90]. In another study, programmed cell death (PCD) status was analyzed across a 1,750 patient glioma RNA-sequencing cohort, and ferroptosis was found to be the most enriched PCD process[25]. Furthermore, gene signatures related to ferroptosis were highly correlated with malignant progression, decreased survival, and decreased antitumor immunity. In both in vitro and in vivo experimentation, inhibiting ferroptosis in GBM altered the immunosuppressive phenotype of TAMs and improved the efficacy of anti-programmed cell death protein and ligand (anti-PD1/L1) immunotherapy in a GBM xenograft model[25]. The indoleamine 2,3-dioxygenase 1 (IDO1)-tryptophan axis provides another layer of complexity within the TIME. IDO1 is an enzyme highly expressed in GBM patients that is involved in tryptophan catabolism and has immunosuppressive abilities[91]. In glioma cells, IDO1 overexpression suppresses ferroptosis, reduces ROS, and decreases lipid peroxide generation[92]. Mechanistically, IDO1 promoted expression and nuclear translocation of the aryl hydrocarbon receptor (AhR) at the promoter regions of the FTO alpha-ketoglutarate-dependent dioxygenase (FTO) gene, an m6A eraser enzyme, thus increasing m6A methylation and the stability of SLC7A11 transcripts[92]. This finding potentially connects the tryptophan immunosuppressive axis with ferroptosis evasion in GBM, a finding with translational relevance given the use of IDO1 inhibitors in clinical trials for several cancers[93-95]. Collectively, these findings suggest that immunosuppressive signaling within the TIME may stabilize the redox axis of ferroptosis resistance in GBM by sustaining glutathione metabolism and limiting lipid peroxide accumulation.
The TIME may also directly modulate the iron axis of ferroptosis susceptibility. In addition to redox regulation, TAMs regulate iron homeostasis[96]. TAMs render GBM less susceptible to ferroptosis by altering the iron status of these tumors. Co-culture of TAMs with GL261 GBM cells decreased ferritin heavy chain 1 (FTH1) and total iron levels in the GL261 tumor cells. Mechanistically, TAMs released extracellular vesicles containing iron-rich FTH1, which was mediated by TNF-α secretion from TAMs[96]. This suggests that the TIME may actively regulate whether tumor cells accumulate sufficient labile iron to sensitize them to ferroptosis.
Ferroptotic tumor cells may also reciprocally remodel the immune microenvironment by releasing oxidized lipids and DAMPs. Counterbalancing the immunosuppressive circuit, in vitro GBM spheroids undergoing ferroptosis release DAMPs and lipid peroxidation products that can trigger M1 repolarization and enhanced CD4+ T cell infiltration in a peripheral blood mononuclear cell (PBMC)-spheroid co-culture[97]. Adenosine triphosphate (ATP) was a candidate DAMP released during ferroptosis, with CD4+ T cells exhibiting a greater response to extracellular ATP than CD8+ T cells. Together, the combination of ferroptosis induction with immunotherapy may improve patient outcomes in GBM, with a therapeutic challenge being to reverse the immunosuppressive TAM phenotype whilst simultaneously engaging potential T-cell recruiting properties of ferroptosis-induced cell death[97]. These findings suggest that lipid peroxidation products generated during ferroptosis may function both as executioners of tumor cell death and as immunologic signaling molecules capable of reshaping the inflammatory landscape of GBM.
Collectively, these findings support a model in which the TIME does not simply regulate immune interactions with GBM but actively modulates ferroptotic susceptibility. Through modulation of antioxidant buffering, lipid peroxide signaling, and iron availability, immune and stromal components reshape the ferroptosis threshold for GBM. These interactions may help explain why ferroptosis-inducing therapies exhibit highly context-dependent effects and suggest that successful therapeutic strategies will likely require simultaneous modulation of both tumor-intrinsic metabolic programs and the surrounding immune landscape.
3.3 TMZ and IR reshape the ferroptotic vulnerability in GBM
Although the canonical mechanisms of radiotherapy and TMZ center on DNA damage, emerging evidence suggests that these therapies also reshape cellular redox states and may influence ferroptotic susceptibility in cancer[98-100]. By increasing ROS, perturbing iron metabolism, and imposing stress on antioxidant buffering systems, these standard-of-care therapies may push GBM cells closer to the ferroptosis threshold, creating potential therapeutic windows for ferroptosis-targeting strategies. However, whether these treatments directly engage ferroptotic cell death pathways or instead generate secondary oxidative stress that sensitizes cells to ferroptosis remains an important unresolved question.
Radiotherapy provides one example of standard-of-care-induced ferroptosis vulnerability. Treatment of HT-1080 cells with differing doses of radiation synergized with ferroptosis-inducing agents to trigger cell death[98]. This was associated with increased lipid peroxidation, which was rescued by the ferroptosis inhibitor ferrostatin-1. Interestingly, the synergistic effects of ferroptosis-inducing agents and radiation were independent of DNA damage, as co-treatment did not increase DNA damage signal relative to radiation alone[98]. These findings in HT-1080 cells were also recapitulated in GBM. Analysis of TCGA data further suggested a role of SLC7A11 as a feature of radioresistance in gliomas, leading to the question of whether combining small molecule ferroptosis inducers and radiation may have therapeutic benefit[98]. In ex vivo samples of human glioma, radiation treatment increased ROS in slice cultures, which further increased upon co-treatment with a ferroptosis inducer[98]. These results suggest the potential of combining ferroptosis agents with radiation; however, the mixed response to radiation suggests better stratification of gliomas to identify which tumors may be most sensitive to the proposed treatment.
In contrast to radiation, the relationship between TMZ and ferroptosis remains more mechanistically ambiguous. One study proposed that TMZ induces ferroptosis through a divalent metal transporter (DMT1, also known as solute carrier family 11 member 2, SLC11A2)-dependent iron accumulation pathway[99]. Upon TMZ treatment, investigators found that GBM cells increased labile iron pools, byproducts of lipid peroxidation (malondialdehyde, MDA), and release of lactate dehydrogenase (LDH), all while depleting glutathione. Short interfering RNA (siRNA)-mediated silencing of DMT1 reversed the increase in ferroptosis markers, establishing DMT1-iron overload as a potential contributor towards the antitumor activity of TMZ outside of its canonical DNA alkylating function[99]. However, whether these findings represent direct ferroptotic execution or a secondary consequence of TMZ-induced oxidative stress remains unresolved, particularly given that DNA damage remains the dominant mechanism underlying TMZ activity and that ferroptosis validation criteria have not been uniformly applied across models.
The above distinction may be of relevance in the context of TMZ resistance. Despite TMZ being a standard-of-care therapy for GBM, TMZ treatment only improves median survival by ~ 2 months, largely due to the ability of the tumor to develop resistance to the drug[101]. TMZ analogs and imidazotetrazine alkylating agents have been developed to overcome TMZ-resistance[100]. Conjugation of chlorambucil, a nitrogen mustard alkylating agent, to an imidazotetrazine group resulted in a compound called QX302, which exhibited significant antitumor effects on O-6 methylguanine-DNA methyltransferase (MGMT) overexpressing glioma cells in culture. Furthermore, treatment with QX302 increased levels of ROS, expanded the labile iron, and induced lipid peroxidation. Compared to TMZ, QX302 more robustly induced ferroptosis across multiple GBM cell lines, and downregulated both SLC7A11 and acyl-CoA synthetase long chain family member 3 (ACSL3), a metabolic enzyme that activates long-chain fatty acids, at the mRNA and protein levels[100]. These findings suggest that next-generation alkylating agents may achieve therapeutic benefit by coupling DNA damage with enhanced disruption of lipid redox homeostasis.
Collectively, current evidence supports a model in which radiotherapy and alkylating therapies can remodel ferroptotic susceptibility in GBM by altering oxidative stress, iron availability, and antioxidant capacity. Rather than functioning as classical ferroptosis inducers, these treatments may transiently lower the ferroptosis threshold, creating context-dependent vulnerabilities that can be exploited through rational combination with ferroptosis-targeting therapies.
4. Therapeutic Targeting of Ferroptosis
The goal of ferroptosis-based therapies is to be tumor-selective and exploit tumors already positioned near the ferroptosis threshold. Successful therapeutic exploitation of ferroptosis will likely require identifying tumors that already exist near the ferroptosis threshold and selecting interventions capable of further destabilizing their antioxidant, lipid metabolic, or iron-handling networks. This is all while overcoming the constraints imposed by GBM biology, which include bypassing the blood-brain barrier, the brain TME, and the heterogeneous inter- and intra-tumoral landscape (Figure 3). Although ferroptosis-regulatory pathways can be conceptually divided into redox buffering, lipid metabolism, and iron handling, therapeutic strategies often perturb multiple axes simultaneously. This combinatorial disruption may be particularly important in GBM, where tumor cells exhibit substantial metabolic plasticity and may compensate for inhibition of any single ferroptosis pathway in isolation.
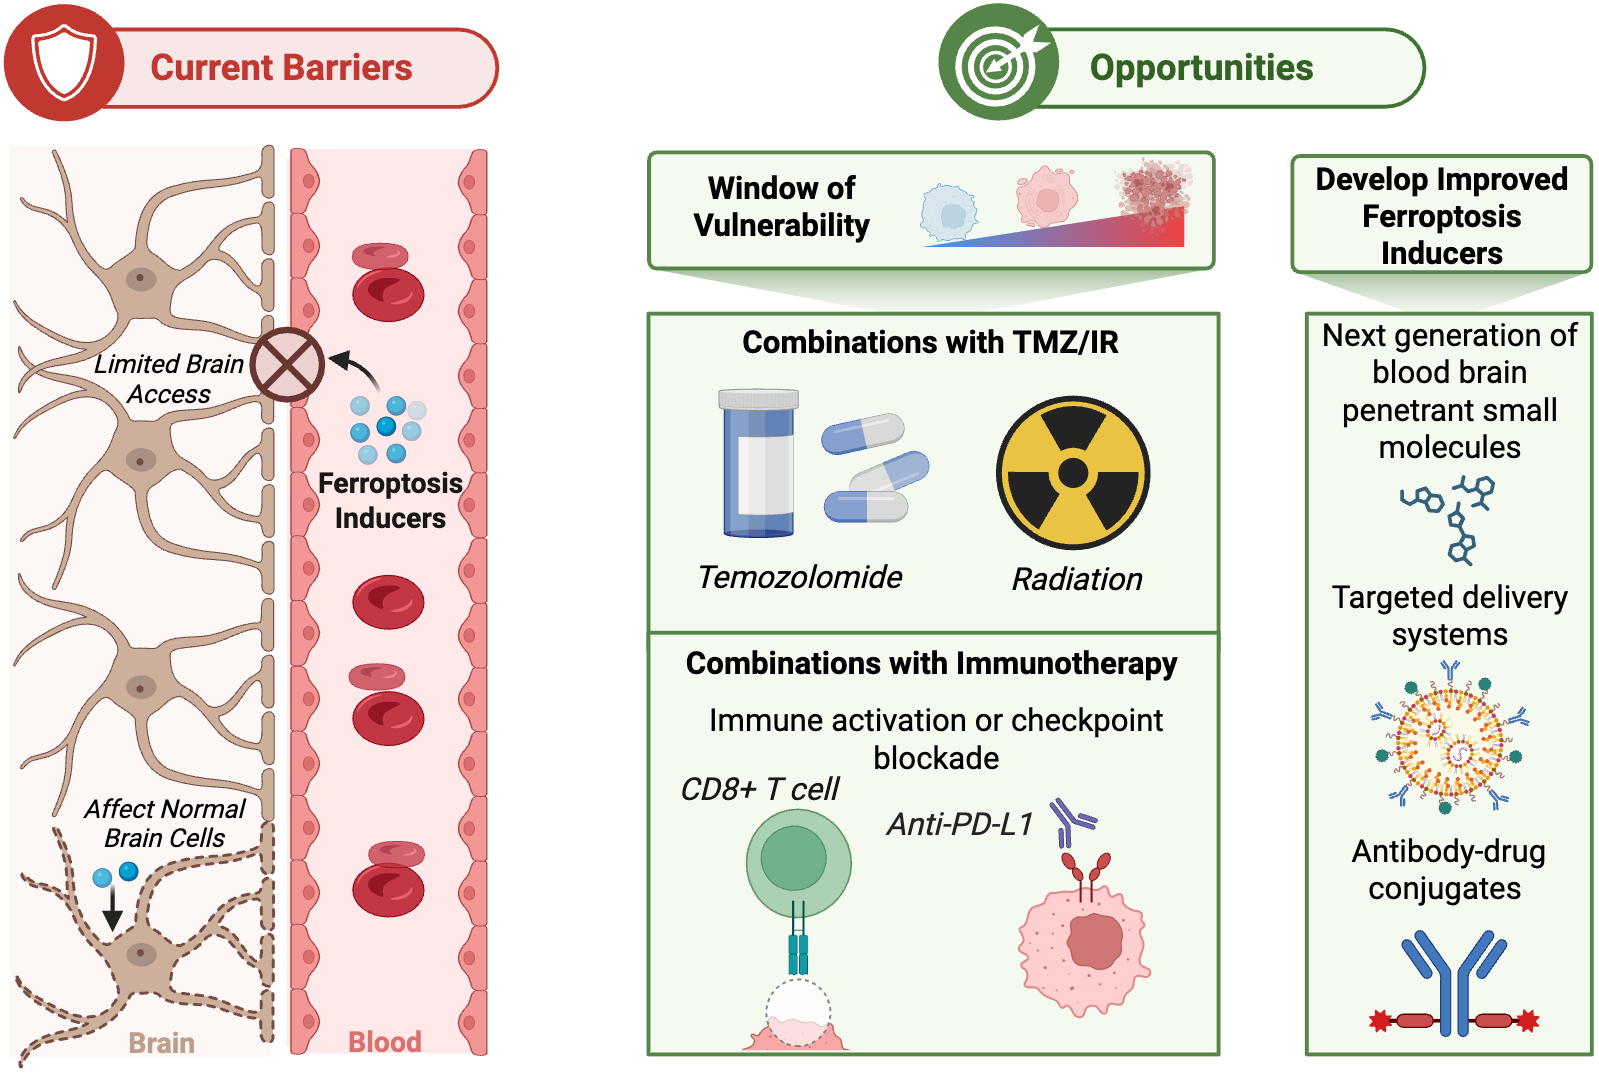
Figure 3. Barriers and opportunities for therapeutic ferroptosis induction in glioblastoma. Schematic outlining key challenges and potential strategies for harnessing ferroptosis as a therapeutic approach in glioblastoma. Current barriers (left): The blood-brain barrier restricts access of ferroptosis-inducing agents to brain tumor tissue, while limited specificity raises concern for off-target effects on normal brain cells. Opportunities (right): Potential strategies include identifying a therapeutic window of vulnerability and pursuing rational combination approaches, pairing ferroptosis induction with standard-of-care TMZ/IR or with immunotherapy, building on existing ferroptosis-inducing modalities such as small molecules, targeted delivery systems (nanoparticles, exosomes), and ADCs. Created in BioRender. Salinas, J. (2026) https://BioRender.com/is0kctq. TMZ/IR: temozolomide/radiation; ADCs: antibody-drug conjugates; Anti-PD1/L1: anti-programmed cell death protein and ligand.
4.1 Targeting redox buffering to lower the ferroptosis threshold
The most direct strategy for ferroptosis induction involves disrupting the antioxidant systems that maintain tumor cells below the ferroptosis threshold. Although many foundational ferroptosis-inducing compounds were initially characterized outside of GBM, these studies provided critical insights into the conserved redox buffering mechanisms that influence ferroptosis susceptibility across cancers. In GBM, where subsets of tumors exhibit elevated basal lipid peroxidation, ROS stress, and metabolic dependence on antioxidant defenses, these pathways may represent exploitable liabilities capable of pushing already primed tumors beyond the threshold for ferroptotic execution.
Ferroptosis inducers have been validated across multiple cancer types and have been utilized as proof-of-concept tools for core targets[102-106]. Class I ferroptosis inducers such as erastin and its analogue imidazole ketone erastin (IKE) inhibit SLC7A11 to inhibit cystine import and prevent glutathione synthesis[107]. Because glutathione availability is a primary determinant of GPX4 activity, these compounds effectively reduce the capacity of cells to detoxify lipid peroxides. This mechanism may be particularly relevant in GBM subpopulations that exhibit elevated oxidative stress or dependence on cystine metabolism to maintain survival. As mentioned, sulfasalazine has a similar mechanism; however, systemic toxicity (such as anorexia and gastrointestinal effects) for doses tested in phase 1/2 clinical trials limited the clinical efficacy of this compound in malignant gliomas[108]. Class II ferroptosis inducers such as RSL3, ML162, and ML210 have been widely used as pharmacological compounds to perturb GPX4-dependent ferroptosis; however, none of these compounds have been approved for human use and have been primarily utilized in both in vitro and in vivo preclinical studies[102,106,109]. GPX4 inhibition is especially conceptually important in GBM because subsets of GBM cells exist in a state of elevated basal lipid peroxidation, potentially rendering them disproportionately dependent on GPX4-mediated detoxification for survival. The withanolide C28 steroidal lactone withaferin A (WA) induces ferroptosis in a dose-dependent manner in both neuroblastoma cell lines and xenograft models[110]. Lastly, FIN56 is another compound that has been identified as inducing ferroptosis across a panel of cell lines[111,112]. This compound is considered a Class III ferroptosis inducer and promotes the degradation of GPX4[111]. Whilst GPX4 inhibition may offer one avenue for inducing ferroptosis, conventional GPX4 inhibitors have limited therapeutic efficacy due to poor pharmacokinetics and the necessity of GPX4 for normal tissue[102,104,106,113-115].
Sorafenib (SRF) is another compound not specifically designed to induce ferroptosis but that may induce ferroptosis[116]. SRF is a small molecule kinase inhibitor and has been clinically approved to treat advanced hepatocellular carcinoma[117]. The role of SRF in ferroptosis is mixed. SRF may induce ferroptosis by suppressing SLC7A11 expression[116], but this appears to be cell-line or cell-type-specific[118]. These conflicting findings further emphasize that ferroptosis susceptibility is highly context-dependent and likely determined by the pre-existing metabolic and lipid state of individual tumors rather than exposure to a ferroptosis-inducing agent alone.
Although many canonical ferroptosis inducers were initially characterized outside of GBM, lipidomic and transcriptional analyses in GBM support the relevance of these pathways within the CNS context. CDKN2A-deleted tumors, mesenchymal-like cellular states, and therapy-exposed recurrent GBM have all been associated with elevated oxidative stress or altered lipid metabolism that may increase reliance on glutathione- and GPX4-dependent buffering systems. These observations provide a mechanistic rationale for adapting redox-targeting ferroptosis strategies specifically to biomarker-defined GBM subpopulations.
4.2 Targeting lipid availability and peroxidation
Because ferroptosis requires membrane phospholipid peroxidation, therapeutic approaches that increase the abundance or oxidation of PUFA-containing phospholipids may selectively sensitize GBM cells to ferroptotic execution. PLs containing AA or AdA are highly susceptible to lipid peroxidation[19,119]. In chronic myeloid leukemia cells, ACSL4 and lysophosphatidylcholine acyltransferase 3 (LPCAT3) catalyze PUFA (e.g., AA and AdA) activation and insertion into membrane lyso-PLs, respectively. These PUFA-containing PLs can be oxidized by lipoxygenases (LOXs) to form PL hydroperoxides, cascading into membrane peroxide formation and ferroptosis[120]. Therefore, in ACSL4- and LPCAT3-high tumors, providing PUFA substrates to be incorporated into the PL membrane could increase the likelihood of ferroptosis execution. These observations are particularly relevant in GBM, where transcriptional states, CDKN2A loss, and lipid droplet dynamics reshape the balance between PUFA storage and membrane incorporation.
DHODH inhibition can simultaneously decrease pyrimidine synthesis and shut down the CoQ10 antioxidant pathway[121]. Intriguingly, DHODH inhibition not only suppresses mitochondrial antioxidant defense but can also alter phospholipid remodeling. Inhibition of DHODH reduced CDP-choline levels and decreased the synthesis of phosphatidylcholine (PC) via the Kennedy pathway; as a compensatory mechanism, cells increased the generation of very long chain polyunsaturated fatty acid containing PC from phosphatidylethanolamines (PEs), which increased CD8+ T cell infiltration and IFN-γ secretion, which enhanced anti-tumor PD-1 blockade in vivo[122]. Increased PUFA-PCs could also prime tumors for ferroptosis. Elevated DHODH expression in neuroblastoma correlates with poorer prognosis, making it a compelling target in brain cancers[123].
Recent GBM-specific therapeutic approaches have attempted to directly amplify phospholipid peroxidation within tumors. Using a genome-wide CRISPR-Cas9 screen in the presence of RSL3, ALOX15 was identified as an essential driver of ferroptosis in GBM cells[124]. ALOX15 promoted ferroptosis through increasing peroxidation of PUFAs. To activate this pathway therapeutically, angiopep-2-modified macrophage membrane-coated biomimetic nanoparticles (Ang-MMsaNPs) were developed by encapsulating a small activating RNA (saRNA) of ALOX15 in mesoporous polydopamine (MPDA) and coating with a modified MM[124]. Small activating RNAs are small, double-stranded RNAs that target the promoter of the gene of interest[125,126]. Mechanistically, the Ang-MMsaNPs caused mitochondrial abnormalities, thus increasing peroxidation and ferroptosis in GBM cells. Preclinical evaluation of Ang-MMsaNPs in GBM orthotopic xenografts showed that Ang-MMsaNPs induced negligible toxic effects on the liver or hematological factors and seemed to decrease tumor volume and increase overall survival. Ang-MMsaNP-treated tumors had increased ALOX15 protein expression and increased ACSL4 expression, as well as increased markers of lipid peroxidation. Ang-MMsaNP could also be combined synergistically with RT to prolong survival and further decrease tumor growth relative to single agent treatment[124]. Importantly, this strategy exploits a pre-existing lipid vulnerability rather than relying solely on generalized oxidative stress.
4.3 Exploiting iron pools and microenvironmental ferroptosis induction
Ferroptosis requires redox-active iron. Multiple emerging GBM-directed therapies therefore aim to amplify ferroptosis through iron delivery, immune-mediated signaling, or simultaneous disruption of multiple ferroptosis axes.
Angiopep-2-modifications have also been utilized to engineer exosome-conjugated magnetic nanoparticles to target both the DHODH and GPX4 axes[127]. Magnetic iron oxide nanoparticles were engineered to simultaneously inhibit GPX4 and DHODH while releasing iron within GBM cells, thereby disrupting both the redox buffering and iron handling axes[127]. These combinatorial nanoparticle systems may be particularly effective because they simultaneously destabilize multiple ferroptosis axes.
Ferroptosis induction may also synergize with immune modulation within the GBM microenvironment. IFN-γ released by activated T cells can induce ferroptosis in cancer cells; to target this phenomenon, a biomimetic microglial membrane-coated Fe3O4 nanoparticle was designed to deliver siPD-L1 (Fe3O4-siPD-L1@M-BV2) to deplete PD-L1[128]. This compound utilized siRNA to interfere with PD-L1 protein synthesis using an iron (II, III) oxide (Fe3O4) nanoparticle to increase siPD-L1 delivery and prevent degradation. Furthermore, this nanoparticle increased intracellular iron, which provided substrates for ferroptosis. To increase blood-brain barrier (BBB) penetration, the nanoparticles were coated with microglial membranes (M-BV2). These modifications showed that Fe3O4-siPD-L1@M-BV2 were mainly distributed in the brain and liver of GBM orthotopic xenograft models, with treatment significantly increasing iron content, polarizing M2 type microglia to M1 type microglia, increasing IFN-γ, TNF-α and IL-12, and decreasing tumor growth[128]. Disrupting stress granules sensitized glioma stem cells to IR/TMZ by recruiting iron-related proteins[129]. Mechanistically, stress granule proteins directly interacted with the ferritin light chain in an IR/TMZ-induced manner. IR/TMZ treatment induced the oxidation of stress-granule proteins, which promoted binding to the ferritin light chain, caused ferritin sequestration in stress granules, suppressed iron accumulation, and inhibited ferroptosis in glioma stem cells[129]. This phenotype was reversed by disrupting the interaction between the stress granule proteins and ferritin light chain, thus restoring iron-mediated ferroptosis and re-sensitizing glioma stem cells (both in vitro and in vivo) to TMZ/IR[129].
Engineered bacterial outer membrane vesicles (OMV-C-C) expressing cell penetrating peptides (CPP) and chlorotoxin (CLT) provide an alternative approach to synthetic nanoparticles[130]. CPP and CLT were co-expressed on the surface of OMV-C-C, with CLT enabling specific targeting of the OMV-C-C to GBM. OMV-C-C crossed the BBB and decreased tumor growth in an orthotopic xenograft model of GBM by increasing the infiltration of CD8+ T cells. Interestingly, BBB penetration was attributed to CPP-mediated transcytosis, as transport was reduced by inhibitors of transcytotic pathways; however, the specific endothelial receptor or transport machinery responsible was not identified. Lastly, CD8+ T cell release of IFN-γ induced ferroptosis through SLC7A11 and GPX4 downregulation, increasing lipid peroxidation[130]. Together, these approaches suggest that ferroptosis induction may be most effective when integrated with immune activation and localized iron amplification rather than as isolated monotherapy.
4.4 Combination therapy to modulate ferroptotic vulnerability
The maximal therapeutic benefit of ferroptosis induction in GBM will likely emerge not from constitutive ferroptosis activation alone, but from exploiting transient windows of vulnerability created by standard therapy. As noted above, it has been proposed that TMZ can prime cells for ferroptosis by depleting glutathione, increasing ROS, and reducing GPX4 activity. Radiotherapy may transiently shift GBM cells closer to the ferroptosis threshold through oxidative membrane damage. Lastly, the ferroptosis-IFN-γ-system xc- axis provides a positive feedback loop that can increase CD8+ T cell infiltration and induce tumor ferroptosis. Collectively, these findings suggest that conventional therapies can synergize with ferroptosis induction and actively create temporally restricted ferroptotic vulnerabilities that can be therapeutically exploited.
5. Future Perspectives-Towards Clinical Translation
Despite preclinical evidence supporting ferroptosis as a therapeutic vulnerability in GBM, clinical translation remains limited by a central challenge: ferroptosis susceptibility is neither static nor universal across tumors. Rather, GBM cells occupy dynamic positions regarding ferroptosis sensitivity, where proximity to the ferroptosis threshold is governed by the interplay between lipid composition, antioxidant buffering capacity, and iron handling (Figure 1). Translating ferroptosis into an effective therapeutic strategy will require identifying tumors already poised near this threshold and selectively pushing them beyond it while sparing normal brain tissue.
5.1 Defining the ferroptosis threshold in GBM
As discussed previously, GBM ferroptosis sensitivity is heterogeneous and depends on many genetic and non-genetic factors. One implication of this is that GBM tumors are unlikely to respond uniformly to ferroptosis-inducing therapies. Instead, sensitivity will reflect the cumulative state of the three ferroptosis-regulatory axes: lipid availability, redox buffering capacity, and iron metabolism. Biomarkers capable of measuring these states may therefore identify tumors intrinsically poised for ferroptotic collapse and help guide patient selection.
Among these axes, lipid remodeling may represent the most immediate determinant of ferroptotic priming in GBM. At the genetic level, CDKN2A deletion status has emerged as the most immediately actionable biomarker, validated through lipidomic and functional testing in over 150 GBM tumors and derivative preclinical in vivo and in vitro models[12]. Here, CDKN2A-deleted GBMs were found to display increased levels of basal lipid peroxidation due to a preferential shuttling of PUFAs towards oxidizable membrane phospholipids, thus sensitizing these tumors to GPX4 inhibition. Since CDKN2A deletion is routinely tested for after surgical resection, this biomarker could be integrated into clinical trial eligibility[12].
In parallel, tumors vary substantially in their antioxidant buffering capacity, which determines their ability to neutralize lipid peroxide accumulation. Furthermore, iron availability represents the third major determinant of ferroptosis susceptibility and may be particularly dynamic within the GBM microenvironment[79,96,129]. At the transcriptional level, GBM subtype and cellular state identity potentially dictate sensitivity to ferroptosis and could be considered as an additional co-stratification variable[24,79,131]. Ferroptosis-gene signatures have been identified and validated in TCGA and CGGA cohorts as stratifying patients by predicted immunotherapy response and could also be leveraged in the context of ferroptosis-inducing therapies[132].
Importantly, no single biomarker is likely to fully predict ferroptosis sensitivity in GBM. Rather, clinically useful stratification will likely require integrated assessment across all three ferroptotic axes. Combining genomic alterations, transcriptional state identity, lipidomic profiling, and ferroptosis-associated gene signatures may provide a more accurate representation of where individual tumors reside relative to the ferroptosis threshold.
5.2 Therapeutic selectivity and the constraint of the Central Nervous System (CNS)
The ferroptosis threshold model also highlights a major therapeutic challenge unique to GBM: the same lipid-rich environment that predisposes tumor cells to ferroptosis also renders normal CNS tissue vulnerable to oxidative membrane damage. Successful clinical translation will therefore depend on inducing ferroptosis in tumor cells while sparing surrounding neural and endothelial cells.
As mentioned previously, the BBB is a formidable physical barrier to ferroptosis-inducing therapies. Conventional small molecule ferroptosis inducers, such as RSL3, ML162, and erastin, offer limited tumor penetration due to poor BBB crossing efficiency and unfavorable pharmacokinetics[133]. Furthermore, a critical constraint of ferroptosis inducers is that they must cross the BBB without inducing ferroptosis in the endothelial cells that line the BBB. This is a high bar because ferroptosis is induced by diverse brain injuries[134-136]. In zebrafish cerebrovascular endothelial cells, BBB disruption was induced upon hypoxic treatment by activating ferroptosis-related genes, inhibiting SLC7A11 activity, and increasing lipid peroxidation and ROS[137]. These effects were reversed with ferrostatin-1 treatment. Thus, there is the concern that doses sufficient to induce GBM ferroptosis may paradoxically compromise the structure that must be passed to successfully deliver drugs to the tumor.
Neurons may also be ferroptosis-sensitive due to their high PUFA content, elevated metabolic demand, and dependence on GPX4-mediated lipid peroxide detoxification. Conditional ablation of Gpx4 in neurons resulted in rapid motor neuron degeneration and paralysis in mice[138]. Spinal cord sections from Gpx4 neuronal KO mice showed increased astrogliosis, increased lipid peroxidation, and mitochondrial damage[138]. In human dopaminergic neuronal models, endogenous levels of alpha-synuclein can determine the sensitivity of neurons to ferroptosis, with increased levels corresponding to an increase in lipid peroxidation and thus ferroptosis[139]. Furthermore, neurons are rich in phospholipids that contain PUFAs to regulate membrane fluidity and signaling[140,141]; however, this also renders them more vulnerable to ferroptosis. Thus, catastrophic side effects could emerge when targeting ferroptosis in GBM, ranging from neurodegeneration to undesired endothelial cell BBB disruption and inflammatory necrosis.
Collectively, these challenges reinforce the need for ferroptosis-inducing strategies that are biomarker-guided, spatially restricted, and temporally coordinated with therapies that transiently destabilize tumor redox homeostasis. In this context, the goal is not universal ferroptosis induction, but selective collapse of tumors already positioned near the ferroptosis threshold[10,64,142-154].
5.3 Antibody-drug conjugates (ADCs) as a tumor-specific delivery strategy
ADCs couple tumor-antigen targeting antibodies to cytotoxic payloads via a chemical linker, restricting payload release to target cells[142,143]. This strategy may be particularly attractive for ferroptosis induction in GBM, where the susceptibility of normal CNS cells to lipid peroxidation may constrain the therapeutic window of systemically administered ferroptosis-inducing agents. Because ADC selectivity is strongly influenced by target-antigen expression, identifying tumor-enriched surface antigens is central to adapting this approach to GBM.
B7-H3 (CD276) represents one potential target, as it is highly expressed in GBM tumor cells, with minimal to no expression in normal brain tissue[10]. B7-H3 directed conjugates have already demonstrated GBM-selective activity in preclinical models[10,144,145], providing proof of principle that this antigen can be exploited for tumor-directed payload delivery. Notably, a B7-H3 targeted MMP-2 nanoparticle-antibody conjugate enhanced IFN-γ driven ferroptosis in orthotopic GBM models, while limiting activation outside the tumor microenvironment[144]. EGFRvIII, a tumor-specific EGFR variant absent from normal tissue, offers another potential target, although its heterogeneous expression within a tumor may limit its efficacy as a sole antigen[64,146]. EGFR- and EGFRvIII-directed ADCs, including AMG 595 and depatuxizumab mafodotin, have reached clinical testing in GBM[147-151], establishing the feasibility of antibody-directed payload delivery against these antigens. However, heterogeneous antigen expression and payload-associated toxicities observed with these agents highlight the importance of both antigen and payload selection when designing GBM-directed ADCs.
Importantly, dedicated ferroptosis-inducing agents have begun to be evaluated as ADC payloads outside the CNS. A trastuzumab-RSL3 conjugate induced ferroptosis in HER2-expressing breast cancer cells[152]. Sulfasalazine (SAS) has similarly been incorporated into an FGFR4-targeted ADC that induced ferroptosis in hepatocellular carcinoma[153], while a bispecific Cadherin-17/Guanylyl cyclase C (CDH17/GUCY2C) ADC carrying RSL3 enhanced internalization and inhibited colorectal tumor growth in cell culture and in vivo[154]. These studies provide proof of principle that agents targeting GPX4 or system Xc- can be incorporated into tumor-directed delivery platforms while retaining ferroptosis-inducing activity. They also raise the possibility that payload selection could be guided by a tumor’s position along the three-axis ferroptosis framework, with different ferroptotic vulnerabilities potentially favoring distinct payload mechanisms.
Despite this promising precedent, there are no reported GBM-targeted ADCs carrying a dedicated ferroptosis-inducing payload. Nevertheless, the availability of GBM-enriched surface antigens, prior experience with ADC-based delivery in GBM, and proof-of-concept ferroptosis-inducing ADCs in other cancers collectively provide a rationale for this approach. Translating ferroptosis-targeted ADCs to GBM will require a coordinated selection of a sufficiently abundant and homogeneous tumor antigen, a ferroptotic payload matched to the underlying tumor vulnerability, and linker and conjugate properties that enable effective tumor delivery while limiting exposure to normal CNS tissue.
6. Concluding Remarks
Ferroptosis represents more than an additional cell death mechanism that can be activated in GBM; it provides a conceptual framework for understanding how lipid metabolism, antioxidant defenses, and iron handling converge to create therapeutically exploitable vulnerabilities within defined subsets of GBM tumors and states. The evidence reviewed here supports a model in which GBM cells traverse a dynamic ferroptotic landscape shaped by three interdependent axes: lipid availability, redox buffering capacity, and iron handling. Genetic alterations, transcriptional states, microenvironmental signals, and therapeutic exposures continuously shift tumor cells toward or away from the threshold of ferroptosis, generating heterogeneous and context-dependent ferroptosis susceptibility. Advances in nanoparticle-based delivery systems, biomarker-guided patient stratification, and rational combination strategies involving radiotherapy, chemotherapy, and immunotherapy suggest ferroptosis-based approaches may be approaching clinical feasibility. Furthermore, targeted therapeutic delivery strategies such as ADCs offer a complementary route to tumor-selective ferroptosis induction, as discussed in detail in Section 5.3. This may be particularly valuable for overcoming the CNS-selectivity barriers outlined above.
Significant but addressable challenges remain (Figure 3). Moving ferroptosis toward clinical translation in GBM will require biomarker-driven therapeutic strategies that identify tumors intrinsically positioned near the ferroptosis threshold. Based on the evidence reviewed here, one of the most actionable approaches may involve combining therapies already associated with ferroptotic priming, including TMZ, IR, and immunotherapy, with brain penetrant ferroptosis inducers in CDKN2A-deleted GBM, a molecular subset with a strong mechanistic rationale and a profound unmet clinical need. Integrating measurements of PUFA-phospholipid abundance, ACSL4 and GPX4 expression, transcriptional state identity, and ferroptosis-associated gene signatures may further refine patient selection and therapeutic response. Equally important will be the development of optimized BBB-penetrant agents capable of selectively targeting tumor cells while minimizing ferroptosis-associated toxicity within normal CNS tissue.
More broadly, ferroptosis may represent only one mechanism within a larger landscape of non-apoptotic, metabolism-linked cell death vulnerabilities in GBM. The same adaptations that render GBM resistant to apoptosis, including metabolic plasticity and lipid remodeling, may simultaneously generate other dependencies that can be therapeutically exploited. Emerging evidence suggests that multiple non-apoptotic cell death mechanisms may intersect through shared control of reactive oxygen species, mitochondrial dysfunction, and lipid metabolic homeostasis[155,156]. In this context, ferroptosis may serve not only as a therapeutic target itself but also as a broader framework for understanding how treatment-resistant GBM tumors become vulnerable through the same metabolic adaptations that sustain them during stress.
As the field moves forward, the central challenge will be to identify additional regulated cell death mechanisms and determine how specific molecular subsets or cell states of GBM become selectively vulnerable to them. Defining these context-dependent liabilities, and therapeutically exploiting them with sufficient precision within the constraints of the CNS, may ultimately provide a path toward overcoming the profound treatment resistance that has historically defined GBM.
Acknowledgements
We would like to thank members of the Nathanson and Dixon laboratories for constructive discussions during the preparation of this manuscript.
Authors contribution
Minami JK: Conceptualization, visualization, investigation, writing-original draft, writing-review & editing.
Salinas JJ: Conceptualization, visualization, writing-review & editing.
Loo CE: Investigation.
Lee WC, Dixon SJ: Writing-review & editing.
Nathanson DA: Conceptualization, writing-review & editing.
Conflicts of interest
David A Nathanson is a co-founder of Trethera Corporation and holds equity in the company. David A Nathanson is a co-founder of Katmai Pharmaceuticals and holds equity in and has consulting agreements with the company. David A Nathanson is an inventor on intellectual property related to ferroptosis. Scott J Dixon is an Editorial Board member of FOS. The other authors declare no conflicts of interest.
Ethical approval
Not applicable.
Consent to participate
Not applicable.
Consent for publication
Not applicable.
Availability of data and materials
Not applicable.
Funding
David A Nathanson and Scott J Dixon are supported by NIH (Grant Nos. R01NS121319 and R01NS143119), and Jennifer J Salinas is supported by the UCLA Tumor Cell Biology Training Program USHHS Ruth L. Kirschstein Institutional National Research Service Award (Grant No. T32 CA009056).
Copyright
© The Author(s) 2026.
References
-
48. Barnes T, Parry P, Hart I, Jones C, Minet M, Patterson D. Regional mapping of the gene encoding dihydroorotate dehydrogenase, an enzyme involved in UMP synthesis, electron transport, and superoxide generation, to human chromosome region 16q22. Somat Cell Mol Genet. 1993;19(4):405-411.
-
64. Felsberg J, Hentschel B, Kaulich K, Gramatzki D, Zacher A, Malzkorn B, et al. Epidermal growth factor receptor variant III (EGFRvIII) positivity in EGFR-amplified glioblastomas: Prognostic role and comparison between primary and recurrent tumors. Clin Cancer Res. 2017;23(22):6846-6855.
-
94. Naing A, Eder JP, Piha-Paul SA, Gimmi C, Hussey E, Zhang S, et al. Preclinical investigations and a first-in-human phase I trial of M4112, the first dual inhibitor of indoleamine 2,3-dioxygenase 1 and tryptophan 2, 3-dioxygenase 2, in patients with advanced solid tumors. J Immunother Cancer. 2020;8(2):e000870.
-
148. Rosenthal M, Curry R, Reardon DA, Rasmussen E, Upreti VV, Damore MA, et al. Safety, tolerability, and pharmacokinetics of anti-EGFRvIII antibody-drug conjugate AMG 595 in patients with recurrent malignant glioma expressing EGFRvIII. Cancer Chemother Pharmacol. 2019;84(2):327-336.
-
149. van den Bent M, Gan HK, Lassman AB, Kumthekar P, Merrell R, Butowski N, et al. Efficacy of depatuxizumab mafodotin (ABT-414) monotherapy in patients with EGFR-amplified, recurrent glioblastoma: Results from a multi-center, international study. Cancer Chemother Pharmacol. 2017;80(6):1209-1217.
-
150. Lassman AB, van den Bent MJ, Gan HK, Reardon DA, Kumthekar P, Butowski N, et al. Safety and efficacy of depatuxizumab mafodotin + temozolomide in patients with EGFR-amplified, recurrent glioblastoma: Results from an international phase I multicenter trial. Neuro Oncol. 2019;21(1):106-114.
-
151. Clement PMJ, Dirven L, Eoli M, Sepulveda-Sanchez JM, Walenkamp AME, Frenel JS, et al. Impact of depatuxizumab mafodotin on health-related quality of life and neurological functioning in the phase II EORTC 1410/INTELLANCE 2 trial for EGFR-amplified recurrent glioblastoma. Eur J Cancer. 2021;147:1-12.
Copyright
© The Author(s) 2027. This is an Open Access article licensed under a Creative Commons Attribution 4.0 International License (https://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, sharing, adaptation, distribution and reproduction in any medium or format, for any purpose, even commercially, as long as you give appropriate credit to the original author(s) and the source, provide a link to the Creative Commons license, and indicate if changes were made.
Publisher’s Note
Science Exploration remains a neutral stance on jurisdictional claims in published
maps
and institutional affiliations. The views expressed in this article are solely those
of
the author(s) and do not reflect the opinions of the Editors or the publisher.
Share And Cite


Science Exploration Style
Minami JK, Salinas JJ, Loo CE, Lee WC, Dixon SJ, Nathanson DA. Beyond ferroptosis induction: Defining ferroptosis vulnerability in glioblastoma. Ferroptosis Oxid Stress. 2027;3:202637. https://doi.org/10.70401/fos.2026.0048
Tips
Copy completed.
Submit a Manuscript
Author Instructions
Cite this Article
Article Metrics
0
View
0
Download
Cited
Article Updates

- Abstract
- Keywords
- 1. Introduction
- 2. Intrinsic Determinants of the Ferroptosis Threshold in GBM
- 3. Extrinsic Signals Dynamically Shift the Three Ferroptosis Axes in GBM
- 4. Therapeutic Targeting of Ferroptosis
- 5. Future Perspectives-Towards Clinical Translation
- 6. Concluding Remarks
- Acknowledgements
- Authors contribution
- Conflicts of interest
- Ethical approval
- Consent to participate
- Consent for publication
- Availability of data and materials
- Funding
- References
- Copyright
 Get citation
Science Exploration Style

Minami JK, Salinas JJ, Loo CE, Lee WC, Dixon SJ, Nathanson DA. Beyond ferroptosis induction: Defining ferroptosis vulnerability in glioblastoma. Ferroptosis Oxid Stress. 2027;3:202637. https://doi.org/10.70401/fos.2026.0048
copy
Share Link
copy