Ferroptosis and oxidative stress crosstalk in tumor microenvironment: Mechanisms and targeting strategies

*Correspondence to:
Jun Xia, Laboratory Medicine Center, Department of Clinical Laboratory, Zhejiang Provincial People’s Hospital (Affiliated People’s Hospital), Hangzhou Medical College, Hangzhou 310014, Zhejiang, China.
E-mail: andisky_005@126.com
Jing Du, Laboratory Medicine Center, Department of Clinical Laboratory, Zhejiang Provincial People’s Hospital (Affiliated People’s Hospital), Hangzhou Medical College, Hangzhou 310014, Zhejiang, China. E-mail: dujing1@hmc.edu.cn
Yanchun Li, Department of Clinical Laboratory, Affiliated Hangzhou First People’s Hospital, School of Medical, Westlake University, Hangzhou 310006, Zhejiang, China. E-mail: lycmed@163.com
Jing Du, Laboratory Medicine Center, Department of Clinical Laboratory, Zhejiang Provincial People’s Hospital (Affiliated People’s Hospital), Hangzhou Medical College, Hangzhou 310014, Zhejiang, China. E-mail: dujing1@hmc.edu.cn
Yanchun Li, Department of Clinical Laboratory, Affiliated Hangzhou First People’s Hospital, School of Medical, Westlake University, Hangzhou 310006, Zhejiang, China. E-mail: lycmed@163.com
Ferroptosis Oxid Stress. 2027;3:202635. 10.70401/fos.2026.0049
Received: July 13, 2026Accepted: October 09, 2026Published: October 10, 2026
Abstract
Ferroptosis, an iron-dependent form of regulated cell death driven by lipid peroxidation, is intricately linked with oxidative stress through shared regulatory nodes and reciprocal amplification loops. Although ferroptosis and oxidative stress have each been extensively investigated, their bidirectional crosstalk, together with its consequences for the tumor microenvironment, has yet to be systematically elucidated. On this basis, this review proposes and systematically dissects a “ferroptosis-oxidative stress-tumor microenvironment” triad, focusing on its bidirectional interaction network and therapeutic translational value. We analyze the driving mechanisms underlying the mutually amplifying loop between the two processes, including iron metabolism, lipid peroxidation cascades, antioxidant defense, and organelle function. Within the tumor microenvironment, this interplay drives context-dependent remodeling of immune cell function, cancer-associated fibroblast activity, angiogenesis, and tumor heterogeneity. Furthermore, this review evaluates emerging therapeutic strategies that target ferroptosis and oxidative stress within the TME, and outlines the obstacles hindering clinical translation and future directions. A deep understanding of the “ferroptosis-oxidative stress-tumor microenvironment” triad will advance our fundamental understanding of the execution and regulatory mechanisms of ferroptosis, and lay a theoretical foundation for the future development of precision therapeutic strategies centered on ferroptosis.
Keywords
Ferroptosis, oxidative stress, tumor microenvironment, therapeutic strategies
1. Introduction
Ferroptosis is a form of regulated cell death driven by iron-dependent lipid peroxidation. Morphologically, it is characterized by reduced mitochondrial cristae and rupture of the outer mitochondrial membrane. The core biochemical mechanisms involve an imbalance in the intracellular iron pool, the collapse of the glutathione/glutathione peroxidase 4 (GSH/GPX4) antioxidant system, and the peroxidative modification of polyunsaturated fatty acids (PUFAs)[1]. Since the concept was first introduced by Stockwell et al. in 2012, ferroptosis research has rapidly expanded into various pathological fields, including oncology, neurodegenerative diseases, and ischemia-reperfusion injury[2]. In the field of oncology, the induction of ferroptosis has been regarded as a promising therapeutic strategy, and the implementation of this strategy is closely related to the unique physicochemical characteristics of the tumor microenvironment (TME).
The TME is the complex ecosystem that surrounds and supports the growth of cancer cells, comprising stromal cells, immune cells, the extracellular matrix, secreted factors, and networks of blood and lymphatic vessels[3]. Metabolic reprogramming is a hallmark of the TME, characterized by the Warburg effect, enhanced glutamine metabolism, and abnormal lipid metabolism. This results in a microenvironment defined by nutrient deprivation, hypoxia, acidity, and an enrichment of reactive oxygen species (ROS)[4]. At physiological levels, ROS function as signaling molecules that promote cell proliferation and survival. Excessive ROS induce oxidative stress, resulting in DNA damage, protein oxidation, and lipid peroxidation[5]. The continuous enrichment of ROS in the TME provides a natural biochemical basis for the triggering of ferroptosis.
There is substantial mechanistic overlap between oxidative stress and ferroptosis, which has garnered considerable attention. Excessive ROS can directly attack membrane lipids, initiating the peroxidation cascade, while iron accumulation catalyzes the production of highly reactive free radicals via the Fenton reaction, further amplifying oxidative damage[6]. Tumor cells often resist this lethal stress by upregulating antioxidant pathways such as nuclear factor erythroid 2-related factor 2 (NRF2), GPX4, and ferroptosis suppressor protein 1 (FSP1). Metabolites within the TME and intercellular communication profoundly influence this delicate balance[7,8]. A deep understanding of the interplay between ferroptosis and oxidative stress within the TME holds significant clinical implications for the development of novel antitumor strategies. Therefore, this review systematically elucidates the interaction between ferroptosis and oxidative stress in the TME, aiming to provide a theoretical basis and a translational perspective for cancer therapies targeting the ferroptosis-oxidative stress axis.
2. Molecular Mechanisms of Ferroptosis
The process of ferroptosis is governed by iron metabolic homeostasis, lipid peroxidation, and the intracellular antioxidant system (Figure 1). In terms of iron dyshomeostasis, transferrin receptor 1 (TfR1) mediates the endocytosis of the transferrin-iron complex[9], and the iron export protein ferroportin (FPN) regulates iron efflux to maintain cellular iron homeostasis[10]. Ferritin is responsible for iron storage and can be selectively degraded via nuclear receptor coactivator 4 (NCOA4)-mediated ferritinophagy, releasing free iron[11]. Intracellular labile iron directly catalyzes lipid peroxidation via the Fenton reaction, generating highly reactive hydroxyl radicals and inducing ferroptosis[12]. The abundance of PUFAs in membrane phospholipids provides the structural foundation for ferroptosis. Acyl-CoA synthetase long-chain family member 4 (ACSL4) and lysophosphatidylcholine acyltransferase 3 (LPCAT3) activate PUFAs to acyl-CoA esters, followed by peroxidation catalyzed by lipoxygenases (LOX) and cyclooxygenases (COX) with the participation of iron[13]. The accumulation of lipid peroxides disrupts membrane lipid bilayer stability, increases membrane permeability, induces membrane protein dysfunction and cellular metabolic imbalance, ultimately damaging the integrity of the cell membrane and triggering ferroptosis.
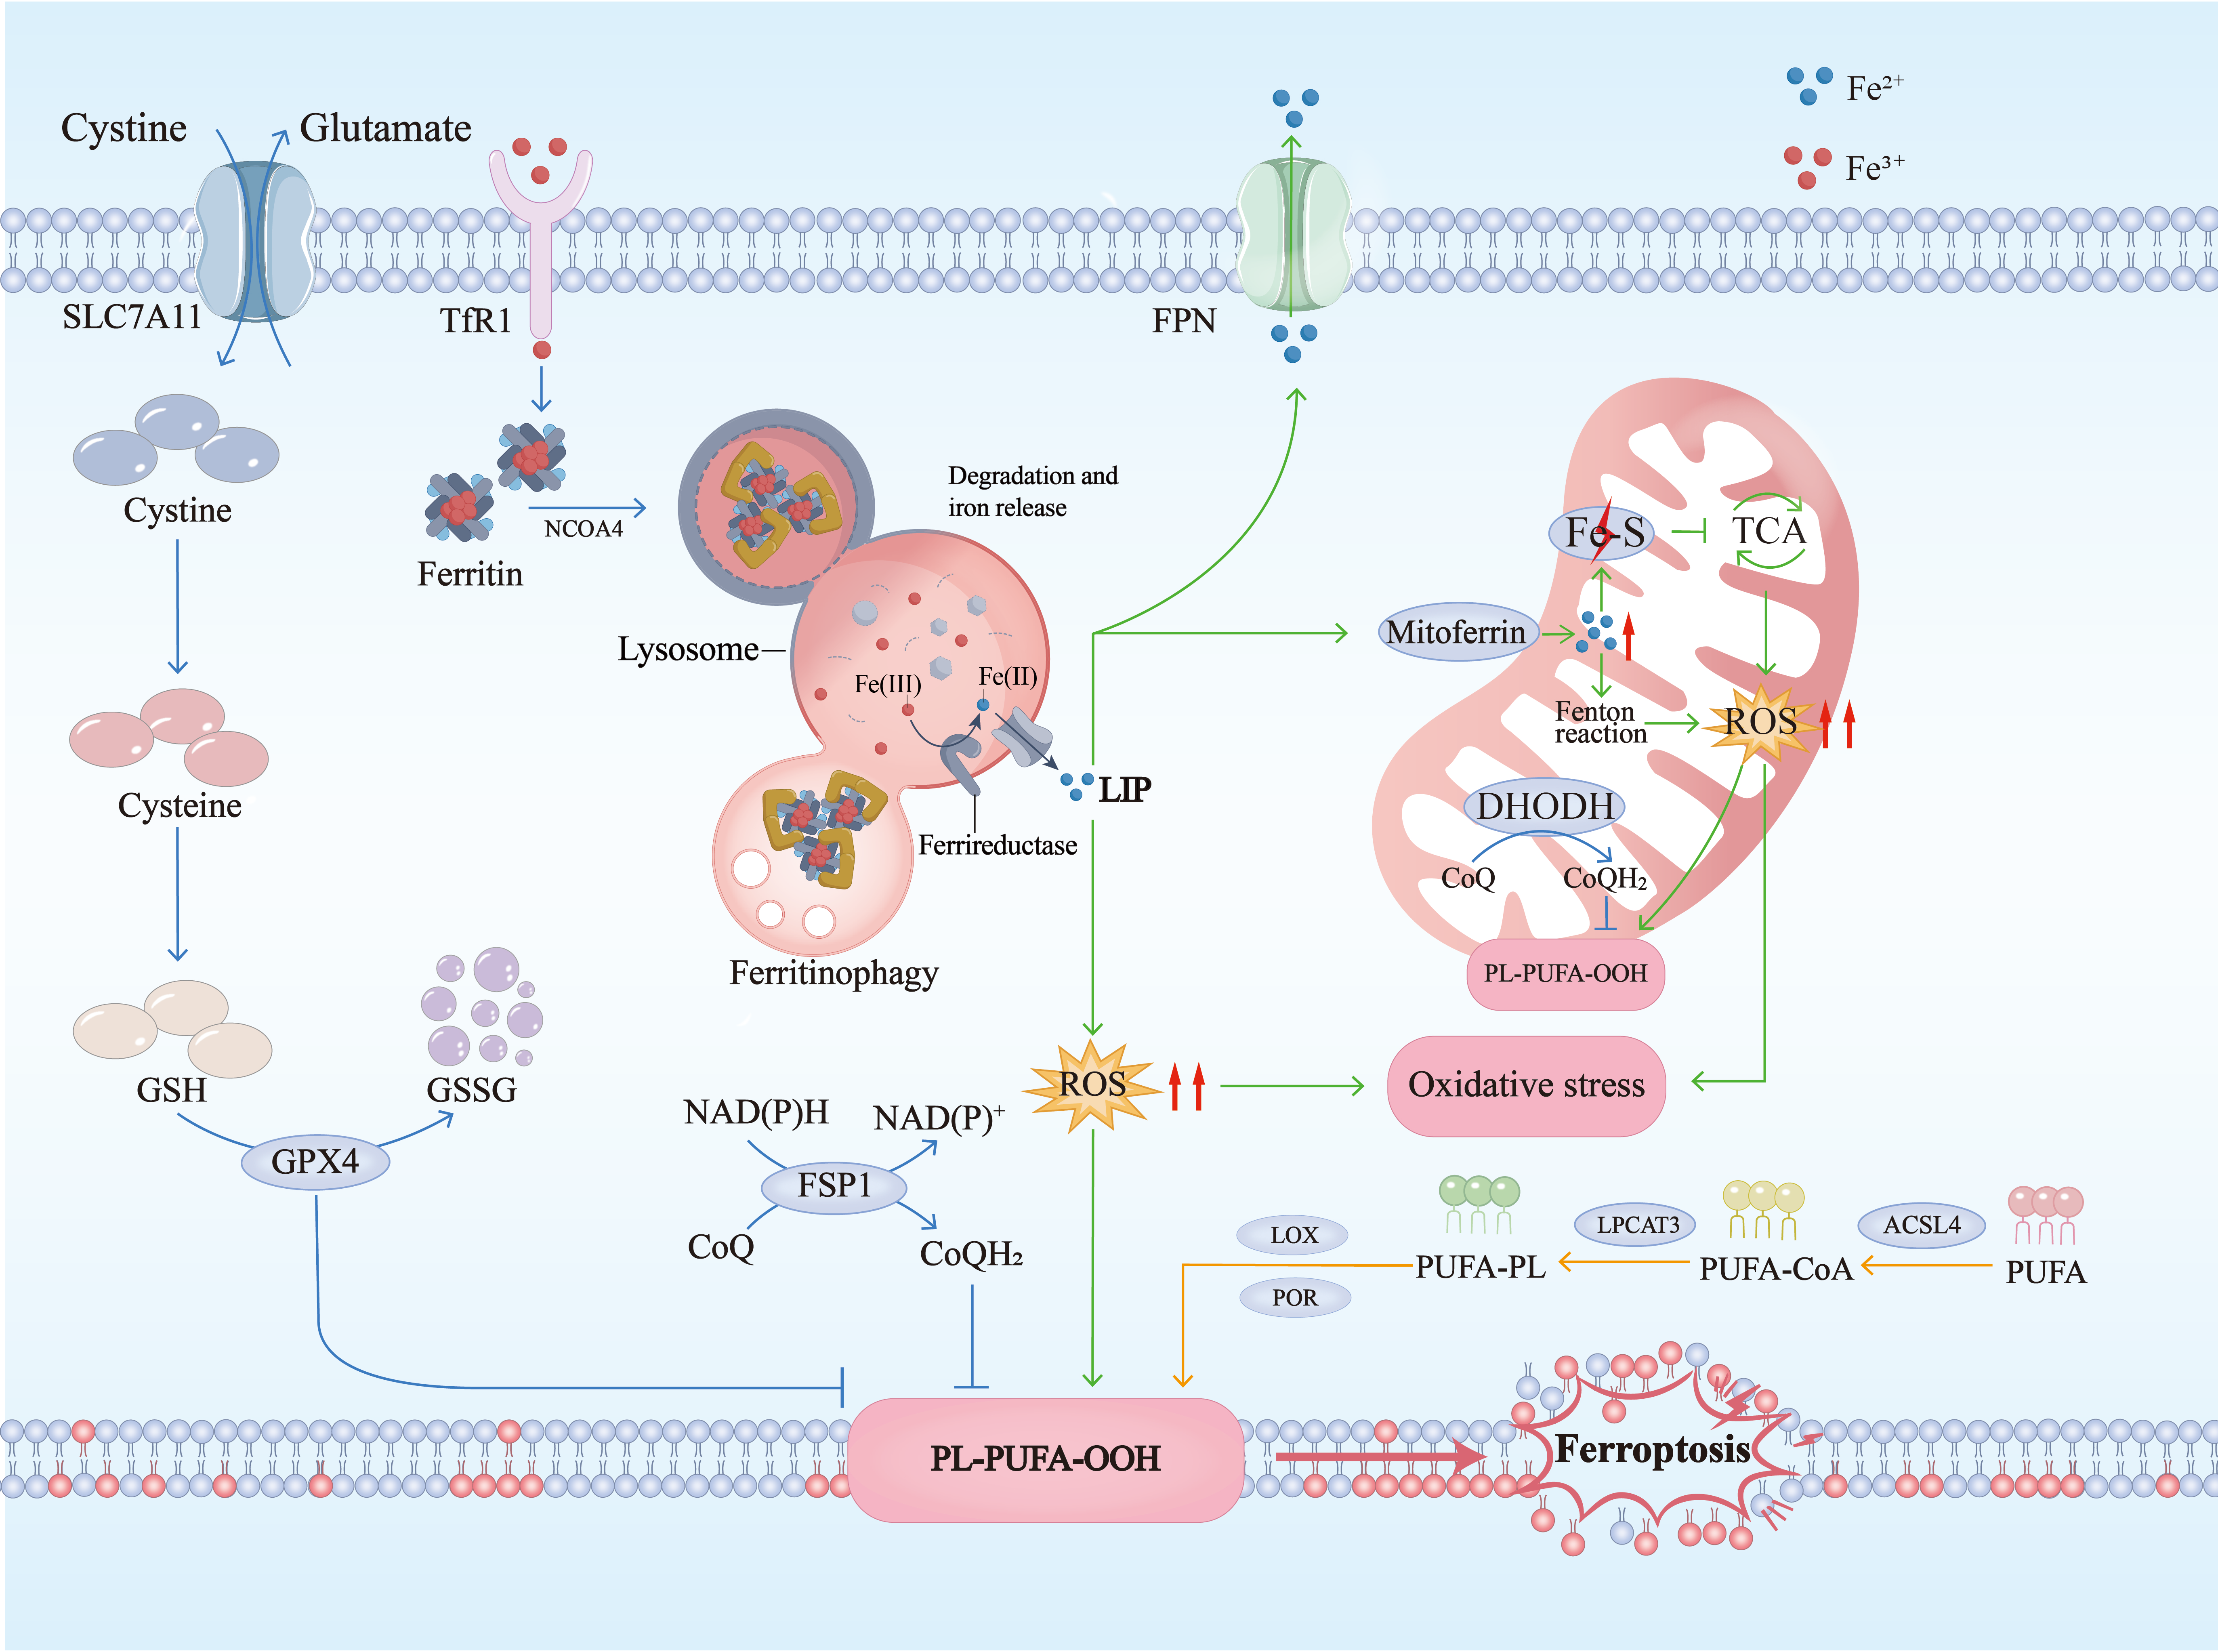
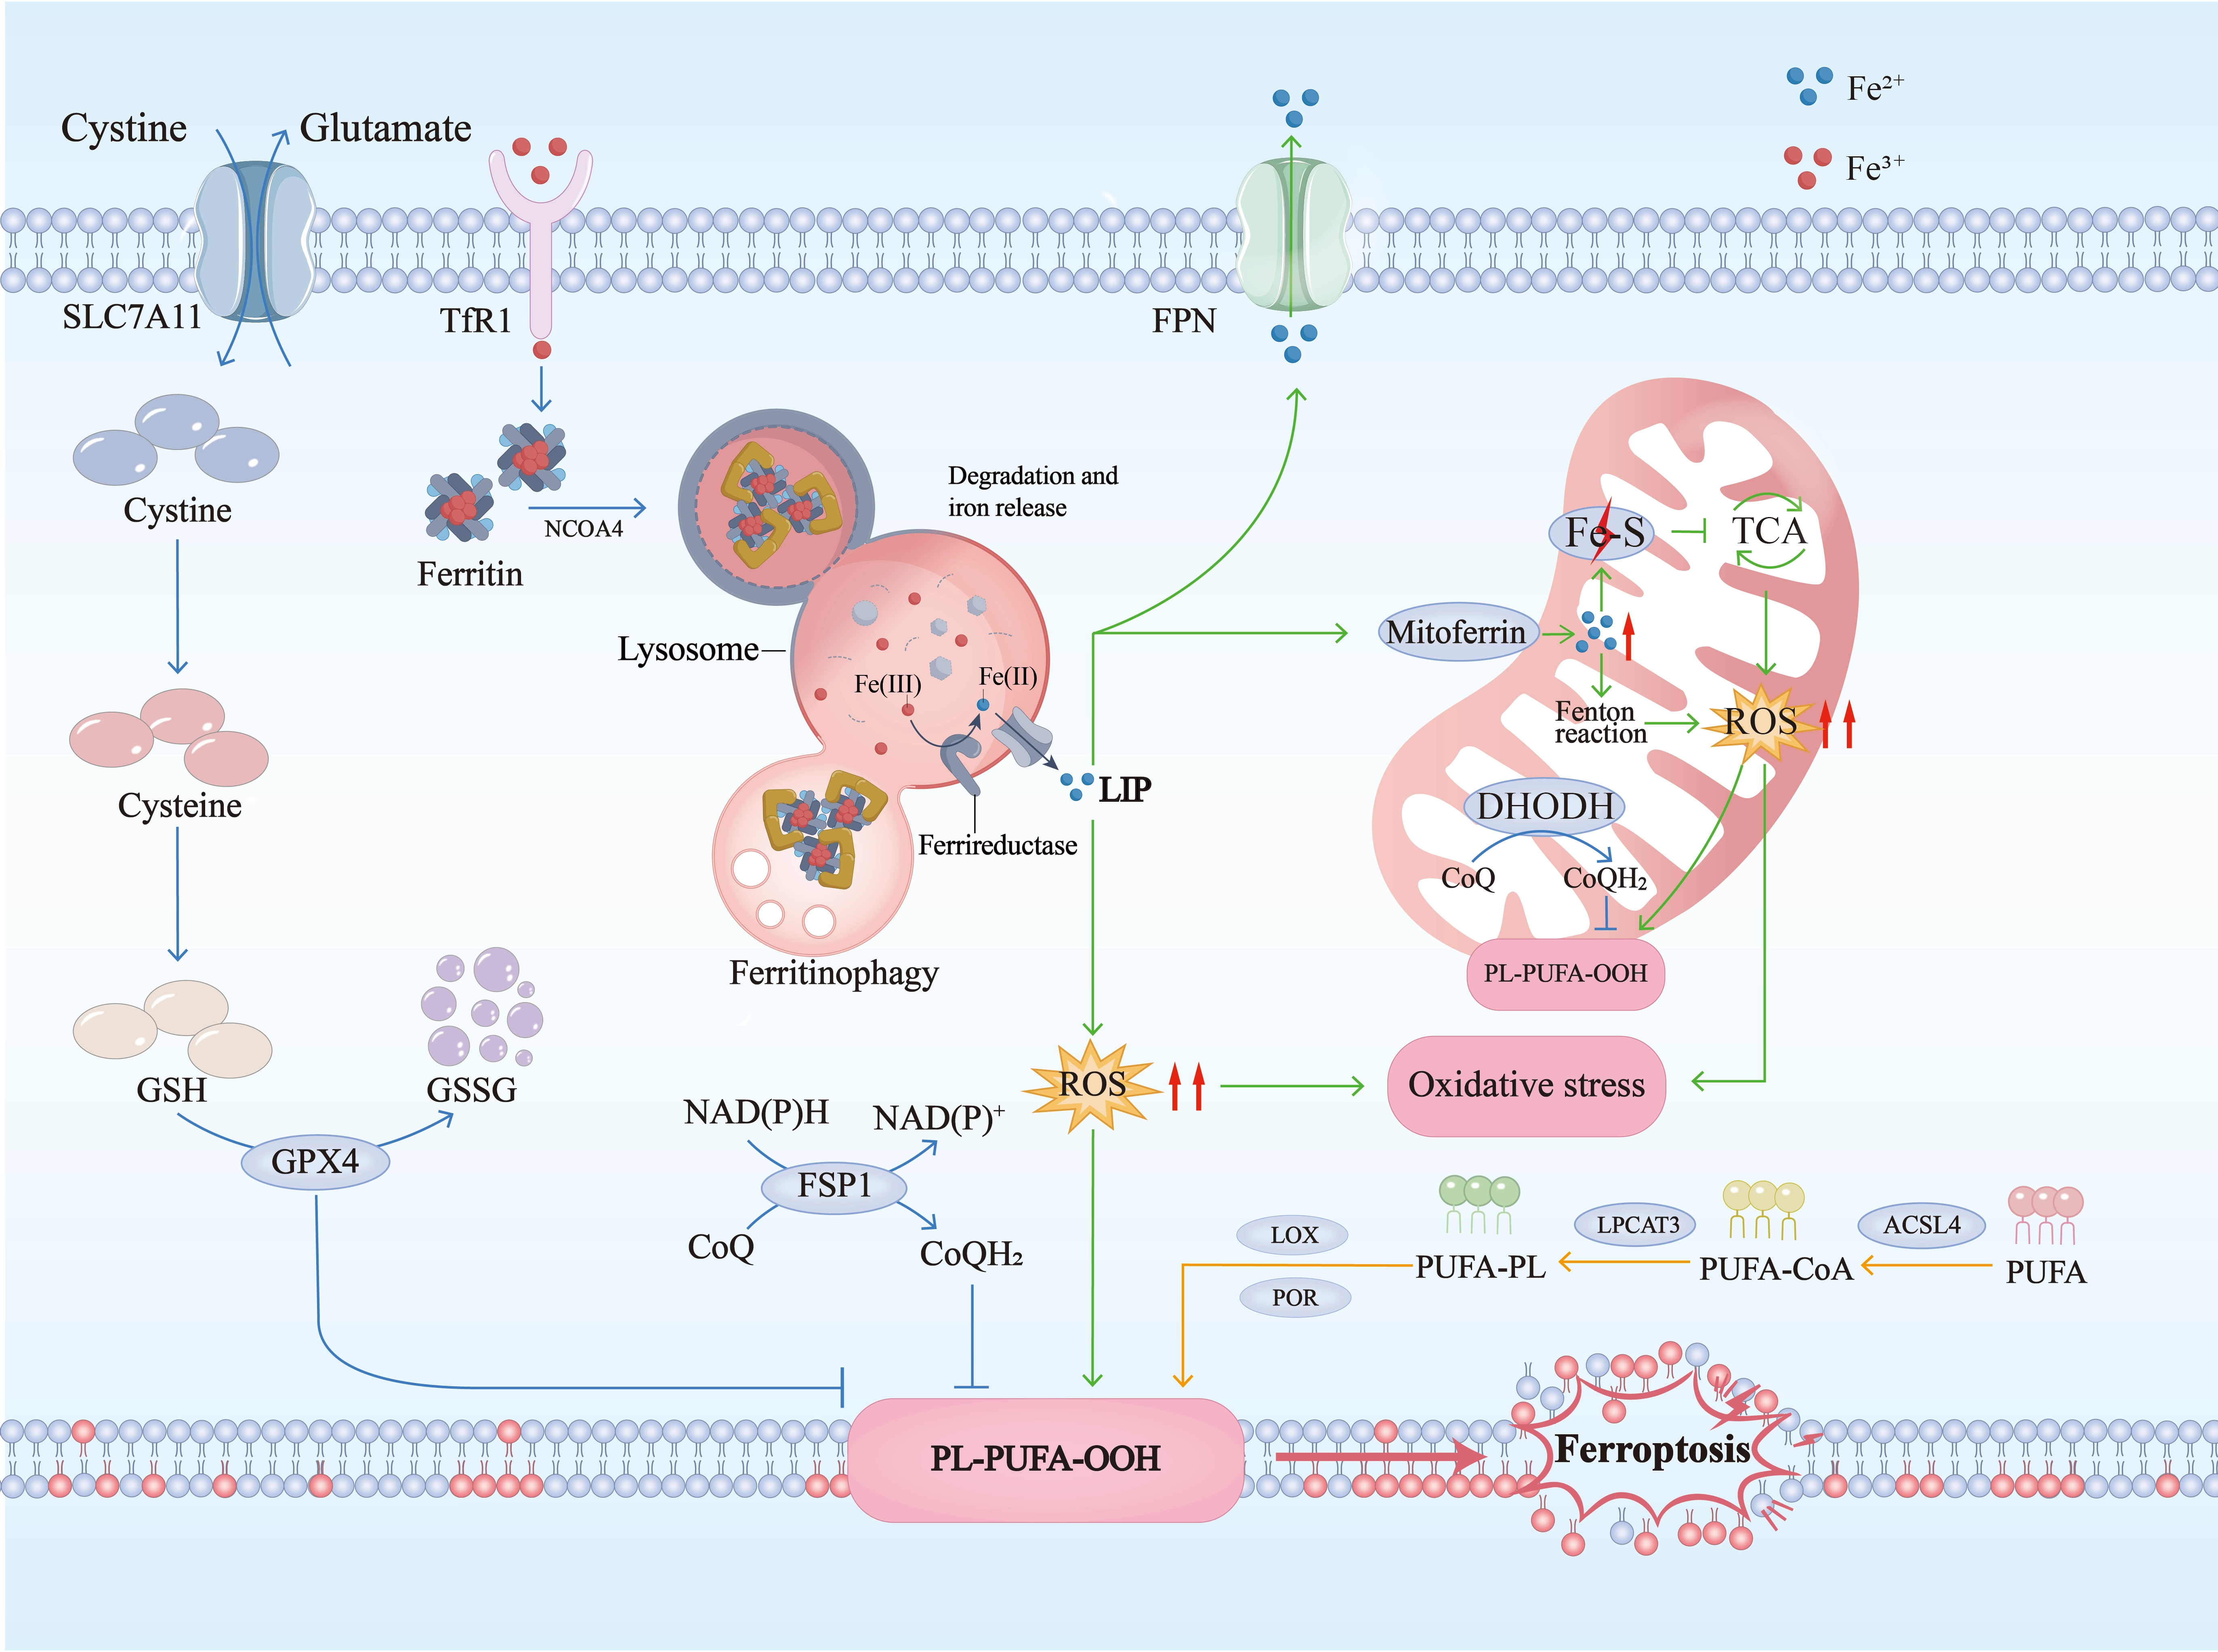
Figure 1. Diagram of the major mechanisms regulating ferroptosis. The graphic was created using Adobe Illustrator. TfR1: transferrin receptor 1; PUFA: polyunsaturated fatty acid; LOX: lipoxygenases; LPCAT3: lysophosphatidylcholine acyltransferase 3; ACSL4: acyl-CoA synthetase long-chain family member 4; ROS: reactive oxygen species; FSP1: ferroptosis suppressor protein 1; GPX4: glutathione peroxidase 4; GSH: glutathione; GSSG: oxidized glutathione; SLC7A11: solute carrier family 7 member 11; NADPH: nicotinamide adenine dinucleotide phosphate; LIP: labile iron pool; DHODH: dihydroorotate dehydrogenase; NCOA4: nuclear receptor coactivator 4; FPN: ferroportin; CoQ: coenzyme Q; POR: cytochrome P450 oxidoreductase; TCA: tricarboxylic acid; CoQH2: ubiquinol.
The solute carrier family 7 member 11 (SLC7A11)-GSH-GPX4 axis is a critical pathway for suppressing ferroptosis. SLC7A11 mediates the import of cystine from the extracellular milieu, which is essential for GSH synthesis. GPX4 utilizes GSH to catalyze the reduction of lipid hydroperoxides (LOOHs) to their corresponding lipid alcohols, and the enzymatic activity of GPX4 is directly contingent upon intracellular GSH levels[14,15]. Classic small-molecule ferroptosis inducers, such as erastin and RSL3, exert their effects by inhibiting SLC7A11 and GPX4, respectively. In addition, there are several parallel antioxidant defense lines: FSP1 scavenges lipid peroxyl radicals by reducing coenzyme Q10 (CoQ10) to ubiquinol[16]; dihydroorotate dehydrogenase (DHODH) in mitochondria inhibits ferroptosis by reducing CoQ to ubiquinol (CoQH2) in parallel with GPX4 in the mitochondrial matrix[17].
Notably, Mishima et al. reported that DHODH inhibitors sensitize cancer cells to ferroptosis primarily by inhibiting FSP1 rather than DHODH, and that cytosolic GPX4 expression in cancer cells far exceeds that of mitochondrial matrix or nuclear matrix GPX4[18]. At the heart of this controversy lies a fundamental question: whether the ferroptosis-sensitizing effect of DHODH inhibitors arises from direct blockade of DHODH enzymatic activity or from off-target inhibition of FSP1. Should the latter prove to be the case, the status of DHODH as an independent ferroptosis defense axis would warrant critical reappraisal, and experimental findings obtained with DHODH inhibitors would need to be interpreted with due consideration of their nonspecific interference with FSP1. Furthermore, Mao et al. proposed a compartmentalization model in which cytosolic GPX4-FSP1 and mitochondrial GPX4-DHODH constitute two spatially segregated defense systems that clear lipid peroxides in the non-mitochondrial and mitochondrial compartments, respectively[19]. This model suggests that ferroptosis is not the simple sum of several independent pathways, but rather a highly redundant network that is precisely orchestrated by subcellular compartmentalization. Accordingly, the focus of ferroptosis research has shifted from the identification of novel regulatory factors toward the elucidation of compartment-specific regulatory mechanisms. The functional characterization of mitochondrial complex I (MCI) exemplifies this trend. MCI suppresses ferroptosis by maintaining the mitochondrial CoQH2 pool, and this protective effect can be rescued by mitochondria-targeted, but not cytosolic, GPX4 or FSP1, functionally demonstrating that defense components from distinct compartments are non-interchangeable and operate within defined spatial jurisdictions[20].
Collectively, ferroptosis is a programmed death driven by multiple regulatory networks. These key mechanisms reveal the dynamic coupling between cellular metabolic state and antioxidant capacity. Emerging evidence shows that ferroptosis can serve as an important theoretical framework to explain tumor adaptability, biofilm damage, and oxidative stress-related disease[21]. Therefore, continued in-depth understanding of its mechanism will help to establish a more accurate biomarker system and stratified intervention strategies, and provide key support for new drug development and multimodal combination therapy.
3. Interplay Between Ferroptosis and Oxidative Stress
Oxidative stress, defined as an imbalance between ROS production and cellular antioxidant defense systems, is a central driver of ferroptosis[22,23]. Elucidating the crosstalk between these processes is critical for unraveling the regulatory networks governing ferroptosis and offers new avenues for therapeutic intervention in cancer.
3.1 The vicious cycle of lipid peroxidation and iron metabolism
Lipid peroxidation represents one of the most intense manifestations of oxidative stress. In ferroptosis, arachidonoyl/adrenoyl-phosphatidylethanolamine (AA/AdA-PE) is oxidized by LOX or by hydroxyl radicals (·OH) generated via the Fenton reaction, producing PUFA-OOH. This process is essentially the propagation of a free radical chain reaction. The level of oxidative stress directly determines the initiation rate and propagation distance of the chain reaction. In the presence of iron catalysis, ROS react with PUFAs to generate PUFA-OOHs, thereby participating in Fenton-like reactions[24]. Moreover, lipid peroxidation products can act as signaling molecules to modulate antioxidant pathways, establishing feedback regulation. Chen et al. demonstrated that 4-hydroxynonenal (4-HNE) forms adducts with Kelch-like ECH-associated protein 1 (KEAP1), destabilizing the NRF2-KEAP1 complex and promoting NRF2-driven transcription of TrxR1, thereby protecting PC12 cells from impending oxidative stress[25].
Iron metabolism and oxidative stress establish a bidirectional amplification loop. Fe2+ in the intracellular labile iron pool (LIP) converts relatively mild H2O2 into highly reactive ·OH via the Fenton reaction, which serves as the key oxidizing species that initiates lipid peroxidation. Meanwhile, heme oxygenase 1 (HO-1) is induced by NRF2 under oxidative stress, accelerating heme degradation and releasing Fe2+ to further fuel the Fenton reaction[26]. Collectively, these interconnected mechanisms create a self-reinforcing cycle between ferroptosis and oxidative stress.
3.2 Interactions between organelles
Mitochondria serve as the central hub of intracellular iron metabolism, taking up iron via mitochondrial ferritin to support iron-sulfur cluster assembly and heme biosynthesis, both of which are essential for the integrity of respiratory chain complexes[27-29]. When iron-sulfur cluster assembly is compromised, electron leakage from the electron transport chain increases markedly, promoting the overproduction of superoxide and other ROS[30]. Concomitantly, excessive free iron accumulating within mitochondria catalyzes the generation of hydroxyl radicals through the Fenton reaction, further amplifying ROS levels and oxidative stress[31]. Notably, the mitochondrial membrane is enriched with cardiolipin bearing PUFA chains, rendering it a preferential target for lipid peroxidation under conditions of ROS overload and iron availability. Therefore, mitochondria simultaneously regulate the sensitivity to oxidative stress and ferroptosis through iron metabolism regulation, ROS generation, and membrane lipid composition.
Recent studies have demonstrated that optic atrophy 1 (OPA1) maintains mitochondrial homeostasis and function, thereby modulating both mitochondrial ROS generation and activating transcription factor 4 (ATF4)-mediated integrated stress responses, ultimately exerting bidirectional control over ferroptosis sensitivity[32]. In human astrocytes, overexpression of nicotinamide adenine dinucleotide phosphate (NADPH) oxidase 4 (NOX4) impairs mitochondrial metabolism and drives excessive mitochondrial ROS production, thereby promoting oxidative stress and lipid peroxidation[33]. These findings support that mitochondrial dysfunction leads to an energy crisis, triggers ferroptosis, and alters the cell’s redox status.
The endoplasmic reticulum (ER) is enriched with AA/AdA-PE, which serve as the core substrates for lipid peroxidation during ferroptosis[34]. The ER membrane-localized enzymes ACSL4 and LPCAT3 coordinately drive the biosynthesis of AA/AdA-PE, effectively establishing the ER as a platform for generating lipid peroxidation substrates in ferroptosis[35-37]. Under oxidative stress, misfolded proteins accumulate abundantly within the ER lumen, triggering ER stress and subsequently activating the eukaryotic translation initiation factor 2A (eIF2α)/ATF4 signaling axis to modulate ferroptosis[38,39]. Moreover, recent evidence has revealed that the ER-resident protein stimulator of interferon genes (STING) can translocate to mitochondria, where it interacts with the outer mitochondrial membrane fusion proteins mitofusin 1 and 2 (MFN1/2) to promote mitochondrial fusion. This process is accompanied by the generation of substantial amounts of ROS and lipid peroxides, thereby further exacerbating cellular oxidative stress and ferroptosis[40]. Collectively, the ER serves as a pivotal hub in both the initiation and amplification of ferroptosis through substrate provision, stress signaling transduction, and inter-organellar crosstalk.
Lysosomes contribute to ferroptosis regulation through multiple selective autophagy pathways, primarily including ferritinophagy, lipophagy, mitophagy, and clockophagy[41]. Specifically, ferritinophagy is mediated by the receptor NCOA4, which targets ferritin for degradation and releases substantial amounts of free iron, thereby supplying the iron source for the Fenton reaction[42]. Lipophagy degrades lipid droplets to liberate free fatty acids, expanding the substrate pool for lipid peroxidation[43]. Mitophagy, while serving to eliminate damaged mitochondria and maintain homeostasis, paradoxically exacerbates ROS leakage when excessively activated[44]. Clockophagy degrades the core circadian protein aryl hydrocarbon receptor nuclear translocator-like (ARNTL/BMAL1), relieving its transcriptional repression of lipid peroxidation-related genes and thereby indirectly promoting ferroptosis[45]. On the other hand, hydroxyl radicals generated under oxidative stress can directly attack the lysosomal membrane, inducing lysosomal membrane permeabilization, which results in the massive leakage of intraluminal hydrolytic enzymes and labile iron into the cytoplasm. This event not only amplifies the Fenton reaction through iron release but also, via hydrolytic enzyme-mediated damage to cellular components, forms a vicious positive feedback loop with lipid peroxidation that further propagates the ferroptotic signal[46]. Taken together, the lysosome functions both as a supply hub for free iron and lipid substrates required for ferroptosis and as an execution platform that accelerates ferroptotic progression following oxidative damage-driven membrane permeabilization.
3.3 Antioxidant network
NRF2 is a master transcription factor central to the cellular oxidative stress response, and its activity is intimately linked to the regulation of ferroptosis. Under physiological conditions or moderate stress, NRF2 dissociates from KEAP1 and translocates into the nucleus, where it drives the transcription of a battery of antioxidant genes, including SLC7A11, GPX4, FSP1, HO-1, and NADPH quinone dehydrogenase 1 (NQO1)[47,48]. These target genes collaboratively establish a multi-layered and mutually complementary defense network against ferroptosis. Given the pivotal role of NRF2 in ferroptosis defense, any impairment of its activity directly compromises the cellular antioxidant capacity. A recent study showed that ethyl carbamate, present in fermented foods or beverages, inactivates NRF2 in hepatocytes, suppressing the expression of SLC7A11 and enzymes catalyzed by glutamate cysteine ligase catalytic subunit (GCLC) and reducing GSH synthesis, ultimately leading to oxidative stress and ferroptosis[49]. In striking contrast, Zhang et al. found that H2S supplementation promotes nuclear translocation of NRF2 and activates the SLC7A11/GSH/GPX4 antioxidant pathway, thereby alleviating doxorubicin-induced ferroptosis and cardiac injury in mice[50]. These two studies, approaching from the opposing directions of inhibition and activation, jointly corroborate the critical role of NRF2 as a regulatory switch in ferroptosis.
Notably, NRF2 activation is not entirely dependent on the classical oxidative modification-KEAP1 dissociation paradigm. BNIP3-mediated mitophagy can trigger the accumulation of P62/SQSTM1, which competitively binds KEAP1 and liberates NRF2 through a non-canonical mechanism, thereby modulating FTH1, HO-1, and the DHODH/FSP1-CoQ10-NADH axis to maintain both iron and redox homeostasis, ultimately conferring resistance to ferroptosis[51]. This mechanism reveals a deep coupling between selective autophagy and the antioxidant transcriptional program, which jointly governs cellular sensitivity to ferroptosis.
4. Differential Ferroptosis Sensitivity in the Tumor Microenvironment
The interactive regulation of oxidative stress and ferroptosis manifests in the TME primarily as marked heterogeneity in ferroptosis sensitivity across distinct cell populations. The TME is a space of profound metabolic and redox imbalance in which nutrient deprivation, hypoxia, abundant metabolic waste, and immunosuppressive cells collectively sustain persistently elevated levels of ROS. Meanwhile, oxidative stress is a “double-edged sword” in the TME. It is both a deleterious stressor for immune cell function and a critical driver of immune cell activation and antitumor responses, with the balance between ROS production and antioxidant defense being the decisive factor.
Faced with the same oxidative pressure, cancer cells evolve an “adaptive antioxidant” program during prolonged exposure that enables them to evade ferroptosis even against elevated ROS, constituting the core of ferroptosis resistance. Cancer cells finely tune ROS generation and clearance to maintain ROS within a “pro-proliferative yet non-lethal” dynamic range. Early in tumorigenesis, oncogene-induced oxidative stress triggers an adaptive defense centered on NRF2-upregulated antioxidant genes, accompanied by enhanced NADPH production via the pentose phosphate pathway[52]. When ROS generation overwhelms antioxidant capacity, cancer cells are pushed toward ferroptosis. For example, solanine induces mitochondrial damage and downregulates the SLC7A11-GPX4 antioxidant axis in lung adenocarcinoma cells, leading to ROS accumulation that ultimately triggers ferroptosis[53].
Notably, the ferroptosis sensitivity of tumor cells is determined not solely by their intrinsic antioxidant capacity but also by active regulation from other cells within the microenvironment. Activated CD8+ T cells secrete interferon-γ (IFN-γ), which downregulates SLC7A11 expression in tumor cells via the JAK-STAT1 signaling pathway, ultimately triggering ferroptosis[54]. IFN-γ and arachidonic acid released by T cells promote ACSL4-dependent ferroptosis in tumor cells[55]. This mechanism is critical for enhanced sensitivity to immunotherapy and chemotherapy[54,56]. However, stromal elements within the TME, particularly cancer-associated fibroblasts (CAFs), form a protective barrier against immune surveillance. CAFs shield tumor cells from ferroptosis through metabolic crosstalk and paracrine signaling. In pancreatic cancer, CAFs directly supply cysteine and other metabolites to replenish the cystine pool in cancer cells, thereby bolstering their antioxidant defenses[57]. In brief, the dynamic interplay between CD8+ T cell-mediated “attack” and CAF-mediated “protection”, together with the intrinsic adaptive antioxidant capacity of cancer cells, collectively governs the ferroptotic fate of tumor cells in the TME.
Unlike cancer cells, immune cells, despite possessing their own antioxidant systems, lack such evolutionarily acquired “adaptive antioxidant” capacity and are therefore more vulnerable to ferroptosis within the same TME. Persistently high levels of ROS and lipid peroxidation in the TME first strike the effector cells responsible for immune surveillance, most notably natural killer (NK) cells. In ovarian cancer models, oxidative stress associated with lipid peroxidation directly impairs glucose metabolism, representing the central mechanism underlying NK cell dysfunction. NK cells cocultured with ascites from patients with ovarian cancer exhibit a dysfunctional phenotype accompanied by increased lipid peroxidation and enhanced ferroptosis. Morphologically, tumor-associated NK cells display changes consistent with ferroptosis, including plasma membrane rounding and shrinkage and reduced mitochondrial size[58].
For T cells, moderate levels of ROS are required to sustain proliferation and effector function. In the TME, however, as intracellular and microenvironmental ROS rise without a corresponding reinforcement of redox-balancing mechanisms, T cells enter an oxidative stress state that drives an exhaustion phenotype characterized by reduced inflammatory cytokine production, elevated inhibitory receptors (PD-1/TIM-3/LAG-3), and upregulation of the exhaustion-associated transcription factor TOX[59,60]. Meanwhile, the expression of GPX4 is relatively low in T cells, rendering them prone to ferroptosis in the TME[61]. Nevertheless, susceptibility to ferroptosis differs among T cell subsets. The Tc9 subset exhibits unique resistance to ferroptosis via IL-9/signal transducer and activator of transcription 3 (STAT3)-mediated upregulation of carnitine palmitoyltransferase I (CPT1A)[62]. As a rate-limiting enzyme in mitochondrial fatty acid β-oxidation, upregulation of CPT1A may reduce the accumulation of lipid peroxidation substrates by directing fatty acids to oxidative breakdown. Collectively, these findings indicate that the sensitivity of distinct T cell subsets to ferroptosis in the TME is heterogeneous, suggesting that oxidative stress and ferroptosis pressure may act as a selective filter that reshapes the composition and function of effector T cells.
Pathologically activated neutrophils, termed myeloid-derived suppressor cells (MDSCs), are major negative regulators of antitumor immunity. MDSCs activate the NRF2 antioxidant program through distinct pathways to counteract oxidative stress in the TME, which confers enhanced metabolic activity, increased glucose uptake, augmented mitochondrial mass, and elevated mammalian target of rapamycin (mTOR) phosphorylation, thereby promoting their expansion[63]. However, tumor-derived ROS induce tumor necrosis factor-α–induced protein 8-like 2 (TIPE2) expression in MDSCs, and hypoxia mediates GPX4 downregulation, which confers ferroptosis sensitivity on MDSCs by altering phospholipid composition and triggering lipid peroxidation[64,65].
The sensitivity of macrophages to ferroptosis varies according to their polarization state. M1 macrophages acquire resistance to ferroptosis through genetic or pharmacologic depletion/inactivation of inducible nitric oxide synthase, whereas NO· donors empower resistance of M2 cells to ferroptosis[66]. Such differences imply that ferroptosis acts as a selective filter in the TME: pro-tumoral M2 subsets are more readily eliminated or reprogrammed, whereas antitumoral M1 subsets are preserved, thereby remodeling macrophage composition.
Taken together, cancer cells resist ferroptosis by relying on “adaptive antioxidant” mechanisms and CAF-mediated protection, whereas the same magnitude of ROS more readily drives immune cells toward oxidative damage and ferroptosis. Therefore, locally increasing ROS or targeting antioxidant pathways such as GPX4 in cancer cells represents a promising combination strategy that eliminates tumors while counteracting immune suppression. It should be emphasized that ferroptosis regulation is inherently double-edged. Inducing ferroptosis in tumor cells necessitates careful evaluation of its potential toxicity to immune cells such as NK cells. The optimal intervention would induce ferroptosis in cancer cells while preserving immune cells, achieving an ideal balance between ROS generation and antioxidant defense.
5. Ferroptosis and Oxidative Stress Drive Remodeling of Tumor Microenvironment
Ferroptosis and oxidative stress engage in a complex bidirectional regulatory network within the TME. The characteristic accumulation of iron and lipid peroxides during ferroptosis forms a feedback loop with ROS generated by oxidative stress, further amplifying the oxidative state of the TME. This vicious cycle shapes the composition and function of the TME through multiple mechanisms (Figure 2), and understanding this crosstalk is critical for developing novel therapeutic strategies targeting the TME.
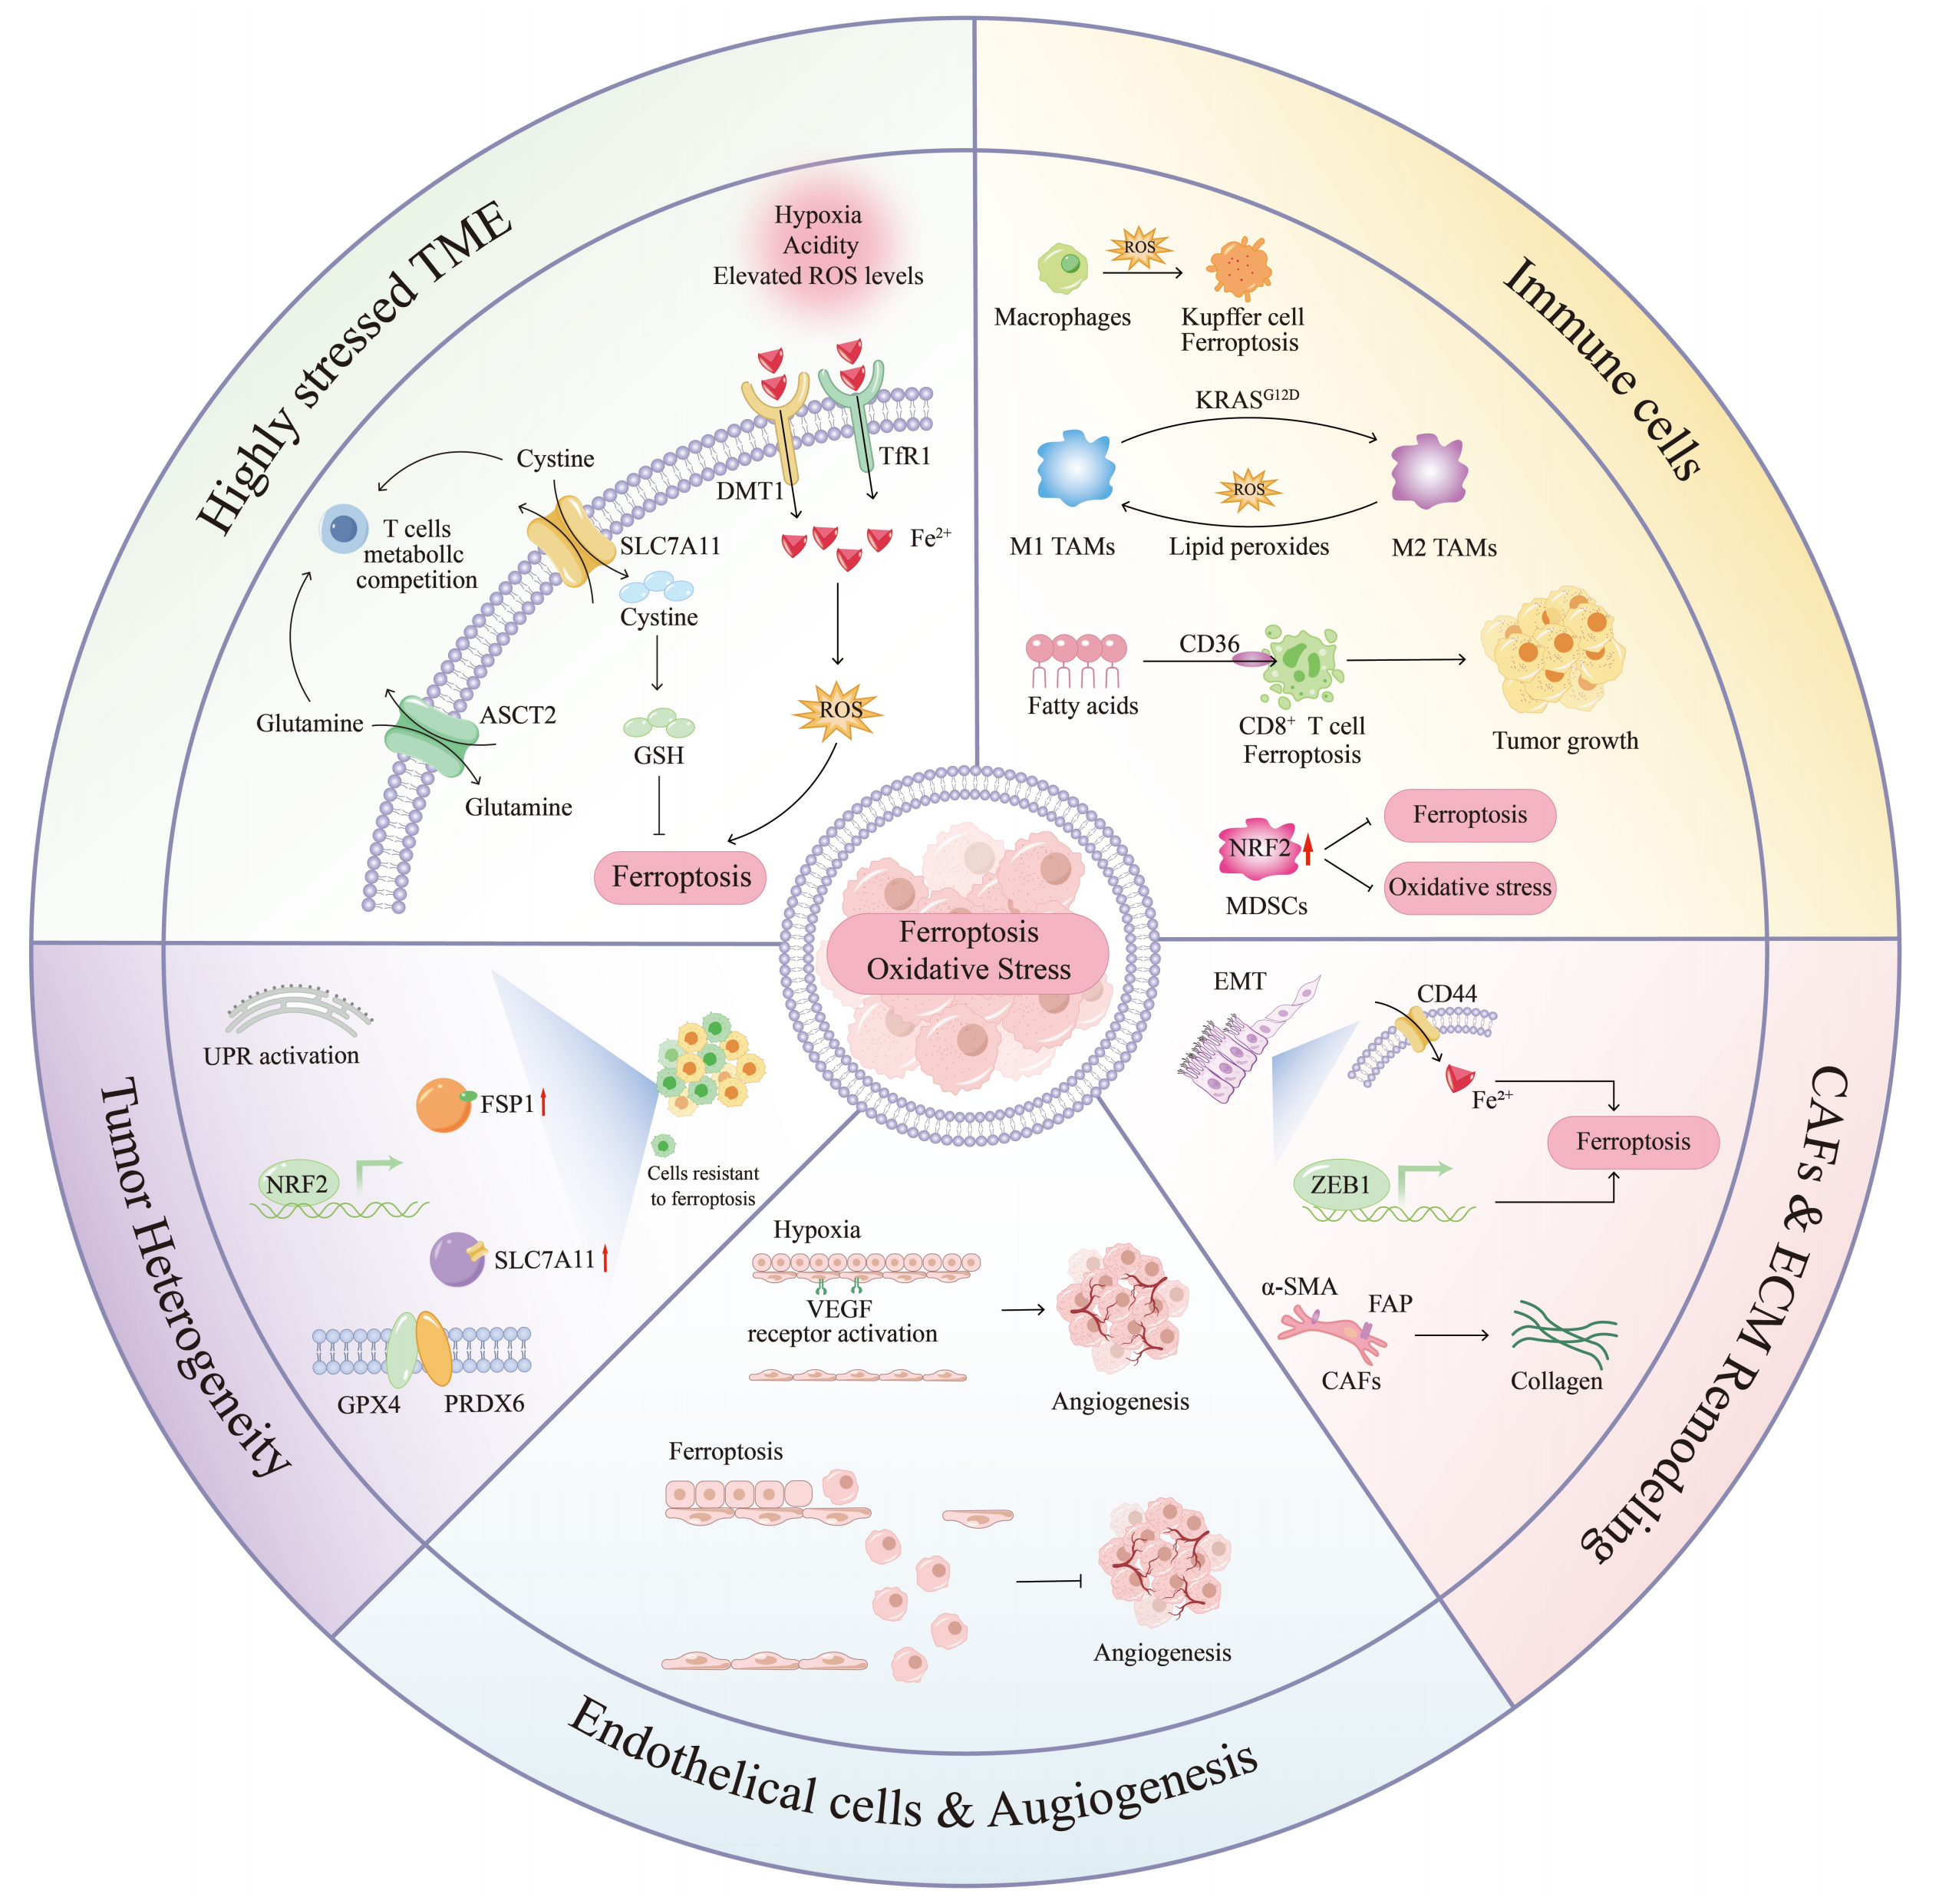
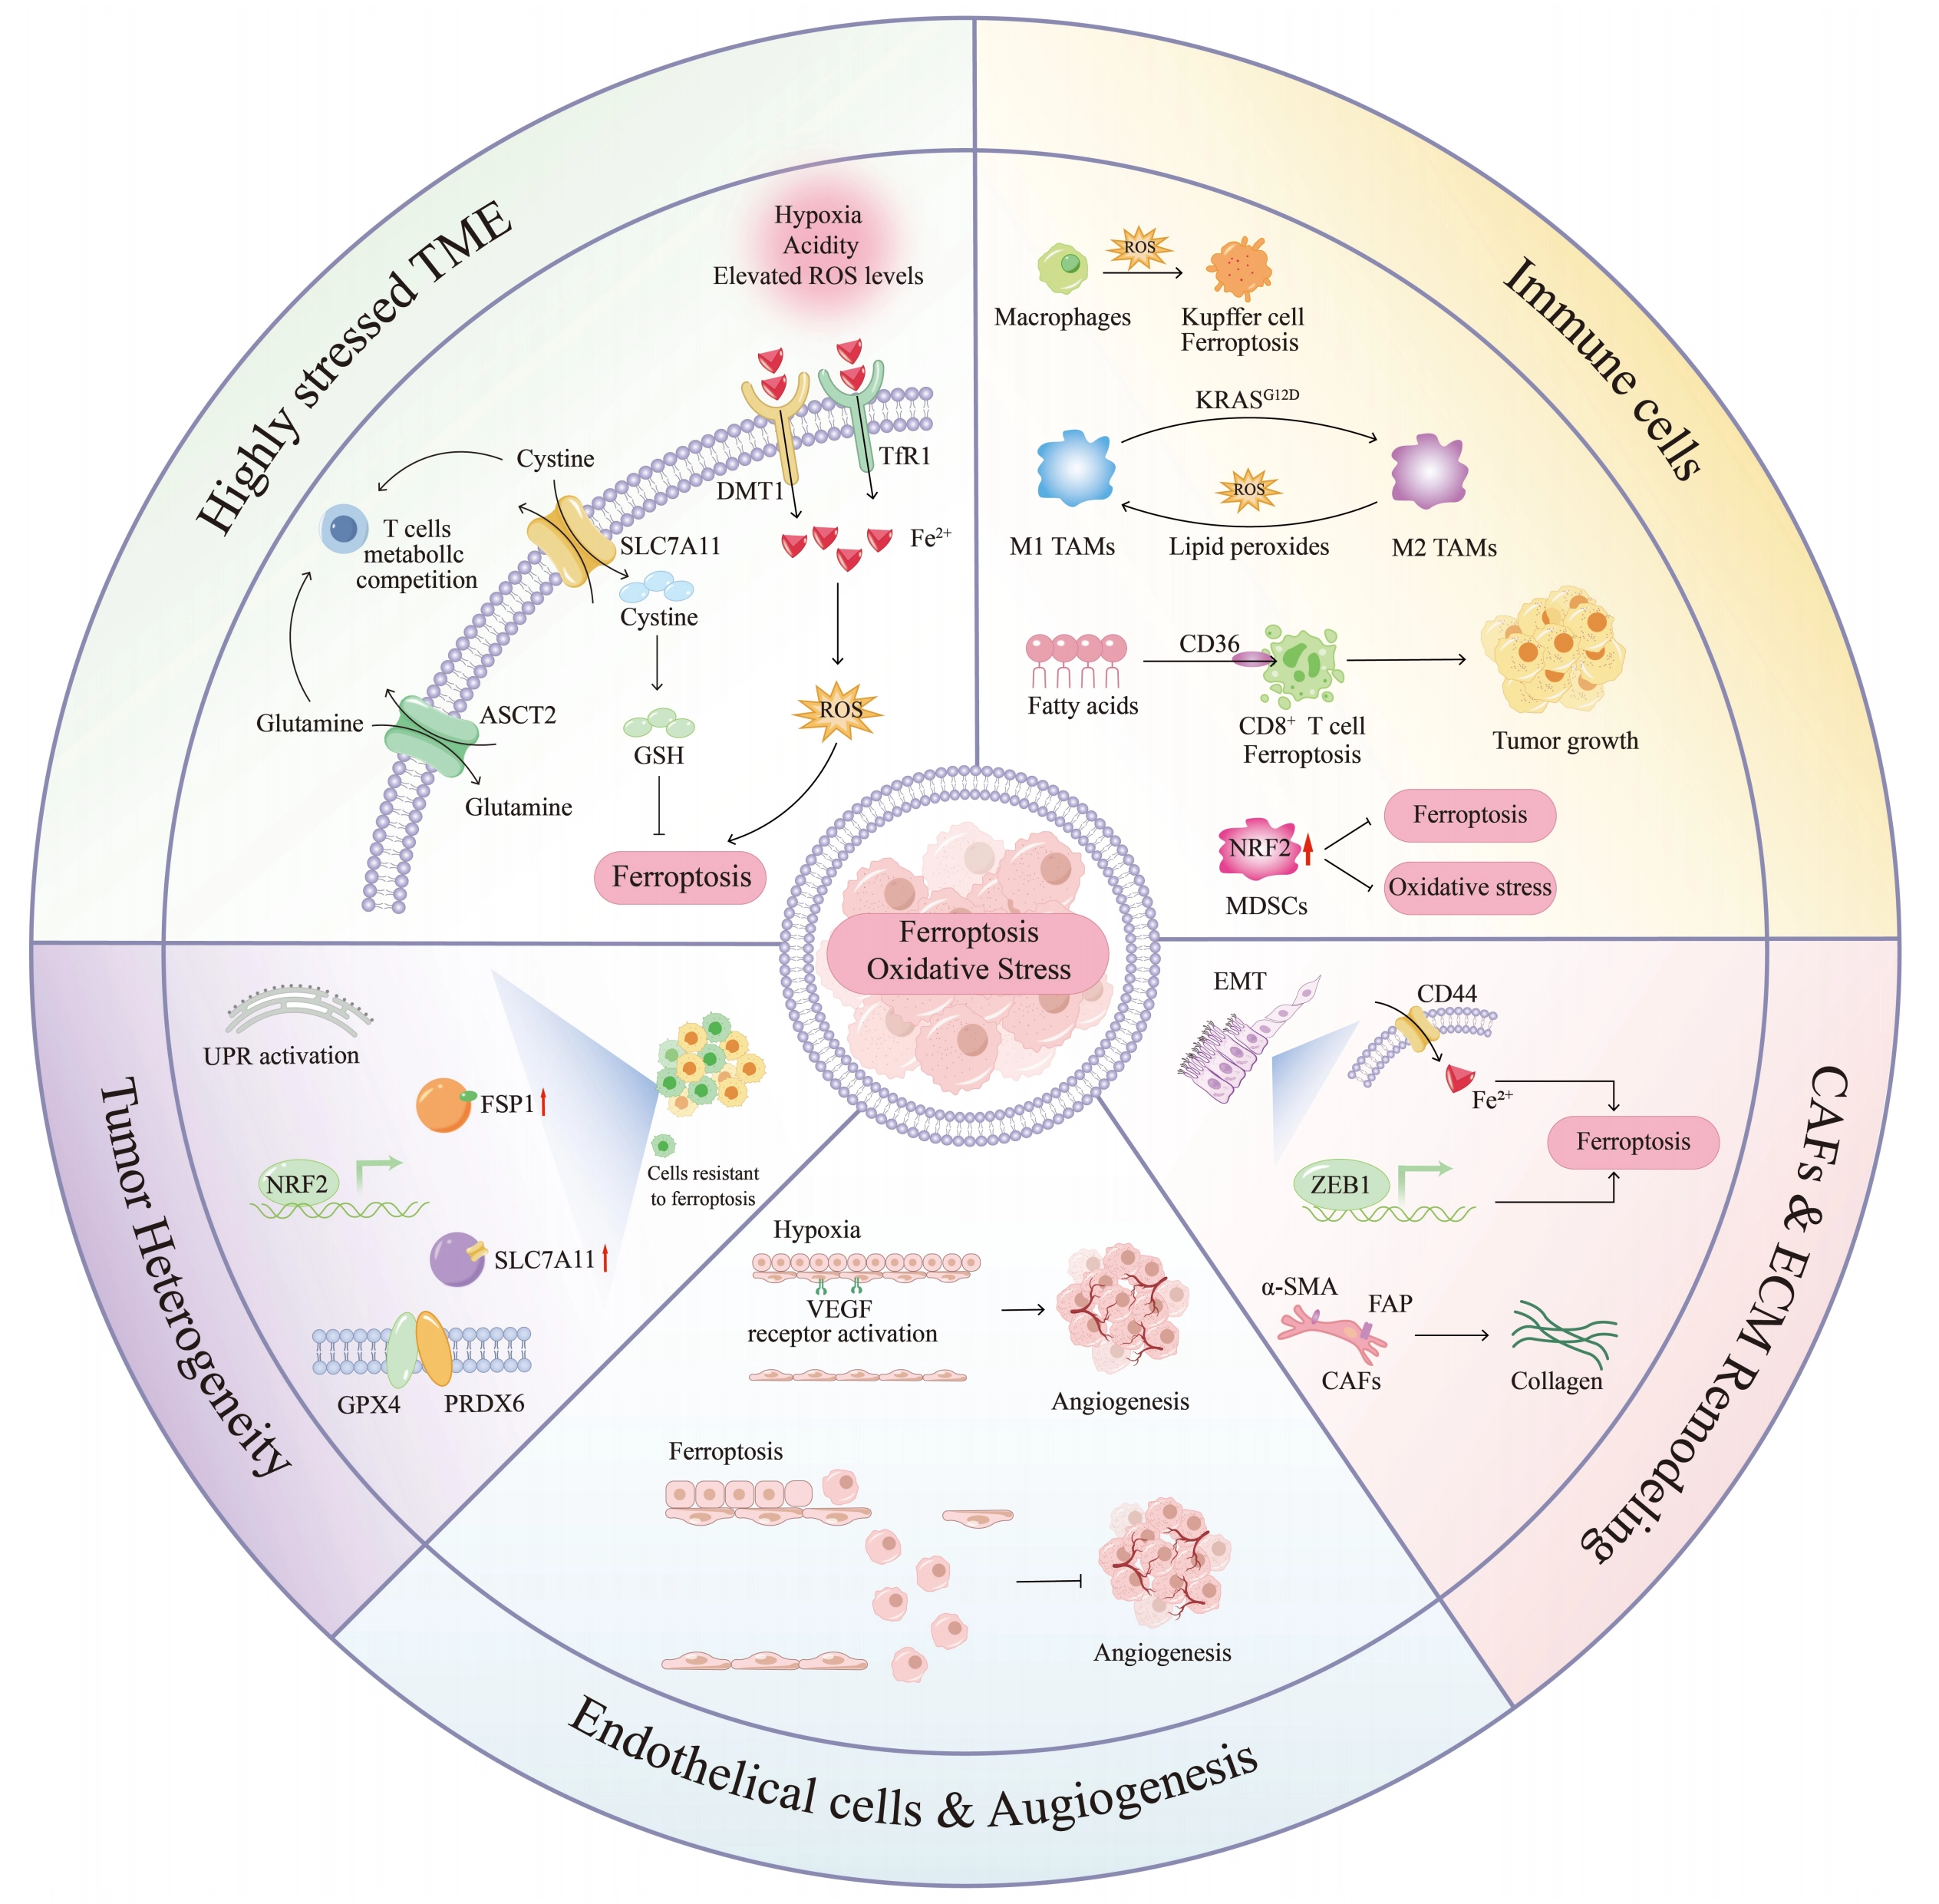
Figure 2. Graphs showing ferroptosis and oxidative stress remodeling of the TME. Ferroptosis and oxidative stress drive remodeling of the TME through five interconnected processes: generation of a highly stressed TME, remodeling of immune cells, CAFs activation and ECM remodeling, endothelial cell remodeling and angiogenesis, and increased tumor heterogeneity. The graphic was created using Adobe Illustrator. CAFs: cancer-associated fibroblasts; TME: tumor microenvironment; ECM: extracellular matrix; TfR1: transferrin receptor 1; SLC7A11: solute carrier family 7 member 11; DMT1: divalent metal transporter 1; GSH: glutathione; ROS: reactive oxygen species; NRF2: nuclear factor erythroid 2-related factor 2; FSP1: ferroptosis suppressor protein 1; GPX4: glutathione peroxidase 4; PRDX6: peroxiredoxin 6; EMT: epithelial-mesenchymal transition; α-SMA: alpha-smooth muscle actin; TAMs: tumor-associated macrophages; MDSCs: myeloid-derived suppressor cells; FAP: fibroblast activation protein; UPR: unfolded protein response; ASCT2: alanine, serine, cysteine-preferring transporter 2.
5.1 The highly stressed tumor microenvironment
The highly stressed TME concurrently promotes ferroptosis and oxidative stress through hypoxia, nutrient deprivation, and metabolic reprogramming[67]. Hypoxia-inducible factors (HIFs) are upregulated under hypoxic conditions and directly modulate iron metabolism-related gene expression, increasing intracellular iron load and susceptibility to lipid peroxidation[68,69]. Tumor cells in the highly stressed TME upregulate divalent metal transporter 1 (DMT1) and TfR1 to increase iron uptake, resulting in iron overload and enhanced Fenton reactions[70,71]. While activation of the NRF2 pathway helps maintain ROS homeostasis, persistent ferroptotic stress leads to GSH depletion and loss of GPX4 activity, exacerbating oxidative stress[72].
The interplay between ferroptosis and oxidative stress intensifies competition for antioxidants within the TME, with cystine and glutamine competition representing a central metabolic feature[73]. Tumor cells highly express SLC7A11 to import cystine for GSH synthesis, thereby suppressing ferroptosis[74]. This process places them in competition with immune cells such as myeloid-derived suppressor cells and antigen-presenting cells for cystine, depleting the extracellular cystine pool and impairing T cell activation[75]. Similarly, tumor cells outcompete T cells for glutamine, depriving them of essential nutrients and suppressing their effector functions[76]. This metabolic competition creates distinct metabolic stress states among different cellular subsets in the TME, not only dampening antitumor immunity but also fostering an immunosuppressive microenvironment that contributes to therapeutic resistance.
5.2 Immune cells
Oxidative stress and ferroptosis are deeply intertwined biological processes that collectively shape the fate and functional landscape of immune cells through intercellular signal transmission. Immune cells undergoing ferroptosis release regulatory signals into their surroundings. For example, neutrophil cytosolic factor 1 (NCF1)-mediated high ROS levels induce iron deposition and ferroptosis in Kupffer cells, promoting the infiltration of inflammatory monocyte-derived macrophages[77]. Pathologically activated neutrophils (PMNs), termed myeloid-derived suppressor cells (PMN-MDSCs) when undergoing ferroptosis, release lipid peroxides that directly constrain T cell activity, constituting a distinct immunosuppressive mechanism that ultimately promotes tumor growth[65]. In the TME of chemotherapy-resistant breast cancer, ferroptotic neutrophils effectively suppress the proliferation and cytolytic capacity of CTLs via PGE2, indoleamine 2,3-dioxygenase (IDO), and abundant peroxidized lipids, correlations that are associated with chemoresistance and poor prognosis in patients with breast cancer. CD4+ T cell subsets promote membrane-bound O-acyltransferase domain-containing 1 (MBOAT1) deficiency in neutrophils through IL1β release and IL1R1/nuclear factor kappa B (NF-κB) signaling and further sustain the persistence of ferroptotic neutrophils in the TME by secreting CXCL3, IL8, and S100A9[78].
Tumor cells release a variety of metabolites and damage-associated molecular patterns (DAMPs), including adenosine triphosphate (ATP), high-mobility group box 1 (HMGB1), and lipid peroxidation products during ferroptosis, which can activate tumor-infiltrating immune cells, trigger inflammatory responses, and stimulate antitumor immunity[79,80]. Studies have shown that ROS and lipid peroxides released during ferroptotic cancer cells can activate the cGAS/STING axis, driving tumor-associated macrophages (TAMs) to shift from an M2 to an M1 phenotype and reversing their immunosuppressive function[81].
Nevertheless, the impact of oxidative stress and ferroptosis on the TME is bidirectional. Oxidative stress induces tumor cells to release exosomes carrying the KRASG12D protein. Upon uptake by macrophages, these exosomes drive a shift toward an M2-like phenotype through STAT3-dependent fatty acid oxidation[82]. In this context, dying tumor cells convert local death signals into immunosuppressive macrophage polarization via exosome-mediated metabolic reprogramming, revealing the remote regulation of immune cells by the stress state of tumor cells. Furthermore, the influence of immunological signals released by ferroptotic cancer cells on dendritic cells (DCs) is also double-edged. Whereas some studies have shown that ferroptotic cancer cells reduce DC maturation and inhibit antigen cross-presentation[83], induction of ferroptosis in head and neck squamous cell carcinoma activates the STING-IFN-I pathway, thereby enhancing DC recruitment and maturation[84].
Collectively, oxidative stress and ferroptosis actively regulate the survival and function of immune cells in the TME by releasing ROS, lipid peroxides, free iron, and DAMPs, thereby reshaping the immune microenvironment. This remodeling is not a unidirectional process but rather a complex bidirectional network among oxidative stress, ferroptosis, and immune cells, in which the same signal can produce markedly divergent effects depending on the cell type and metabolic context. Accordingly, future therapeutic strategies need to move beyond the simplistic paradigm of either “inducing” or “inhibiting” ferroptosis. Instead, based on the cellular composition and metabolic specificity of the TME, combination regimens that target ferroptosis-defense pathways together with immune checkpoint inhibitors should be explored to maximize antitumor immune responses.
5.3 Cancer-associated fibroblasts and extracellular matrix remodeling
Oxidative stress inflicts chronic cellular damage, including DNA lesions and protein oxidation. Lipid peroxidation products generated during ferroptosis, such as malondialdehyde (MDA) and 4-HNE, form adducts with proteins and DNA, causing persistent cellular injury[85,86]. More critically, the ferroptosis and oxidative stress vicious cycle amplifies this chronic damage and drives tissue remodeling, ultimately promoting tumor invasion. In this process, CAFs are important regulators of tissue remodeling. CAFs express high levels of alpha-smooth muscle actin (α-SMA) and fibroblast activation protein, and their activation status closely correlates with ferroptosis sensitivity. These cells produce abundant collagen and fibronectin, remodeling the extracellular matrix (ECM), restricting nutrient and oxygen diffusion, and exacerbating TME stress[67]. In addition, oxidative stress has been shown to activate fibroblasts directly, promoting their hyperproliferation and differentiation into myofibroblasts, leading to aberrant deposition of ECM proteins and eventual tissue fibrosis[87].
Furthermore, epithelial-mesenchymal transition (EMT) markedly enhances tumor cell susceptibility to ferroptosis by remodeling cellular metabolism and epigenetic states. The underlying mechanism involves upregulation of the EMT-associated transcription factor ZEB1, which regulates the expression levels of stearoyl-Co-A desaturase 1 (SCD), fatty acid synthase (FASN), fatty acid desaturase 2 (FADS2), elongation of very long-chain fatty acid 5 (ELOVL5), and ACSL4, to promote accumulation of PUFA-PLs, providing substrates for lipid peroxidation[88]. Concurrently, CD44-mediated iron endocytosis is enhanced during EMT, leading to intracellular iron accumulation to promote the expression of mesenchymal genes[89]. These findings underscore the potential of ferroptosis-inducing agents to selectively eliminate therapy-resistant cancer cells with mesenchymal phenotypes.
5.4 Endothelial cells and angiogenic signaling
The activation, proliferation, and migration of vascular endothelial cells (ECs) are central to angiogenesis, influencing tumor cell metastasis, chemotherapy-induced injury, and the efficacy of immunotherapy[90]. Under hypoxic conditions, upregulated endothelial cell specific molecule-1 promotes angiogenesis by activating vascular endothelial growth factor receptor 2 (VEGFR2) signaling[91]. Consistent with the pro-oxidant nature of the TME, an oxidative stress–driven ferroptosis-like mechanism hyperactivates ECs, enhancing their proliferation, migration, and tube formation while disrupting VE-cadherin junctions and facilitating cancer cell adhesion and transendothelial migration, which is reversed by the antioxidant propranolol[92]. Similarly, ROS accumulated in tumor vessels promote the pro-angiogenic phenotype of tumor endothelial cells by suppressing NRF2 and activating the SMAD2/3 axis[93]. At the post-transcriptional level, the lncRNA MEG8/miR-497-5p/NOTCH2 axis governs ferroptosis of hemangioma endothelial cells by modulating SLC7A11 and GPX4, linking ferroptotic signaling to tumor EC survival[94]. Collectively, within the TME, oxidative stress and ferroptosis act synergistically to regulate ECs’ function and angiogenic signaling, ultimately shaping the structure of the tumor vasculature.
5.5 Emergence of tumor heterogeneity
The regulatory landscape of ferroptosis exhibits marked heterogeneity across different tumor types, reflecting diverse adaptive strategies that tumor cells employ in response to oxidative stress. This variability arises not only from intrinsic metabolic pathway alterations but is also profoundly shaped by the TME. Persistent oxidative stress within the TME imposes selective pressure on tumor cells. Subpopulations that survive under these high-stress conditions often evolve distinct defense mechanisms. For example, the glycolytic byproduct L-lactate triggers a ROS burst in neuroblastoma, which, in turn, activates cellular defense programs such as the unfolded protein response and NRF2 signaling[95]. KRAS-mutant cells upregulate FSP1 to confer resistance to ferroptosis[96]. Lung cancer stem-like cells increase SLC7A11 expression to evade ferroptotic cell death[97]. The co-localization of GPX4 and peroxiredoxin 6 (PRDX6) at the plasma membrane enables a “reduction-hydrolysis” two-enzyme cascade that efficiently repairs peroxidized phospholipid damage to resist ferroptosis[98]. Variations in oxidative stress and ferroptosis sensitivity among different tumor cells directly influence therapeutic resistance and clinical outcomes, highlighting potential targets for precision oncology.
6. The Ferroptosis-Oxidative Stress-Tumor Microenvironment Triad
On the basis of the previous summary and evidence, ferroptosis, oxidative stress, and the TME are not isolated phenomena operating in parallel, but rather constitute a deeply entangled triadic system. Here, we propose a reciprocal causality among these three pillars: (i) ROS-driven lipid peroxidation initiates ferroptosis; (ii) ferroptotic cell death functions simultaneously as executor and signal broadcaster via the release of lipid electrophiles and DAMPs; and (iii) the TME acts as a responsive arena wherein multiple stromal and immune cell types decode these signals, undergo phenotypic reprogramming, and in turn modulate the feedback redox landscape. This triad gives rise to a redox-lipid-immune feedback loop, manifests through the remodeling of distinct TME cellular compartments, and ultimately drives metabolic competition that selects for heterogeneous, therapy-resistant clones.
This feedback architecture explains a central paradox of ferroptosis biology in cancer: the same molecular machinery that enables tumor cell killing simultaneously cultivates the immunosuppressive, therapy-resistant TME that protects residual tumor clones. This hints that monotherapy directed at any single node of this loop is likely to be undermined by the compensatory dynamics of the remaining nodes. Multi-node strategies, including simultaneous amplification of oxidative stress, induction of ferroptosis execution, and mitigation of metabolic competition, may be a more efficient strategy for treating tumors[99,100].
7. Ferroptosis and Oxidative Stress Induction Strategies: Targeting the TME
Conventional anticancer strategies have predominantly focused on single cell death pathways or individual immune checkpoints. However, tumors rapidly acquire therapeutic resistance through signaling network redundancy and metabolic compensation. In recent years, the development of novel therapeutic platforms around the multi-node and multi-modal combined treatment strategy that can achieve spatiotemporally controlled drug delivery in the TME, synergistically induce ferroptosis, regulate immunity, and intervene in metabolism, and achieve cascaded amplification of therapeutic effects has become a research focus.
7.1 Ferroptosis small molecule inducers
The core execution mechanism of ferroptosis hinges on the collapse of intracellular redox homeostasis. Accordingly, triggering ferroptosis through targeted disruption of the redox balance constitutes the fundamental rationale underlying current ferroptosis-based therapeutic strategies. Classical small-molecule ferroptosis inducers achieve this by pharmacologically dismantling distinct intracellular antioxidant pathways, and a growing body of evidence has further revealed their capacity to modulate immune cells. For instance, Erastin, a System Xc- inhibitor, not only potently induces ferroptosis but also enhances NK cell-mediated cytotoxicity against tumors by activating the ligand of the NK cell receptor natural-killer group 2 member D (NKG2D) via the ATF4 transcription factor[101]. In contrast, RSL3 directly inhibits GPX4 activity to trigger ferroptosis, and its ferroptotic effects have been shown to upregulate the immune checkpoint molecule IDO1. IDO1 silencing further sensitizes tumor cells to RSL3-mediated ferroptosis, suggesting a bidirectional regulatory interplay between ferroptosis and the TME[102].
7.2 TME-responsive amplification of oxidative stress for ferroptosis induction
The intrinsic metabolic heterogeneity of the TME, including acidity, hypoxia, and elevated H2O2 levels, constitutes a redox vulnerability that distinguishes tumors from normal tissues and provides an endogenous chemical basis for the in situ activation of ferroptosis. Exploiting these metabolic features, researchers have developed various TME-responsive nanoplatforms that couple tumor-intrinsic signals with material functionalities to achieve precise amplification of oxidative stress and cascade induction of ferroptosis. Among the diverse nanoplatforms explored, iron-based nanomaterials represent the most extensively investigated ferroptosis-inducing systems. Iron-based nanomaterials capitalize on the intrinsic capacity to supply Fe2+/Fe3+ ions that catalyze hydroxyl radical generation via Fenton/Fenton-like chemistry utilizing endogenous H2O2 enriched in the TME, thereby rapidly amplifying ROS and initiating lipid peroxidation[103,104]. Building upon this concept, multifunctional iron-based drug delivery platforms have been engineered to achieve multi-pathway ferroptosis amplification. For instance, Fe-metal organic framework (MOF)-coated hollow mesoporous organosilica nanosuspensions function as localized postoperative delivery systems that sustain drug release at residual tumor sites while enhancing oxidative stress to induce ferroptosis. Concurrently, they act as “immune amplifiers” by promoting T cell recruitment and lymph node antigen presentation, effectively suppressing postoperative local recurrence and brain metastasis in breast cancer[105]. A shared feature of these strategies is the establishment of a ferroptosis execution-centered positive feedback loop, wherein direct tumor cell killing and immune activation are mutually reinforcing.
Nevertheless, the high reducing potential in the TME frequently constrains the efficacy of iron-based systems. Copper-based and copper-iron bimetallic nanomaterials address this limitation through superior Fenton-like reactivity and GSH depletion capacity[106]. More innovatively, copper-based platforms can trigger synergistic ferroptosis-cuproptosis effects. DSF@HMCIS-PEG-FA releases Cu2+, Fe2+, and disulfiram in the acidic TME. The Fe/Cu dual Fenton-like reactions induce robust ferroptosis, whereas GSH depletion and mitochondrial damage further elicit cuproptosis, establishing a self-accelerating death cycle[107]. This “dual-death modality” not only enhances tumor cell clearance efficiency but also maximizes immunogenic cell death (ICD) effects through multiple stress signals, providing abundant DAMPs for immune activation.
7.3 Gene regulation for ferroptosis induction
To achieve tumor-specific ferroptosis induction while minimizing systemic toxicity, researchers have incorporated gene regulators into TME-responsive nanodelivery systems. Proteolysis-targeting chimeras (PROTACs) represent an emerging therapeutic modality with greater potential than conventional receptor antagonists or enzyme inhibitors. PROTACs harness endogenous E3 ubiquitin ligases to degrade proteins of interest via the ubiquitin-proteasome system in a catalytic cycle[108]. Zhu et al. developed an antibody-based PROTAC targeting SLC6A6 degradation and subsequently integrated it into biomimetic ROS-responsive nanoparticles. This system depletes intracellular taurine in tumor cells through SLC6A6 degradation, dismantling antioxidant defenses and inducing ferroptosis, while concurrently driving M1 macrophage polarization and restoring CD8+ T cell cytotoxicity, resulting in marked tumor suppression in cholangiocarcinoma models[109]. Currently, PROTACs are being advanced toward oral formulations to align with clinically preferred routes of administration[110]. Nevertheless, existing combinations of PROTACs with ferroptosis induction remain largely dependent on nanoparticle-based delivery, and future efforts should focus on developing oral dosage forms to facilitate more streamlined clinical translation.
7.4 Physical energy driven multimodal combination
To further overcome the limitations of ferroptosis monotherapy, including insufficient ROS generation, TME constraints, and unstable efficacy, multimodal combination strategies have been extensively explored. AuAg bimetallic hollow nanoshells loaded with pyrotinib and herceptin achieve direct tumor ablation via near-infrared (NIR) photothermal therapy while inducing a ROS burst and ferroptosis, and upregulating TNF/NF-κB pathways to enhance immune activation and ICD, offering a promising strategy for human epidermal growth factor receptor 2 (HER2)-positive breast cancer that has developed resistance to targeted therapy[111]. NIR-II and photoimmunotherapy platforms developed for gastric cancer and hepatocellular carcinoma can inhibit the SLC7A11/GSH/GPX4 axis, elevate ROS levels, promote the release of DAMPs, and facilitate the formation of memory T cells[112,113]. The central logic underlying these multimodal strategies is the use of physical energy input (light, magnetism, ultrasound) to breach the metabolic barriers of the TME, thereby creating favorable conditions for ferroptosis execution while utilizing ICD to bridge innate and adaptive immune responses.
7.5 Ferroptosis combined with immunotherapy
Tumors can be broadly classified into two immunophenotypes based on their immunogenicity and immune infiltration density, “cold tumors” and “hot tumors”[114]. For immune-excluded or cold tumors, combining ferroptosis with immune checkpoint blockade (ICB), such as αPD-1/PD-L1 antibodies, can achieve synergistic therapeutic effects. For example, the IFN-γ-inducible guanylate-binding protein 2 (GBP2) sensitizes melanoma cells to ferroptosis by activating STAT1 and inhibiting SLC7A11, while the concomitant release of high-mobility group box 1 (HMGB1) during ferroptosis further promotes the infiltration of cytotoxic T cells, improving tumor responsiveness to ICB immunotherapy[115]. Similarly, doxorubicin (DOX)- and erianin-loaded CaCO3 nanoparticles induce Ca2+ overload and neutralize acidic TME, activating hybrid ferroptosis/apoptosis pathways and eliciting severe ICD. When combined with αPD-L1, this system enhances systemic immune responses and reverses immunosuppression and drug resistance driven by acidic, poorly immunogenic TME[116].
The use of ferroptotic cells directly as vaccines represents an emerging direction in the field. It has been reported that ferroptosis-armed DC vaccines can suppress glioma growth in mice. The underlying principle involves pulsing DCs with ferroptotic tumor cell lysates, which promotes IFN-γ production and induces robust CD8+ T cell infiltration, activation, and effector memory formation within the TME[117]. Additionally, in a post-surgical tumor model, DC vaccines loaded with ferroptotic cell lysates integrate the triple functions of DC recruitment, antigen delivery, and immune activation, thereby effectively counteracting surgery-induced immunosuppression[118].
Collectively, despite divergent mechanistic emphases, these therapeutic strategies converge upon a unified multi-nodal axis of oxidative stress amplification, ferroptosis execution, immune regulation, and metabolic competition relief, forming a complementary and synergistic therapeutic network.
8. Clinical Applications
Although extensive preclinical evidence supports ferroptosis as a promising anticancer strategy, its clinical translation remains at an early stage. Currently, clinical evidence retrieved on clinicaltrials.gov using the keyword “ferroptosis” can be divided into two categories: interventional clinical studies in which ferroptosis is implicated as a putative mechanistic basis rather than the primary therapeutic target; and prospective observational studies evaluating ferroptosis-related molecules as biomarkers for prognosis, stratification, or treatment monitoring. By contrast, relatively few candidate agents have entered clinical trials explicitly as ferroptosis-targeting therapeutics (Table 1).
Table 1. Summary of clinical trials on ferroptosis.
| Clinical trial ID | Study Title | Study Type | Phases | Study Status(2026/04/20) |
| NCT05924074 | Ferroptosis Study in SF3B1-mutant Myelodysplastic Syndromes (FerMDS) | interventional | NA | recruiting |
| NCT07260942 | Ferroptosis Role in the Pathophysiology of Systemic Lupus Erythematosus | interventional | NA | not yet recruiting |
| NCT06928649 | Stratifying Critically Ill Patients for Novel Ferroptosis or Pyroptosis Intervention Strategies | interventional | NA | recruiting |
| NCT06491394 | Lactoferrin Effect on Kidney and Heart of Rhabdomyolysis Rats | interventional | IV | completed |
| NCT06218524 | The Effectiveness of HP and TMZ Synergism on Adult Recurrence GBM | interventional | II | not yet recruiting |
| NCT07433283 | Carbon Nanoparticle-Loaded Iron in the Treatment of Advanced Solid Tumor | interventional | I and II | recruiting |
| NCT05493800 | Evaluate the Safety and Efficacy for Oral Mucositis Prevention of MIT-001 in Auto HSCT | interventional | II | active, not recruiting |
| NCT06048367 | Carbon Nanoparticle-Loaded Iron [CNSI-Fe(II)] in the Treatment of Advanced Solid Tumor | interventional | I | completed |
| NCT06151548 | Effect of Krill Oil Supplementation on Red Blood Cell Physiology Against Changes in Markers of Iron Metabolism. | interventional | IV | unknown |
| NCT04378075 | A Study to Evaluate Efficacy and Safety of Vatiquinone for Treating Mitochondrial Disease in Participants With Refractory Epilepsy | interventional | II and III | terminated |
| NCT07412574 | Vitamin E Supplementation As Adjunctive Therapy To Lower Inflammation In COVID-19 Patients | interventional | Early Phase I | completed |
| NCT06261086 | Evaluation of Pyroptosis-related Indicators in the Pathogenesis of Vitiligo:Across-sectional Comparative Study | interventional | NA | unknown |
| NCT05753332 | Association Between PM2.5 and Ferroptosis | observational | NA | unknown |
| NCT05269901 | Association Between Ferroptosis and Epilepsy | observational | NA | completed |
| NCT05950386 | Effects of Lead Exposure on Ferroptosis Pathway | observational | NA | unknown |
| NCT05758129 | Association Between PM2.5 Exposure and Ferroptosis in Seizures Patients | observational | NA | unknown |
| NCT05410665 | The Roles of IL-9/E-cadherin and Ferroptosis in Intestinal Mucosal Barrier Injury in Sepsis | observational | NA | unknown |
| NCT06237907 | Pyroptosis and Ferroptosis in the Pathophysiology of Lymphedema | observational | NA | unknown |
| NCT06896383 | Role of USP35 in the Detection of Ferroptosis in Juvenile Autoimmune Hepatitis | observational | NA | not yet recruiting |
| NCT06102993 | Ferroptosis in Patients With COPD With/Without Risk of Cardiovascular Events. Pathophysiological Implications, Diagnostics and Prognoses. | observational | NA | unknown |
| NCT06554392 | Identification of Serum Level of Glutathione Peroxidase 4 | observational | NA | not yet recruiting |
| NCT06863116 | Analysis of HIF-1α, MDA, and GPX4 in Peri-Implant Crevicular Fluid | observational | NA | completed |
| NCT06891820 | Multifaceted Analysis of the Adaptation of Rowers in the Process of Sports Training | observational | NA | completed |
| NCT04211636 | Autoimmunity And Immune Deficiency After Spinal Cord Injury: Association With Rehabilitation Outcomes | observational | NA | not yet recruiting |
GPX4: glutathione peroxidase 4; MDA: malondialdehyde; TMZ: temozolomide; GBM: glioblastoma multiforme; HIF-1α: hypoxia-inducible factor 1-alpha; HP: haloperidol; HSCT: hematopoietic stem cell transplantation; COPD: chronic obstructive pulmonary disease.
In oncology, ferroptosis induction as a sensitization strategy for anticancer treatment has begun to enter the clinical validation stage. A representative example is the combination of sorafenib with stereotactic body radiotherapy (SBRT) in colorectal cancer liver metastases. Mechanistically, SBRT suppresses SLC7A11 expression, while sorafenib further amplifies this effect, thereby weakening tumor antioxidant defenses and promoting ferroptosis. A phase II clinical trial demonstrated that this combination could overcome radioresistance in liver metastatic colorectal cancer with high SLC7A11 expression, while showing favorable efficacy and safety, indicating that ferroptosis induction is beginning to enter clinical validation as a radiosensitizing strategy[119]. In addition, in relapsed/refractory acute myeloid leukemia (AML) and high-risk myelodysplastic syndrome, a phase I study of pevonedistat plus belinostat did not designate ferroptosis as a primary endpoint. Yet, analyses revealed changes in SLC7A11 and other oxidative stress/ferroptosis-related molecules, suggesting that ferroptosis may contribute to the activity of this regimen[120]. Similarly, the antileukemic effects of imetelstat in AML have been linked to enhanced lipid peroxidation and ferroptosis regulation, although current evidence remains largely translational and has not yet matured into clinical trials specifically designed for ferroptosis-directed intervention[121].
Concurrently, targeted modulation of ferroptosis and oxidative stress pathways is advancing in parallel across diverse disease contexts. The therapeutic strategies exhibit a bidirectional divergence, encompassing both mitigating tissue injury via ferroptosis inhibition and exploiting ferroptosis induction for tumor eradication. A mitochondrial-targeting antioxidant, MIT-001, has completed a phase I study in healthy volunteers evaluating pharmacokinetics and safety. Following subcutaneous administration, MIT-001 was rapidly absorbed and well tolerated, and it is currently being investigated in a phase II trial for the prevention of oral mucositis after autologous hematopoietic stem cell transplantation (NCT05493800)[122,123]. RT001 (deuterated linoleic acid) inhibits ferroptosis by suppressing lipid peroxidation chain reactions. However, it failed to improve the primary endpoint in a placebo-controlled trial in Friedreich’s ataxia, suggesting that the clinical translation of antioxidant strategies still faces challenges[124]. In promoting ferroptosis, CNSI-Fe(II), an iron-loaded carbon nanostructure complex, is under clinical investigation to assess its efficacy, safety, tolerability, and pharmacokinetics in patients with advanced solid tumors[125].
Meanwhile, an increasing number of prospective observational studies have demonstrated the clinical value of ferroptosis-related markers for stratification. In chronic obstructive pulmonary disease, diabetic kidney disease, sepsis, aneurysmal subarachnoid hemorrhage, and advanced non-small cell lung cancer, biomarkers such as GPX4, ACSL4, SLC7A11, and the sTfR1/GPX4 ratio have been associated with disease severity, risk of exacerbation, or short-term prognosis[126-130]. Although these studies do not yet constitute therapeutic evidence, they provide an important clinical foundation for future precision stratification, response prediction, and targeted intervention based on ferroptosis.
9. Clinical Translation Challenges
Despite the promising outlook of ferroptosis in cancer treatment, its clinical translation faces multiple challenges. Firstly, although classical ferroptosis inducers effectively trigger ferroptosis in cell culture and animal models, their clinical applicability is constrained by poor chemical stability, low aqueous solubility, suboptimal pharmacokinetic properties, potential off-target toxicity, and the emergence of acquired resistance[131]. In this regard, repurposing clinically approved drugs and screening ferroptosis-inducing compounds from traditional Chinese medicine or natural products represent promising strategies to overcome the limitations of existing inducers. In addition, while a nano-delivery platform provides a new opportunity for the application of ferroptosis, there are also problems such as material stability, batch-to-batch material differences, and complex mass production, which hinder the process of clinical translation.
Secondly, systemic induction of ferroptosis may cause off-target effects and unacceptable toxicity. Because ferroptosis is fundamentally driven by iron-dependent lipid peroxidation, normal cells enriched in PUFAs are equally vulnerable to peroxidative damage when ferroptosis is induced in target cells, leading to collateral toxicity[132]. Moreover, systemic inhibition of SLC7A11 disrupts cystine/glutamate exchange, thereby compromising tissues that depend on this transport system to maintain redox homeostasis, such as the kidney and neurons[133]. This conundrum stems from the ubiquitous nature of ferroptosis-regulatory mechanisms, underscoring the need for strategies capable of selectively targeting cancer cells.
Thirdly, the sensitivity of cancer cells to ferroptosis is markedly heterogeneous[134]. For instance, KRAS-mutant cancer cells are relatively resistant to ferroptosis[135], and squamous cell carcinoma can upregulate NRF2 through mechanisms including RNA epigenetic regulation, thereby acquiring ferroptosis resistance[136]. More importantly, the metastatic niche can reshape ferroptosis vulnerability. One study demonstrated that colorectal cancer liver metastases exhibit a lower GSH/oxidized glutathione (GSSG) ratio than primary tumors, and that successful colonizers display enhanced resistance to ferroptosis[137]. These disparities indicate that ferroptosis-inducing strategies should be tailored to the specific cancer type, molecular subtype, and metastatic niche.
Lastly, the complexity of the TME further complicates therapeutic targeting. As discussed above, immune cells within the TME are sensitive to ferroptosis, and distinct ferroptotic immune cell subsets can emit signals that modulate other components of the TME. By contrast, cancer cells tend to be comparatively resistant to ferroptosis. Therefore, how to selectively induce ferroptosis in cancer cells while preserving the normal functions of immune cells remains a central bottleneck in the clinical translation of ferroptosis-based therapy.
10. Conclusion and Outlook
The hypoxic, acidic, and nutrient-deprived characteristics of the TME are closely linked to ferroptosis susceptibility. The mechanisms of ferroptosis are intricately intertwined with oxidative stress, encompassing mitochondrial dynamics that regulate ROS generation and stress responses, Fenton reaction-driven chain amplification of lipid peroxidation, and the SLC7A11/GSH/GPX4 and NRF2 axes that constitute the core antioxidant defense network[138]. Within the TME, this interplay not only dictates the fate of tumor cells themselves but also profoundly influences tumor progression and therapeutic response by remodeling immune cell function, CAFs activity, angiogenesis, and tumor heterogeneity.
Therapeutic strategies targeting the interactive network between ferroptosis and oxidative stress have demonstrated potent antitumor efficacy[103,139]. However, numerous urgent challenges remain to be addressed in advancing the clinical translation of ferroptosis-based therapies, warranting focused attention in future research. Firstly, the high heterogeneity of tumors means that different tumor types and treatment stages exhibit significant differences in their responses to ferroptosis inducers[140]. Therefore, optimal application strategies require a precise, individualized design. The development of personalized biomarkers is essential for identifying specific patient populations likely to benefit from ferroptosis-inducing therapy. This process should integrate multidimensional data, including ferroptosis-related gene expression profiles in tumor tissues, serum iron metabolism indicators, and imaging features[67]. Secondly, the dynamic evolution of the TME and its adaptive changes under therapeutic pressure, along with the long-term efficacy and safety assessment of ferroptosis inducers, represent critical areas requiring further investigation to enable clinical application of ferroptosis. Furthermore, multimodal combination regimens have been widely applied in the oncology field[141]. Based on the interactive mechanisms among ferroptosis, oxidative stress, and TME remodeling, designing combination treatments that synergistically target multiple pathways is expected to further enhance antitumor efficacy. Importantly, the synergistic effects between ferroptosis-targeted therapies and existing standard treatments, including chemotherapy, RT, and immunotherapy, provide a theoretical foundation and practical direction for improving overall treatment outcomes and overcoming therapeutic resistance.
In summary, the interplay between ferroptosis, oxidative stress, and the TME has unveiled new targets and strategic combinations for cancer therapy. The clinical application of ferroptosis inducers will evolve from single-agent approaches toward combination regimens with other treatment modalities to enhance antitumor efficacy and overcome resistance. Future efforts should emphasize close integration of basic research and clinical practice, validating the efficacy and safety of novel therapeutic strategies through rigorous clinical trial design, thereby facilitating the translation of ferroptosis-targeted therapies from bench to bedside.
Acknowledgements
The figures were generated using Adobe Illustrator software.
Authors contribution
Zhang P, Zhou C: Writing-original draft.
Yang C, Li H, Ren X: Data curation.
Lu Y, Pan F: Visualization.
Xia J, Du J, Li Y: Supervision, writing-review & editing.
Conflicts of interest
The authors declare that there is no conflict of interest.
Ethical approval
Not applicable.
Consent to participate
Not applicable.
Consent for publication
All authors agree to publish.
Availability of data and materials
Not applicable.
Funding
This research was supported by the Mindray Joint Fund of Zhejiang Provincial Natural Science Foundation of China (Grant Nos. LMRY26H080001, ZCLMRY26H0801), the ZhongWei Joint Funds of the Zhejiang Provincial Natural Science Foundation of China (Grant Nos. LBY23H080001). Basic Scientific Research Funds of Department of Education of Zhejiang Province (Grant No. KYYB202214). Construction Fund of Key Medical Disciplines of Hangzhou (Grant Nos. 2025HZGF04 and 2025HZZD01).
Copyright
© The Author(s) 2026.
References
-
3. Bejarano L, Jordāo MJC, Joyce JA. Therapeutic targeting of the tumor microenvironment. Cancer Discov. 2021;11(4):933-959.[DOI]
-
7. Yamamoto S, Kodama T, Kuwano A, Maesaka K, Yoshida-Hashidate T, Shindou H, et al. NRF2-COX2-PGE2 axis drives immune cold tumors and predicts resistance to combination immunotherapy in hepatocellular carcinoma. Hepatology. 2026.[DOI]
-
12. Long H, Zhu W, Wei L, Zhao J. Iron homeostasis imbalance and ferroptosis in brain diseases. MedComm. 2023;4(4):e298.[DOI]
-
14. Xia C, Xing X, Zhang W, Wang Y, Jin X, Wang Y, et al. Cysteine and homocysteine can be exploited by GPX4 in ferroptosis inhibition independent of GSH synthesis. Redox Biol. 2024;69:102999.[DOI]
-
19. Mao C, Liu X, Yan Y, Olszewski K, Gan B. Reply to: DHODH inhibitors sensitize to ferroptosis by FSP1 inhibition. Nature. 2023;619(7968):E19-E23.[DOI]
-
21. Chen F, Kang R, Tang D, Liu J. Ferroptosis: Principles and significance in health and disease. J Hematol Oncol. 2024;17(1):41.[DOI]
-
25. Chen ZH, Saito Y, Yoshida Y, Sekine A, Noguchi N, Niki E. 4-hydroxynonenal induces adaptive response and enhances PC12 cell tolerance primarily through induction of thioredoxin reductase 1 via activation of Nrf2. J Biol Chem. 2005;280(51):41921-41927.[DOI]
-
26. Luo T, Song S, Wang S, Jiang S, Zhou B, Song Q, et al. Mechanistic insights into cadmium-induced nephrotoxicity: NRF2-Driven HO-1 activation promotes ferroptosis via iron overload and oxidative stress in vitro. Free Radic Biol Med. 2025;235:162-175.[DOI]
-
28. Zhang T, Sun L, Hao Y, Suo C, Shen S, Wei H, et al. ENO1 suppresses cancer cell ferroptosis by degrading the mRNA of iron regulatory protein 1. Nat Cancer. 2022;3(1):75-89.[DOI]
-
30. Bucarey JL, Casas M, Espinosa A. Mitochondrial iron handling and lipid peroxidation as drivers of ferroptosis. Int J Mol Sci. 2026;27(5):2232.[DOI]
-
31. Zhang J, Nie C, Zhang Y, Yang L, Du X, Liu L, et al. Analysis of mechanism, therapeutic strategies, and potential natural compounds against atherosclerosis by targeting iron overload-induced oxidative stress. Biomed Pharmacother. 2024;177:117112.[DOI]
-
32. Liang FG, Zandkarimi F, Lee J, Axelrod JL, Pekson R, Yoon Y, et al. OPA1 promotes ferroptosis by augmenting mitochondrial ROS and suppressing an integrated stress response. Mol Cell. 2024;84(16):3098-3114.e6.[DOI]
-
40. Li C, Liu J, Hou W, Kang R, Tang D. STING1 promotes ferroptosis through MFN1/2-dependent mitochondrial fusion. Front Cell Dev Biol. 2021;9:698679.[DOI]
-
41. Li J, Jia YC, Ding YX, Bai J, Cao F, Li F. The crosstalk between ferroptosis and mitochondrial dynamic regulatory networks. Int J Biol Sci. 2023;19(9):2756-2771.[DOI]
-
43. Yang Y, Zhu X, Fang Y, Li J, Shao X, Li S, et al. The nuclear receptor ESRRA is a crucial regulator of acute kidney injury through inhibition of the lipophagy-ferroptosis axis. Autophagy. 2026;22(8):1903-1924.[DOI]
-
48. Guo WY, Wu QM, Zeng HF, Chen YL, Xu J, Yu ZY, et al. A sinomenine derivative alleviates bone destruction in collagen-induced arthritis mice by suppressing mitochondrial dysfunction and oxidative stress via the NRF2/HO-1/NQO1 signaling pathway. Pharmacol Res. 2025;215:107686.[DOI]
-
51. Wang XX, Li M, Xu XW, Zhao WB, Jin YM, Li LL, et al. BNIP3-mediated mitophagy attenuates hypoxic-ischemic brain damage in neonatal rats by inhibiting ferroptosis through P62-KEAP1-NRF2 pathway activation to maintain iron and redox homeostasis. Acta Pharmacol Sin. 2025;46(1):33-51.
-
52. Jomova K, Alomar SY, Valko R, Fresser L, Nepovimova E, Kuca K, et al. Interplay of oxidative stress and antioxidant mechanisms in cancer development and progression. Arch Toxicol. 2026;100(1):27-73.[DOI]
-
61. Kłopotowska M, Baranowska I, Hajduk S, Jurga A, Leśniowska N, Łaźniewski M, et al. GPX4 is a key ferroptosis regulator orchestrating T cells and CAR-T-cells sensitivity to ferroptosis. Cancer Immunol Immunother. 2025;74(9):280.[DOI]
-
63. Ohl K, Fragoulis A, Klemm P, Baumeister J, Klock W, Verjans E, et al. Nrf2 is a central regulator of metabolic reprogramming of myeloid-derived suppressor cells in steady state and sepsis. Front Immunol. 2018;9:1552.[DOI]
-
67. Cui K, Wang K, Huang Z. Ferroptosis and the tumor microenvironment. J Exp Clin Cancer Res. 2024;43(1):315.[DOI]
-
69. Yu X, Yao L, Zhang S, Huang X, Xu A, Fu D. P53 competitively binds P300 to suppress HIF-1α/TFRC-mediated ferroptosis and promote doxorubicin resistance in breast cancer. FASEB J. 2026;40(16):e72228.[DOI]
-
71. Cheng J, Liu Z, Liu H, Fang C, Li J. PPP2CA knockdown upregulates the expression levels of ferroptosis-related genes TFRC and ACSL4 in colorectal cancer cells by promoting mTOR phosphorylation. Front Oncol. 2025;15:1694932.[DOI]
-
75. Jiang Y, Sun M. SLC7A11: The Achilles heel of tumor? Front Immunol. 2024;15:1438807.[DOI]
-
76. Lobel GP, Jiang Y, Simon MC. Tumor microenvironmental nutrients, cellular responses, and cancer. Cell Chem Biol. 2023;30(9):1015-1032.[DOI]
-
79. Hu J, Li Y, Lian B, Mao Y, Zhao L. Mechanism and role of regulated cell death in tumor immunity and immunotherapy. Cancer Commun. 2025;45(11):1456-1495.[DOI]
-
98. Hu Y, Li Z, Li M, Wu X, Zhang S, Tang M, et al. Targeting PRDX6-dependent localization and function of GPX4 enhances ferroptosis-mediated tumor suppression. Mol Cell. 2025;85(24):4602-4620.e9.[DOI]
-
100. Tang D, Kroemer G, Kang R. Ferroptosis in immunostimulation and immunosuppression. Immunol Rev. 2024;321(1):199-210.[DOI]
-
103. Fan X, Liu J, Xie S, Tan H, Mi Z, Zhang P, et al. HSA-templated synergistic platform boosts radiotherapy via enhanced radiosensitization and ferroptosis induction. Drug Resist Updat. 2025;83:101293.[DOI]
-
107. Huang L, Zhu J, Wu G, Xiong W, Feng J, Yan C, et al. A strategy of “adding fuel to the flames” enables a self-accelerating cycle of ferroptosis-cuproptosis for potent antitumor therapy. Biomaterials. 2024;311:122701.[DOI]
-
108. Wang C, Zhang Y, Chen W, Wu Y, Xing D. New-generation advanced PROTACs as potential therapeutic agents in cancer therapy. Mol Cancer. 2024;23(1):110.[DOI]
-
110. Pike A, Lee ECY, Michaelides IN, Schade M, Sharma A, Scott JS, et al. Lessons learned in linking PROTACs from discovery to the clinic. Nat Rev Chem. 2026;10(2):117-132.[DOI]
-
111. Zhao L, Chang F, Tong Y, Yin J, Xu J, Li H, et al. A multifunctional bimetallic nanoplatform for synergic local hyperthermia and chemotherapy targeting HER2-positive breast cancer. Adv Sci. 2024;11(16):2308316.[DOI]
-
112. Wang M, Ding Q, Su W, Luo M, Yang R, Chen G, et al. A mitochondrion-targeted NIR-II modulator for synergistic ferroptosis–immunotherapy. Small. 2025;21(22):2501397.[DOI]
-
115. Liu X, Fang S, Ren X, Hong Y, Guo J, Liu X, et al. GBP2 condensates promote ferroptosis to sensitize anti-PD-L1 immunotherapy in melanoma. Nat Commun. 2026;17:964.[DOI]
-
117. Saviuk M, Turubanova VD, De Brée S, Van Lint S, Maia TM, Devos S, et al. Ferroptosis-armed dendritic cell vaccines for glioma immunotherapy. Nat Commun. 2026;17:6158.[DOI]
-
119. He J, Zhang Y, Luo S, Zhao Z, Mo T, Guan H, et al. Targeting SLC7A11 with sorafenib sensitizes stereotactic body radiotherapy in colorectal cancer liver metastasis. Drug Resist Updat. 2025;81:101250.[DOI]
-
120. Maher KR, Shafer D, Schaar D, Bandyopadhyay D, Deng X, Wright J, et al. A phase I study of MLN4924 and belinostat in relapsed/refractory acute myeloid leukemia or myelodysplastic syndrome. Cancer Chemother Pharmacol. 2025;95(1):24.[DOI]
-
121. Bruedigam C, Porter AH, Song A, Vroeg in de Wei G, Stoll T, Straube J, et al. Imetelstat-mediated alterations in fatty acid metabolism to induce ferroptosis as a therapeutic strategy for acute myeloid leukemia. Nat Cancer. 2024;5(1):47-65.[DOI]
-
123. Bae S, Kim E, Rhee SJ, Kim S, Yu KS, Lee S. Population pharmacokinetic analysis of MIT-001, a novel ferroptosis inhibitor, for dose optimization. J Clin Pharmacol. 2026;66(4):e70189.[DOI]
-
129. Wu X, Hu X, Xia Y, Wang B. The serum levels and clinical significance of ferroptosis markers in patients with aneurysmal subarachnoid hemorrhage who underwent aneurysm clipping surgery. J Stroke Cerebrovasc Dis. 2025;34(11):108440.[DOI]
-
131. Luo Y, Bai XY, Zhang L, Hu QQ, Zhang N, Cheng JZ, et al. Ferroptosis in cancer therapy: Mechanisms, small molecule inducers, and novel approaches. Drug Des Devel Ther. 2024;18:2485-2529.[DOI]
-
134. Liang Y, Zhao Y, Qi Z, Li X, Zhao Y. Ferroptosis: CD8+T cells’ blade to destroy tumor cells or poison for self-destruction. Cell Death Discov. 2025;11:128.[DOI]
-
140. Zhang C, Ding J, Lim KS, Zhou W, Miao W, Wu S, et al. JMJD6 rewires ATF4-dependent glutathione metabolism to confer ferroptosis resistance in SPOP-mutated prostate cancer. Cancer Res. 2025;85(8):1496-1513.[DOI]
Copyright
© The Author(s) 2027. This is an Open Access article licensed under a Creative Commons Attribution 4.0 International License (https://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, sharing, adaptation, distribution and reproduction in any medium or format, for any purpose, even commercially, as long as you give appropriate credit to the original author(s) and the source, provide a link to the Creative Commons license, and indicate if changes were made.
Publisher’s Note
Science Exploration remains a neutral stance on jurisdictional claims in published
maps
and institutional affiliations. The views expressed in this article are solely those
of
the author(s) and do not reflect the opinions of the Editors or the publisher.
Share And Cite


Science Exploration Style
Zhang P, Zhou C, Yang C, Li H, Ren X, Lu Y, et al. Ferroptosis and oxidative stress crosstalk in tumor microenvironment: Mechanisms and targeting strategies. Ferroptosis Oxid Stress. 2027;3:202635. https://doi.org/10.70401/fos.2026.0049
Tips
Copy completed.
Submit a Manuscript
Author Instructions
Cite this Article
Article Metrics
0
View
0
Download
Cited
Article Updates

- Abstract
- Keywords
- 1. Introduction
- 2. Molecular Mechanisms of Ferroptosis
- 3. Interplay Between Ferroptosis and Oxidative Stress
- 4. Differential Ferroptosis Sensitivity in the Tumor Microenvironment
- 5. Ferroptosis and Oxidative Stress Drive Remodeling of Tumor Microenvironment
- 6. The Ferroptosis-Oxidative Stress-Tumor Microenvironment Triad
- 7. Ferroptosis and Oxidative Stress Induction Strategies: Targeting the TME
- 8. Clinical Applications
- 9. Clinical Translation Challenges
- 10. Conclusion and Outlook
- Acknowledgements
- Authors contribution
- Conflicts of interest
- Ethical approval
- Consent to participate
- Consent for publication
- Availability of data and materials
- Funding
- References
- Copyright
 Get citation
Science Exploration Style

Zhang P, Zhou C, Yang C, Li H, Ren X, Lu Y, et al. Ferroptosis and oxidative stress crosstalk in tumor microenvironment: Mechanisms and targeting strategies. Ferroptosis Oxid Stress. 2027;3:202635. https://doi.org/10.70401/fos.2026.0049
copy
Share Link
copy