Beyond slides: The era of 3D histology

Zihang He
1

,
Yingying Li
1
,
Lixue Shi
1,2,*
*Correspondence to:
Lixue Shi, Shanghai Xuhui Central Hospital, Zhongshan-Xuhui Hospital, Shanghai Key Laboratory of Medical Epigenetics, International Co-laboratory of Medical Epigenetics and Metabolism, Institutes of Biomedical Sciences, Shanghai Medical College, Fudan University, Shanghai 200032, China.
E-mail: shilixue@fudan.edu.cn
EXO. 2026;1:202622. 10.70401/EXO.2026.0021
Received: June 03, 2026Accepted: September 30, 2026Published: September 30, 2026
Abstract
Histology has long served as the foundation of tissue diagnosis, yet its reliance on thin two-dimensional (2D) sections incompletely captures the spatial continuity, volumetric heterogeneity, and multicellular architecture of biological tissues. Recent advances in volumetric imaging, spatial omics, label-free optical pathology, and artificial intelligence are enabling tissue analysis beyond the conventional glass slide. In this Perspective, we discuss the emergence of three-dimensional (3D) histology and the technological developments driving the transition from planar sampling to volumetric tissue analysis. We highlight how the added spatial dimension can reveal diagnostically relevant features that are only partially represented in conventional sections, and discuss efforts to extend molecular profiling into intact tissues through multiplexed imaging and volumetric spatial omics. We further examine the growing role of label-free modalities, particularly stimulated Raman scattering microscopy, for rapid and minimally destructive pathology. Finally, we consider the computational foundations required to reconstruct, align and interpret volumetric data, including emerging applications in virtual histology and molecular prediction. Together, these developments suggest that 3D histology is evolving into a broader framework for integrating tissue morphology, molecular state, and function within intact spatial contexts, with emerging opportunities for biological discovery and precision medicine.
Keywords
3D histopathology, non-destructive histology, molecular histology, label-free imaging, virtual staining
1. Introduction
Histopathology has served as the foundation of diagnostic medicine and biological discovery for more than a century. Since the introduction of light microscopy, tissue staining, chemical fixation, and physical microtomy, slide-based histology, particularly hematoxylin and eosin (H&E) staining, has become the clinical gold standard for tissue diagnosis[1]. Over the past century, the integration of immunohistochemistry (IHC), fluorescence microscopy, and spatially resolved molecular profiling has further expanded histology from a primarily morphological discipline toward molecular characterization within the tissue context[2]. Yet despite these advances, the fundamental physical paradigm of histology has remained largely unchanged: tissue information is still predominantly acquired through thin two-dimensional (2D) sections[3]. This reliance on planar sampling limits the ability to capture the inherently three-dimensional (3D) and spatially heterogeneous organizations of biological tissues, particularly for applications requiring volumetric continuity, comprehensive margin assessment, or spatially resolved microenvironmental analysis[3-5].
Recognition of these limitations has driven growing efforts to visualize tissue architecture directly in three dimensions[4,6,7]. Early approaches relied primarily on serial physical sectioning followed by computational reconstruction[8], while more recent developments in tissue clearing and volumetric microscopy have enabled direct interrogation of intact specimens[6]. Together, these advances are transforming 3D histology from a conceptual possibility toward a practical framework for studying tissue organization across scales, from organ-wide architecture to single-cell spatial heterogeneity. Importantly, the value of the third dimension extends beyond imaging more tissue: volumetric analysis can recover structural continuity, spatial relationships, and microanatomical features that are only partially represented in individual sections[6,9].
At the same time, 3D histology is expanding beyond morphology alone. Spatial omics and multiplexed molecular imaging are extending transcriptomic and proteomic information into preserved 3D tissue contexts, providing opportunities to relate molecular states to volumetric tissue organization[10-13]. Separately, label-free optical imaging approaches, including stimulated Raman scattering microscopy[14], optical coherence tomography[15], and ultraviolet-based imaging[16], provide complementary routes to volumetric pathology by deriving contrast directly from intrinsic biochemical and physical tissue properties. Meanwhile, artificial intelligence (AI) is enabling virtual staining and cross-modal prediction, creating new links among alternative imaging contrasts, conventional histology, and molecular information[17-19]. Collectively, these developments raise a broader question: as histology moves beyond the slide, how can advances in volumetric imaging, molecular profiling, and computational analysis be integrated to extract biologically meaningful and clinically actionable representations of intact tissues?
This question places 3D histology at the intersection of several rapidly developing fields while defining a scope distinct from each. Recent reviews have highlighted advances in non-destructive 3D imaging, including tissue clearing, labeling, and volumetric microscopy[6], alongside rapid progress in constructing 3D tissue and tumor atlases[7,20]. Building on these developments, we consider 3D histology as a broader evolution of tissue analysis, in which the added spatial dimension creates new opportunities for morphological assessment, molecular characterization, and clinical translation. This Perspective examines this evolution from planar sampling to volumetric pathology, from morphology to molecular characterization, and from conventional labeling toward label-free and AI-assisted analysis, with particular attention to emerging opportunities in intraoperative pathology and integrated morphological and molecular analysis (Figure 1).
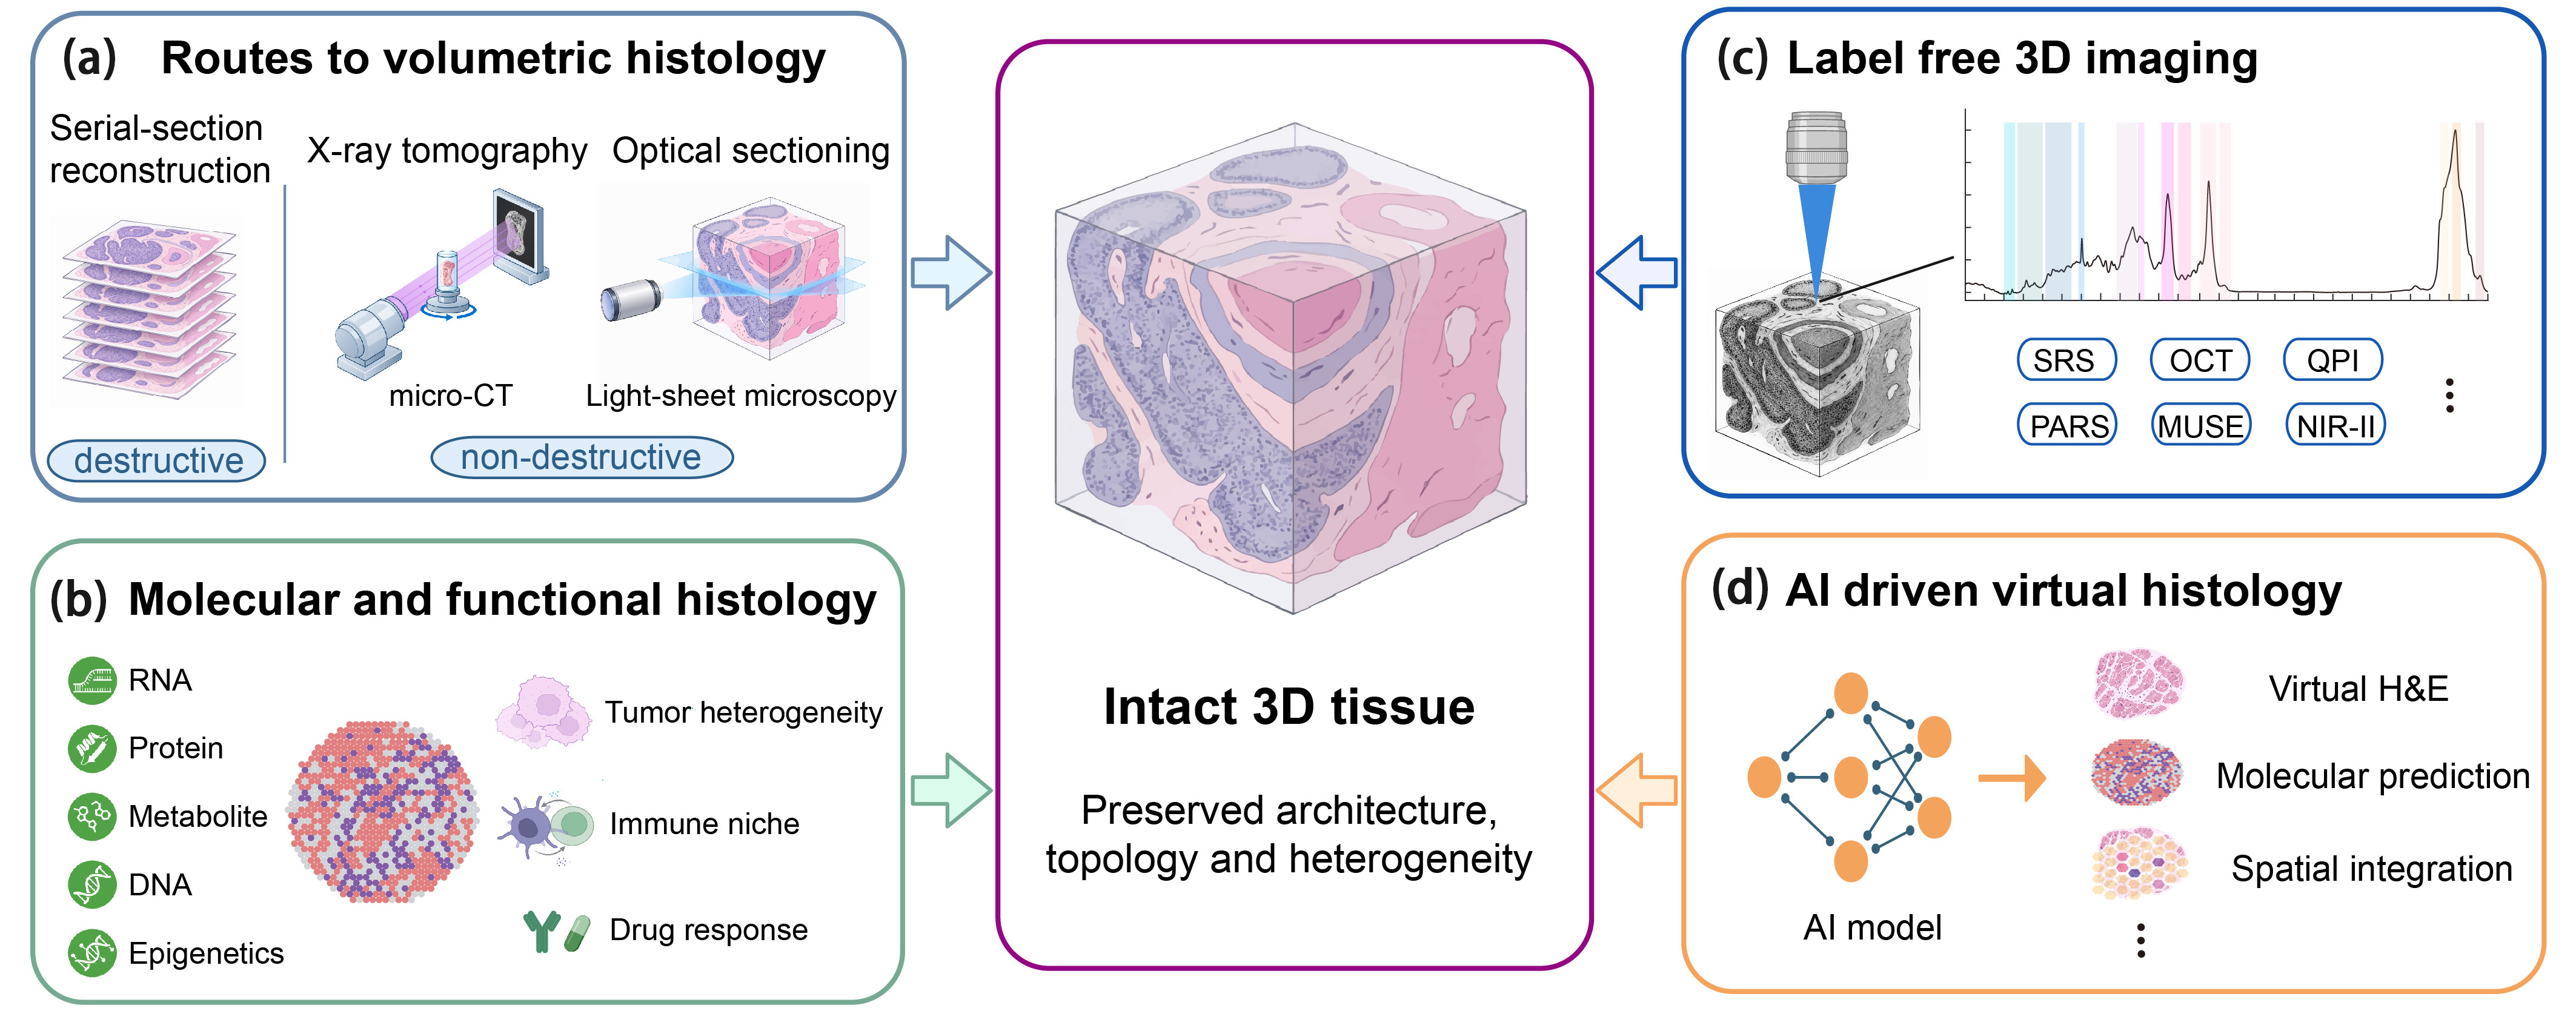
Figure 1. Overview of 3D histology as an integrated framework. The schematic summarizes the conceptual transition from conventional slide-based histology to three-dimensional tissue analysis. The central tissue block represents intact or volumetrically reconstructed tissue architecture. The surrounding modules show four major directions discussed in this Perspective: (a) Volumetric pathology based on serial-section reconstruction or non-destructive imaging; (b) Molecular and functional histology based on spatially resolved protein, RNA and biochemical readouts; (c) Label-free 3D imaging based on endogenous optical contrast; (d) AI-driven virtual histology for virtual staining, molecular inference and multimodal tissue interpretation. 3D: three-dimensional; AI: artificial intelligence.
2. From Slides to Volumes: Redefining Pathology in Three Dimensions
For more than a century, histopathology has relied on microtomy to generate thin tissue sections, with a standard 4-5 μm section representing only a minute fraction of the total biopsy or surgical specimen volume[6,7,21]. This planar sampling can miss rare but diagnostically important features outside the sampled planes, such as focal inflammatory infiltrates, isolated micrometastases, and lymphovascular invasion[4,5]. Physical sectioning also disrupts spatial continuity. Complex architectures such as branching vasculature, glandular and ductal networks, neural projections, and extracellular matrix organization are fragmented across sections, limiting the reconstruction of their 3D geometry and spatial relationships[6,7,22,23].
These limitations are particularly relevant to spatially heterogeneous diseases such as cancer, where malignant cells, stromal programs, immune microenvironments, and necrotic regions can vary substantially across a tissue volume[24,25]. Diagnostic interpretation may therefore depend on sectioning depth and orientation. This mismatch between volumetric tissue organization and planar histological sampling provides a central motivation for the development of 3D pathology.
2.1 Current landscape of 3D pathology
Current strategies for volumetric pathology have evolved along two complementary directions: section-based 3D reconstruction from serial physical sections and non-destructive volumetric imaging of intact specimens[6].
In the first approach, 3D tissue architecture is recovered through post-hoc alignment and assembly of serial sections[26]. Historically, this strategy was constrained by labor-intensive serial microtomy and the difficulty of registering warped or mechanically distorted sections, limiting both reconstruction scale and spatial fidelity[27]. Recent advances in automated sectioning, whole-slide imaging, deep learning-based registration frameworks, such as CODA[8] and Virtual Alignment of pathoLogy Image Series (VALIS)[28] have made large-scale serial-section reconstruction increasingly feasible (Figure 2a). These pipelines can now align tissue volumes at single-cell resolution, enabling the analysis of long-range anatomical organization and tissue microenvironments across whole organs. Despite these advances, section-based 3D pathology remains inherently destructive[6]. Irreversible physical sectioning fragments the tissue and limits repeated imaging or downstream analysis of the same specimen[13]. Sectioning artifacts, tissue loss, and anisotropic sampling can further compromise reconstruction accuracy, particularly across large or heterogeneous tissues.
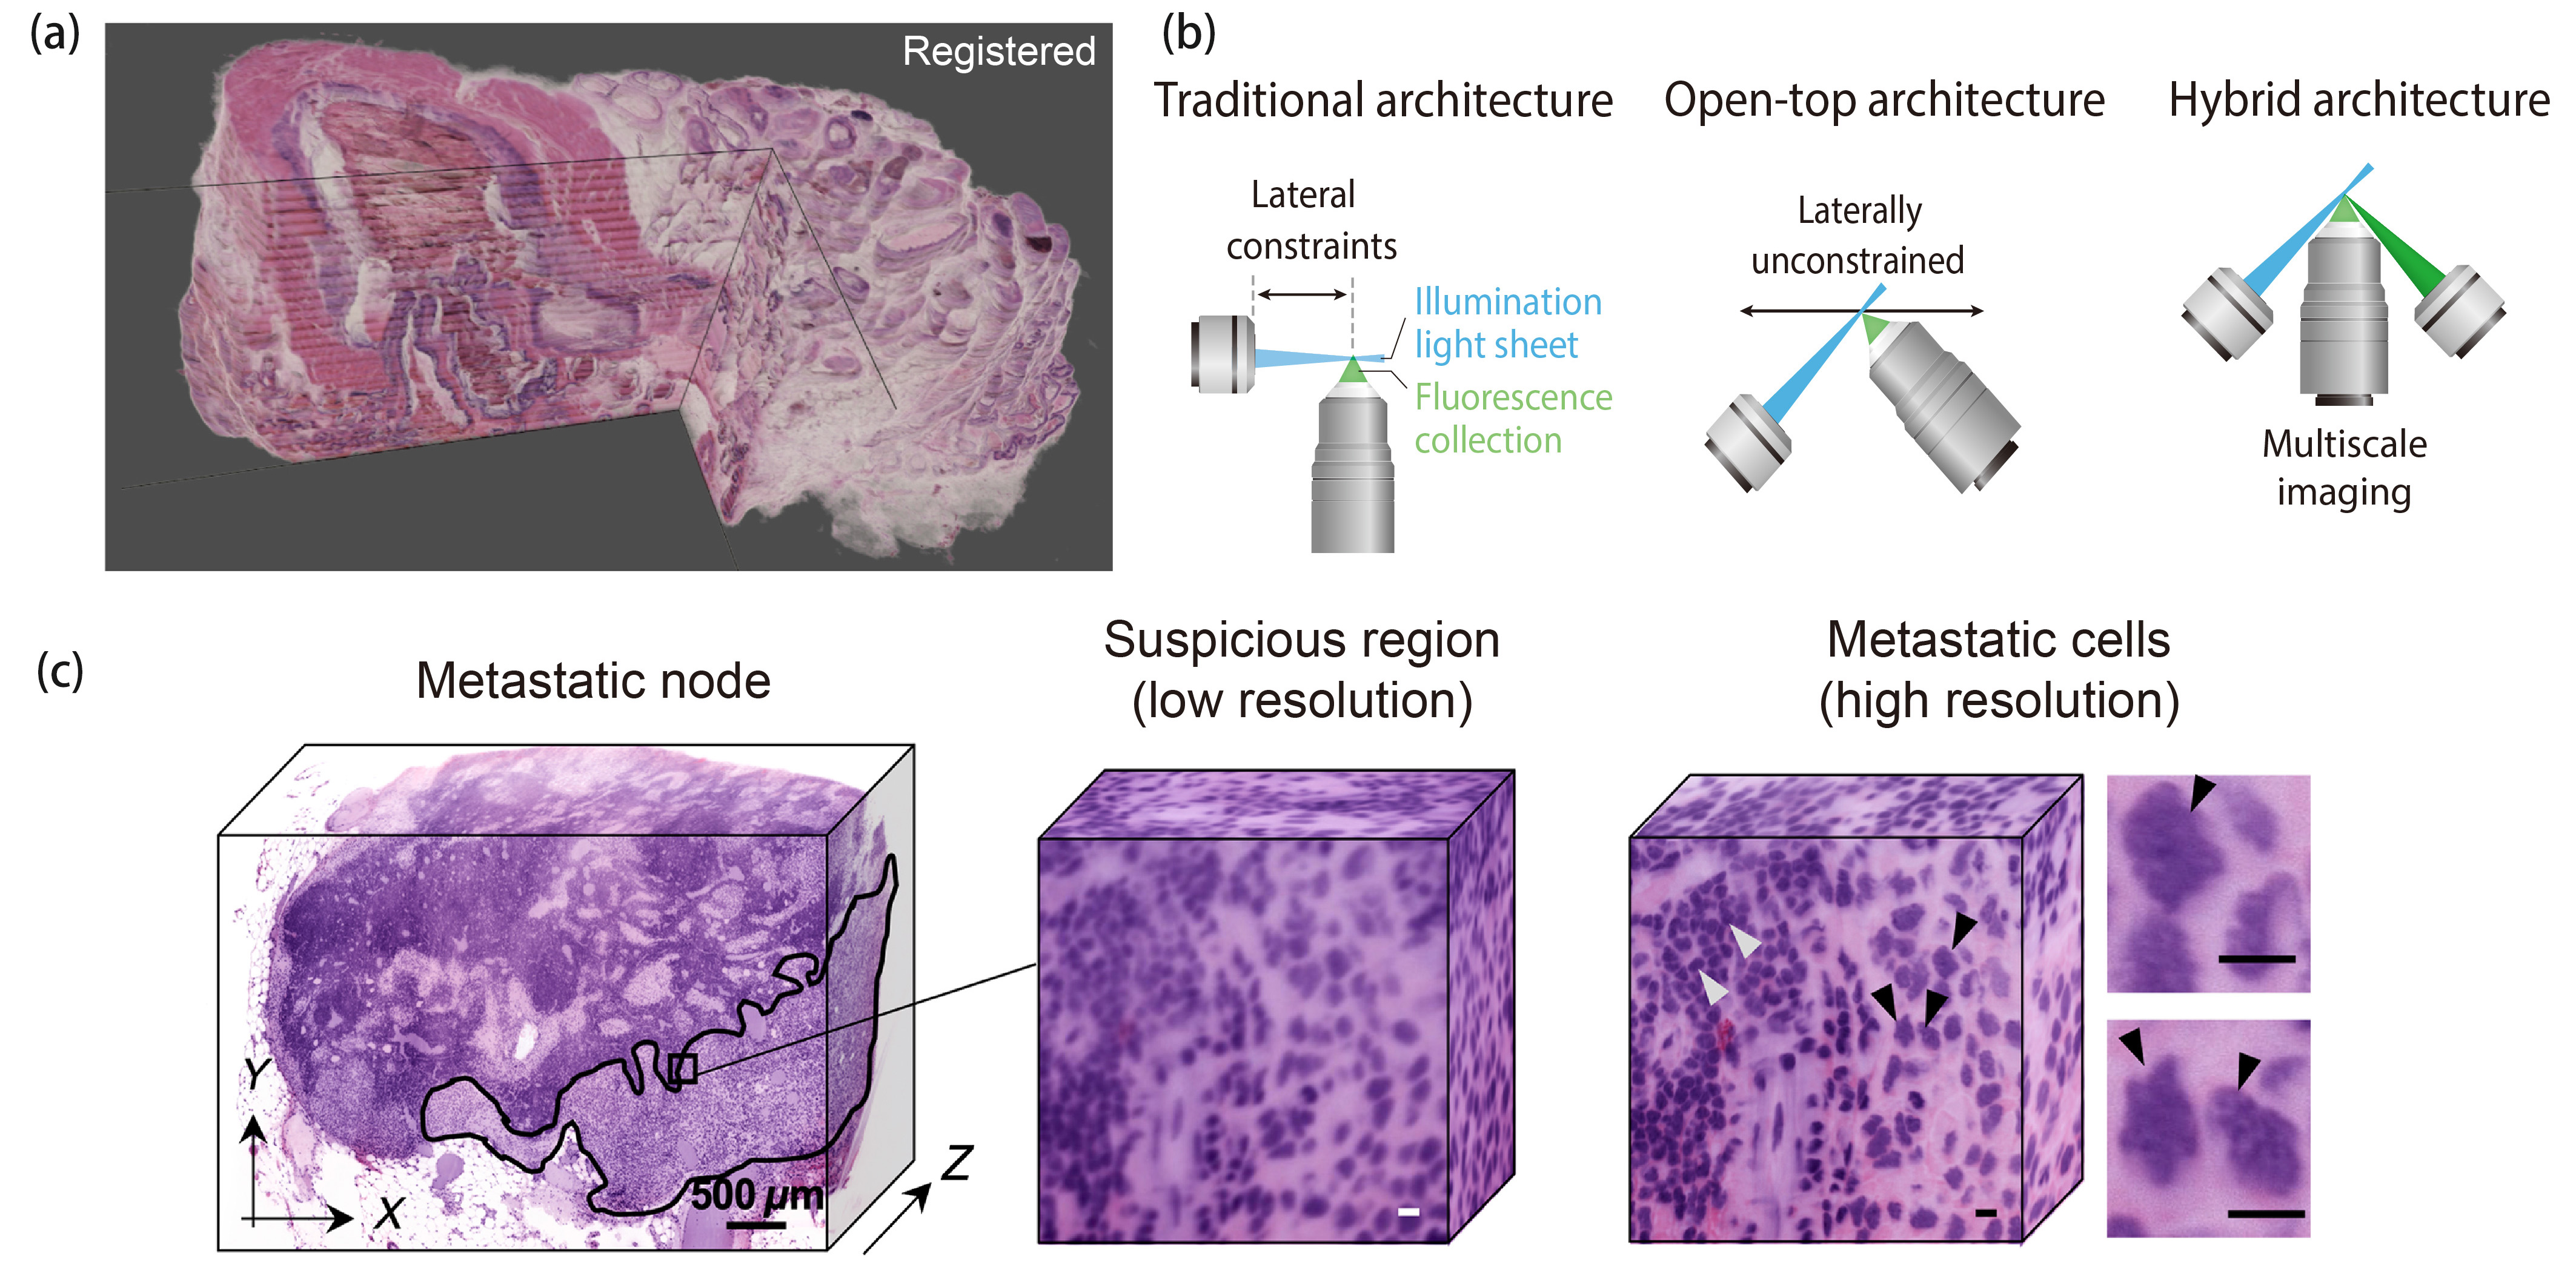
Figure 2. Representative workflows and clinical applications of volumetric pathology. (a) Computational registration of serial histological sections. A representative registered whole-slide image illustrates the recovery of coherent tissue architecture after alignment of serial sections. Reproduced from reference[28]. CC BY 4.0; (b) Major light-sheet microscopy architectures for non-destructive 3D pathology. Conventional orthogonal systems impose lateral constraints on specimen access, open-top systems enable laterally unconstrained imaging, and hybrid open-top systems support multiscale acquisition within the same specimen. Reproduced from reference[4]. CC BY 4.0; (c) Multiresolution 3D pathology of lymph-node specimens for breast cancer staging. A whole-volume lymph-node image is first acquired at low resolution. Regions containing metastatic deposits are then examined at higher resolution to identify metastatic cells within the tissue volume. Reproduced from reference[36]. CC BY 4.0. 3D: three-dimensional.
In parallel, non-destructive volumetric imaging has shifted 3D tissue analysis from post-hoc reconstruction toward direct interrogation of intact specimens[6]. This transition has been driven by two major technological advances. First, tissue-clearing methods reduce refractive-index mismatch and improve optical penetration in thick specimens[29,30]. Second, light-sheet microscopy (LSM) combines plane-selective illumination and camera-based detection, enabling rapid volumetric acquisition with reduced photobleaching[31,32]. However, conventional light-sheet systems typically position the illumination and detection objectives orthogonally around the specimen, imposing constraints on sample size, mounting, and accessibility. Open-top light-sheet (OTLS) microscopy addresses these limitations through an open imaging interface that better accommodates large and irregular clinical specimens[33,34]. More recent hybrid OTLS systems further support multiscale imaging, combining rapid volumetric survey with targeted high-resolution interrogation within the same specimen (Figure 2b)[35].
Despite rapid progress, the performance of non-destructive 3D pathology varies with specimen size[6,30,34]. Achieving homogeneous high-resolution imaging becomes more challenging in centimeter-scale tissues, where probe penetration is often difficult[29,30,34]. Objective working distance, residual refractive-index mismatch, and the field-of-view–resolution trade-off can further influence whole-volume imaging performance[30,33,35]. Consequently, high-resolution volumetric imaging is currently most often demonstrated in millimeter-scale specimens, such as core-needle biopsies[31,34], whereas larger surgical resections may benefit from multiscale strategies that combine lower-resolution 3D imaging with targeted high-resolution acquisition[35,36]. Non-destructive imaging also preserves the specimen for potential downstream or integrated molecular analysis, although compatibility depends on the specific imaging and processing workflow[37].
2.2 Diagnostic value of the z-dimension
Recent studies increasingly suggest that the diagnostic value of 3D histology extends beyond imaging larger tissue volumes. The added z-dimension can reveal pathological features that are incompletely represented in individual sections, particularly when their interpretation depends on spatial extent, continuity, or connectivity[9,36,38-41]. Importantly, this added dimension can provide diagnostic value at two levels: by improving the measurement of pathological features and by changing how these features are structurally interpreted.
First, 3D histology can improve the quantitative assessment of lesion extent and spatial distribution. In breast cancer lymph-node staging, simulated 2D review underestimated the maximum size of metastatic deposits compared with multiresolution 3D pathology, in some cases sufficiently to alter nodal classification (Figure 2c)[36]. Large-scale 3D reconstruction of the human pancreas similarly revealed the abundance, size, and spatial distribution of pancreatic intraepithelial neoplasia (PanIN) lesions, providing a more comprehensive view of precancerous lesion burden than could be obtained from individual sections[42]. In bladder cancer, 3D mapping of lymphatic microvasculature identified spatial descriptors of lymphatic heterogeneity that outperformed 2D measurements for distinguishing higher-stage disease and lymphovascular invasion[41].
Second, the z-dimension can change how pathological structures themselves are interpreted. In prostate cancer, glandular growth patterns traditionally classified as distinct morphologies on thin sections were shown in 3D to converge into a smaller number of continuous architectural subgroups[38]. Quantitative 3D glandular features further improved recurrence-risk stratification compared with matched 2D features[23]. Likewise, in extrahepatic cholangiocarcinoma, structures classified in 2D as detached tumor buds were frequently revealed to represent contiguous protrusions extending from the primary tumor mass[9]. Together, these studies suggest that some conventional histological categories may partially reflect the ambiguity introduced by planar sectioning rather than true biological separation.
3. From Morphology to Molecular Histology
Conventional histology remains foundational because tissue morphology contains rich biological and diagnostic information. However, morphologically similar tissues can differ substantially in cell identity, molecular state, disease progression, and therapeutic response[43-48]. Molecular profiling complements morphology by resolving cell identities, pathway activities, and microenvironmental states within their native spatial context[49]. Histology is therefore expanding from morphological interpretation toward spatially resolved molecular characterization through multiplexed imaging and spatial omics technologies[10,13].
Most molecular tissue profiling methods still operate primarily on thin sections. Growing efforts are therefore extending molecular measurements into intact tissue volumes to relate molecular states directly to 3D tissue architecture. One major direction is multiplexed protein imaging (Figure 3a)[50]. Advances in tissue clearing, immunolabeling, and volumetric fluorescence microscopy have enabled highly multiplexed protein mapping across large intact tissues[49,51,52]. In parallel, vibrational dyes combined with stimulated Raman scattering microscopy have enabled simultaneous visualization of more than 10 protein targets within millimeter-thick tissues (Figure 3b)[53]. Recent workflows combining tissue clearing, multiplexed labeling, light-sheet microscopy, and mass spectrometry have demonstrated proteome-scale molecular mapping in intact 3D specimens[13].
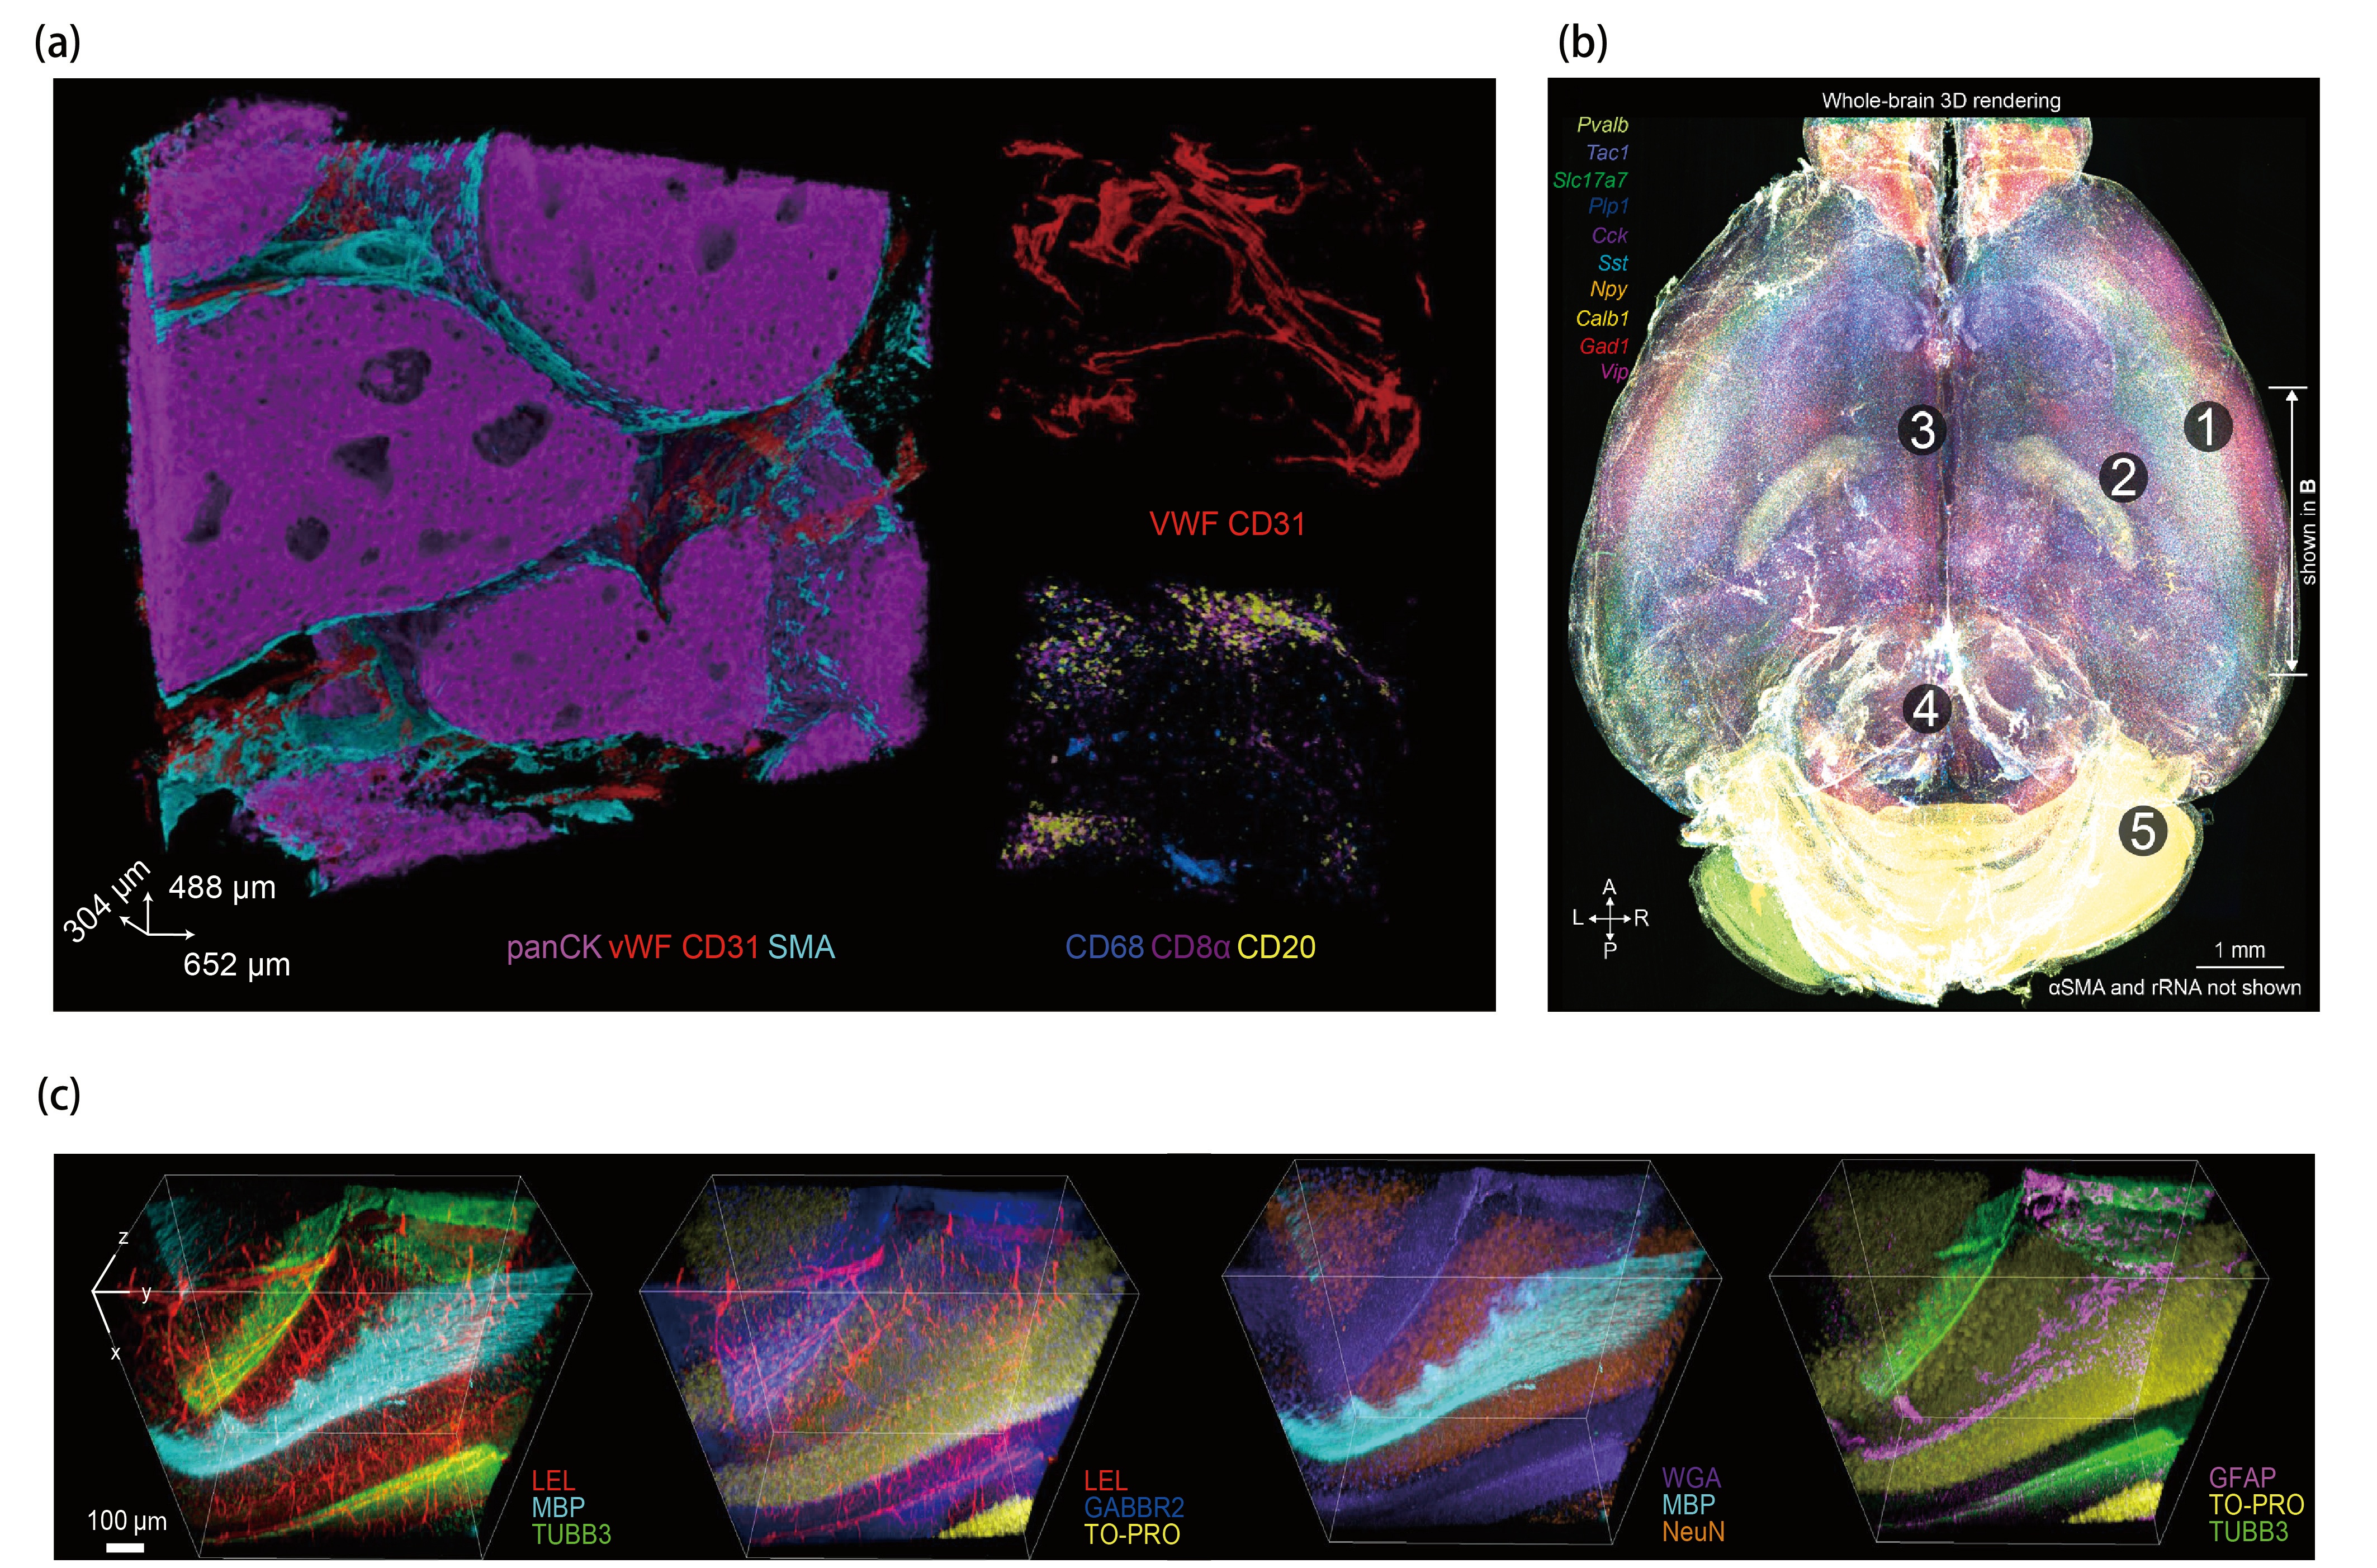
Figure 3. Volumetric molecular imaging approaches for 3D histology. (a) Three-dimensional imaging mass cytometry of human breast carcinoma tissue. Multiplexed metal-tagged antibodies are used to profile serial FFPE breast cancer sections. The reconstructed 3D marker maps reveal epithelial tumor regions, vascular structures, stromal components and immune-cell populations within the tumor microenvironment. Reproduced from reference[50]. CC BY 4.0; (b) Multiplex Raman imaging in cleared thick tissue. Raman-active probes or vibrational labels are imaged by stimulated Raman scattering microscopy. This approach generates multichannel molecular maps within thick tissue volumes. Reproduced with permission from reference[53]. Copyright © 2022 Springer Nature; (c) Whole-brain three-dimensional RNA imaging using multiplexed in situ hybridization. A cleared intact mouse brain is imaged after repeated fluorescence in situ hybridization. Multiple mRNA markers are rendered across the whole-brain volume. Reproduced from reference[54]. CC BY 4.0. 3D: three-dimensional; FFPE: formalin-fixed, paraffin-embedded.
A parallel transition is occurring for RNA analysis. Although spatial transcriptomics (ST) initially developed largely through section-based workflows, efforts to extend transcriptomic profiling into 3D tissues have followed three main directions. First, multiplexed fluorescence in situ hybridization (FISH) has been extended into thick tissues and whole organs through tissue clearing and volumetric imaging (Figure 3c)[54,55], with related approaches combining transcript and protein measurements within the same volumes[12,56]. Second, imaging-based ST methods use iterative barcoding[11,12,57,58]. For example, STARmap employs hydrogel-anchored in situ sequencing to profile RNA directly in thick tissues[10]. Third, serial spatial-transcriptomic sections can be computationally assembled into volumetric gene-expression maps, as demonstrated by platforms such as Open-ST[59].
Beyond mapping molecular distributions, 3D molecular histology is beginning to relate molecular states to tissue organization and function. Integration of volumetric imaging with single-cell transcriptomics and proteomics has revealed distinct molecular identities across anatomically defined bone-marrow compartments and their interactions with neighboring tissues, linking spatial organization to region-specific biological programs[60]. At larger scales, cleared-tissue light-sheet imaging is approaching single-cell censuses across organs and whole organisms, extending molecular histology toward comprehensive spatial cell atlases[61]. Functional molecular readouts are also emerging. For example, intact-tissue click chemistry enables volumetric imaging of covalent drug engagement, adding pharmacological information to 3D molecular histology[62,63].
Despite these advances, the effective depth of 3D molecular profiling remains limited by probe penetration and depth-dependent detection efficiency. In Deep-STARmap and Deep-RIBOmap, for example, transcript read counts declined substantially beyond ~200 μm in 260-μm brain slices[11]. Iterative barcoding further requires robust signal preservation, decoding, and cross-cycle registration[12], which can constrain the tissue depth over which high-plex measurements remain quantitatively reliable. Serial-section reconstruction circumvents penetration limits but introduces distinct challenges, including tissue loss, physical deformation, and spatial misregistration[27,59]. Scaling 3D molecular profiling will therefore depend on improvements in reagent penetration and detection sensitivity, together with more robust computational methods for cross-round and cross-section alignment[7].
4. The Emergence of Label-Free Imaging for 3D Histology
The transition from thin sections to volumetric tissue analysis also highlights a practical limitation of conventional pathology: most established contrast mechanisms rely on exogenous labels[7,64]. Histochemical stains, fluorescent antibodies, and isotope-based reporters provide rich morphological and molecular information, but their dependence on diffusion, incubation, and specimen processing complicates their application to intact 3D tissues[7,64,65]. These constraints have motivated increasing interest in label-free approaches that derive contrast directly from intrinsic biochemical or physical tissue properties[34,66].
Among these approaches, stimulated Raman scattering (SRS) microscopy is particularly relevant to 3D pathology because it combines intrinsic chemical contrast with fresh-tissue compatibility, subcellular resolution, and rapid imaging[67-69]. By detecting molecular vibrational signatures, SRS directly visualizes endogenous tissue biochemical composition without exogenous staining and has demonstrated utility for rapid assessment of tumor architecture and infiltration in cancer pathology[65,67,68]. Although most clinical applications of SRS have focused on planar imaging, recent progress is extending this capability into three dimensions. For example, ultrarapid cleared stimulated Raman with AI (ULTRA) combines rapid tissue clearing with volumetric SRS imaging to generate 3D virtual histology and map depth-dependent glioma infiltration at single-cell resolution[70] (Figure 4a).
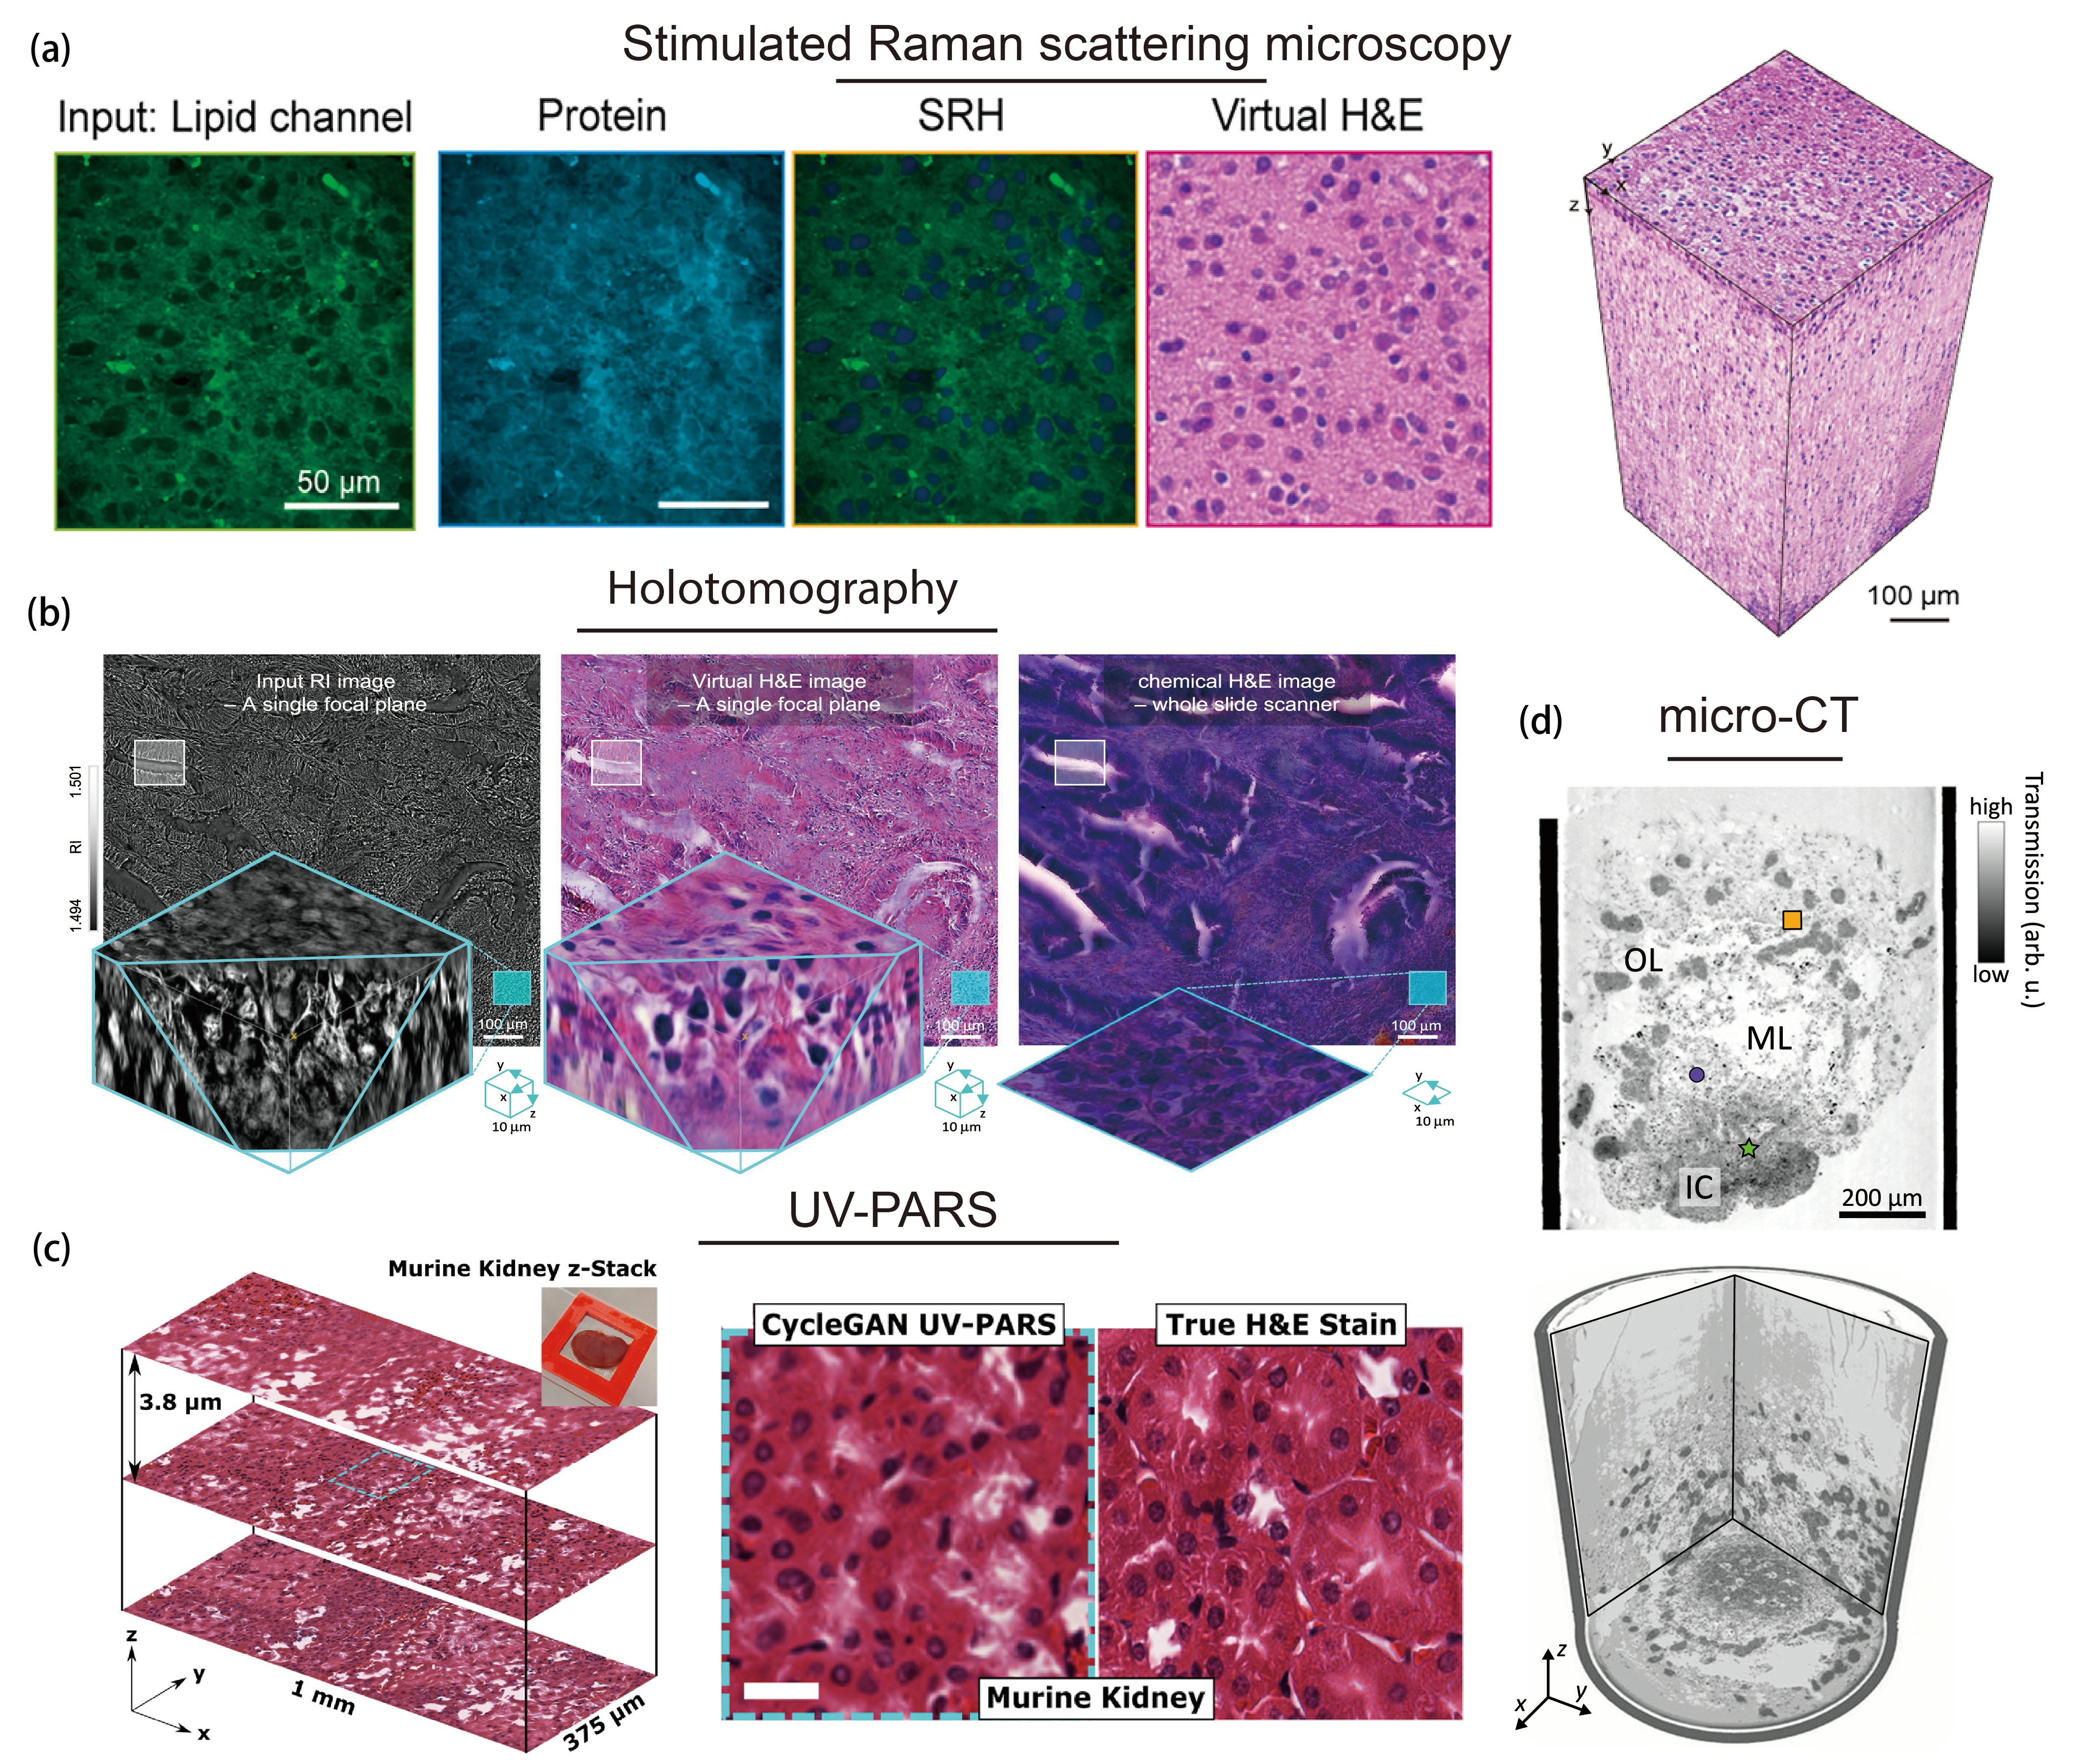
Figure 4. Representative label-free histology modalities for 3D histology. (a) Stimulated Raman scattering microscopy for volumetric virtual histology. Lipid- and predicted protein-sensitive SRS channels are combined to generate SRH and virtual H&E-like contrast. A three-dimensional virtual H&E reconstruction is shown at right. Reproduced with permission from reference[70]. Copyright © 2026 Elsevier; (b) Holotomography-based 3D virtual H&E imaging of an unlabeled colon cancer specimen. A representative refractive-index image and corresponding virtual H&E image are shown, with volumetric insets highlighting microanatomical structure. Reproduced from reference[73]. CC BY 4.0; (c) Multi-layer optical sectioning and virtual histology using UV-PARS and UV scattering microscopy. Reproduced from reference[79]. CC BY 4.0; (d) X-ray phase-contrast micro-computed tomography of a human heart-forming organoid. A virtual cross-section identifies the OL, ML, and IC, and the reconstructed volume is displayed as orthogonal three-dimensional views. Reproduced from reference[84]. CC BY 4.0. 3D: three-dimensional; SRH: stimulated Raman histology; SRS: stimulated Raman scattering; H&E: hematoxylin and eosin; UV-PARS: ultraviolet photoacoustic remote sensing; OL: outer layer; ML: myocardial layer; IC: inner core.
Beyond vibrational imaging, a broader ecosystem of label-free modalities is also expanding the contrast mechanisms available for 3D histology. Quantitative phase imaging (QPI)[71-73], optical coherence tomography (OCT)[74,75], and related interferometric methods primarily extend structural and refractive-index information into 3D space, while harmonic generation microscopy emphasizes extracellular matrix organization[76,77] (Figure 4b). Ultraviolet-excitation and photoacoustic approaches, such as ultraviolet photoacoustic microscopy (UV-PAM)[78] and ultraviolet photoacoustic remote sensing (UV-PARS)[79] (Figure 4c), provide rapid imaging of superficial tissue morphology and surgical margins. Emerging near-infrared-II (NIR-II) autofluorescence approaches further expand the macroscopic reach of intraoperative imaging[80].
Beyond optical microscopy, X-ray phase-contrast micro- and nano-computed tomography (micro-/nano-CT) provide volumetric imaging of thick or optically opaque specimens without physical sectioning (Figure 4d)[81-84]. Recent multimodal studies have further combined micro-CT with light-sheet microscopy to link tissue-scale architecture with cellular features[85], while frameworks such as TriPath illustrate how volumetric data from different imaging modalities can be computationally analyzed within a common framework[86].
A common challenge across these approaches is that endogenous contrast does not necessarily correspond directly to conventional histological representation. Computational strategies are therefore being used to translate label-free measurements into pathology-readable information through virtual staining and AI-assisted interpretation, as discussed in the following section. As label-free imaging expands the range and scale of volumetric tissue measurements, the challenge extends beyond contrast generation to the standardization and interpretation of these signals, providing a foundation for AI-driven virtual histology and molecular prediction.
5. Computational foundations of trustworthy 3D histology
3D histology relies on computational methods to reconstruct, analyze, and translate raw data into biologically meaningful insights[6,7,20]. Errors introduced at one stage can propagate into subsequent analyses, making it important to establish an auditable path from the recorded signal to the reported biological or clinical conclusion. Here, we consider four computational foundations of trustworthy 3D histology: volumetric reconstruction, AI-assisted interpretation, diagnostic modeling, and standardized data infrastructure.
5.1 Computational volumetric reconstruction
For serial-section approaches, 3D reconstruction requires computational alignment to recover tissue geometry from discrete 2D sections. Rigid and deformable registration methods align adjacent images, while frameworks such as CODA and VALIS support reconstruction across larger tissue series[8,27,28]. These methods can correct section deformation but cannot recover material lost during physical sectioning. Generative approaches such as InterpolAI use optical flow to estimate images between adjacent sections, improving apparent continuity across structures such as blood vessels and branching ducts[87]. Importantly, such interpolated information represents computational inference rather than direct measurement and should therefore be distinguished from experimentally acquired data. Non-destructive volumetric imaging avoids inter-section registration but still requires computational processing, including tile stitching[88], multiview fusion[89], and correction of depth-dependent signal attenuation and optical blurring[90]. Across both paradigms, quality control and validation against independent spatial landmarks are important to ensure that reconstructed volumes reflect biological architecture rather than computational artifacts.
5.2 AI-driven virtual histology and molecular prediction
As label-free imaging advances, AI provides a bridge between endogenous imaging contrasts and familiar histological representations. Early virtual-staining frameworks relied largely on paired training datasets and supervised image-to-image (I2I) translation, requiring closely registered input and target images[91]. More recent cycle-consistent learning[69], unpaired diffusion models[92] and self-supervised approaches[70] have reduced dependence on precisely paired datasets and expanded the applicability of virtual staining across imaging conditions and tissue types (Figure 5a).
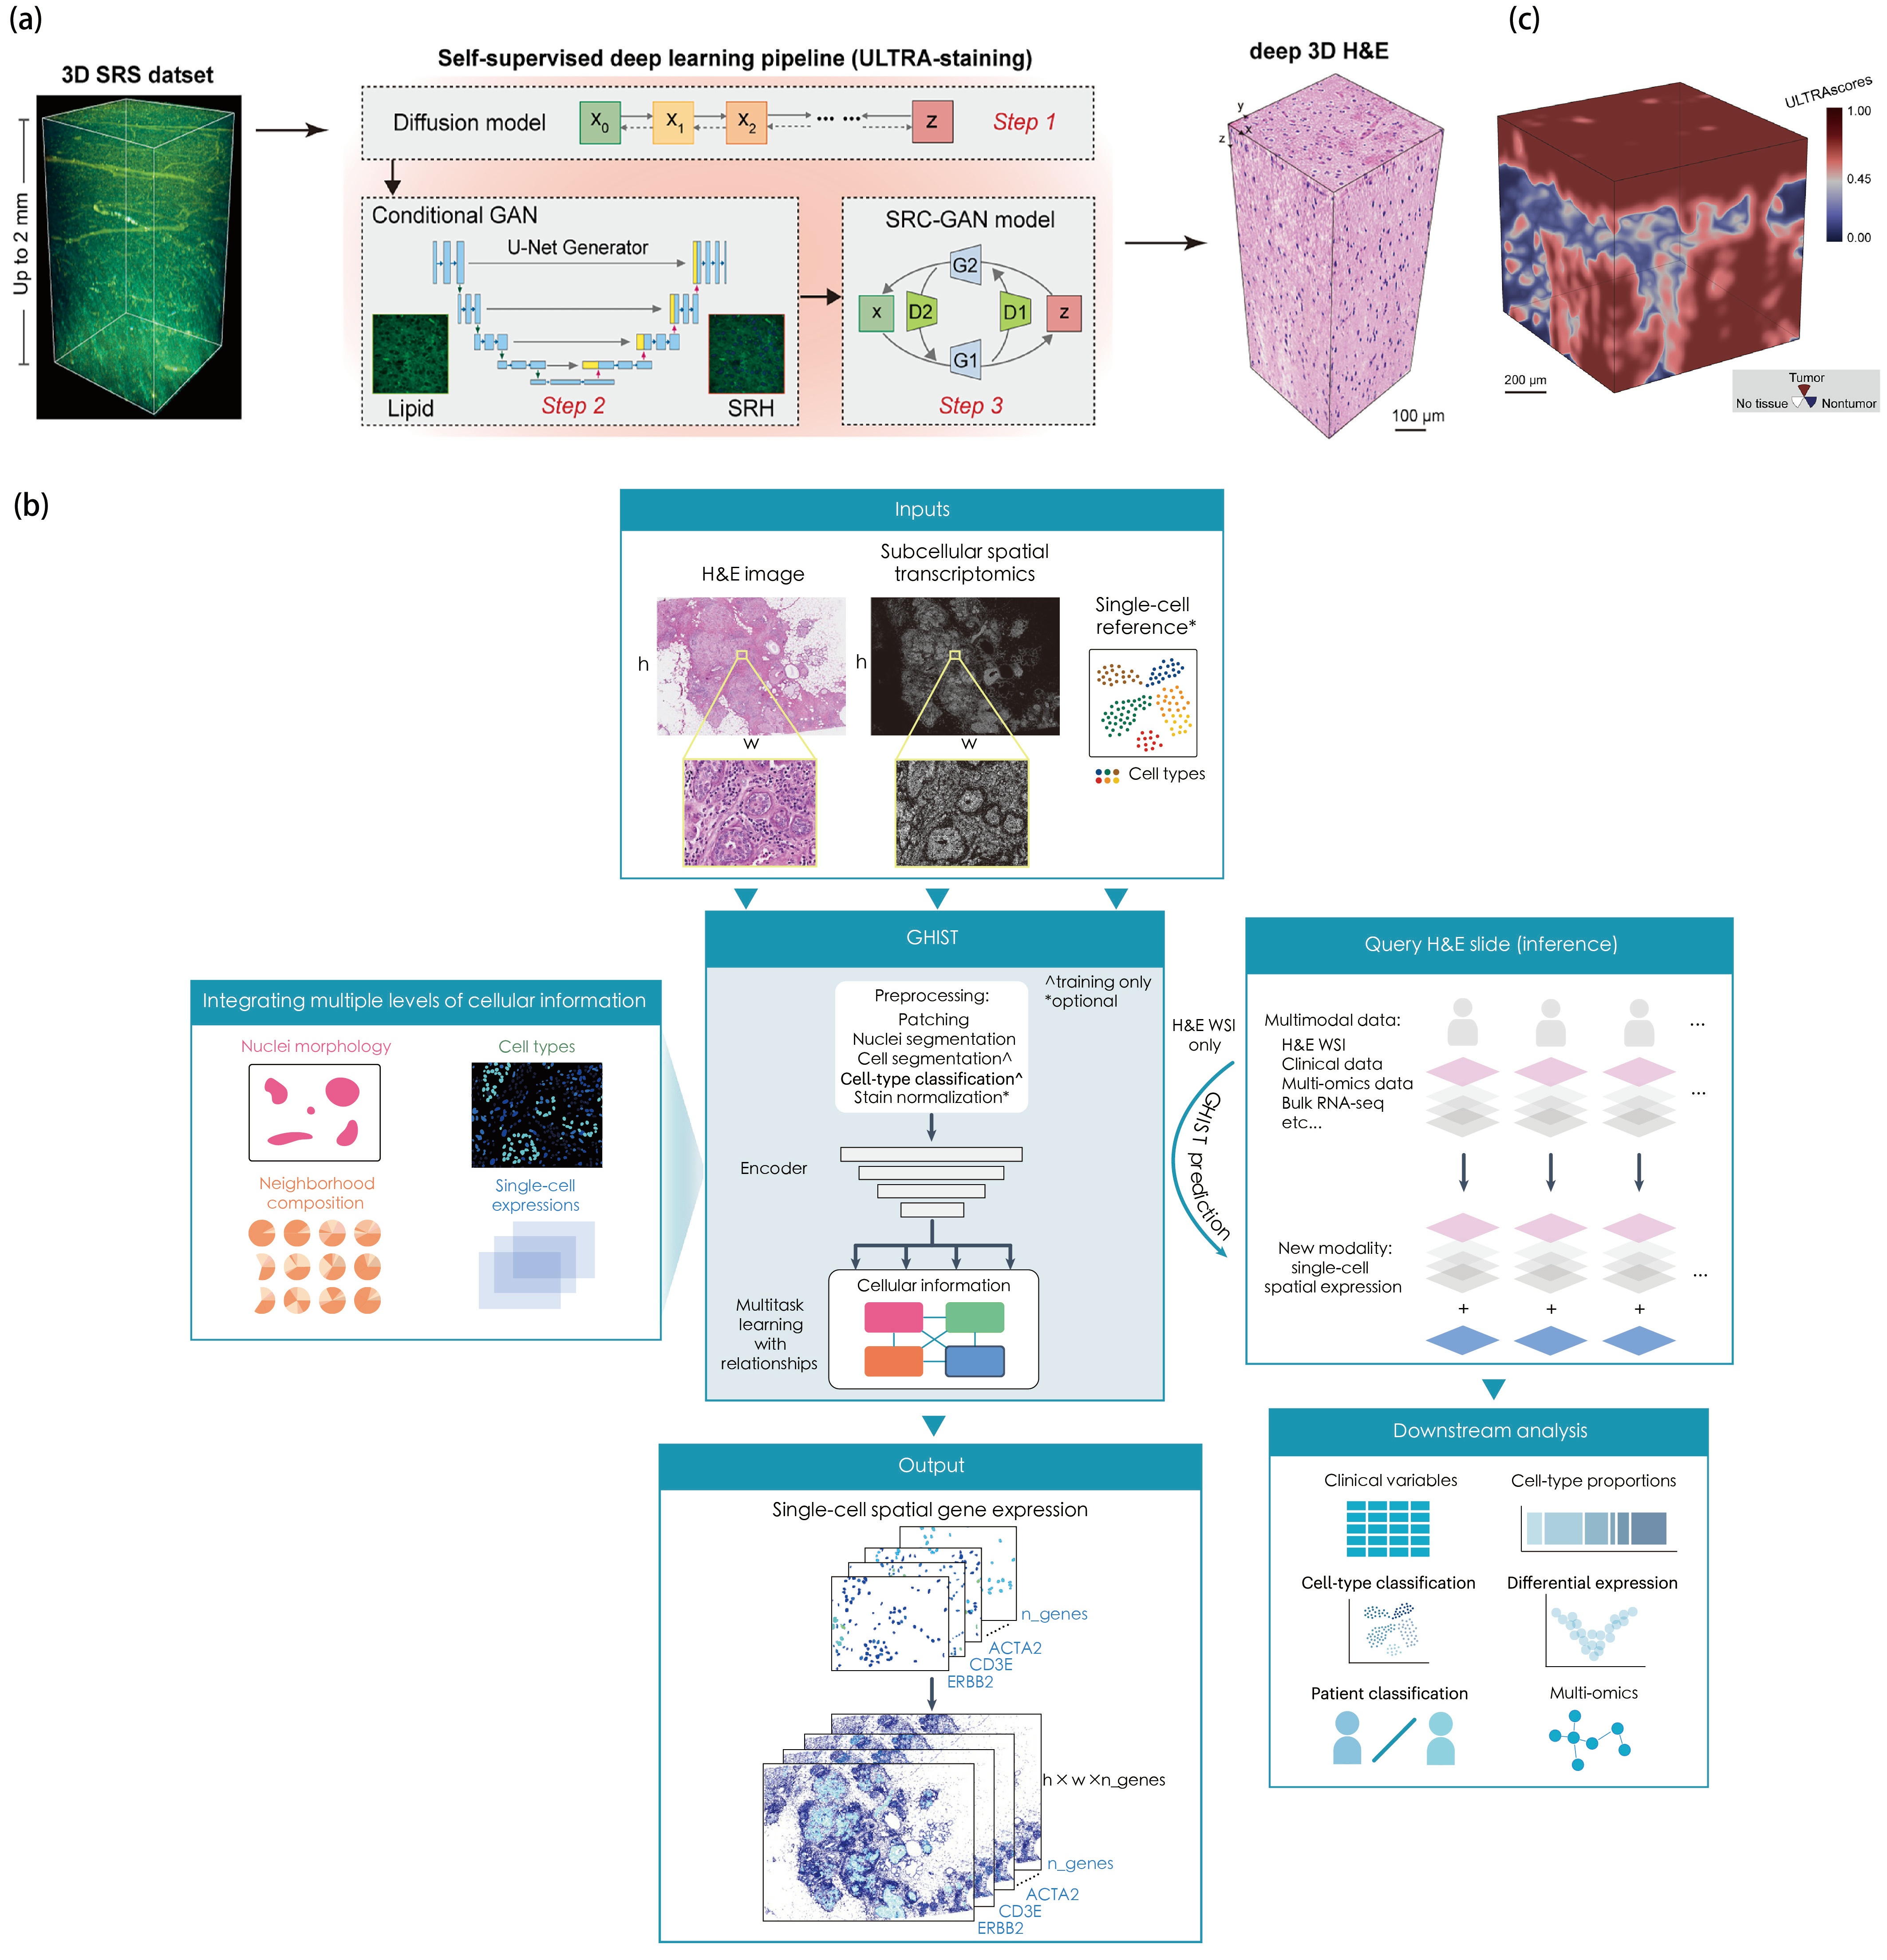
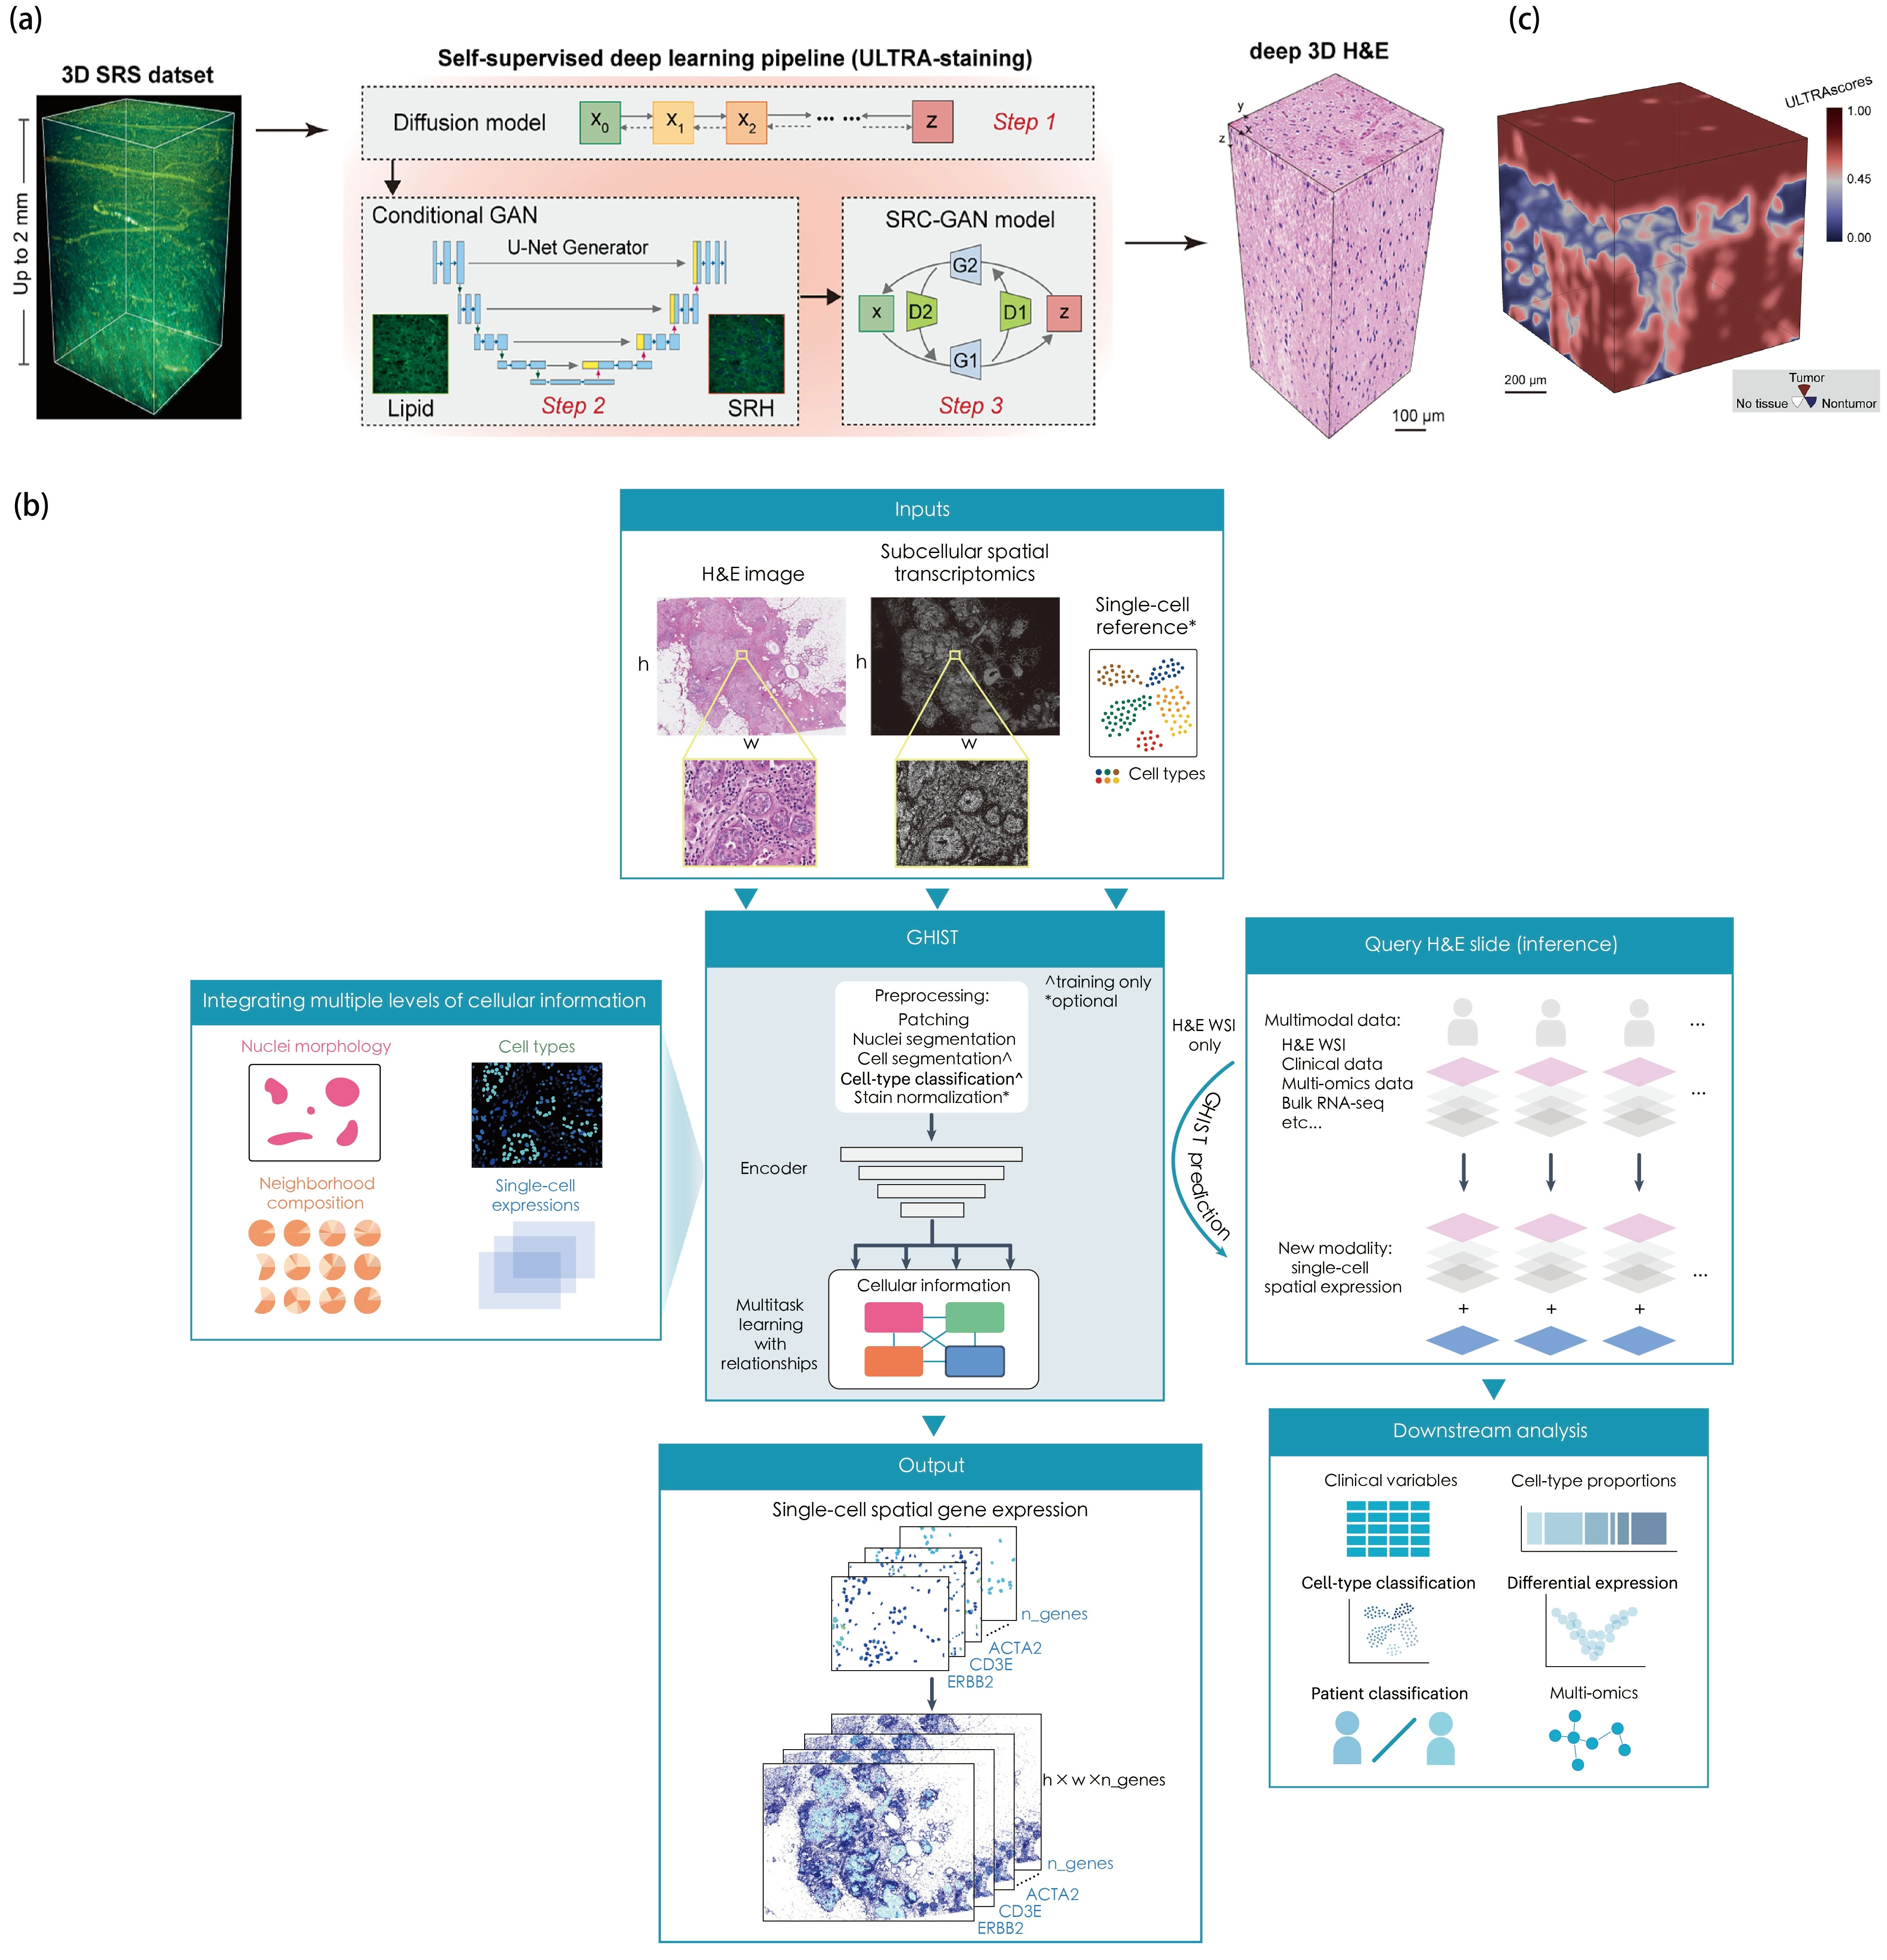
Figure 5. Representative cases of AI-based virtual staining and spatial molecular prediction. (a) A three-dimensional SRS dataset is processed through the multistage ULTRA-staining pipeline, which combines diffusion-based depth-aware denoising, conditional-GAN-based protein-channel prediction, and SRC-GAN-based virtual H&E staining. Reproduced with permission from reference[70]. Copyright © 2026 Elsevier; (b) GHIST integrates H&E images with spatial transcriptomic and single-cell information to predict single-cell spatial gene-expression maps from histology. Reproduced from reference[18]. CC BY 4.0; (c) Three-dimensional tumor infiltration mapping enabled by AI-assisted volumetric histology. Reproduced with permission from reference[70]. Copyright © 2026 Elsevier. AI: artificial intelligence; SRS: stimulated Raman scattering; ULTRA: ultrarapid cleared stimulated Raman with AI; H&E: hematoxylin and eosin; GAN: Generative Adversarial Network; SRC-GAN: stimulated Raman CycleGAN.
Molecular prediction represents a more inferential task. Recent 2D studies have predicted gene-expression patterns and virtual multiplexed protein maps directly from routine histology[18,19,93] (Figure 5b), suggesting that some molecular states have detectable morphological correlates. However, performance in planar sections does not necessarily establish reliable prediction across tissue depth[94]. Emerging frameworks are beginning to integrate volumetric morphology with matched spatial transcriptomics to predict 3D molecular profiles[95], but this direction remains at an early stage and requires validation across independent specimens and clinical cohorts. More broadly, virtual staining and molecular prediction should be interpreted as distinct computational tasks: the former translates measured image contrast into a familiar representation, whereas the latter infers biological information that is not directly measured.
5.3 From 3D segmentation to diagnostic models
The translation of 3D volumetric data into diagnostic and prognostic models generally follows two main strategies: feature-based approaches and end-to-end learning. Feature-based approaches rely on dense 3D segmentation of tissue structures, such as nuclei, glands, and vessels, using deep learning architectures such as U-Net[96,97] or Segment Anything Model (SAM)-based frameworks[98,99]. Once segmented, their 3D geometric and spatial features can be quantified and incorporated into diagnostic or prognostic models. For example, 3D glandular morphology and spatial organization have been used to improve recurrence-risk stratification in prostate cancer[23], while volumetric lymphatic features have shown value for distinguishing higher-stage disease and lymphovascular invasion in bladder cancer[41].
Alternatively, end-to-end approaches directly use 3D tissue volumes as input to predict clinical outcomes without requiring predefined segmentation. For instance, weakly supervised AI platforms such as TriPath have demonstrated that volumetric 3D pathology can outperform conventional 2D slice-based methods and clinical baselines in predicting cancer recurrence[86]. Complementing these predictive approaches, AI-triaged 3D pathology retains the pathologist as the final decision-maker[100,101]. For example, the TRICARE framework leverages spatial context from neighboring depth levels to rank and prioritize high-risk optical sections for focused review, a strategy validated across both prostate and esophageal biopsies[101]. Furthermore, the emergence of 2D pathology foundation models pretrained on diverse multi-institutional datasets may provide transferable representations for 3D pathology and facilitate more robust clinical prediction across patient cohorts[102-104].
5.4 Standardized 3D data, storage and sharing
The transition to 3D histology generates large datasets that can reach terabyte scales, creating new demands for data storage, access, and analysis. Cloud-optimized formats such as OME-Zarr support multiresolution and chunked data access, enabling interactive visualization and patch-wise model training without loading entire tissue volumes into memory[105]. Additionally, universal spatial coordinate frameworks are important to precisely link volumetric images with cellular annotations, molecular measurements, and clinical metadata[106]. Together with adherence to FAIR (Findable, Accessible, Interoperable, and Reusable) principles, these infrastructures will be important for data sharing, computational reproducibility, and future multicenter validation of 3D histology[107].
6. Discussion and Outlook
Overall, the developments discussed throughout this Perspective suggest that histology is transitioning from slide-based toward integrated volumetric tissue analysis. Advances in volumetric imaging, label-free pathology, molecular profiling, and AI are converging to enable tissue architecture, molecular state, and functional organization to be studied within the same spatial context. Although substantial technical and clinical challenges remain, these developments point toward a multidimensional and computationally integrated framework for tissue analysis. Several emerging directions may be particularly important in shaping how 3D histology is integrated into biological research and clinical practice.
6.1 Toward intraoperative 3D pathology
One important emerging direction for 3D histology is intraoperative pathology. Extending 3D histology to this setting requires tissue processing, imaging, and analysis to be completed within clinically actionable timeframes. Recent advances are beginning to address this challenge at different stages of the workflow. OTLS microscopy has enabled rapid volumetric imaging of clinical specimens[31,108], although tissue processing and dye staining remain important determinants of overall turnaround time. Label-free imaging provides a complementary strategy by reducing the need for conventional staining. AI-enhanced SRS has progressed from rapid virtual staining and molecular classification to label-free detection of glioma infiltration in fresh surgical specimens[69,70,109].
Most recently, ULTRA integrated rapid tissue clearing, volumetric SRS imaging, and unsupervised learning into a complete 3D histology workflow within 30 min[70] (Figure 5c). The platform generates formalin-fixed, paraffin-embedded (FFPE)-grade 3D virtual histology at single-cell resolution without physical sectioning or conventional staining, bringing deep 3D histology into an intraoperative timeframe. Importantly, its application to human glioma specimens revealed pronounced depth-dependent heterogeneity at tumor margins and enabled volumetric mapping of glioma infiltration, demonstrating how 3D information can provide additional spatial context for intraoperative assessment. These results establish the feasibility of intraoperative 3D histology, although broader clinical translation will require prospective validation in larger patient cohorts, integration into surgical workflows, and evaluation across other tumor types.
6.2 Toward spatial omics in intact 3D tissues
As discussed above, molecular profiling is beginning to extend from thin sections into thick and intact tissues through multiplexed protein imaging and volumetric spatial transcriptomics. However, current approaches still face trade-offs between molecular depth, imaging depth, and volumetric coverage. For protein imaging in particular, the number of molecular targets that can be measured simultaneously in intact 3D tissues remains substantially lower than the molecular depth accessible by proteomic analysis, while antibody penetration and repeated labeling further constrain large-volume measurements. RNA-based approaches have achieved higher multiplexing in thick tissues, but quantitative performance can still vary with imaging depth.
One possible direction is to combine non-destructive volumetric imaging with targeted downstream molecular profiling. DISCO-MS, for example, integrates whole-specimen clearing and 3D imaging with image-guided tissue extraction and ultrasensitive mass spectrometry, allowing proteome-scale analysis of spatially defined regions while retaining their position within the original 3D tissue context[13]. Such strategies may help bridge the molecular depth of omics measurements with the spatial completeness of volumetric imaging, although molecular analysis still requires physical sampling of selected regions.
A complementary direction is computational molecular inference. Emerging AI frameworks suggest that some spatial molecular states may eventually be predicted directly from volumetric morphology[95], potentially extending molecular information beyond experimentally measured regions. However, these predictions remain indirect and require rigorous validation against matched molecular measurements across tissue depths, specimens, and disease contexts. Direct molecular measurements and AI-inferred molecular maps should therefore be regarded as distinct evidence classes rather than interchangeable readouts[7]. Together, these developments point toward 3D spatial omics workflows that increasingly balance molecular depth, spatial coverage, tissue preservation, and measurement fidelity.
6.3 Integrated morphological and molecular analysis
As 3D histology becomes increasingly multimodal, a key computational challenge is how to integrate morphological and molecular measurements within a common spatial framework. Existing approaches address this problem at different levels. Methods such as SpaGCN incorporate histological features and spatial coordinates into gene-expression analysis to improve spatial-domain identification[110], whereas frameworks such as multi-modal structured embedding (MUSE) jointly embed morphological and molecular features into shared latent representations[111]. Other approaches, including Starfysh, integrate histology with spatial transcriptomics to resolve heterogeneous cellular states and tissue microenvironments[112]. Together, these strategies illustrate a broader transition from parallel analysis of individual modalities toward computational models that explicitly capture relationships between tissue structure and molecular state.
Extending such integration into 3D will require accurate spatial registration across imaging and molecular modalities, harmonization of measurements acquired at different spatial resolutions, and computational representations that preserve both local cellular features and long-range tissue architecture[113,114]. Emerging foundation models for multimodal learning may provide another route by learning transferable representations across histological and molecular data[115,116], although their generalizability across tissues, platforms, and clinical cohorts remains to be established. Ultimately, the goal is not simply to combine more data modalities, but to determine when their integration provides biological or diagnostic information that cannot be obtained from either morphology or molecular profiling alone.
6.4 A staged roadmap for clinical translation
Clinical translation of 3D histology can be considered across three stages. First, technical workflows need to be standardized, including specimen preparation, imaging, volumetric reconstruction, and quality-control criteria, to ensure reproducibility across tissues and centers[34]. Second, clinical utility should be evaluated prospectively against current standards of care using predefined endpoints, particularly in applications where 3D information may improve diagnosis or treatment decisions[117]. Finally, implementation will require integration with routine pathology workflows and digital systems, together with regulatory frameworks for data traceability, quality management, and model monitoring[118]. Progress across these stages will be important for moving 3D histology from technical feasibility toward validated clinical use.
Acknowledgements
The authors declare that ChatGPT 5.6 was used solely for linguistic polishing and language editing during the manuscript preparation process. All core research content, including study design, data synthesis, mechanistic interpretations, conceptual figure design, and structured tables, is original and was not generated using AI tools. The authors reviewed, revised, and approved the final manuscript and take full responsibility for its content.
Authors contribution
He Z: Conceptualization, investigation, writing-original draft, visualization.
Li Y: Investigation, writing-original draft.
Shi L: Conceptualization, supervision, writing-review & editing.
Conflicts of interest
The authors declare no conflicts of interest.
Ethical approval
Not applicable.
Consent to participate
Not applicable.
Consent for publication
Not applicable.
Availability of data and materials
Not applicable.
Funding
We acknowledge support from National Natural Science Foundation of China (Grant No. 22377016), the National Key R&D Program of China (Grant No. 2024YFC3406500) and the Fund of Fudan University and Cao’ejiang Basic Research Program (No. 24FCA08).
Copyright
© The Author(s) 2026.
References
-
1. Bera K, Schalper KA, Rimm DL, Velcheti V, Madabhushi A. Artificial intelligence in digital pathology: New tools for diagnosis and precision oncology. Nat Rev Clin Oncol. 2019;16(11):703-715.[DOI]
-
5. Almagro J, Messal HA, Zaw Thin M, van Rheenen J, Behrens A. Tissue clearing to examine tumour complexity in three dimensions. Nat Rev Cancer. 2021;21(11):718-730.[DOI]
-
7. Ertürk A. Deep 3D histology powered by tissue clearing, omics and AI. Nat Methods. 2024;21(7):1153-1165.[DOI]
-
11. Sui X, Lo JA, Luo S, He Y, Tang Z, Lin Z, et al. Scalable spatial single-cell transcriptomics and translatomics in 3D thick tissue blocks. Nat Methods. 2025;22(12):2574-2584.[DOI]
-
13. Bhatia HS, Brunner AD, Öztürk F, Kapoor S, Rong Z, Mai H, et al. Spatial proteomics in three-dimensional intact specimens. Cell. 2022;185(26):5040-5058.e19.[DOI]
-
16. Cao R, Nelson SD, Davis S, Liang Y, Luo Y, Zhang Y, et al. Label-free intraoperative histology of bone tissue via deep-learning-assisted ultraviolet photoacoustic microscopy. Nat Biomed Eng. 2023;7(2):124-134.[DOI]
-
18. Fu X, Cao Y, Bian B, Wang C, Graham D, Pathmanathan N, et al. Spatial gene expression at single-cell resolution from histology using deep learning with GHIST. Nat Methods. 2025;22(9):1900-1910.[DOI]
-
19. Andani S, Chen B, Ficek-Pascual J, Heinke S, Casanova R, Hild BF, et al. Histopathology-based protein multiplex generation using deep learning. Nat Mach Intell. 2025;7(8):1292-1307.[DOI]
-
21. Tissue histology in 3D. Nat Methods. 2024;21(7):1133.[DOI]
-
25. Mathur R, Wang Q, Schupp PG, Nikolic A, Hilz S, Hong C, et al. Glioblastoma evolution and heterogeneity from a 3D whole-tumor perspective. Cell. 2024;187(2):446-463.e16.[DOI]
-
34. Bishop KW, Erion Barner LA, Han Q, Baraznenok E, Lan L, Poudel C, et al. An end-to-end workflow for nondestructive 3D pathology. Nat Protoc. 2024;19(4):1122-1148.[DOI]
-
37. Bhatia HS, Simons LH, Kuemmerle LB, McCabe C, Jansen S, He Z, et al. DISCO-seq: 3D single-cell transcriptomics of intact biological systems. bioRxiv [Preprint]. 2025.[DOI]
-
42. Braxton AM, Kiemen AL, Grahn MP, Forjaz A, Parksong J, Mahesh Babu J, et al. 3D genomic mapping reveals multifocality of human pancreatic precancers. Nature. 2024;629(8012):679-687.[DOI]
-
44. Capper D, Jones DTW, Sill M, Hovestadt V, Schrimpf D, Sturm D, et al. DNA methylation-based classification of central nervous system tumours. Nature. 2018;555(7697):469-474.[DOI]
-
48. Berglund E, Maaskola J, Schultz N, Friedrich S, Marklund M, Bergenstråhle J, et al. Spatial maps of prostate cancer transcriptomes reveal an unexplored landscape of heterogeneity. Nat Commun. 2018;9:2419.[DOI]
-
49. Chung K, Wallace J, Kim SY, Kalyanasundaram S, Andalman AS, Davidson TJ, et al. Structural and molecular interrogation of intact biological systems. Nature. 2013;497(7449):332-337.[DOI]
-
51. Zhao Y, Bucur O, Irshad H, Chen F, Weins A, Stancu AL, et al. Nanoscale imaging of clinical specimens using pathology-optimized expansion microscopy. Nat Biotechnol. 2017;35(8):757-764.[DOI]
-
52. Ku T, Swaney J, Park JY, Albanese A, Murray E, Cho JH, et al. Multiplexed and scalable super-resolution imaging of three-dimensional protein localization in size-adjustable tissues. Nat Biotechnol. 2016;34(9):973-981.[DOI]
-
54. Murakami TC, Xia M, Maeda Y, Yin Y, Barbano PE, Lin Z, et al. Artificial intelligence-driven whole-brain cell mapping with highly multiplexed in situ hybridization. Neuron. 2026;114(8):1380-1398.e9.[DOI]
-
57. Kanatani S, Kreutzmann JC, Li Y, West Z, Larsen LL, Nikou DV, et al. Whole-brain spatial transcriptional analysis at cellular resolution. Science. 2024;386(6724):907-915.[DOI]
-
59. Schott M, León-Periñán D, Splendiani E, Strenger L, Licha JR, Pentimalli TM, et al. Open-ST: High-resolution spatial transcriptomics in 3D. Cell. 2024;187(15):3953-3972.e26.[DOI]
-
63. Pang Z, Leung VH, Wang CC, Attarpour A, Rinaldi A, Shen H, et al. Mapping cellular targets of covalent cancer drugs in the entire mammalian body. Cell. 2026;189(3):725-738.e15.[DOI]
-
71. Park J, Bai B, Ryu D, Liu T, Lee C, Luo Y, et al. Artificial intelligence-enabled quantitative phase imaging methods for life sciences. Nat Methods. 2023;20(11):1645-1660.[DOI]
-
72. Park Y, Depeursinge C, Popescu G. Quantitative phase imaging in biomedicine. Nat Photonics. 2018;12(10):578-589.[DOI]
-
73. Park J, Shin SJ, Kim G, Cho H, Ryu D, Ahn D, et al. Revealing 3D microanatomical structures of unlabeled thick cancer tissues using holotomography and virtual H&E staining. Nat Commun. 2025;16:4781.[DOI]
-
76. Aghigh A, Bancelin S, Rivard M, Pinsard M, Ibrahim H, Légaré F. Second harmonic generation microscopy: A powerful tool for bio-imaging. Biophys Rev. 2023;15(1):43-70.[DOI]
-
77. Chen X, Nadiarynkh O, Plotnikov S, Campagnola PJ. Second harmonic generation microscopy for quantitative analysis of collagen fibrillar structure. Nat Protoc. 2012;7(4):654-669.[DOI]
-
80. He H, Zhu W, Miao H, Wang S, Du Z, Zhang H, et al. Label-free tissue NIR-II autofluorescence imaging for visualization of human liver malignancy. Nat Biomed Eng. 2026;1-13.[DOI]
-
81. Saccomano M, Albers J, Tromba G, Dobrivojević Radmilović M, Gajović S, Alves F, et al. Synchrotron inline phase contrast µCT enables detailed virtual histology of embedded soft-tissue samples with and without staining. J Synchrotron Rad. 2018;25(4):1153-1161.[DOI]
-
85. Dubey A, Yamashita E, Stangeland B, Abbas I, Fooksman D, Harris RA, et al. Brain tumors induce widespread disruption of calvarial bone and alteration of skull marrow immune landscape. Nat Neurosci. 2025;28(11):2231-2246.[DOI]
-
87. Joshi S, Forjaz A, Han KS, Shen Y, Queiroga V, Selaru FA, et al. InterpolAI: Deep learning-based optical flow interpolation and restoration of biomedical images for improved 3D tissue mapping. Nat Methods. 2025;22(7):1556-1567.[DOI]
-
88. Hörl D, Rojas Rusak F, Preusser F, Tillberg P, Randel N, Chhetri RK, et al. BigStitcher: Reconstructing high-resolution image datasets of cleared and expanded samples. Nat Methods. 2019;16(9):870-874.[DOI]
-
89. Preibisch S, Amat F, Stamataki E, Sarov M, Singer RH, Myers E, et al. Efficient Bayesian-based multiview deconvolution. Nat Methods. 2014;11(6):645-648.[DOI]
-
92. Liu A, Wang X, Cai J, Li C. Score-based diffusion model for Unpaired virtual histology staining. In: Li C, Qin W, Wu J, Zaki N. editors. Computational mathematics modeling in cancer analysis. Cham: Springer; 2026. p. 30-39.[DOI]
-
93. Wu E, Bieniosek M, Wu Z, Thakkar N, Charville GW, Makky A, et al. ROSIE: AI generation of multiplex immunofluorescence staining from histopathology images. Nat Commun. 2025;16:7633.[DOI]
-
94. Wang C, Chan AS, Fu X, Ghazanfar S, Kim J, Patrick E, et al. Benchmarking the translational potential of spatial gene expression prediction from histology. Nat Commun. 2025;16:1544.[DOI]
-
95. Almagro-Pérez C, Song AH, Weishaupt L, Kim A, Jaume G, Williamson DFK, et al. AI-driven 3D spatial transcriptomics. arXiv [Preprint]. 2025.[DOI]
-
97. Çiçek Ö, Abdulkadir A, Lienkamp SS, Brox T, Ronneberger O. 3D U-Net: Learning dense volumetric segmentation from sparse annotation. In: Ourselin S, Joskowicz L, Sabuncu MR, Unal G, Wells W. editors. Medical image computing and computer-assisted intervention–MICCAI 2016. Cham: Springer; 2016. p. 424-432.[DOI]
-
98. Kirillov A, Mintun E, Ravi N, Mao H, Rolland C, Gustafson L, et al. Segment anything. In: 2023 IEEE/CVF international conference on computer vision (ICCV). IEEE; 2023. p. 3992-4003.[DOI]
-
99. Wang H, Guo S, Ye J, Deng Z, Cheng J, Li T, et al. SAM-Med3D: A vision foundation model for general-purpose segmentation on volumetric medical images. IEEE Trans Neural Netw Learn Syst. 2025;36(10):17599-17612.[DOI]
-
101. Gao G, Yan R, Song AH, Hsieh HC, Barner LAE, Wang F, et al. Deep-learning triage of three-dimensional pathology datasets for comprehensive and efficient pathologist assessments. Nat Biomed Eng. 2026.[DOI]
-
109. Hollon T, Jiang C, Chowdury A, Nasir-Moin M, Kondepudi A, Aabedi A, et al. Artificial-intelligence-based molecular classification of diffuse gliomas using rapid, label-free optical imaging. Nat Med. 2023;29(4):828-832.[DOI]
-
111. Bao F, Deng Y, Wan S, Shen SQ, Wang B, Dai Q, et al. Integrative spatial analysis of cell morphologies and transcriptional states with MUSE. Nat Biotechnol. 2022;40(8):1200-1209.[DOI]
-
116. Liu Y, Wang C, Wang Z, Chen L, Li Z, Song J, et al. High-parameter spatial multi-omics through histology-anchored integration. Nat Methods. 2026;23(2):373-386.[DOI]
-
117. Voskuil FJ, Vonk J, van der Vegt B, Kruijff S, Ntziachristos V, van der Zaag PJ, et al. Intraoperative imaging in pathology-assisted surgery. Nat Biomed Eng. 2022;6(5):503-514.[DOI]
Copyright
© The Author(s) 2026. This is an Open Access article licensed under a Creative Commons Attribution 4.0 International License (https://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, sharing, adaptation, distribution and reproduction in any medium or format, for any purpose, even commercially, as long as you give appropriate credit to the original author(s) and the source, provide a link to the Creative Commons license, and indicate if changes were made.
Publisher’s Note
Science Exploration remains a neutral stance on jurisdictional claims in published
maps
and institutional affiliations. The views expressed in this article are solely those
of
the author(s) and do not reflect the opinions of the Editors or the publisher.
Share And Cite


Science Exploration Style
He Z, Li Y, Shi L. Beyond slides: The era of 3D histology. EXO. 2026;1:202622. https://doi.org/10.70401/EXO.2026.0021
Tips
Copy completed.
Submit a Manuscript
Author Instructions
Cite this Article
Article Metrics
0
View
0
Download
Cited
Article Updates

 Get citation
Science Exploration Style

He Z, Li Y, Shi L. Beyond slides: The era of 3D histology. EXO. 2026;1:202622. https://doi.org/10.70401/EXO.2026.0021
copy
Share Link
copy