Autonomic control of myeloid cell biology across tissues

Marie Hartmann
1,2
,
Yamina Hamel
3

,
Mireille Laforge
1,2
,
Christophe Delclaux
1,2,4
,
Peter van Endert
5,6
,
François-Xavier Mauvais
1,2,4,*
*Correspondence to:
François-Xavier Mauvais, NeuroDiderot, INSERM, Université Paris Cité, Paris 75019, France; Institut Hospitalo-Universitaire Robert-Debré du Cerveau de l'Enfant, Paris 75019, France; Service de Physiologie-Explorations Fonctionnelles Pédiatriques, AP-HP, Hôpital Universitaire Robert-Debré, Paris 75019, France.
E-mail: francois-xavier.mauvais@inserm.fr
Myeloid Cells. 2026;1:202608. 10.70401/mc.2026.0010
Received: April 30, 2026Accepted: August 07, 2026Published: August 07, 2026
Abstract
The autonomic nervous system (ANS) regulates myeloid cell biology across lymphoid and non-lymphoid tissues. Sympathetic, parasympathetic, and enteric circuits shape myeloid cell development, positioning or activation, and antigen presentation through norepinephrine, acetylcholine, dopamine and neuropeptides. In primary lymphoid organs, autonomic signals regulate myeloid progenitors and thymic macrophages, shaping the output and functional competence of innate immune compartments. In secondary lymphoid organs, most extensively characterized in the spleen, neural efferent pathways control macrophages, dendritic cells, monocytes and neutrophils, influencing phagocytosis, cytokine production and lymphocyte priming. Distinct neuro-myeloid interactions occur in the gut, where the enteric nervous system is a mandatory relay for parasympathetic signals to intestinal myeloid cells, and in the tumor microenvironment, where sympathetic and dopaminergic signals regulate tumor-associated myeloid subsets in tumor type-specific ways. The functional output of ANS-myeloid communication is guided by tissue context, myeloid cell identity, receptor type, and signal dynamics. The systemic characterization of these neuroimmune variables will be critical to design therapeutic strategies targeting the ANS-myeloid axis in infection, inflammation, autoimmunity and cancer.
Keywords
Autonomic nervous system, macrophages, dendritic cells, antigen presentation, cholinergic anti-inflammatory pathway, adrenergic signaling, neuroimmunology
1. Introduction
The autonomic nervous system (ANS) coordinates involuntary physiological functions through its sympathetic, parasympathetic, and enteric divisions[1], as described by Langley’s concept, a concept recently called into question[2]. Primary and secondary lymphoid organs are densely innervated by sympathetic and parasympathetic nerve fibers[3], as well as sensory fibers. Immune cells express receptors for the ANS neurotransmitters, including catecholamines (epinephrine, norepinephrine (NE) and dopamine), acetylcholine (ACh), and neuropeptides, supporting a direct neuro-immune communication at the molecular level[4] (Table 1). The inflammatory reflex, in which vagal efferents dampen systemic cytokine production through a splenic cholinergic circuit[50], has driven the emergence of bioelectronic medicine in inflammatory disease[51,52]. This communication is reciprocal as myeloid cells can produce and release neurotransmitters[23,53]. In addition, nerve-associated macrophages (NAMs) have been described in multiple tissues including the spleen[54], the lung[55,56], the skin[57], the gut[58] and the adipose tissue[59], where they play context-specific roles ranging from catecholamine degradation to immunoregulation. Importantly, NAMs are defined by their physical proximity to nerve fibers and not by a conserved transcriptional identity, limiting their fine characterization and manipulation in vivo.
Table 1. Principal ANS neurotransmitters and neuropeptides, their receptors on myeloid cells, functional consequences across organs and disease contexts.
| Molecule | Receptor | Cell | Effect | Organ | Refs |
| NE | β2-AR | Macs, Monos | ↓ TNF, IL-6, IL-12; ↑ IL-10; immunosuppressive polarization; ↓ phagocytosis | Spleen, BM, TME, intestine (muscularis) | [5-7] |
| NE | β2-AR | GMPs | ↑ GMP proliferation; expanded myeloid output; MAFB upregulation in CMPs | BM | [8] |
| NE | β2-AR | DCs | ↓ Cross-presentation (Gαi/0-dependent); ↓ MHC-I loading; ↓ CTL priming; ↓ DC maturation; ↑ Treg; IL-10-dependent ↓ CCR7-driven migration | Spleen, LNs, TME | [9-12] |
| NE | β2-AR | MDSCs | ↑ Recruitment and immunosuppressive function; ↑ arginase 1, PD-L1, IL-10, TGF-β; FAO-dependent metabolic reprogramming | TME | [6,13] |
| NE | β2-AR | Macs | Arginase 1+ neurosupportive program; enteric neuronal protection; tonic anti-inflammatory restraint; sympathectomy → colitis | Intestine (muscularis) | [14,15] |
| NE | β2-AR | MARCO+ Macs | ↓ Phagocytosis; ↓ bactericidal function | Spleen | [16,17] |
| NE | β2-AR | Neus | Pro-tumorigenic phenotype; ↑ VEGF, MMPs; ↓ leukocyte motility via vasoconstriction-induced hypoxia | TME, spleen | [18,19] |
| NE | β3-AR | HSPCs, myeloid progenitors | ↑ HSPC proliferation; sex-dimorphic: myeloid skewing (males), B cell expansion (females) | BM | [20] |
| NE | α2-AR | DCs | ↑ Antigen endocytosis via PI3K-ERK1/2; immunostimulatory at brief low-dose exposure | LNs | [21,22] |
| NE | α1-AR | DCs (immature) | ↑ DC migration to draining LN via α1b-AR; absent in mature DCs | LNs, skin | [11,22] |
| ACh | α7-nAChR | Macs | ↓ NF-κB-driven TNF and HMGB1; AC6-cAMP-PKA-CREB signaling; ↓ bactericidal activation | Spleen, intestine (muscularis) | [23-27] |
| ACh | α7-nAChR | DCs | ↓ Antigen processing (uptake preserved); ↓ CD4+ T cell priming (Treg, Th1, Th2, Th17); GTS-21-sensitive, α-BTX-insensitive | Spleen | [28,29] |
| ACh | α7-nAChR | pDCs | ↓ Migration toward lymphoid follicles via Rac1 inactivation (JAK2/caspase-3-dependent) | Intestine | [30] |
| ACh | α7-nAChR | BM-derived myeloid progenitors | CAP competence pre-programming; required for CAP integrity; hematopoietically determined | BM | [31] |
| ACh | α7-nAChR | MDSCs | ↓ Immunosuppressive activity | Spleen, colon | [32] |
| ACh | Muscarinic M1 AChR | Macs, Monos, Neus | Modulation of splenic myeloid numbers and cytokines during sepsis via central cholinergic circuits | Spleen | [33] |
| Dopamine | D3R | DCs | Constitutive ↓ cross-presentation; D3R deficiency → ↑ CTL responses | LNs, spleen, TME | [34,35] |
| Dopamine | D4R | TAMs | ↓ CD206+ immunosuppressive TAMs; ↓ IL-1 via cAMP-PKA; ↑ gemcitabine efficacy in PDAC | TME (PDAC) | [36] |
| Dopamine | D5R (DRD5) | DCs, B cells | ↑ Antigen presentation; JAK1-STAT1; ↑ tumor-specific CD8+ T cells | TME | [37] |
| Dopamine | D1-like receptors | MDSCs | ↓ IFN-γ-induced ERK/JNK and NO; ↓ immunosuppressive function | TME | [38] |
| Dopamine | Dopamine transporter (DAT) | Macs, Monos | Tonic dopamine regulation; DAT deficiency → ↑ MHC-II, ↑ myeloid populations | Spleen, thymus, BM | [39] |
| NPY | Y1 receptor | Macs | ↓ IL-6; modulation of NE co-transmission | Spleen, TME | [40] |
| CART | Not fully characterized | Myeloid cells | ↓ LPS-induced splenic inflammation; parallel CAP-independent anti-inflammatory route | Spleen | [41] |
| VIP | VPAC1/VPAC2 receptors | Macs | ↓ TNF, IL-6, IL-12; anti-inflammatory polarization; ↑ cholesterol efflux; VPAC2 regulated by TLR2/4 via p38 MAPK | Spleen, LN, cardiovascular | [42-44] |
| VIP | VPAC1/VPAC2 receptors | DCs | Tolerogenic DCs → CD4+ and CD8+ Treg; ↓ CCR7, ↑ CCR1 → ↓ migration to draining LNs | Spleen, LNs | [45-48] |
| VIP | VPAC receptors | TAMs | VIP blockade → pro-inflammatory, phagocytic TAM phenotype; ↑ pro-inflammatory/immunosuppressive ratio; synergy with anti-PD-1 | TME (colorectal cancer) | [49] |
Effects listed for individual neurotransmitter-receptor-cell type combinations may vary by organ context; see corresponding sections for organ-specific detail. α1b-AR: α1b-adrenergic receptor; α2-AR: α2-adrenergic receptor; α7-nAChR: α7 nicotinic acetylcholine receptor; AC6: adenylyl cyclase 6; ACh: acetylcholine; AR: adrenergic receptor; β2-AR: β2-adrenergic receptor; β3-AR: β3-adrenergic receptor; BTX: bungarotoxin; CAP: cholinergic anti-inflammatory pathway; CART: cocaine- and amphetamine-regulated transcript; CCR1: C-C chemokine receptor type 1; CCR7: C-C chemokine receptor type 7; ChAT: choline acetyltransferase; CMP: common myeloid progenitor; CTL: cytotoxic T lymphocyte; cAMP: cyclic adenosine monophosphate; CREB: cAMP response element-binding protein; CXCL12: C-X-C motif chemokine ligand 12; D3R: dopamine D3 receptor; D4R: dopamine D4 receptor; D5R: dopamine D5 receptor; DA: dopamine; DAT: dopamine transporter; DC: dendritic cell; ERK: extracellular signal-regulated kinase; FAO: fatty acid oxidation; GMP: granulocyte-macrophage progenitor; HMGB1: high-mobility group box 1 protein; HSPC: hematopoietic stem and progenitor cell; IFN: interferon; IL: interleukin; IRAK4: IL-1 receptor-associated kinase 4; JAK: Janus kinase; JNK: c-Jun N-terminal kinase; LN: lymph node; LPS: lipopolysaccharide; Mac: macrophage; MAFB: musculoaponeurotic fibrosarcoma oncogene homolog B; MAPK: mitogen-activated protein kinase; MARCO: macrophage receptor with collagenous structure; MDSC: myeloid-derived suppressor cell; MHC: major histocompatibility complex; MMP: matrix metalloproteinase; Mono: monocyte; MyD88: myeloid differentiation primary response 88; NE: norepinephrine; Neu: neutrophil; NF-κB: nuclear factor kappa B; NO: nitric oxide; NPY: neuropeptide Y; pDC: plasmacytoid dendritic cell; PDAC: pancreatic ductal adenocarcinoma; PD-L1: programmed death-ligand 1; PI3K: phosphoinositide 3-kinase; PKA: protein kinase A; Rac1: Ras-related C3 botulinum toxin substrate 1; STAT: signal transducer and activator of transcription; TAM: tumor-associated macrophage; TAP: transporter associated with antigen processing; TGF: transforming growth factor; TLR: Toll-like receptor; TME: tumor microenvironment; TNF: tumor necrosis factor; Treg: regulatory T cell; VEGF: vascular endothelial growth factor; VIP: vasoactive intestinal peptide; VPAC: vasoactive intestinal peptide receptor; GTS-21: 3-[(2,4-dimethoxy)benzylidene]-anabaseine.
Myeloid cells including monocytes, macrophages, dendritic cells (DC), and neutrophils regulate tissue homeostasis[60-62], inflammation, and adaptive immunity through antigen presentation[63,64]. Their regulation by the ANS remains underexplored, relative to lymphocyte-focused neuroimmunology[65]. As examples, autonomic neuropathies are associated with dysregulation of innate immune responses and increased susceptibility to infection and chronic inflammation[66-68]. Chronic psychological stress drives sustained sympathetic activation[69] through the central autonomic network (CAN), integrating cognitive, emotional or visceromotor signals via the insular cortex, amygdala, hypothalamus and nucleus tractus solitarius[70], and durably alters myeloid cell output[71-73], polarization[72,74], and tissue distribution[75]. The nature of ANS control over myeloid cells varies with tissue, myeloid cell type, pathophysiological context, and the neural circuit engaged, precluding a simple directionality. As an illustration, the same adrenergic signal suppresses macrophage cytokine production, drives immunosuppressive myeloid expansion in tumors, yet protects remote organs from ischemic injury, and shapes DC antigen cross-presentation through mechanisms varying with receptor subtype, signal strength, and tissue context. We first outline ANS anatomy and innervation of immune organs (Table 1, Figure 1), then examine organ-specific evidence across primary lymphoid organs, spleen, lymph nodes, intestine, and tumor microenvironment (TME).
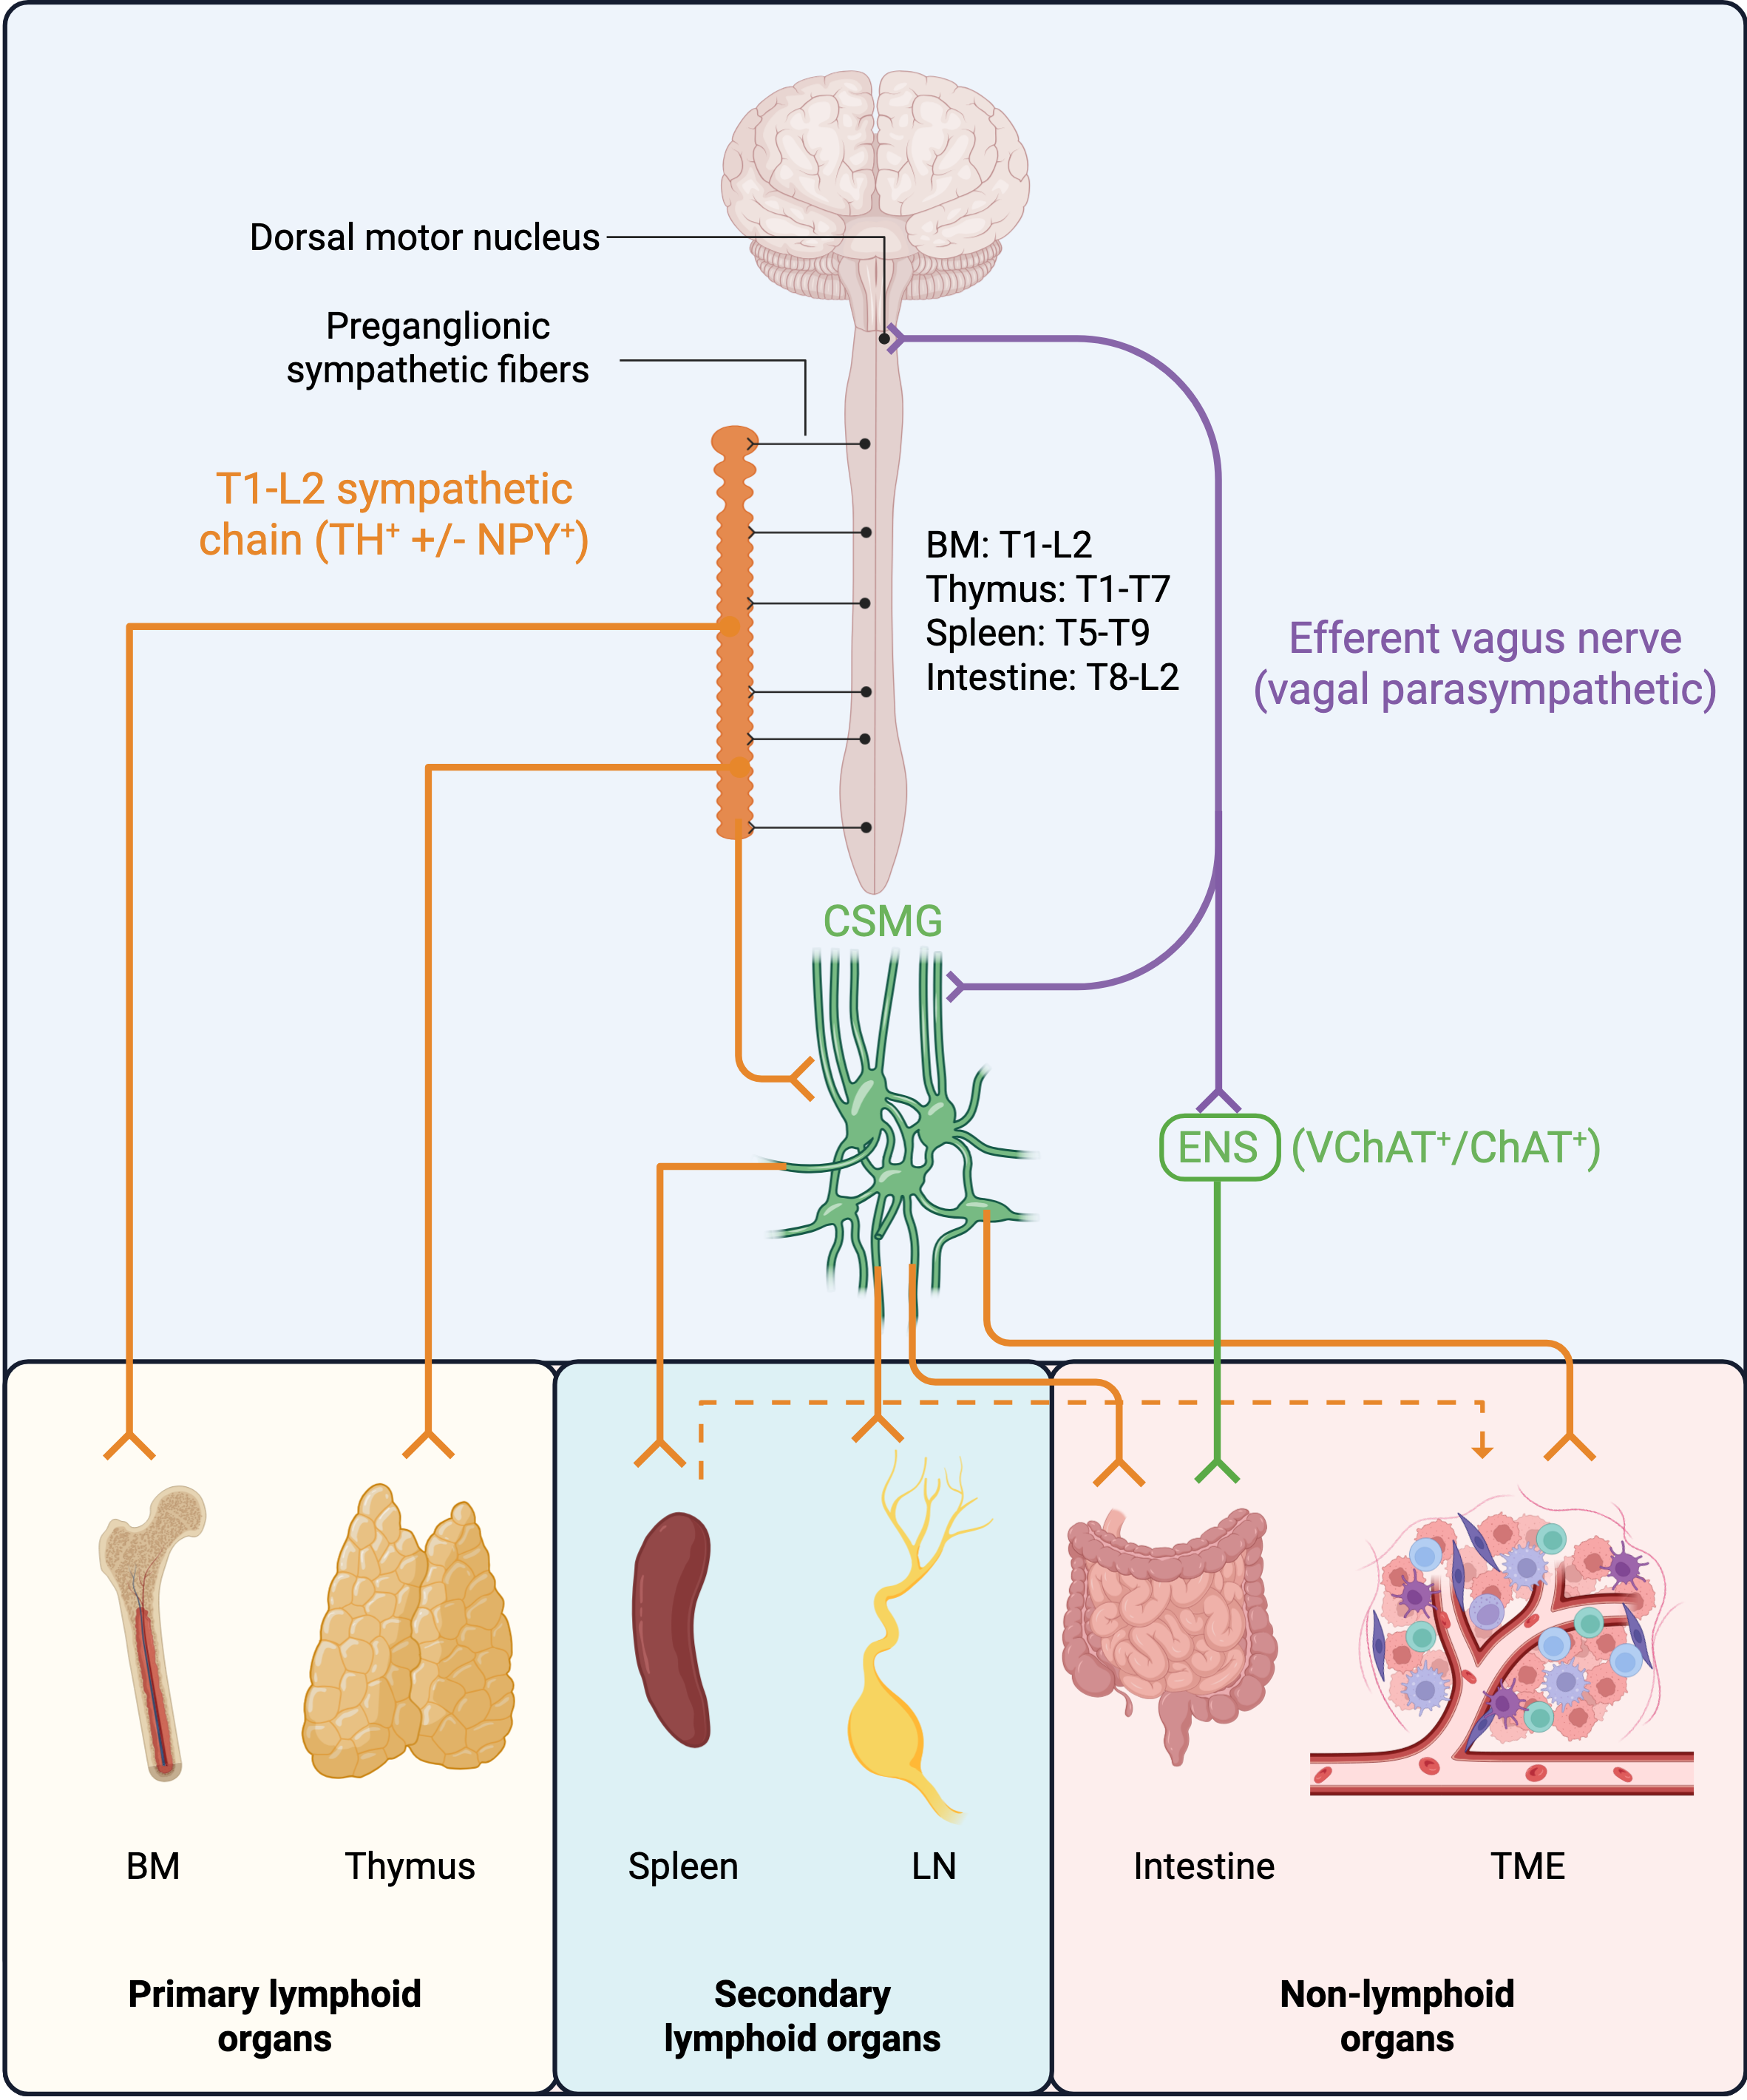
Figure 1. Anatomical organization of autonomic nervous system innervation of myeloid cell compartments. The sympathetic nervous system originates from the thoracolumbar spinal cord and projects via the paravertebral sympathetic chain (orange) expressing TH and/or NPY to the CSMG (green), from which postganglionic noradrenergic fibers innervate the spleen, mesenteric lymph nodes, intestinal muscularis, and tumor microenvironment. BM receives sympathetic innervation via perivascular fibers tracking along nutrient arteries from the paravertebral chain. The thymus receives sympathetic innervation via cervical and stellate ganglia. The parasympathetic vagus nerve originates from the dorsal motor nucleus of the brainstem and projects to the CSMG, from which postganglionic sympathetic fibers convey vagal anti-inflammatory signals to the spleen and LN. In the intestine, vagal efferents terminate directly within myenteric ganglia of the ENS (green), which constitutes an obligatory relay to muscularis macrophages via α7 nicotinic acetylcholine receptors. Myenteric ganglia express ChAT and VChAT. Sympathetic fibers independently innervate muscularis macrophages via β2-adrenergic receptor. In the TME, sympathetic innervation operates through both intratumor nerve sprouting and systemic stress-driven mobilization of myeloid cells from the splenic reservoir (dashed arrow). Myeloid cells themselves produce and release neurotransmitters, contributing to bidirectional neuro-immune communication. Created in BioRender. Mauvais FX. (2026) https://BioRender.com/ncg5aqa. TH: tyrosine hydroxylase; NPY: neuropeptide Y; CSMG: celiac-superior mesenteric ganglia; BM: bone marrow; LN: lymph nodes; ENS: enteric nervous system; ChAT: choline acetyltransferase; VChAT: vesicular acetylcholine transporter; TME: tumor microenvironment
2. Main Body
2.1 General anatomical and functional architecture of the ANS
2.1.1 ANS anatomical organization and innervation of lymphoid organs
The ANS comprises three divisions[76]. The sympathetic nervous system (SNS) originates from thoracolumbar preganglionic neurons (T1-L2) that synapse in paravertebral and prevertebral ganglia, notably the celiac and superior mesenteric ganglia, and then project to visceral organs and lymphoid tissues[76,77]. Sympathetic fibers release NE, neuropeptide Y (NPY), and in some branches, ACh. The vagus nerve provides approximately 75% of parasympathetic outflow and projects from the dorsal motor nucleus of the brainstem to the celiac-superior mesenteric ganglia (CSMG), and via relay neurons to abdominal viscera and lymphoid organs, with ACh as its principal neurotransmitter[77]. The enteric nervous system (ENS), embedded in the gastrointestinal wall, forms a semi-autonomous network that is the main neural interface between the ANS and intestinal immune cells[77]. In addition, sympathetic terminals co-release NPY[40] and cocaine- and amphetamine-regulated transcript (CART) peptide[41], whereas parasympathetic terminals co-release vasoactive intestinal peptide (VIP)[77]. Dopamine, although primarily a central nervous system neurotransmitter, is also produced by peripheral sympathetic terminals and immune cells, and acts on myeloid and lymphoid populations[39,78].
All primary and secondary lymphoid organs receive ANS innervation with marked differences in density, distribution, and functional consequences across tissues. Sympathetic fibers reach bone marrow hematopoietic compartments along vasculature[20,79], and the thymus receives noradrenergic innervation near cortical and medullary DCs and macrophages[80,81]. The spleen is the most extensively innervated lymphoid organ: noradrenergic fibers enter along the splenic artery, branch into trabeculae, and penetrate white pulp periarteriolar lymphoid sheaths (PALS), marginal zone and red pulp, reaching distinct macrophage and DC subsets[17,82-84]. Lymph nodes receive sympathetic innervation near high endothelial venules, subcapsular sinus macrophages, and multiple DC subsets[85,86]. In the intestine, vagal efferent fibers terminate within the myenteric plexus around enteric neurons[15,87-89], rather than forming direct contacts with lamina propria macrophages, establishing the ENS as an obligatory relay for parasympathetic signals to intestinal myeloid cells (Figure 1).
2.1.2 Functional evidence supporting an ANS regulation of myeloid cells
Chemical sympathectomy with 6-hydroxydopamine (6-OHDA), which selectively destroys catecholaminergic nerve terminals, reproducibly alters myeloid cell numbers, tissue distribution, and functional responses across multiple organs[90-92]. Vagus nerve stimulation (VNS) suppresses systemic macrophage cytokine production and confers protection against organ injury in experimental models of inflammation[93] and ischemia-reperfusion[94,95]. These studies demonstrate that ANS tone actively shapes myeloid cell output but carry significant caveats: 6-OHDA depletes all sympathetic terminals indiscriminately, VNS activates both afferent and efferent fibers simultaneously, and neither permits cell type-specific conclusions.
Immune cells themselves produce and release neurotransmitters: macrophages, and monocytes express tyrosine hydroxylase (TH) and synthesize catecholamine[96]; choline acetyltransferase (ChAT)-expressing T cells release ACh in lymphoid organs[97,98]; and dopamine transporter (DAT)-expressing macrophages actively regulate local dopamine bioavailability[53]. Pharmacological studies using adrenergic or cholinergic agonists and antagonists perturb both neural and immune-cell-derived neurotransmitter signaling.
Several principles apply across organ contexts. First, receptor subtype, signal concentration and duration determine functional outcome. Brief, low-concentration NE enhances DC antigen handling[99] while sustained high-concentration NE suppresses it, and co-released NPY acts non-additively on myeloid targets[100]. Second, myeloid cell activation state critically modulates the response: adrenergic and cholinergic effects interact with concurrent Toll-like receptor (TLR), cytokine, and microenvironmental signals to produce outcomes unpredictable from neurotransmitter pharmacology alone. Third, physical proximity between nerve terminals and myeloid cells is a prerequisite for direct neuro-myeloid communication but is not sufficient to establish it. In this review, anatomical data are used to identify where neuro-myeloid communication is structurally possible; functional regulation is indicated wherever receptor-specific, cell type-restricted or optogenetic evidence is available, and pharmacological data are presented with their inherent limitations elsewhere.
2.2 Primary lymphoid organs
Primary lymphoid organs occupy a distinct position in ANS-myeloid regulation: autonomic signals here act on myeloid progenitors prior to the establishment of tissue-specific identity, regulating the quantitative and qualitative output of the myeloid compartment before it is deployed to peripheral tissues. Both the bone marrow and thymus are innervated by sympathetic fibers, establishing a structural framework through which the ANS can influence early hematopoietic[101] and thymocyte-dependent processes[102].
2.2.1 Bone marrow
2.2.1.1 Anatomical organization
In the bone marrow, sympathetic fibers expressing TH and/or NPY track along the vasculature and extend into hematopoietic niches, in proximity to progenitor populations[20,79,101]. Parasympathetic bone marrow innervation has been underexplored and currently lacks neuroanatomical evidence[101]. Hematopoietic progenitors express adrenergic receptors, most notably β2-adrenergic receptors (β2-ARs), as well as β3-ARs. These include granulocyte-macrophage progenitors (GMPs), monocyte precursors, and developing DCs, suggesting that sympathetic signaling may directly modulate early stages of myeloid cell development[8,101].
2.2.1.2 Sympathetic regulation of myeloid progenitor output
In mice, chronic NE elevation, as in diabetic animals, expands myeloid progenitor pools via β2-AR, whereas disruption of sympathetic signaling reduces GMP proliferation and myeloid output[8]. This regulatory axis is reinforced by a local amplification loop: TH-expressing leukocytes in the bone marrow produce catecholamines that act in concert with neuronal inputs to sustain GMP expansion[20]. The axis is sexually dimorphic: β3-AR signaling drives myeloid progenitor expansion in male mice, whereas sympathetic activity preferentially expands B cell progenitors in females[103] (Figure 2). In multiple myeloma, β-adrenergic signaling promotes myeloid lineage commitment in human hematopoietic stem and progenitor cells (HSPCs) through V-maf musculoaponeurotic fibrosarcoma oncogene homolog B (MAFB) upregulation and GATA-binding factor 1 (GATA1) repression in common myeloid progenitors and GMPs; propranolol reverses this myeloid bias[104]. Central circuits involving the motor cortex and central amygdala also control neutrophil and monocyte mobilization through sympathetic projections to the bone marrow[105]. Sympathetic neuropathy within the bone marrow, a common feature in hematological malignancies, is associated with aberrant vasculature and myeloid-biased hematopoiesis[106]. Central metabolic signals converge on this axis via leptin-driven hypothalamic 5’ adenosine monophosphate-activated protein kinase (AMPK) activation increasing sympathetic outflow to hematopoietic compartments[107].
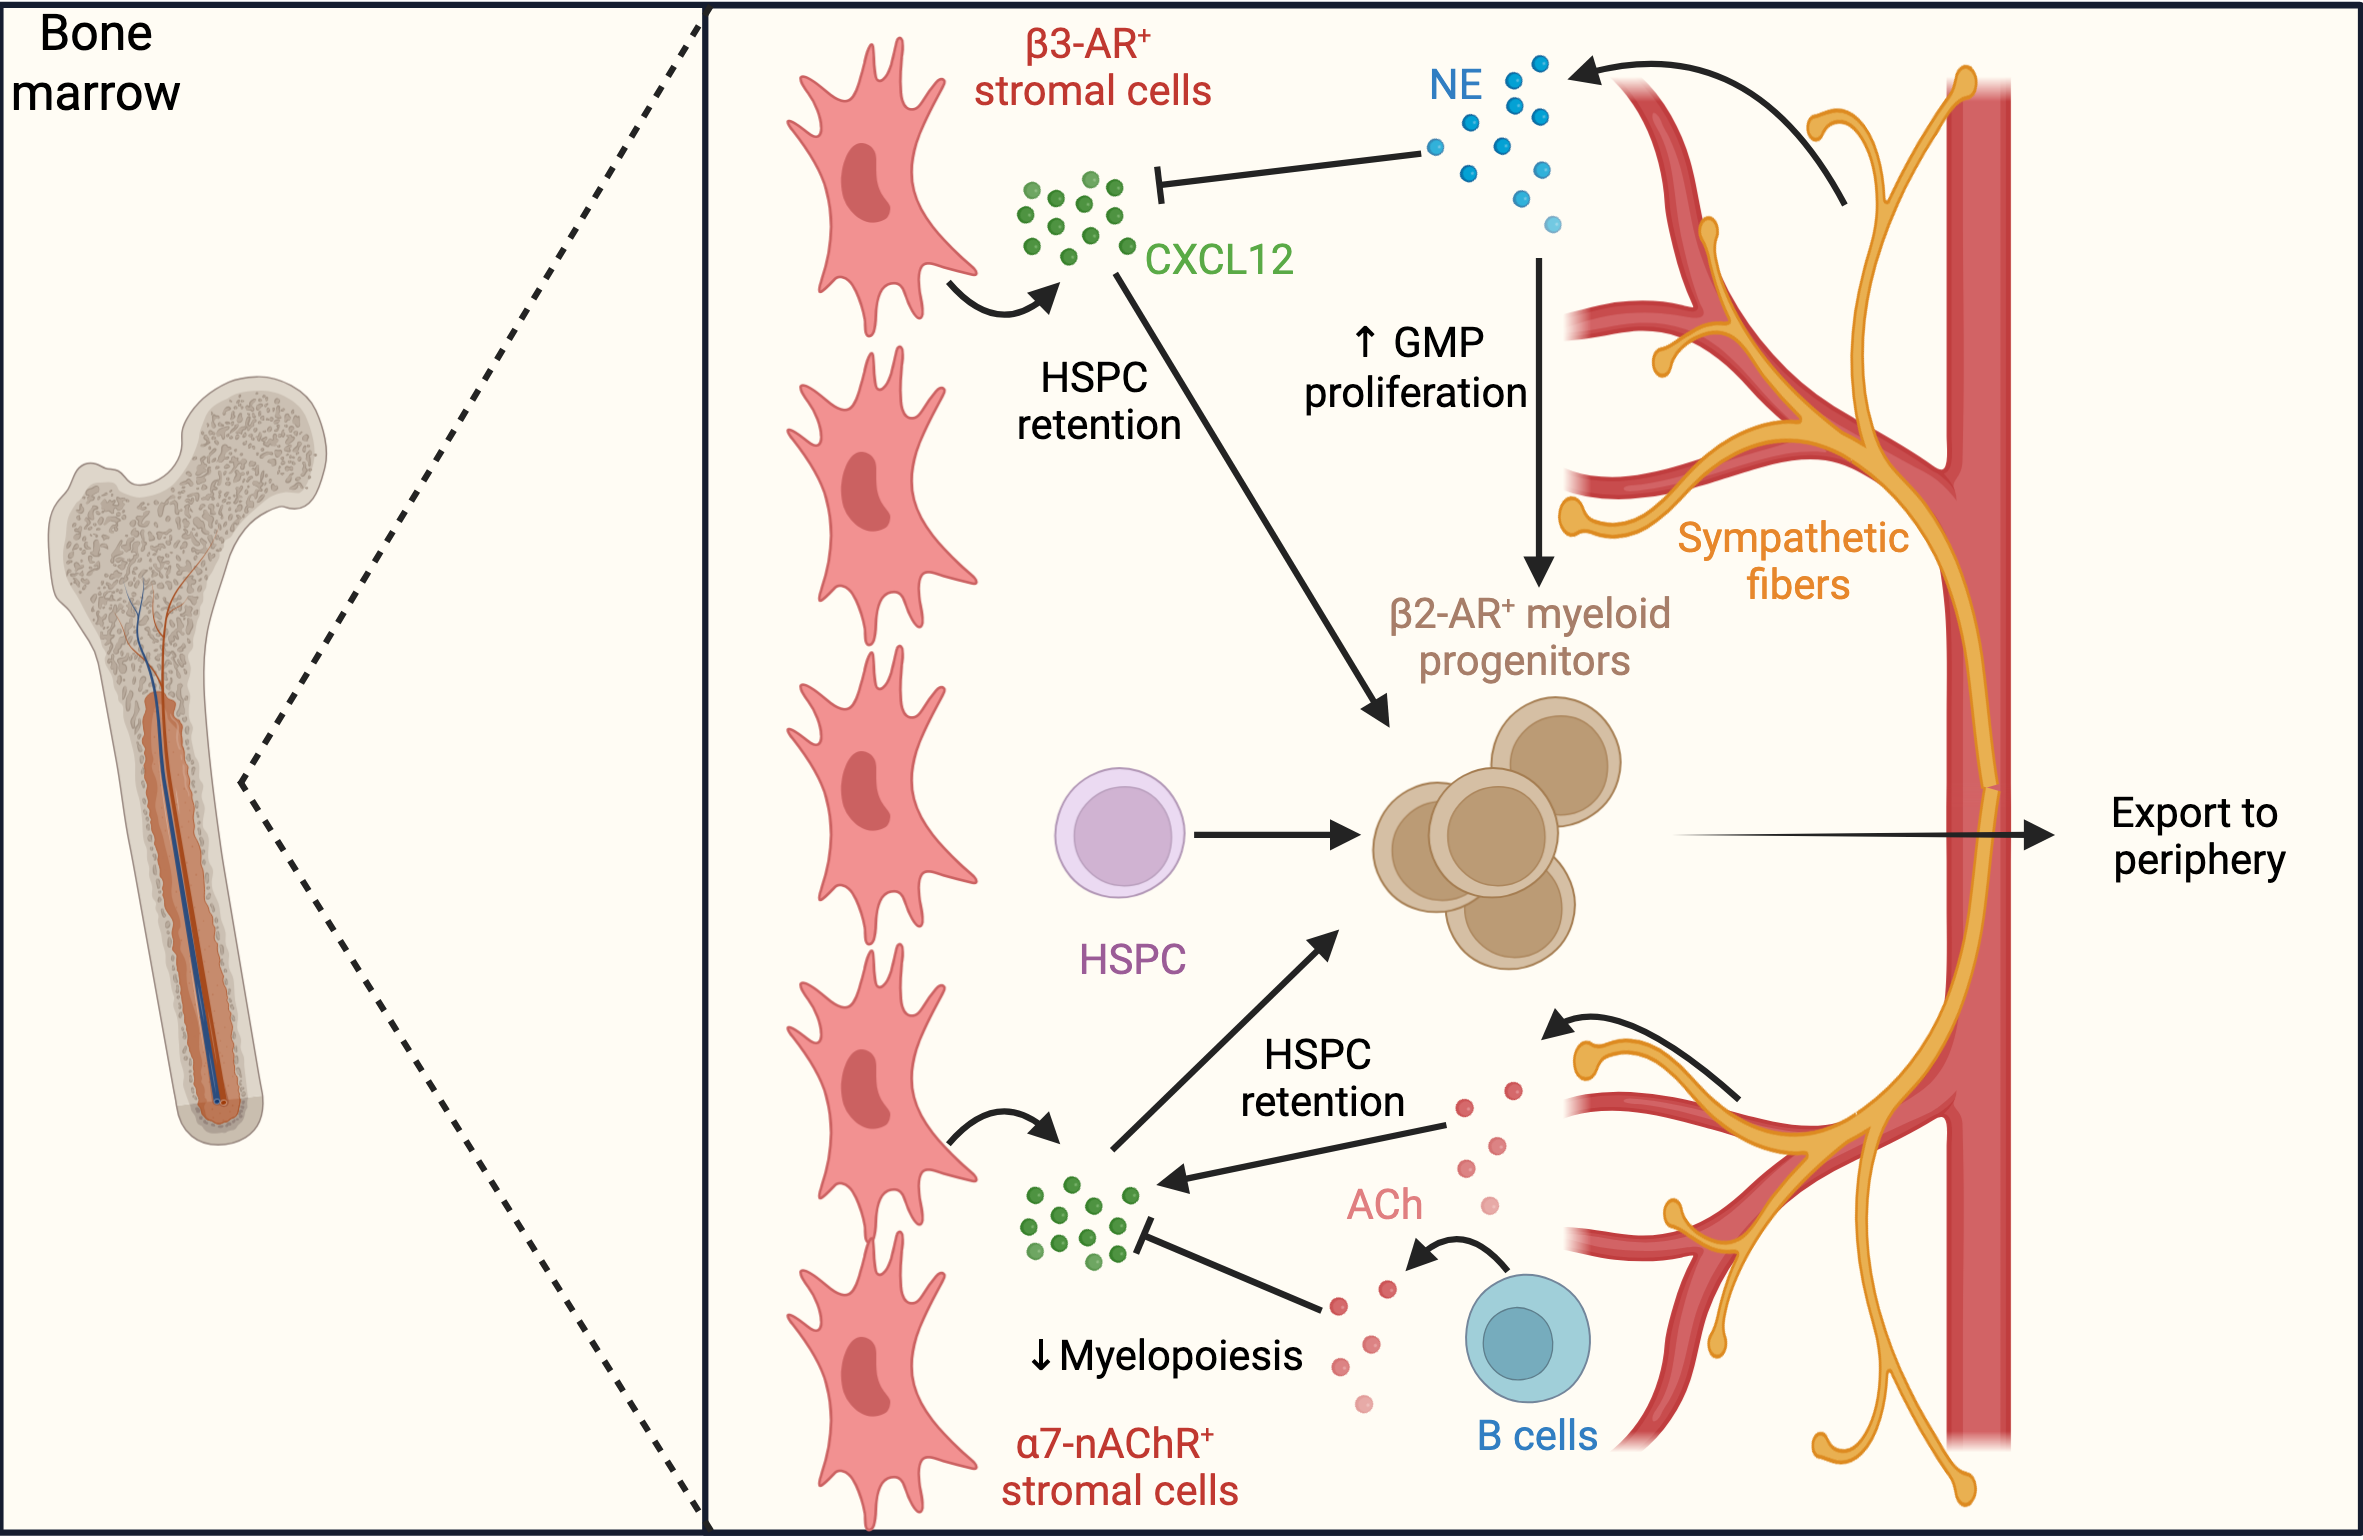
Figure 2. Sympathetic and cholinergic regulation of myeloid cell output in the bone marrow. Sympathetic fibers enter the bone marrow along the vasculature and release NE and ACh onto distinct stromal cell populations. NE acts via β3-AR on stromal cells to suppress CXCL12 and promote HSPC mobilization, while directly stimulating β2-AR+ GMP proliferation. ACh acts via α7-nAChR on a separate stromal population to maintain CXCL12 and HSPC retention; B cell-derived ACh provides a parallel immune-intrinsic brake on myelopoiesis. Created in BioRender. Mauvais FX. (2026) https://BioRender.com/xmibrku. NE: norepinephrine; ACh: acetylcholine; β3-AR: β3-adrenergic receptors; CXCL12: C-X-C motif chemokine ligand 12; HSPC: hematopoietic stem and progenitor cell; GMP: granulocyte-macrophage progenitor; α7-nAChR: α7 nicotinic acetylcholine receptor.
2.2.1.3 Cholinergic tone and myeloid pre-programming
Sympathetic pro-myelopoietic signaling is counterbalanced by cholinergic mechanisms. Sympathetic fibers with cholinergic capacity release ACh acting on α7 nicotinic acetylcholine receptor (α7-nAChR) on mesenchymal stromal cells to enhance Chemokine (C-X-C motif) ligand 12 (CXCL12) production and maintain HSPC quiescence[79]. B lymphocytes provide a parallel local source of ACh, suppressing CXCL12 via Leptin receptor-expressing stromal cells to limit myelopoiesis[20]. Pharmacological enhancement of cholinergic tone via acetylcholinesterase inhibition reduces circulating inflammatory myeloid cells in both mice and humans, establishing a push-pull adrenergic/cholinergic system governing myeloid output[20]. ANS signals also pre-program the functional competence of myeloid cells during differentiation. The requirement for α7-nAChR expression in bone marrow-derived myeloid cells for the cholinergic anti-inflammatory pathway (CAP) integrity, established by chimeric bone marrow transfer experiments, demonstrates that macrophage responsiveness to cholinergic signals is determined during hematopoietic development[31]. Dopaminergic tone similarly calibrates baseline levels of myeloid activation: DAT disruption elevates local dopamine and NE within lymphoid organs, expanding splenic myeloid populations and increasing major histocompatibility complex class-II (MHC-II) molecule expression, identifying a tonic dopaminergic brake on myeloid activation at homeostasis[53,39].
2.2.1.4 Controversies and open questions
Most reviewed studies rely on chemical sympathectomy with 6-OHDA or systemic use of adrenergic agonists or antagonists, which non-selectively target neuronal, stromal and hematopoietic compartments. Conditional receptor deletion may help establish whether the effects on GMP proliferation and myeloid output are mediated directly through progenitors versus indirectly through stromal niche cells. In the same line, the local amplification loop involving TH-expressing leukocytes producing catecholamines in the bone marrow raises the question of whether pharmacological perturbations model neural input or immune-derived catecholamine signaling. Whether sexually dimorphic wiring of β3-AR signaling identified in mice under psychosocial stress conditions translates to the human bone marrow and extends to other tissues remains to be investigated. Finally, addressing whether and how prenatal and perinatal sympathetic signals shape the long-term epigenome of tissue-resident macrophages seeded during fetal life may have potential implications for developmental programming of innate immune responses.
2.2.2 Thymus
2.2.2.1 Anatomical organization
The thymus is supplied by sympathetic fibers distributed throughout all compartments including the capsule, the subcapsular region, the cortex, the cortico-medullary junction, the medulla and along the vessels[81]. Thymic sympathetic input emerges from the cervical and stellate ganglia of the sympathetic trunk, and the thoracic spinal cord from T2 to T7[102]. Sympathetic neurons projecting to the thymus co-express noradrenergic and peptidergic neurotransmitters such as NPY[102]. VIP-immunoreactive fibers are detected in the thymus but their autonomic versus non-neuronal sources are not resolved[81,102]. The presence of a direct parasympathetic input has not been anatomically established[102] and any cholinergic input if present is likely minor and of uncertain function. Sympathetic innervation of the thymus is profoundly modelled by ageing, with axonal degeneration, reduced fiber volume and loss of axonal synapses accompanying thymic involution[108]. In the ageing mouse thymus, ionized calcium-binding adapter molecule 1 (Iba1)+ macrophages, physically close to dystrophic sympathetic axons, adopt a hypertrophic phenotype combining enlarged cell bodies, lipid droplet accumulation and upregulation of pro-inflammatory and phagocytic genes such as Tnf, Il1b, Trem2 or Apoe[108]. For a detailed anatomical schematic of thymic sympathetic innervation, see the review by Carpenter et al.[102].
2.2.2.2 Sympathetic regulation of thymic myeloid cells
In mice, sympathetic fibers are observed in proximity to thymic macrophages and mast cells[102,109,110]. Single-cell analyses have revealed at least two thymic macrophage populations: T-cell immunoglobulin and mucin domain containing 4 (TIM4)+ cortical macrophages specialized in efferocytosis of apoptotic thymocytes, and CX3C motif chemokine receptor 1 (CX3CR1)+ macrophages at the corticomedullary junction with antigen-presenting potential[110]. However, direct evidence for functional ANS control of thymic myeloid cells is lacking.
2.2.2.3 Controversies and open questions
Whether Iba1+ thymic macrophages actively drive sympathetic degeneration or perform the homeostatic clearance of degenerating fibers remains currently unknown. Resolving this question may help to understand how sympathetic neuropathy propagates within lymphoid organs. Whether sympathetic signals influence efferocytosis, antigen presentation within the thymic medulla, or the efficiency of thymic selection and thereby central tolerance, remains an open question whose investigation could help to understand how chronic stress or autonomic dysfunction shapes autoimmune susceptibility. The sympathetic innervation of the human thymus, including its age-related remodeling, represents a significant gap given the clinical relevance of thymic involution in immunosenescence.
2.3 Secondary lymphoid organs
Secondary lymphoid organs include the spleen and the lymph nodes, where myeloid cells encounter antigenic materials to initiate innate immune response and interact with adaptive immune cells. Unlike the bone marrow and thymus, ANS signaling acts on tissue-resident, migratory or mature myeloid cells engaged in immune surveillance, inflammation and antigen presentation to lymphocytes. The spleen and lymph nodes differ substantially in their autonomic innervation, anatomical and functional architecture.
2.3.1 Spleen
2.3.1.1 Anatomical organization
The spleen receives its principal autonomic input through the splenic nerve, a postganglionic sympathetic conduit arising from neurons in the CSMG[111,112]. Noradrenergic fibers enter alongside the splenic artery and branch into trabeculae and parenchyma, innervating white pulp, including the PALS and B cell follicles, marginal zone, and red pulp, placing sympathetic fibers near compartment-specific resident macrophage and DC populations[113]. In mice, three major nerve branches innervate the spleen: two catecholaminergic arterial branches and an apical branch reported to induce cholinergic signaling suppressing myeloid cell activation through a lymphocyte-independent mechanism[114] (Figure 3). Whether this reflects a distinct cholinergic nerve or non-neuronal ACh release from local immune cells remains unresolved[115]. Three-dimensional imaging has revealed a panicle-like network of nerve terminals in close association with macrophages and multiple DC subsets across all compartments[17,116]. Within the splenic nerve itself, NAMs may participate in afferent signaling back to the central nervous system[54]. Sympathetic innervation is conserved in human spleens, with an age-related decline in innervation density[117]. Anterograde tracing studies have found no evidence of direct vagal innervation of the spleen; vagal influence is relayed via the CSMG to postganglionic sympathetic neurons forming the splenic nerve[118].
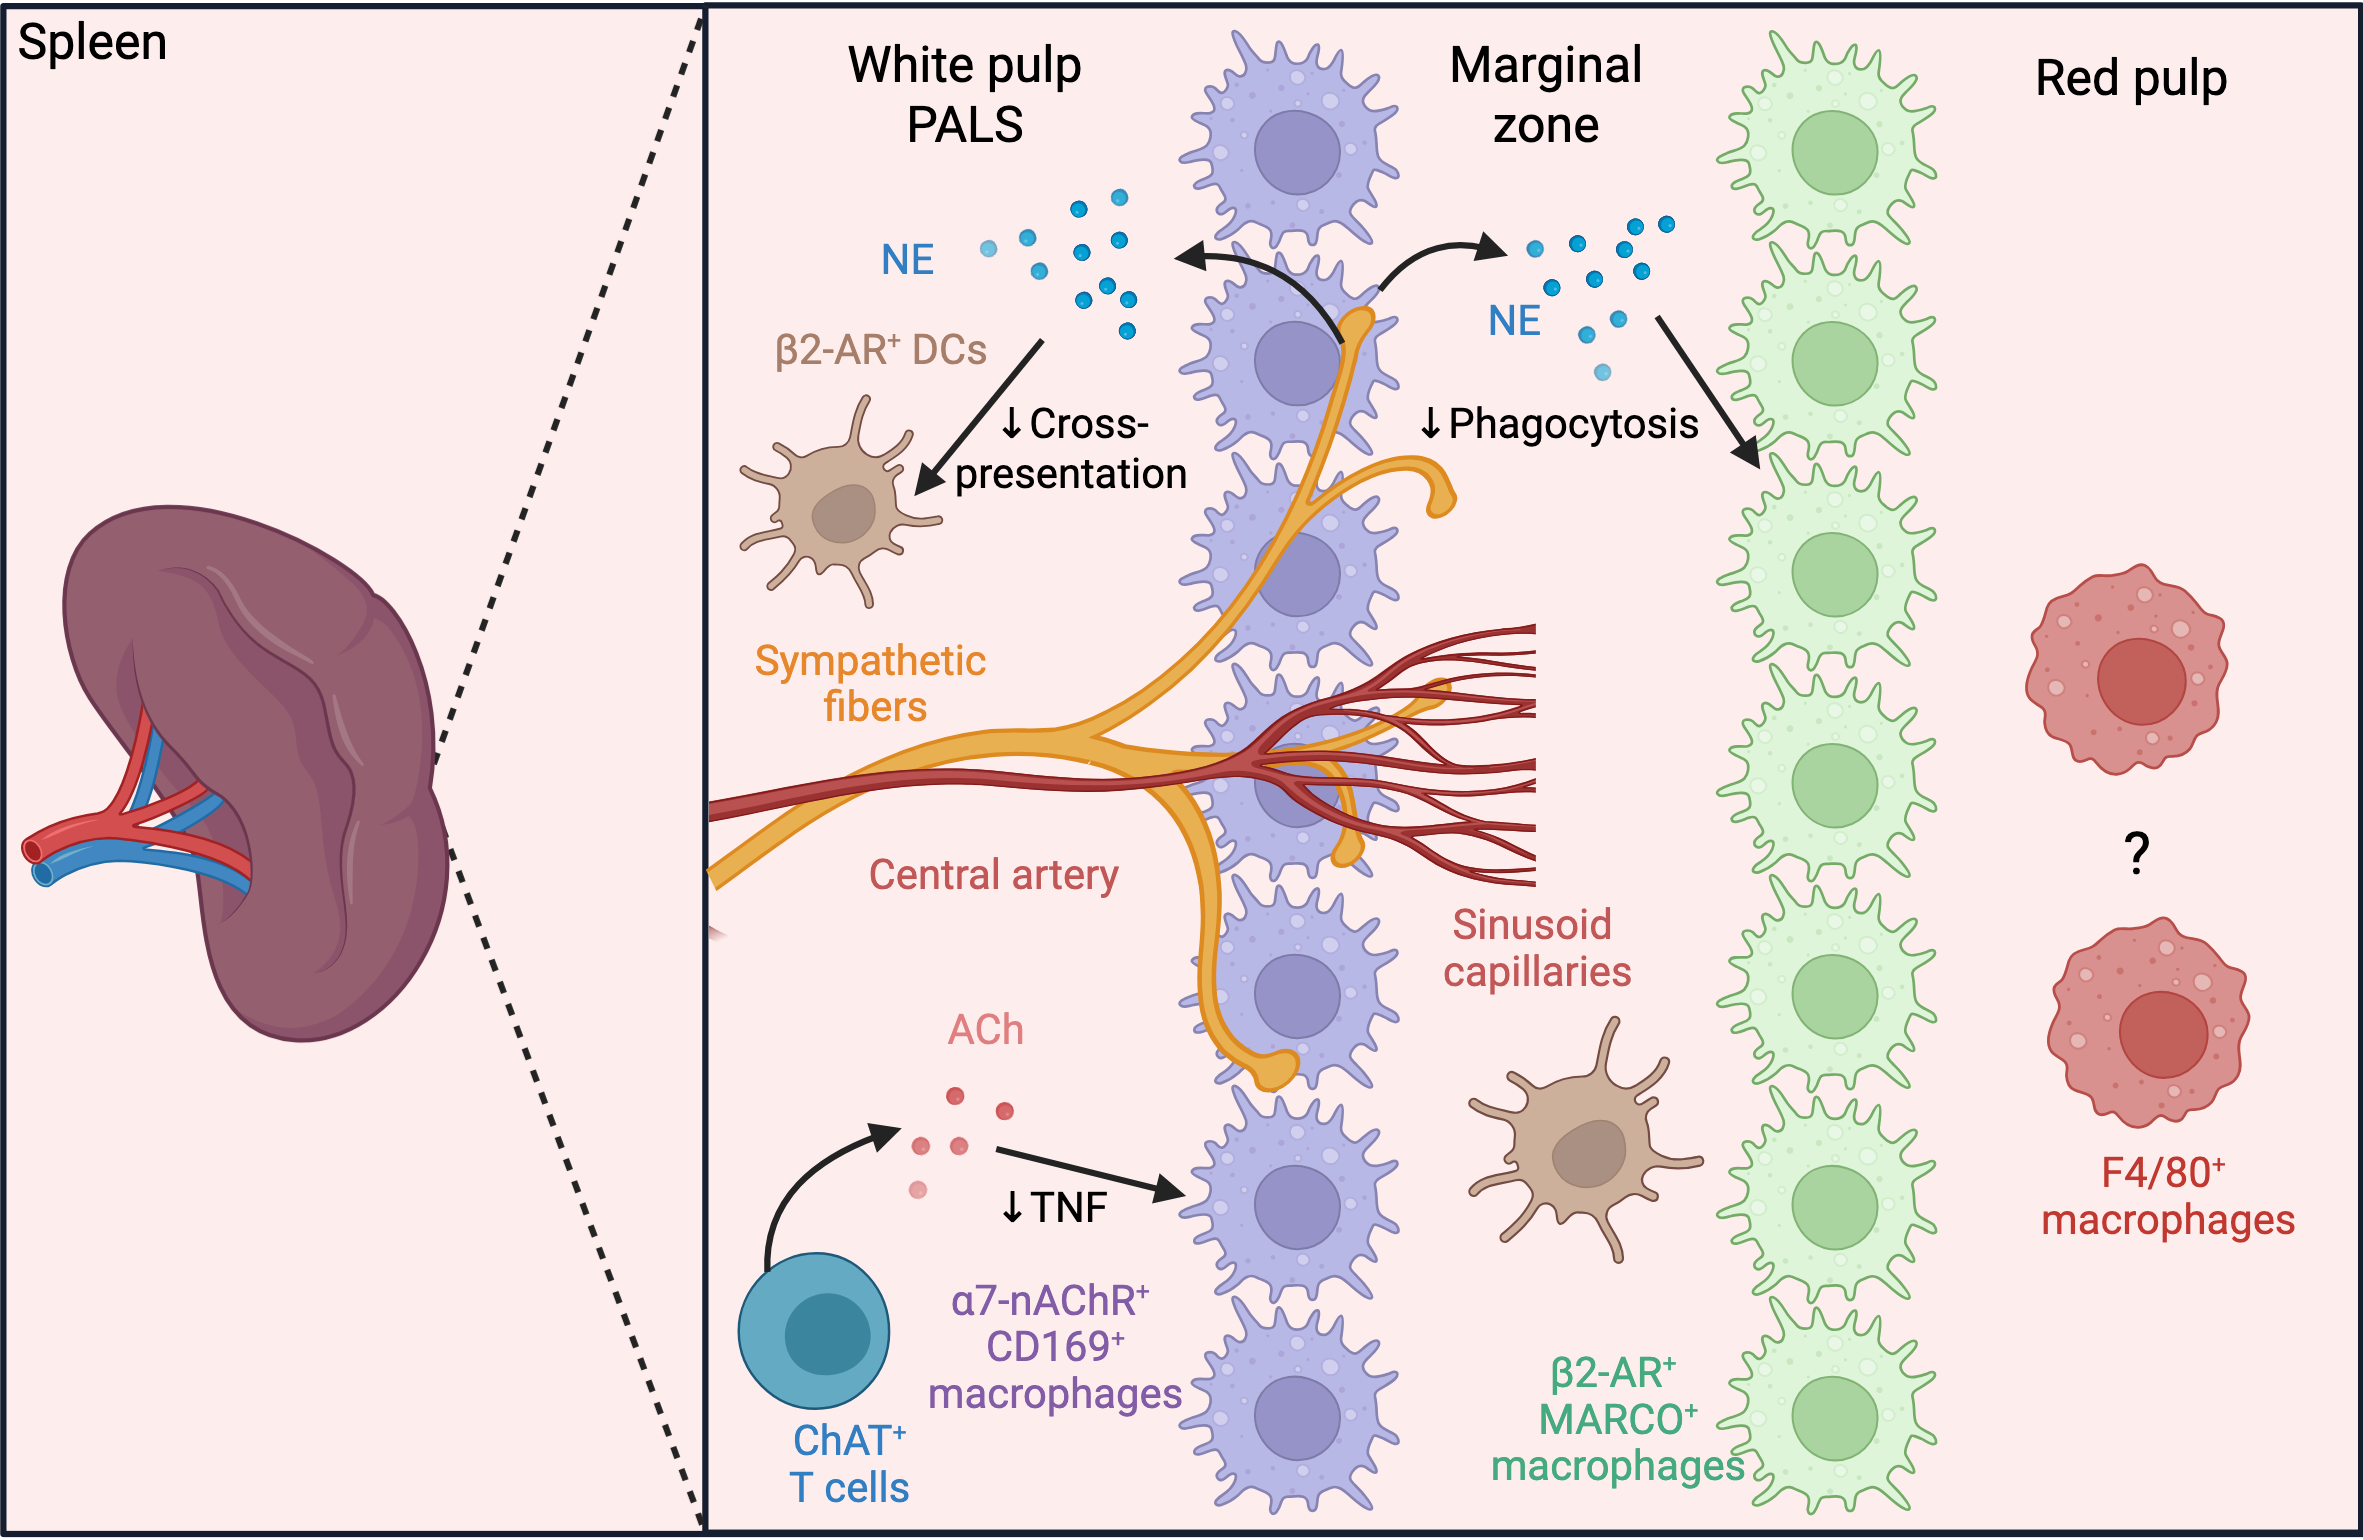
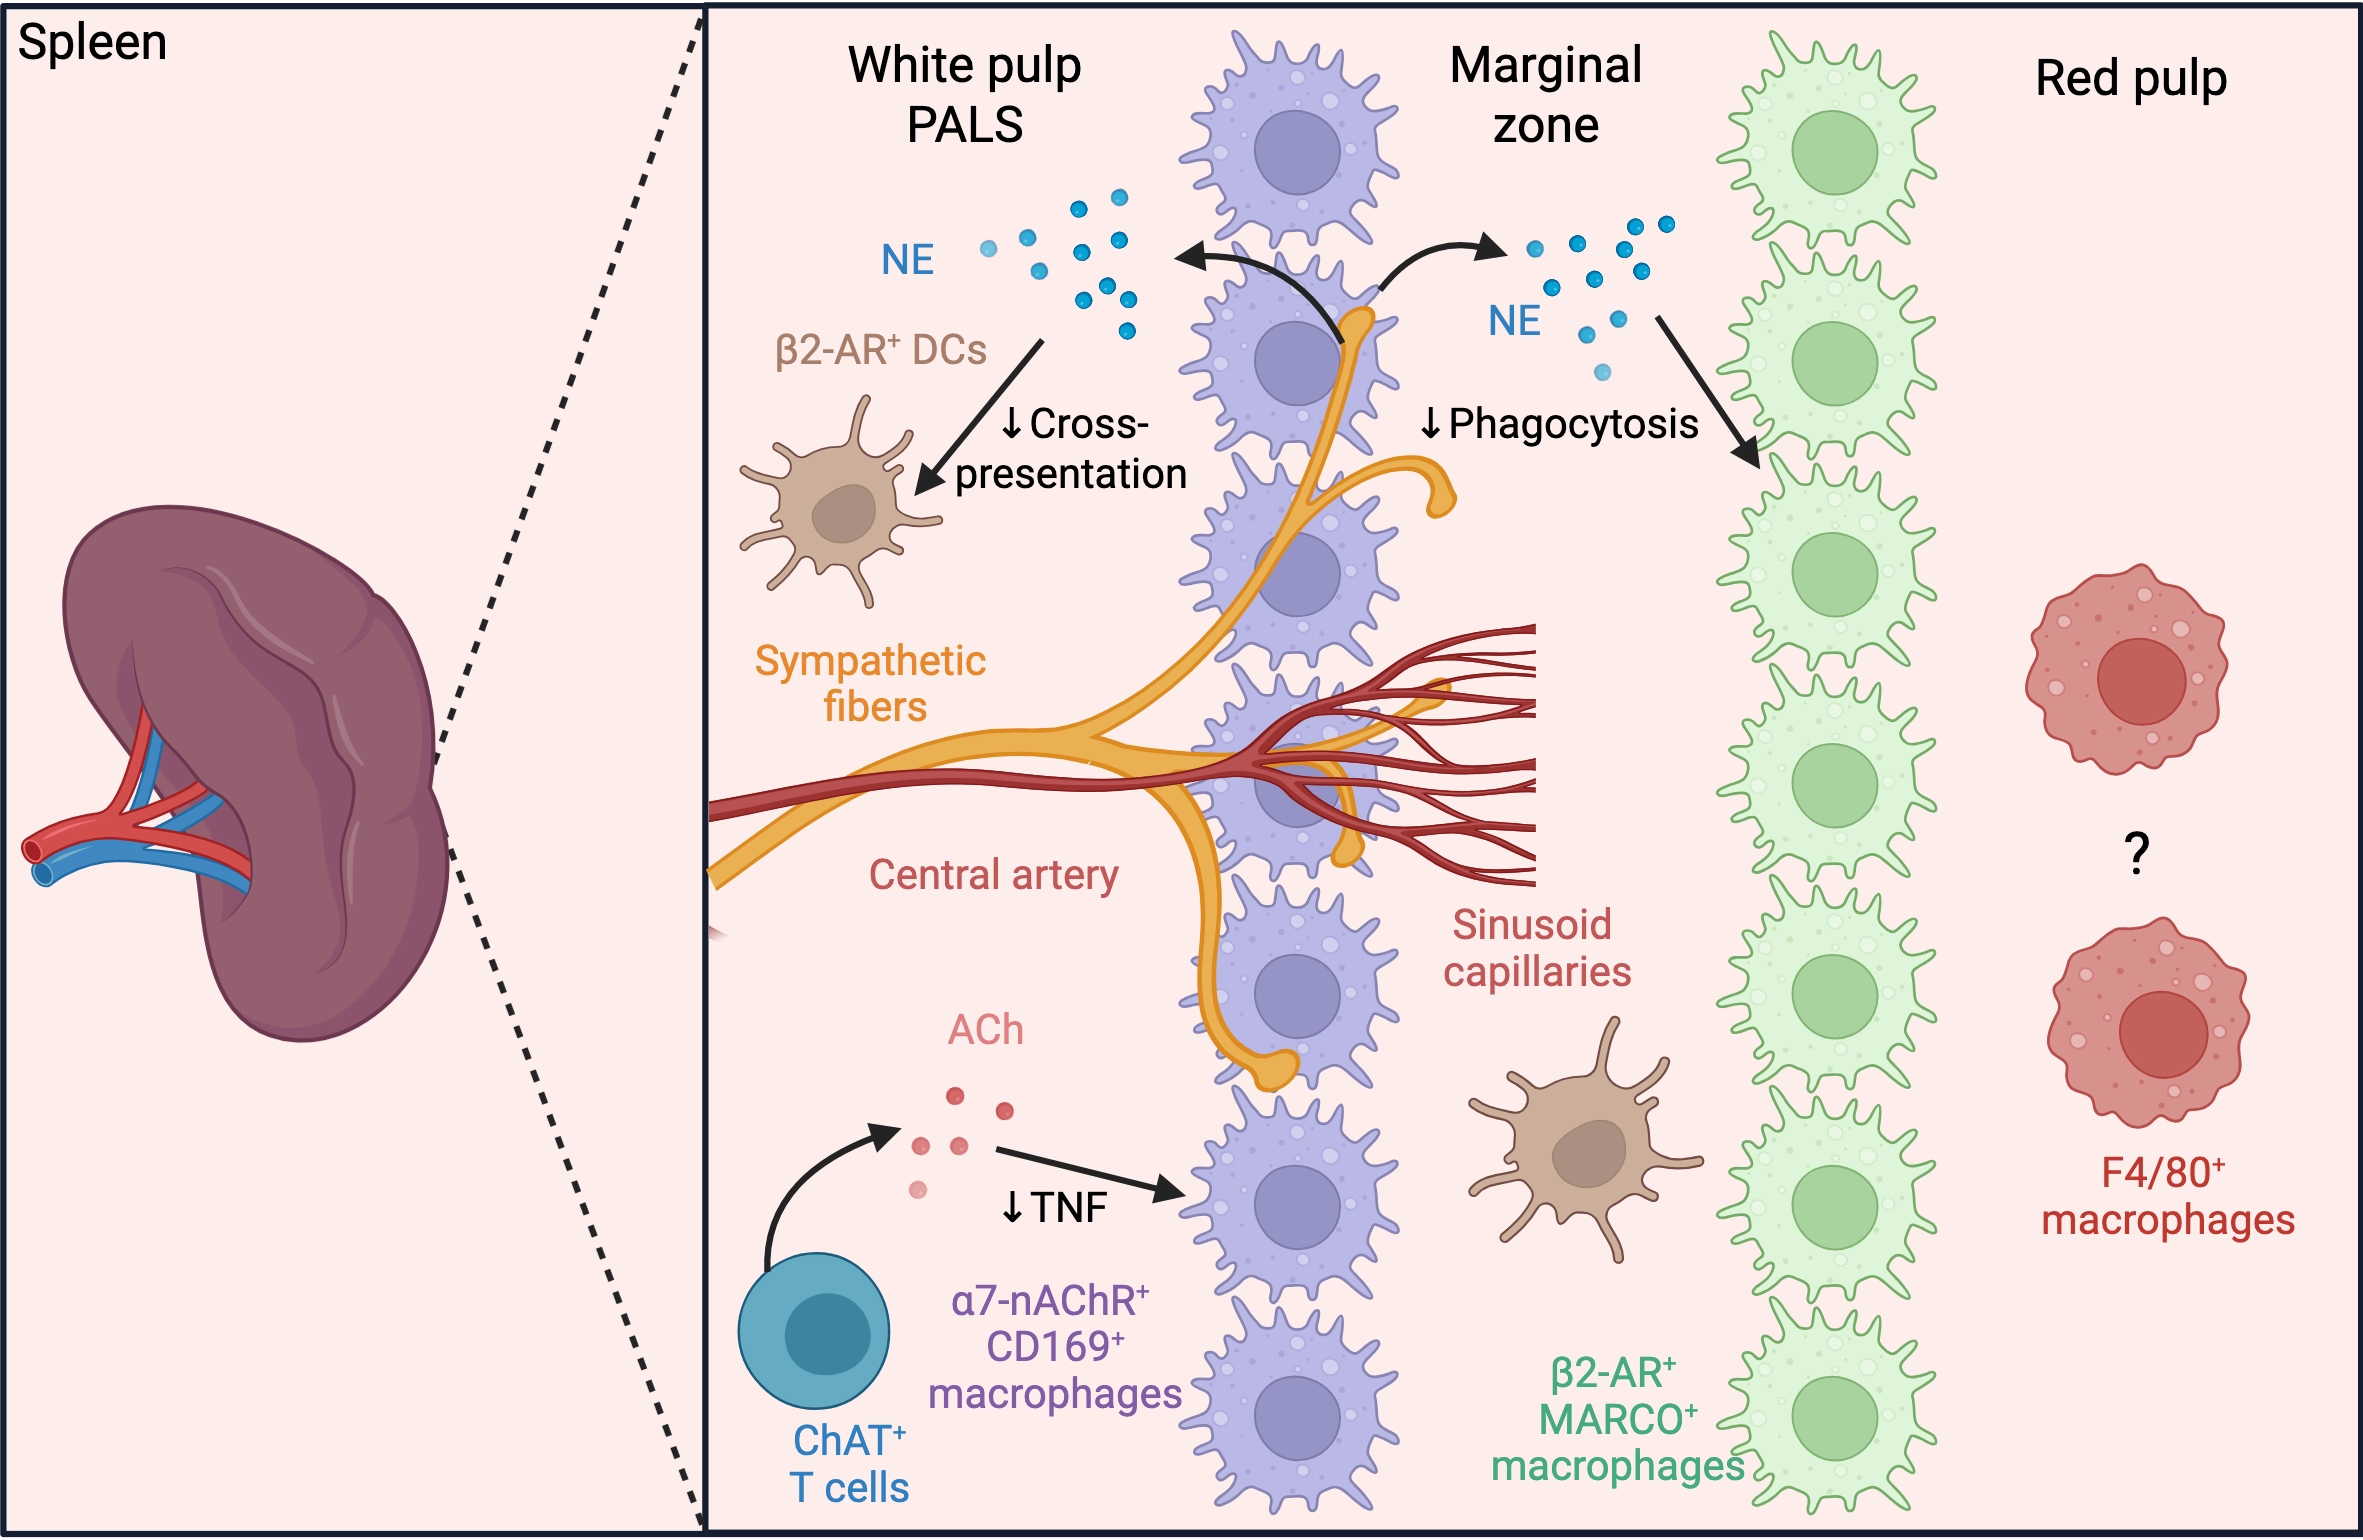
Figure 3. Autonomic regulation of myeloid cell function in the spleen. Sympathetic fibers enter the spleen along the central artery from the CSMG; the vagus nerve does not directly innervate the spleen but relays anti-inflammatory signals via the CSMG. In the PALS, NE acts via β2-AR on ChAT+ T cells, which release ACh onto α7-nAChR+ macrophages to suppress TNF production, a process referred to as the CAP. Whether this T cell relay is obligatory remains contested. NE additionally impairs cross-presentation in β2-AR+ DCs and suppresses phagocytosis in MARCO+ marginal zone macrophages. The functional consequences of sympathetic signaling on F4/80+ red pulp macrophages remain poorly characterized. Created in BioRender. Mauvais FX. (2026) https://BioRender.com/9qwgq26. CSMG: celiac-superior mesenteric ganglia; PALS: periarteriolar lymphoid sheath; NE: norepinephrine; β2-AR: β2-adrenergic receptor; ChAT: choline acetyltransferase; ACh: acetylcholine; α7-nAChR: α7 nicotinic acetylcholine receptor; TNF: tumor necrosis factor; CAP: cholinergic anti-inflammatory pathway; DCs: dendritic cells; MARCO: macrophage receptor with collagenous structure.
2.3.1.2 Inflammatory regulation and the cholinergic anti-inflammatory pathway
The CAP represents the best characterized neuroimmune circuit in the spleen[23,24]. In its canonical formulation, cholinergic neurons of the dorsal motor nucleus of the brainstem[119] project via the vagus nerve to the CSMG, from which postganglionic sympathetic fibers of the splenic nerve release NE onto β2-AR-expressing ChAT+ Cluster of Differentiation 4 (CD4)+ T cells in the PALS[23,24,119]. T cells in turn release ACh that acts on α7-nAChR on macrophages to suppress Nuclear Factor-kappa B (NF-κB)-driven tumor necrosis factor (TNF) production[51,23,120,121]. Optogenetic activation of cholinergic neurons of the dorsal motor nucleus confirms the brainstem origin of the circuit[119]. Downstream of α7-nAChR engagement, sustained TNF suppression requires activation of adenylyl cyclase 6 and downstream cyclic adenosine monophosphate-protein kinase A-cyclic adenosine monophosphate response element-binding protein (cAMP-PKA-CREB) signaling[26]. Beyond TNF suppression, α7-nAChR engagement on macrophages inhibits high-mobility group box 1 protein (HMGB1) release, a late-phase sepsis mediator, in response to both endotoxin and TNF-α, through a nicotinic anti-inflammatory pathway requiring NF-κB inhibition[25]. Nicotinic agonists improve survival in experimental sepsis even when treatment is initiated after disease onset, extending the therapeutic window of CAP activation[25]. Parallel routes have been identified in which CART peptide, released directly by caudal dorsal motor nucleus neurons, or NPY suppress splenic inflammation independently of the canonical CAP circuit[40,41] and may act on lymphocytes. Yet, the contribution of myeloid cells has not been investigated. Central M1 muscarinic acetylcholine receptor signaling in the basal forebrain also modulates splenic immune cell composition and systemic cytokine levels during sepsis following cecal ligation and puncture by acting on splenic neutrophil, macrophage, and inflammatory monocyte numbers, and attenuating serum TNF-α and Interleukin-1 beta (IL-1β). Thus, central cholinergic circuits can engage splenic myeloid populations through descending pathways distinct from the peripheral vagal-splenic nerve axis[33].
A significant mechanistic controversy surrounds the necessity of the T cell relay. T cell-deficient mice retain vagal suppression of splenic TNF[122]. In situ hybridization fails to detect ChAT or α7-nAChR in the murine spleen, whereas β2-AR expression is robust, suggesting key cholinergic interactions may occur at the celiac ganglion rather than within the spleen[123]. Stimulation of the apical splenic nerve branch suppresses inflammation directly in myeloid cells, independently of lymphocytes[114]. Multiple parallel pathways (direct adrenergic signaling, T cell-mediated cholinergic signaling, and neuropeptide-mediated mechanisms) likely converge on splenic macrophages, DCs, and monocytes as final effectors, with their relative contribution varying by inflammatory context, neural input pattern, and species.
2.3.1.3 Antimicrobial defense
In contrast to the CAP, sympathetic signaling in the spleen predominantly restrains the antimicrobial effector functions of myeloid cells. NE suppresses macrophage activation via β2-AR, and pharmacological activation of this pathway reduces the phagocytic capacity of marginal zone macrophages, particularly within the highly bactericidal macrophage receptor with collagenous structure (MARCO)-expressing subset[16,17]. Adrenergic stimulation is associated with vasoconstriction within lymphoid tissues, reducing local blood flow and generating transient hypoxia that halts leukocyte migration via calcium-dependent pathways[19]. Chemical sympathectomy enhances survival in Klebsiella pneumoniae peritonitis, driven by increased monocyte chemoattractant protein-1 (MCP1)-dependent monocyte mobilization from the spleen[92]. Sympathectomy similarly promotes macrophage accumulation at sites of infection and modulates cytokines critical for host defense against intracellular pathogens including Listeria monocytogenes[90,91]. The physiological constraint imposed by adrenergic tone on splenic myeloid antimicrobial function extends to antiviral immunity: mice globally deficient in β2-AR mount exaggerated innate immune responses to murine cytomegalovirus infection, with elevated myeloid cytokine production in the spleen and liver and enhanced viral clearance, whereas pharmacological β2-AR agonism has the opposite effect. This suggests that β2-AR signaling constitutively limits the magnitude of splenic innate antiviral responses in vivo[7]. Ablation of splanchnic sympathetic outflow enhances bacterial clearance by shifting neutrophil functional states toward microbicidal phenotypes in septic peritonitis models[124].
2.3.1.4 Antigen presentation
Cholinergic signaling through α7-nAChR selectively impairs antigen processing in splenic DCs without affecting antigen uptake, thereby limiting the differentiation of CD4+ T cells into regulatory (Treg), T helper 1 (Th1), Th2, and Th17 subsets[28]. The α7-nAChR on splenic DCs is pharmacologically distinct from its neuronal counterpart: it is sensitive to the partial agonist 3-[(2,4-dimethoxy)benzylidene]-anabaseine (GTS-21) but not to classical antagonists α-bungarotoxin and methyllycaconitine, reflecting differences in receptor subunit composition[28,29]. β2-AR agonist exposure impairs antigen direct[9] and cross-presentation[9,10] to CD8+ T cells by mature DCs through a Gαi/0-dependent mechanism, reducing cytotoxic T lymphocyte (CTL) priming while preserving MHC-II-restricted presentation[10] or not[9], possibly depending on the antigen type. Conversely, nicotinic stimulation can augment cross-presentation capacity via phosphoinositide 3-kinase-protein kinase B-mammalian target of rapamycin (PI3K-Akt-mTOR) signaling and TLR4-myeloid differentiation primary response 88-IL-1 receptor-associated kinase 4 (TLR4-MyD88-IRAK4)-dependent transporter associated with antigen processing (TAP) recruitment[125].
VIP released from splenic nerve terminals and immune cells themselves acts on Vasoactive intestinal peptide receptor 1 (VPAC1) and VPAC2 to generate tolerogenic DCs with the capacity to induce Treg cells, an effect demonstrated both in murine models of graft versus host disease and autoimmune disease and in human monocyte-derived DCs[45-47]. VIP additionally impairs the acquisition of the pro-inflammatory macrophage polarization profile, shifting granulocyte macrophage colony-stimulating factor (GM-CSF)-polarized macrophages toward an anti-inflammatory phenotype via VPAC1 and VPAC2[42]. Notably, VPAC2 expression in macrophages is itself regulated by TLR2 and 4 ligands through p38 MAPK-dependent pathways[43], establishing a feedback loop in which bacterial signals modulate macrophage sensitivity to VIP-mediated immunosuppression.
2.3.1.5 Systemic tissue homeostasis and disease
Beyond its roles in local inflammatory and antimicrobial regulation, the spleen functions as a systemic neuro-myeloid effector organ. In hypertensive heart disease, left ventricular pressure overload recruits a brainstem circuit that enhances splenic sympathetic activity and induces placental growth factor secretion, driving the proliferation of neuropilin-1-expressing cardiac-resident macrophages[84]; inhibition of this splenic neuroimmune axis leads to cardiac decompensation[84]. Although placental growth factor is secreted by stromal cells from the marginal zone[84], marginal zone CD169+ macrophages may play a pathogenic role as their activation correlates with lymphocyte egress to the sites of vascular damage in hypertension mouse models[126,127]. VNS promotes repair-associated macrophage phenotypes in cardiac injury via α7-nAChR signaling[128], while β2-AR activity on immune cells drives inflammatory macrophage recruitment and adverse remodeling[129]. In atherosclerosis, reciprocal communication between the nervous system, spleen, and vascular lesions forms a feedback loop that amplifies inflammation, and disruption of this circuit reduces plaque formation[130]. Splenic control of the timing of myeloid cell release following myocardial infarction is essential for coordinated tissue repair[131-134]; whether sympathetic signals promoted by acute infarction and possibly activating the heart-brain-spleen axis orchestrate cell migration behaviors in this context has not been tested. VIP co-released with NE from splenic nerve terminals and by splenic immune cells extends the neuro-myeloid axis of the spleen-heart circuit through a separate anti-inflammatory mechanism targeting VPAC receptors on cardiac macrophages and stromal cells[44]. VIP treatment reduces myocardial inflammatory infiltration and prevents profibrotic cardiac remodeling in experimental autoimmune myocarditis, and reduces atherosclerotic plaque burden by limiting Th1-driven responses, increasing Treg cells in atherosclerotic arteries and draining lymph nodes, regulating macrophage cholesterol efflux, and reducing foam cell formation[44].
VNS confers protection against renal ischemia-reperfusion injury via α7-nAChR-positive splenocytes, with protection abolished by splenectomy or α7-nAChR knockout[94]. A parallel stress-induced anti-inflammatory circuit has been identified in which C1 neurons of the medulla oblongata, distinct from the classical dorsal motor nucleus-vagal pathway, mediate protection against renal ischemia-reperfusion injury through optogenetic or restraint stress-driven activation: C1 stimulation activates a predominantly sympathetic, cholinergic pathway that requires β2-AR signaling, splenic integrity, and α7-nAChR expression, reproducing the cytoprotective effect through adoptive transfer of NE-preincubated splenocytes[135]. C1 neuron activation thus provides a parallel brainstem route to splenic neuroimmune activation distinct from the dorsal motor nucleus-vagal route. α7-nAChR agonism similarly reduces acute lung injury following renal ischemia-reperfusion through splenic myeloid cells[136]. HIV-1 blocks sympathetic-mediated transcription of interferon-β in plasmacytoid DCs[137]; in murine acquired immunodeficiency syndrome and simian immunodeficiency virus infection, viruses shift splenic macrophages toward an immunosuppressive CD163+ phenotype[138], illustrating that the ANS-myeloid interface can be actively exploited by pathogens to create an immunosuppressive niche.
2.3.1.6 Controversies and open questions
The requirement of the ChAT+ T cell relay in the CAP remains contested. T cell-deficient mice retain vagal TNF suppression, ChAT and α7-nAChR transcripts are undetectable by in situ hybridization in the murine spleen, and apical nerve stimulation suppresses myeloid activation independently of lymphocytes. Whether and how the CAP and sympathetic antimicrobial circuit are engaged simultaneously or sequentially, and which predominates, is currently unresolved. Opposing roles of β2-AR signaling have been identified in this section: it drives inflammatory macrophage recruitment and adverse cardiac remodeling in heart failure, but mediates cytoprotection against renal ischemia-reperfusion injury through the C1 brainstem pathway. This illustrates that β2-AR functional output is determined by disease context, target cell population, and the brainstem circuit engaged rather than by receptor identity alone.
2.3.2 Lymph nodes
2.3.2.1 Anatomical organization
Sympathetic nerve fibers enter lymph nodes at the hilum and extend primarily along blood vessels into the medullary and paracortical regions, terminating near DCs and CD68+ macrophages but not penetrating B-cell follicles[3,19,116,139]. Optogenetic activation of sympathetic postganglionic neurons projecting from the celiac-superior mesenteric ganglion suppresses lipopolysaccharide-induced TNF-α production in the spleen and in mesenteric but not inguinal lymph nodes[140], revealing an anatomically precise and compartmentally restricted circuit distinct from diffuse systemic catecholamine release[141]. For a detailed anatomical schematic of lymph nodes, see Cleypool et al.[117] and Kremer et al.[139].
2.3.2.2 Adrenergic control of DC migration and T-cell priming
NE drives chemotaxis of immature DCs via α1b-adrenergic receptor (α1b-AR) but not of CD40-stimulated DCs, as supported by prazosin blockade suppressing DC emigration from skin to draining lymph nodes, reducing contact hypersensitivity[11]. Acute psychological stress amplifies this circuit through a corticosteroid-independent mechanism, enhances skin DC migration to draining lymph nodes and increases CD8+ T cell priming[11,142]. An additional indirect effect operates independently of hematopoietic adrenoreceptors: NE-induced vasoconstriction generates transient hypoxia that triggers calcium signaling in leukocytes and halts interstitial motility, suppressing T cell responses to viral, parasitic, and tumor antigens in vivo[19]. These two effects are not contradictory: the former acts directly on DC-intrinsic adrenoreceptors during early immune activation, while the latter reflects an indirect vascular effect constraining bulk leukocyte movement under sustained sympathetic activation.
Once DCs reach lymphoid organs, β2-AR signaling reshapes their functional output. DCs and Langerhans cells express β1-, β2-, α2(A)-, and α2(C)-AR. β2-AR stimulation suppresses IL-12 and enhances IL-10 via β2-AR and α2(A)-AR, and β2-AR-induced IL-10 suppresses DC homing to T cell zones in an autocrine loop[22,143]. Topical β2-AR blockade during sensitization increases Langerhans cell migration, enhances the contact hypersensitivity response, and augments interferon-γ and IL-2 in draining lymph node cells in vivo[22]. β-AR blockade restores cross-presentation and improves cancer vaccine efficacy[12]. Because α1- and β-adrenergic blockade in these studies was applied systemically or topically instead of selectively targeting DC, none of the pharmacological findings in this section establish a DC-autonomous mechanism independent of effects on skin vasculature, keratinocytes, or other local immune populations. The α2-AR provides a counterpoint: brief NE exposure enhances antigen endocytosis via PI3K-ERK1/2 activation, reversed by yohimbine and absent with β-AR antagonists[21]. VIP provides a further neuropeptide brake on DC migration: by downregulating C-C chemokine receptor type 7 (CCR7) and CCR1 on mature DCs, VIP inhibits DC trafficking to draining lymph nodes in vivo[48].
2.3.2.3 Cholinergic and dopaminergic regulation
Cholinergic regulation of DC function in lymph nodes is less well characterized than its adrenergic counterpart. The best-documented effect of α7-nAChR signaling has been established in splenic DCs[28] and cannot be directly extrapolated to lymph node-resident populations. In plasmacytoid DCs, α7-nAChR activation suppresses migration toward isolated lymphoid follicles through Rac1 inactivation via a Janus Kinase 2- and caspase-3-dependent mechanism, with therapeutic relevance in ulcerative colitis[30]. D3R on DCs constitutively restrains antigen cross-presentation in a murine tumor model[34]. D3R deficiency potentiates antitumor CTL responses in vivo[34]. Dopamine receptor agonism with cabergoline shifts monocyte-derived DCs toward an immunogenic phenotype with increased TNF-α and IL-12 and decreased IL-10, transforming growth factor beta (TGF-β), and Indoleamine 2, 3-dioxygenase (IDO)[35]. These dopaminergic effects on DCs have been characterized primarily in tumor contexts and are discussed in section 2.4.2.2. CD8+ T cells also express D3R[144], providing a confounding factor for in vivo pharmacological D3R studies. Myeloid cells express multiple dopamine receptors beyond D3R[37,145], but their precise roles in lymph node DC and macrophage function have not been elucidated.
2.3.2.4 Controversies and open questions
Dopaminergic effects on DCs have been characterized primarily in monocyte-derived DCs in vitro and cannot be directly translated to lymph node-resident DC subsets. Direct characterization of ANS receptor expression and functional responses of lymph node-resident DC and macrophage subsets in their native cortical, paracortical and medullary niches is largely absent. Whether observed T cell phenotypes in vivo reflect direct adrenergic or cholinergic signaling on T cells or indirect consequences of altered myeloid function remains to be tested.
2.4 Non-lymphoid organs
2.4.1 Intestine
The intestine is distinctive in the ANS-myeloid regulation because it contains an intrinsic nervous system, the ENS, that both operates independently of extrinsic autonomic input and serves as an obligatory relay for parasympathetic signaling to intestinal myeloid cells.
2.4.1.1 Anatomical organization
Cholinergic innervation of intestinal myeloid cells differs fundamentally from the classical CAP described in the spleen. ChAT-reporter mice tracing cholinergic structures have revealed that the dense fiber network surrounding macrophages, in the lamina propria originates almost exclusively from enteric neurons, rather than from extrinsic autonomic fibers[146]. Consistent with this, vagal efferents terminate in enteric ganglia and do not directly contact lamina propria myeloid cells[27]. In contrast, the muscularis externa receives sympathetic postganglionic innervation, with adrenergic varicosities directly adjacent to resident macrophages[27]. This compartmental separation defines two anatomically and functionally distinct neuro-immune interfaces within the intestinal wall (Figure 4).
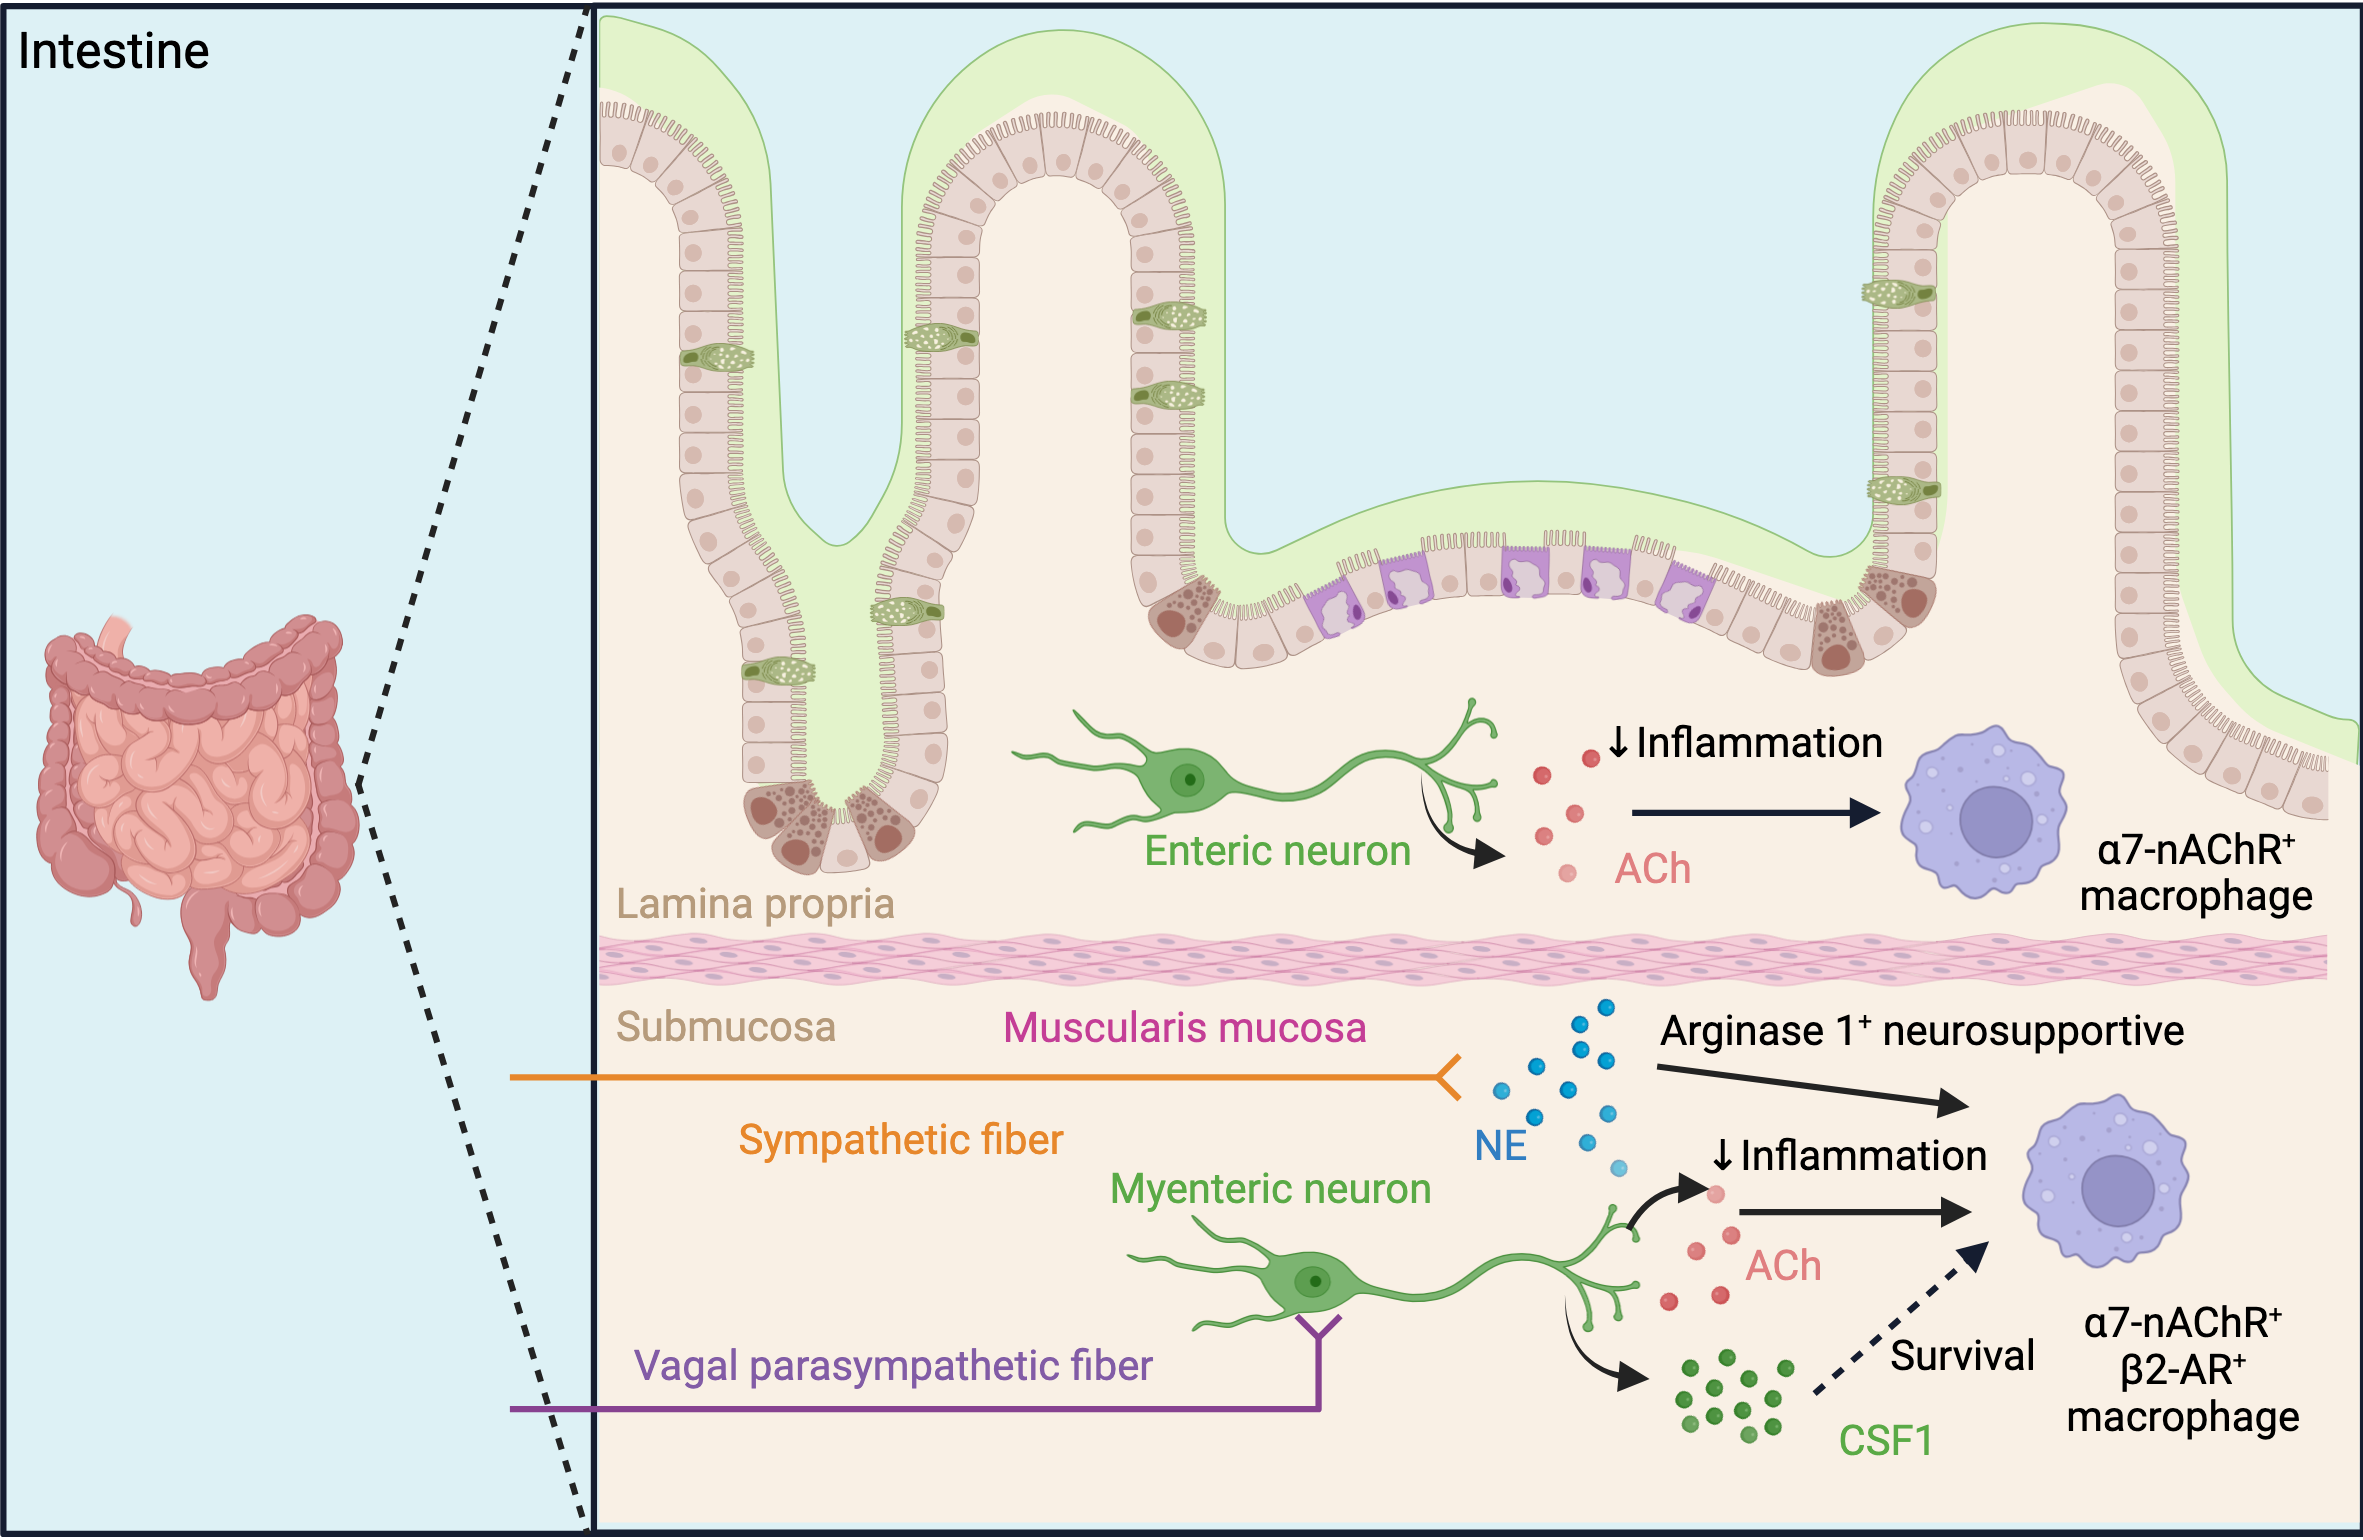
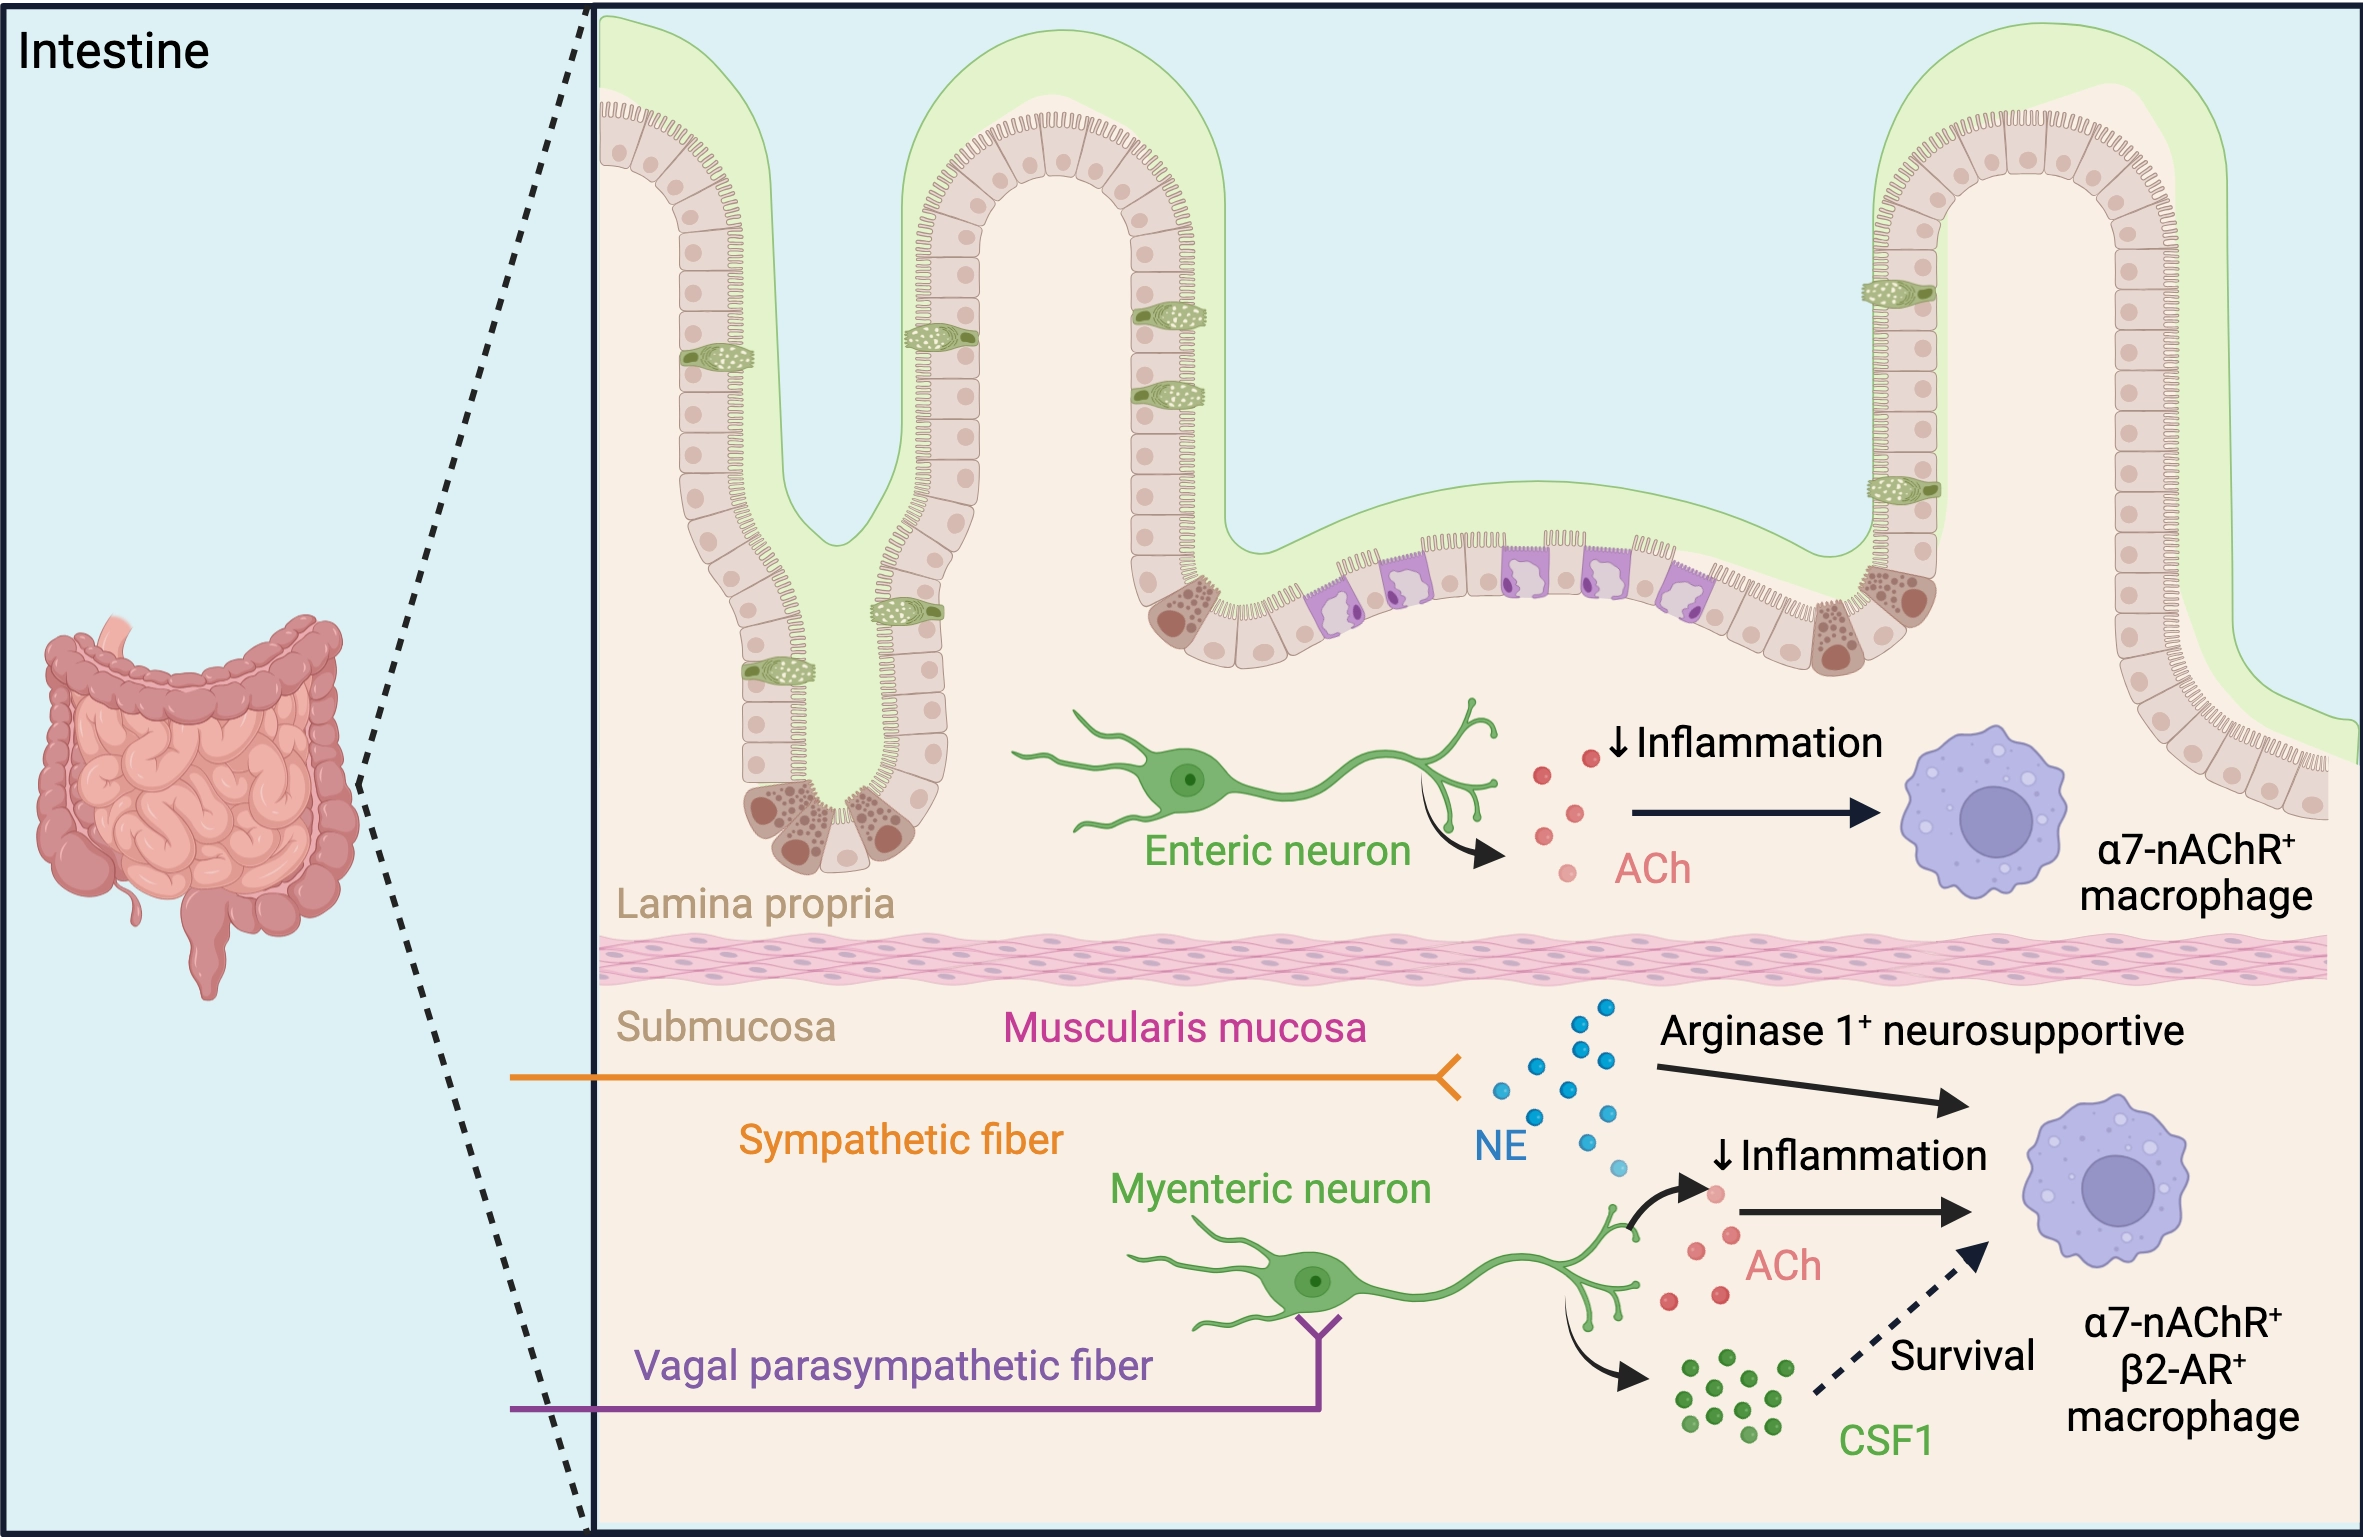
Figure 4. Compartment-specific neuro-myeloid interfaces in the intestinal wall. Vagal efferents terminate in myenteric ganglia of the ENS and do not directly contact intestinal myeloid cells. In the lamina propria, ENS-intrinsic cholinergic neurons release ACh onto α7-nAChR+ macrophages to suppress inflammation. In the muscularis externa, sympathetic fibers directly contact β2-AR+ macrophages to induce an arginase 1-dependent neurosupportive program independently of ENS relay, while myenteric neurons provide trophic CSF1-dependent survival signals to the same macrophage population. Created in BioRender. Mauvais FX. (2026) https://BioRender.com/4ikkf64. ENS: enteric nervous system; ACh: acetylcholine; α7-nAChR+: α7 nicotinic acetylcholine receptor; β2-AR+: β2-adrenergic receptor; CSF1: colony stimulating factor 1.
2.4.1.2 Sympathetic regulation of muscularis macrophages
Postganglionic neurons from the celiac–superior mesenteric ganglion project to the muscularis externa, where their fibers terminate near β2-AR-expressing macrophages[147], without requiring an enteric interneuron relay. Microbial signals activate these extrinsic sympathetic neurons, leading to noradrenaline release that induces an arginase 1-dependent macrophage program that preserves enteric neuronal integrity[147]. Deletion of Adrb2 in macrophages phenocopies the loss of sympathetic input, whereas adrenalectomy has no effect, identifying local nerve terminals as the relevant source of NE[15]. Under steady-state conditions, tonic sympathetic activity constrains the inflammatory potential of intestinal myeloid cells, and its disruption is sufficient to induce spontaneous, innate immune-driven colitis in immunodeficient mice[148].
2.4.1.3 Vagal and cholinergic regulation of the ENS
Unlike the spleen, the vagus nerve does not directly regulate intestinal myeloid cells but is structurally dependent on the ENS, which provides the final cholinergic interface with macrophages. Vagal efferents synapse onto myenteric cholinergic neurons, whose terminals contact α7 nicotinic ACh receptor (α7-nAChR)-expressing muscularis macrophages[27]. VNS prevents postoperative ileus in a spleen-independent manner, but requires intact enteric circuitry, establishing the ENS as an essential relay[27]. The 5-HT4 receptor agonist prucalopride acts exclusively on enteric neurons, its receptor being absent from macrophages, to enhance ACh release onto α7-nAChR+ macrophages and resolve ileus, an effect lost in α7-nAChR-deficient animals[149]. Optogenetic activation or ablation of enteric ChAT+ neurons is sufficient to modulate macrophage inflammatory output and intestinal motility, even in the absence of vagal input[150].
2.4.1.4 ENS-intrinsic regulation of myeloid identity
The ENS is not only a relay for extrinsic autonomic signals but also a local regulator of intestinal myeloid cells. Enteric neurons constitutively produce colony-stimulating factor 1 (CSF1), the principal trophic factor maintaining the functional muscularis macrophage pool[14]. During the neonatal period, muscularis macrophages prune enteric synapses in a process analogous to microglial remodeling in the central nervous system; postnatally, enteric neurons in turn provide TGF-β-dependent signals that program a neurosupportive macrophage phenotype required for neuronal survival[88]. Complement component C1q derived from macrophages further contributes to normal synapse organization, highlighting reciprocal regulation between the two cell types[151]. Enteric glia regulate monocyte and macrophage recruitment via CXCL10 secretion[152], while mast cells in close associations with enteric neurons in the submucosa and lamina propria can drive persistent visceral hypersensitivity through histamine and tryptase signaling following infection[153]. Non-neuronal sources of ACh include ChAT-expressing CD4⁺ T cells, tuft cells, and epithelial cell populations, and primarily regulate luminal immunity, rather than engaging α7-nAChR-dependent macrophage signaling in the muscularis[154].
2.4.1.5 Disease consequences and therapeutic implications
Sympathetic denervation models show that loss of adrenergic tone is sufficient to trigger innate immune-driven colitis, implicating dysautonomia as a potential contributor to inflammatory bowel disease pathogenesis[148]. The vagal-ENS-macrophage pathway has emerged as a therapeutic target: clinical studies of VNS in Crohn’s disease and ulcerative colitis, including a device-based multicenter trial in biologic-refractory Crohn’s disease[155] and non-invasive transcutaneous auricular stimulation in pediatric inflammatory bowel disease[156], have reported reductions in inflammatory biomarkers alongside clinical improvement. The ENS-dependent architecture of this pathway supports the hypothesis that ENS dysfunction may impair intestinal macrophage regulation, thereby impairing mucosal immunity, but this hypothesis remains mechanistically underexplored.
2.4.1.6 Open questions and controversies
Although the sympathetic and ENS-derived cholinergic innervations are anatomically separated, the functional consequences of this asymmetry for intestinal myeloid regulation under pathological contexts have not been investigated. The relative contributions of extrinsic vagal input versus autonomous ENS activity to muscularis macrophage homeostasis remain unclear. Whether the vagal-ENS-macrophage circuit characterized in mice translates to humans has not been directly demonstrated.
2.4.2 Tumor microenvironment
The TME represents a qualitatively distinct context for studying ANS-myeloid interactions. Tumors actively remodel their neural microenvironment, through axonal sprouting and neuronal reprogramming, establishing bidirectional tumor-nerve communication[157]. Intratumoral nerve density correlates with worse prognosis across multiple solid tumor types. Again, sympathetic and dopaminergic signals regulate tumor-associated myeloid populations, including tumor-associated macrophages (TAMs), myeloid-derived suppressor cells (MDSCs), DCs, monocytes and neutrophils, in tumor-type, spatial scale and disease stage dependent ways.
2.4.2.1 Sympathetic regulation of tumor-associated myeloid populations
NE acting on β2-AR is a recurring mechanism of neural immunosuppression within the TME, but the evidence for individual myeloid populations comes mainly from separate tumor models rather than from cross-cancer comparisons. In TAMs, chronic adrenergic stimulation promotes immunosuppressive polarization via β2-AR: CD163+ breast cancer macrophages, presumably an immunosuppressive subset, express β2-AR[5]. In MDSCs, β2-AR signaling upregulates arginase 1, Programmed Death-Ligand 1 (PD-L1), IL-10, and TGF-β, suppressing T cell proliferation and Natural Killer cell cytotoxic function, with metabolic reprogramming through fatty acid oxidation amplifying this immunosuppressive program[6,13]. In neutrophils, NE-driven β-AR activation shifts phenotypes toward pro-tumorigenic states with upregulation of vascular endothelial growth factor and matrix metalloproteinases, facilitating angiogenesis and matrix remodeling[157,158].
By analogy with splenic DCs, sympathetic signals within the TME would be predicted to impair Gαi/0-dependent cross-presentation[10], selectively reducing CTL priming, though this mechanism has not been demonstrated in the context of tumor-infiltrating DCs. β-adrenergic signaling additionally suppresses DC maturation and enhances Treg expansion, contributing to a tolerogenic immune landscape[6,13]. NE upregulates PD-L1 on tumor cells through cAMP-PKA-AKT-NF-κB pathways[157], compounding myeloid-mediated immunosuppression. The β1-AR provides an additional node: chronic β1-AR signaling directly drives T cell exhaustion, amplifying the tolerogenic environment created by ANS-regulated myeloid cells[159].
In pancreatic ductal adenocarcinoma (PDAC), sympathectomy increases tumor growth and metastatic spread through SNS-dependent suppression of intratumoral CD163+ protumorigenic macrophage accumulation[160]. Trace-n-Seq characterization reveals transcriptional reprogramming of pancreas-innervating neurons by the TME[161]. Chronic psychological stress promotes hepatocellular carcinoma growth by mobilizing splenic monocytes and MDSCs via a β-adrenergic-C-X-C chemokine receptor type 2 (CXCR2)/CXCL2-3 axis; splenectomy, propranolol, and CXCR2 inhibition each individually reduces tumor myeloid infiltration[162]. Because splenectomy removes the entire splenic reservoir and propranolol acts systemically across neuronal, immune, and stromal compartments, these interventions support the proposed mechanism without establishing myeloid cell autonomy. Taken together, these findings indicate that systemic stress-driven recruitment through the spleen and local sympathetic signaling within the tumor can have divergent consequences, helping explain the apparent contradiction between cancer-protective and cancer-permissive sympathetic effects across tumor types (Figure 5).
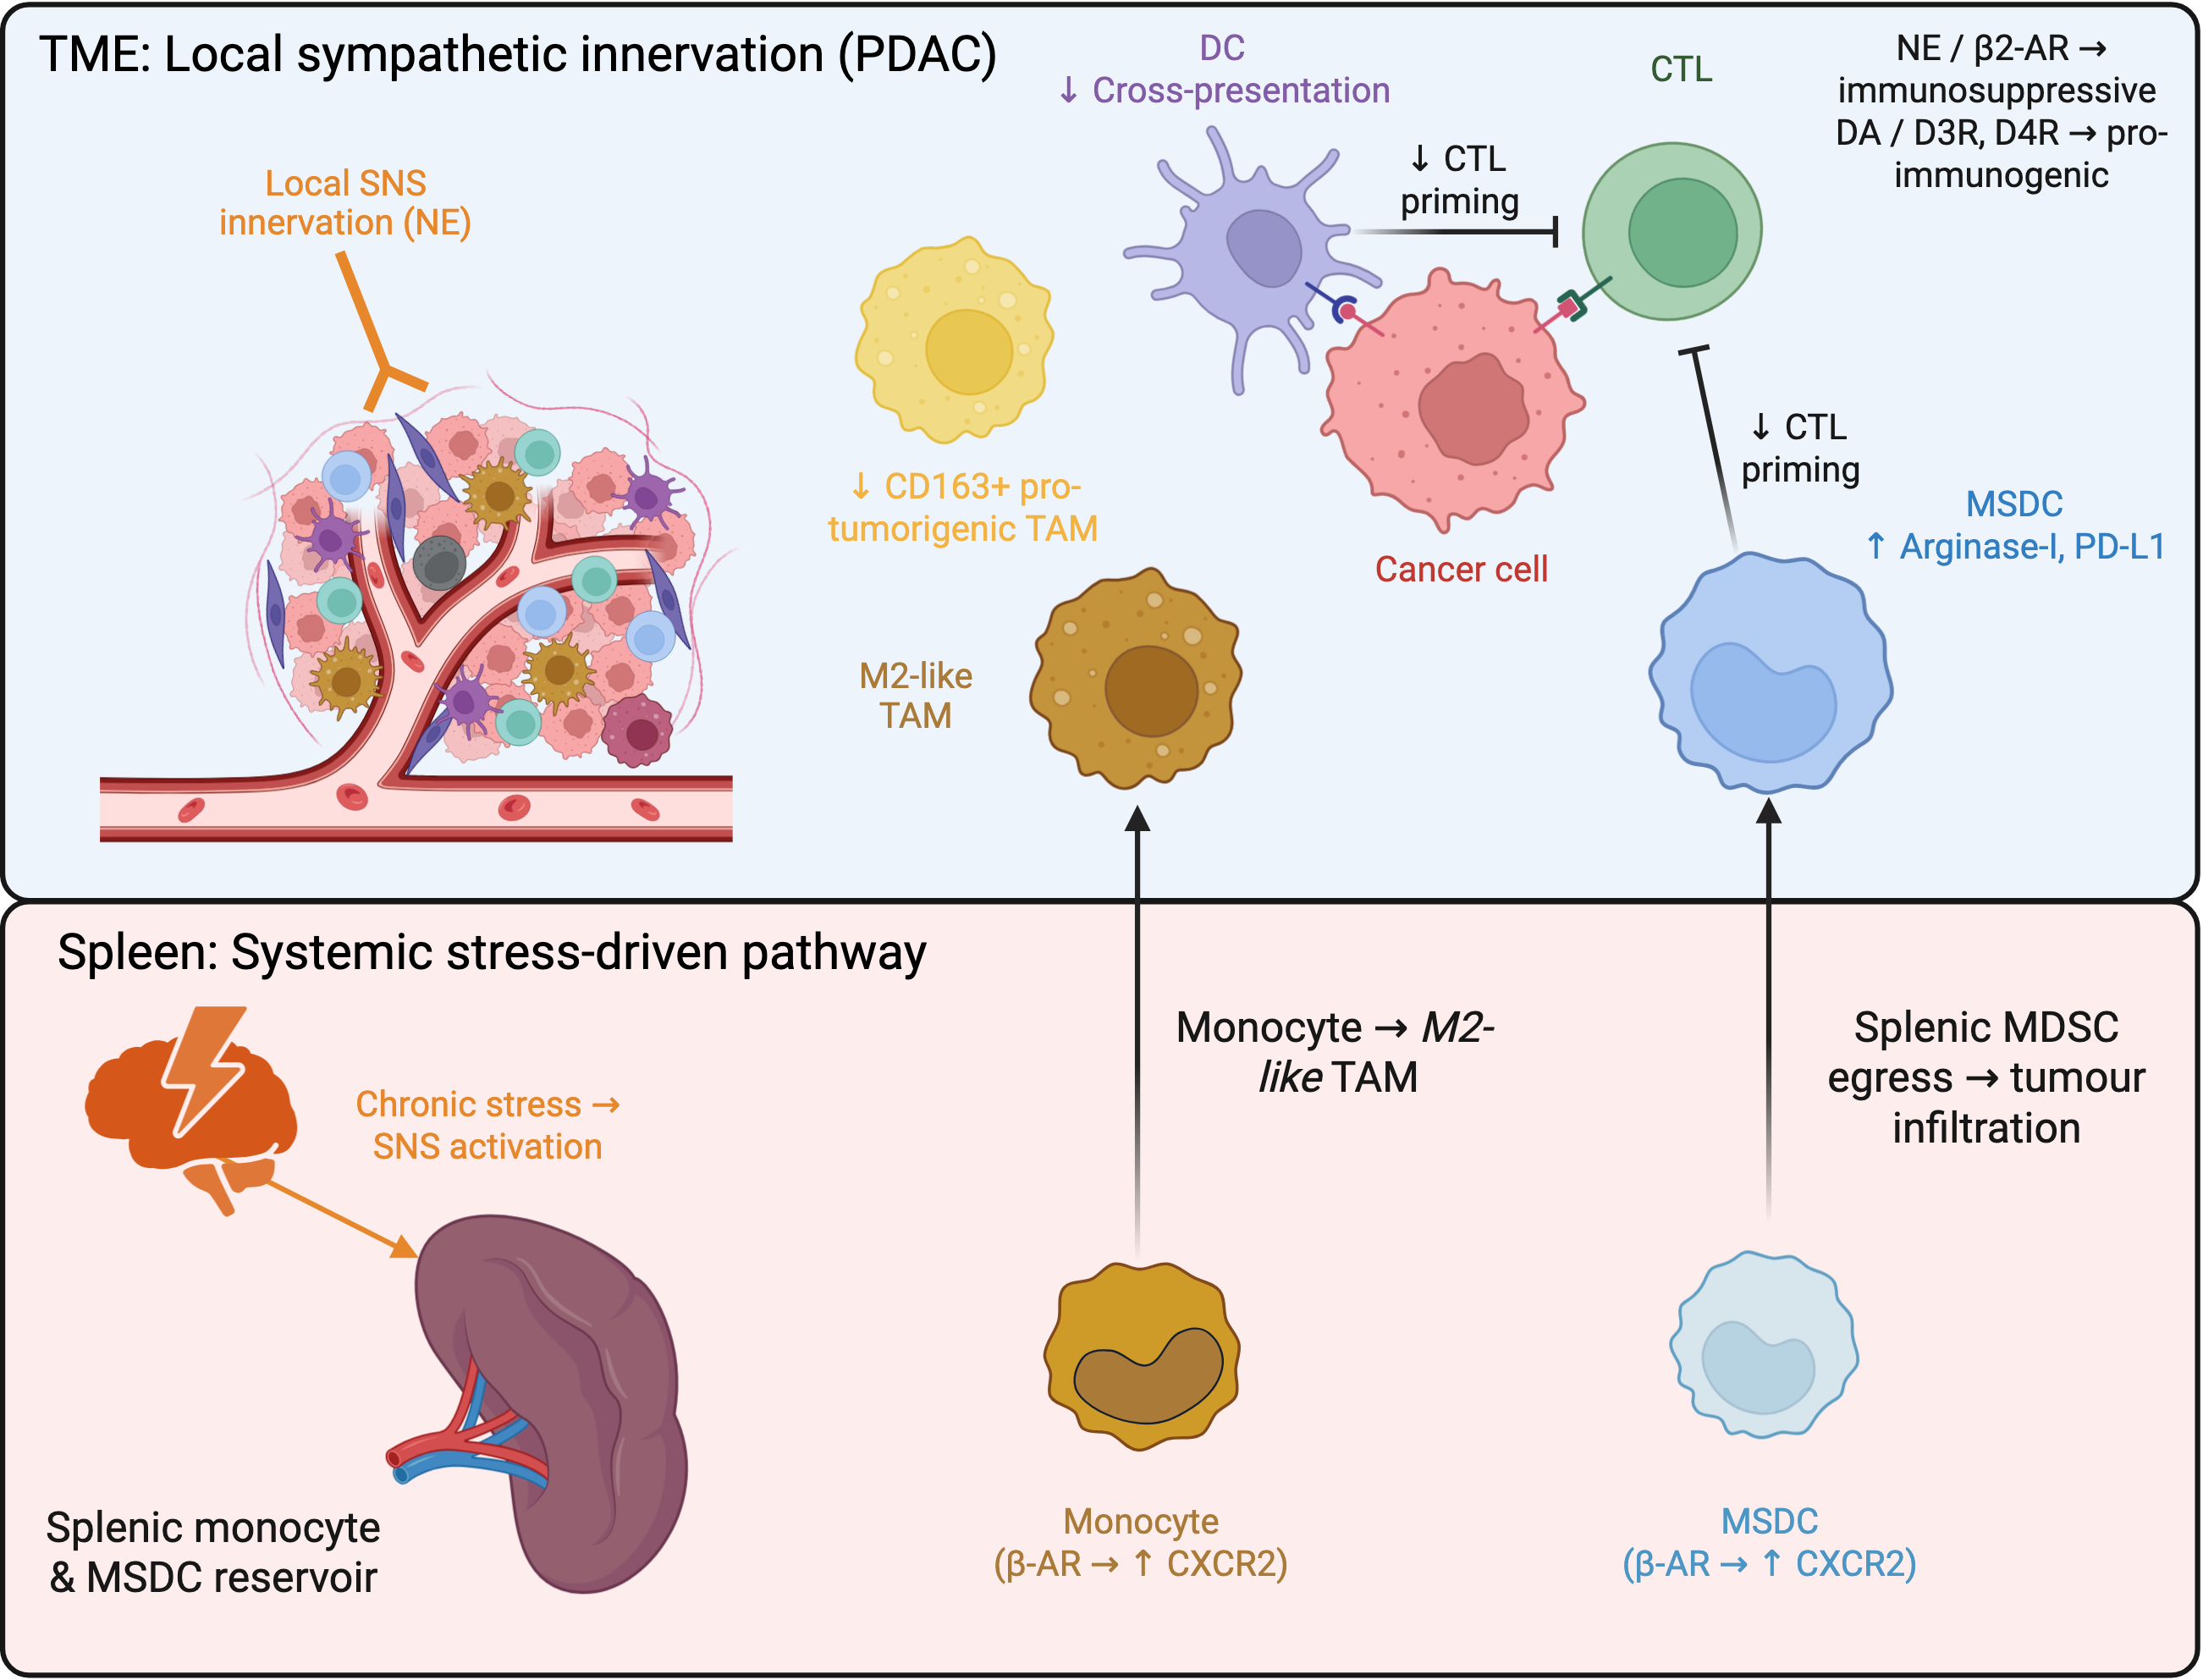
Figure 5. Context-dependent sympathetic regulation of myeloid cell function in the TME. (Top) Local SNS innervation in PDAC. Local sympathetic nerve sprouting releases NE within the TME, activating β2-AR on tumor-associated myeloid cells, suppressing CD163+ pro-tumorigenic TAM accumulation, impairing DC cross-presentation, and promoting MDSC-mediated inhibition of CTL priming via arginase 1 and PD-L1 upregulation. Dopaminergic signals counteract adrenergic immunosuppression: DA D3R restrains DC cross-presentation while D4R agonism reduces immunosuppressive TAM accumulation. (Bottom) Systemic stress-driven pathway (hepatocellular carcinoma). Chronic psychological stress activates the SNS, elevating splenic NE and upregulating CXCR2 on splenic monocytes and MDSCs via β-AR signaling, driving their egress from the splenic reservoir and recruitment to the tumor, where monocytes differentiate into immunosuppressive TAMs. Created in BioRender. Mauvais FX. (2026) https://BioRender.com/axg8x88. TME: tumor microenvironment; SNS: sympathetic nervous system; PDAC: pancreatic ductal adenocarcinoma; NE: norepinephrine; β2-AR: β2-adrenergic receptors; TAM: tumor-associated macrophage; DC: dendritic cell; MDSC: myeloid-derived suppressor cell; CTL: cytotoxic T lymphocyte; PD-L1: programmed death-ligand 1; DA: dopamine; D3R: D3 receptor; CXCR2: C-X-C chemokine receptor type 2.
2.4.2.2 Dopaminergic regulation of tumor-associated myeloid populations
Dopaminergic signals regulate antitumor myeloid function through multiple receptor-specific, predominantly immunostimulatory, mechanisms. In DCs, D3R constitutively restrains antigen cross-presentation within the TME; D3R-deficient DCs potentiate antitumor CTL responses in vivo, identifying D3R as a myeloid immune checkpoint whose pharmacological inhibition could enhance DC-driven antitumor immunity[34]. Conversely, cabergoline-driven dopamine receptor agonism shifts monocyte-derived DCs toward an immunogenic phenotype characterized by increased TNF-α and IL-12 and decreased IL-10, TGF-β, and IDO[35].
In TAMs, D4R activation enhances the antitumor efficacy of gemcitabine in PDAC and reduces the number of CD206+ macrophages with immunosuppressive features through a cAMP-PKA pathway that downregulates IL-1 expression[36]. Dopamine receptor agonism with bromocriptine inhibits tumor growth and induces apoptosis in breast cancer cells through the same receptor-mediated mechanisms[36,163], while high dopamine concentrations inhibit TAM recruitment and reduce the expression of pro-inflammatory factors including IL-6 and TNF-α[36,163].
In MDSCs, dopamine acts in direct opposition to the NE-driven program of immunosuppressive expansion, with receptor expression confirmed on MDSCs from human lung cancer patients. Systemic dopamine administration activates D1-like receptors on Gr-1+CD115+ MDSCs[38], suppressing interferon-γ-induced ERK and JNK signaling and nitric oxide synthesis, thereby mitigating their immunosuppressive effects on T cells and enhancing antitumor immunity[38]. Pharmacological activation of the ventral tegmental area dopaminergic circuit can suppress the growth of B16 melanoma and Lewis lung carcinoma through MDSC-dependent mechanisms[164].
In monocytes, dopaminergic agonism shifts differentiation away from immunosuppressive monocyte-derived DCs and TAMs toward immunogenic phenotypes[35,36]. Dopamine D5 receptor (D5R) signaling on B cells via Janus Kinase 1-signal transducer and activator of transcription 1 (STAT1) enhances antigen presentation and co-stimulatory capacity, expanding tumor-specific effector CD8+ T cells in a myeloid-dependent manner, and correlating with circulating B cell numbers in cancer patients[37].
2.4.2.3 Therapeutic implications
The neuro-myeloid interactions in the TME have immediate and clinically actionable therapeutic implications. β-blockade with propranolol is associated with a Th1-polarized CD4+ T cell response, reduces monocyte-mediated immunosuppression, and attenuates metastasis in breast cancer or melanoma preclinical models[165]. β-blockers reduce immunosuppressive TAM infiltration and dampen pro-metastatic gene expression in primary tumors, especially murine breast cancer models. Combining β1-selective blockade with anti-PD-1/PD-L1 or anti- Cytotoxic T-lymphocyte-associated protein 4 (CTLA4) immunotherapy improves T cell function and reduces exhaustion markers in breast and lung cancer preclinical models through targeting myeloid-driven immunosuppression and T cell-intrinsic exhaustion[159,166]. As β1-selective blockade is likewise not restricted to myeloid or T cells, the relative contribution of each compartment to the combined benefit remains unresolved. In non-small cell lung cancer patients, concurrent β-blocker use with immune checkpoint inhibitors has been associated with prolonged progression-free survival[167], and retrospective analyses across breast cancer and prostate cancer cohorts suggest improved outcomes in patients receiving β-blockers for cardiovascular indications[168-170], findings motivating multiple prospective clinical trials investigating perioperative or adjuvant propranolol. α-adrenergic antagonists provide a complementary approach acting through DC cross-presentation: prazosin, identified in a screen of 700 FDA (food and drug administration)-approved drugs as an enhancer of endolysosomal antigen import into the cytosol, reduces tumor growth and synergizes with checkpoint immunotherapy in murine melanoma and colorectal cancer models[171]. However, its mechanism of action likely involves endolysosomal membrane permeabilization rather than α1-AR blockade per se. In the dopaminergic pathway, D3R inhibition in DCs[34], D4R agonism in TAMs in PDAC[36], dopamine-mediated MDSC suppression via D1-like receptors in melanoma and lung cancer models[38], and D5R agonism in antigen-presenting B cells[37] represent emerging antitumor myeloid targets derived from distinct tumor type specific models. In colorectal cancer models, VIP blockade shifts TAM polarization toward a pro-inflammatory, phagocytically active phenotype and increases the pro-inflammatory to immunosuppressive ratio in tumor-infiltrating myeloid cells, and attenuates tumor growth, synergizing with anti-PD-1 therapy[49]. VIP signaling thus constitutes an additional immunosuppressive neuro-myeloid axis in the TME, distinct from adrenergic and dopaminergic pathways discussed above.
The TME illustrates the full context-dependence of ANS-myeloid regulation: the same adrenergic input that restrains pro-tumorigenic TAM accumulation in PDAC drives systemic immunosuppressive myeloid mobilization in stress-exposed hosts with hepatocellular carcinoma. Dopaminergic signals counteract adrenergic immune suppression in myeloid subsets across murine melanoma, lung, colorectal, and pancreatic cancer models. Determining which mechanism predominates in which cancer type and disease stage is essential before ANS-targeting strategies can be rationally deployed in oncology. These interactions are summarized in Table 2.
Table 2. ANS-myeloid interactions across organs and functional axes.
| Axis | BM/thymus | Spleen | LNs | Intestine | TME |
| Myeloid development & output | ↑ GMPs (β2-AR); β3-AR (sex-dimorphic); ACh → HSPC quiescence | Monocyte reservoir; SNS → mobilization; NAMs within splenic nerve | - | CSF1→ macrophage homeostasis | ↑ splenic MDSC egress; ↓ CD163+ TAM (PDAC) |
| Inflammatory regulation & antimicrobial defense | CAP pre-programming; DA: tonic brake | CAP: ↓ TNF/HMGB1; β2-AR: suppressive; CART/NPY: parallel; β2-AR → ↓ MARCO+phagocytosis; Sympathectomy → ↑ bacterial survival | β2-AR → ↓ IL-12 ↑ IL-10 (Th2 bias); Circuit: mesenteric > inguinal LN; NE → vasoconstriction→ ↓ leukocyte motility | β2-AR → arginase 1+; VNS → ↓ ileus; Sympathectomy → colitis; Non-neuronal ACh→ luminal immunity | β2-AR → immunosuppressive TAM/MDSC; β1-AR → T exhaustion; DA → pro-immunogenic; β2-AR KO → ↑ antiviral |
| Antigen presentation & T cell priming | α7-nAChR pre-programs CAP competence; DA/D3R → ↓ cross-pres. | α7-nAChR → ↓ processing; β2-AR → ↓ cross-pres.; VIP → tolerogenic DCs | α1b-AR → ↑ DC migration; β2-AR → ↓ cross-pres.; D3R → ↓ cross-pres. | ENS → α7-nAChR; pDC migration | D3R KO → ↑ CTL; D4R → ↓ CD206+ TAM; Cabergoline → immunogenic DC |
| Tissue homeostasis & disease | BM neuropathy → myeloid bias Thymus: unstudied | Heart failure: SNS → cardiac Mac; VNS → renal protection; VIP → ↓ myocarditis | VIP → ↓ CCR7 → impaired DC trafficking | VNS → ↓ IBD (clinical trials) | β-blockade + ICI → ↑ antitumor VIP antag. + anti-PD-1 |
| Myeloid → ANS | TH+ leukocytes → ↑ GMP (local loop); Macs contact dystrophic sympathetic axons during ageing; causal role unknown | NAMs in splenic nerve; ChAT+ cells → ACh | ChAT+ T cells → ACh | Macrophage synaptic pruning (neonatal) | Tumors reprogram innervating neurons |
See corresponding sections for organ-specific detail. α1b-AR: α1b-adrenergic receptor; α7-nAChR: α7 nicotinic acetylcholine receptor; ACh: acetylcholine; ANS: autonomic nervous system; AR: adrenergic receptor; β1-AR: β1-adrenergic receptor; β2-AR: β2-adrenergic receptor; β3-AR: β3-adrenergic receptor; BM: bone marrow; CAP: cholinergic anti-inflammatory pathway; CART: cocaine- and amphetamine-regulated transcript; ChAT: choline acetyltransferase; CTL: cytotoxic T lymphocyte; D3R: dopamine D3 receptor; D4R: dopamine D4 receptor; DA: dopamine; DC: dendritic cell; ENS: enteric nervous system; GMP: granulocyte-macrophage progenitor; HMGB1: high-mobility group box 1 protein; HSPC: hematopoietic stem and progenitor cell; ICI: immune checkpoint inhibitor; IBD: inflammatory bowel disease; LN: lymph node; Mac: macrophage; MARCO: macrophage receptor with collagenous structure; MDSC: myeloid-derived suppressor cell; NAM: nerve-associated macrophage; NE: norepinephrine; NPY: neuropeptide Y; pDC: plasmacytoid dendritic cell; PDAC: pancreatic ductal adenocarcinoma; SNS: sympathetic nervous system; TAM: tumor-associated macrophage; TH: tyrosine hydroxylase; TME: tumor microenvironment; TNF: tumor necrosis factor; VIP: vasoactive intestinal peptide; VNS: vagus nerve stimulation.
2.4.2.4 Controversies and open questions
Most mechanistic evidence for sympathetic-mediated immunosuppression in the TME comes from distinct transplanted syngeneic mouse tumor models, which do not recapitulate the stromal, innervation and immune complexity of spontaneous human tumors. Cross-cancer translation of sympathetic and dopaminergic regulation of myeloid cells has not been established. Direct demonstration of sympathetic cross-presentation impairment by tumor-infiltrating as opposed to splenic DCs is lacking. Whether peripheral dopaminergic myeloid targeting can be achieved without perturbing central circuits remains to be tested. Again, surgical or pharmacological interventions reviewed in this section preclude conclusions about myeloid cell specificity.
2.5 Perspectives
2.5.1 Organ-specific myeloid identity and ANS sensitivity
Whether the functional heterogeneity of ANS-myeloid interactions across tissues reflects differences in neural circuit architecture alone, or also in the intrinsic identity of myeloid populations remains unresolved. Tissue-resident macrophages possess distinct ontogenies, transcriptional programs, and epigenetic landscapes[172] that likely determine their receptor expression profiles and responsiveness to ANS signals, yet neurotransmitter receptor expression across macrophage, DC, monocyte and neutrophil subsets has not been systematically mapped. Systemic mapping of neurotransmitter receptor expression across myeloid cell subsets using single-cell proteogenomics and chromatin accessibility profiling remains to be performed.
A related unresolved question concerns the differential impact of ANS signals on the three major pathways of antigen presentation (endogenous MHC-I presentation, exogenous MHC-II presentation, and cross-presentation) across myeloid cell populations and tissues. Available evidence suggests β2-AR signaling selectively impairs cross-presentation while largely sparing MHC-II-restricted presentation in splenic and lymph node DCs. Whether this asymmetry applies to tissue-resident macrophages or monocyte-derived DCs remains untested. These populations differ from conventional DCs in antigen processing machinery[173,174].
2.5.2 Developmental, age-related, sex-dependent and circadian variables
How ANS-myeloid interactions during the neonatal period shape adult immune set points is unknown. Prenatal stress represents an earlier potential layer of programming: maternal stress may influence fetal immune development through placental transfer of glucocorticoids and catecholamines[175]. Whether it durably reprograms fetal myeloid progenitors and the tissue-resident macrophage populations seeded during fetal life remains unresolved. Sympathetic innervation density in the human spleen declines with age[117]. Whether this shifts tissue-resident macrophages toward constitutive activation or impairs CAP-mediated inflammation resolution remains elusive. The sexually dimorphic neuro-hematopoietic wiring has been reported in the bone marrow[103] where β3-AR/CXCL12-dependent HSPC mobilization and sympathetic stress responses differ in a sex-dependent manner. Sex-dependent differences have been proposed in experimental intestinal inflammation[176], and immunity more broadly[177], yet the direct neural and myeloid underlying mechanisms remain incompletely defined. Whether sex-dependent differences in ANS-myeloid signaling extend to spleen, lymph nodes and thymus remains unknown. Sympathetic tone follows a circadian rhythm driven by suprachiasmatic nucleus output, generating rhythmic β2-AR and β3-AR signaling in the bone marrow, controlling the timed egression of neutrophils and monocytes into the circulation[178]. Neutrophil release peaks at the onset of the active phase, driven by circadian downregulation of CXCL12 by stromal cells that releases CXCR4-expressing neutrophils from bone marrow retention, while a nocturnal cholinergic signal damps sympathetic tone to restore retention[178-180]. Adrenergic innervation of the vasculature extends this program to peripheral tissues, governing rhythmic endothelial adhesion molecule expression and circadian monocyte and neutrophil trafficking to inflamed sites[181]. In the spleen, the circadian clock regulates TLR9-mediated innate and adaptive immune responses[182]. Whether analogous cell-autonomous Bmal1/Rev-Erbα molecular mechanisms support resident macrophage function specifically remains to be established. In lymph nodes, lymphocyte homing peaks at night onset with daytime egression, generating circadian oscillations in cellularity that depend on rhythmic expression of promigratory factors in lymphocytes and are abolished by lymphocyte-specific clock disruption[183], a circadian architecture within which DC trafficking and myeloid antigen presentation likely also oscillate, though this has not been directly demonstrated. In the intestine, VIP-expressing enteric neurons entrain circadian innate lymphoid cell programs with indirect consequences for myeloid cell function[184]. Chronic circadian disruption can remodel the TME and promote metastasis via the CXCL5-CXCR2 axis[185], the extent to which this is mediated by direct ANS-myeloid coupling remains unresolved. Whether therapeutic timing of neuromodulatory interventions could exploit this circadian dimension remains to be explored.
2.5.3 Translational implications
Translating ANS-myeloid mechanisms from mouse to human requires consideration of known species differences. Reviews summarize evidence that human myeloid cells can express adrenergic receptors[3,4]. Systematic cross-species comparisons of receptor density and function remain lacking. Sympathetic nerve density in the human spleen declines with age[117] but the functional cholinergic relay and its myeloid cellular targets remain to be tested. Anatomical components of the ENS are broadly conserved in humans[77], whereas the functional vagal-ENS-myeloid relay remains to be demonstrated directly in human intestinal tissue. For tumor contexts, dopaminergic and α-adrenergic myeloid targets have been identified exclusively in murine models of breast, lung, colorectal, and pancreatic cancer; human myeloid receptor expression profiles in these tumor contexts and their functional relevance remain uncharacterized.
Beta-blockers suppress β2-AR signaling on myeloid cells as an off-target consequence of cardiovascular indications, with immunological consequences still underexplored in clinical populations. VNS clinically improves inflammation in rheumatoid arthritis (RA) in the RESET-RA trial[186], yet whether splenic macrophages, monocytes or DCs mediate this positive response remains uncharacterized. Identifying myeloid biomarkers of CAP engagement would guide patient stratification and optimize stimulation parameters. Non-invasive approaches to ANS modulation, including splenic ultrasound stimulation[187] and transcutaneous VNS[128,156], provide translational potential supported by preclinical[128] and early clinical[156] studies, without surgical risk, though their myeloid mechanisms remain poorly characterized. Electroacupuncture[188] has shown immunomodulatory effects in specific preclinical settings; human clinical trials will be required before clinical translation can be established. α-adrenergic blockade and dopaminergic modulation of myeloid antitumor function warrant prospective clinical evaluation, stratified by tumor type, innervation density, and sympathetic tone. Direct human validation of the relevant myeloid receptor expression profiles in tumor contexts is lacking.
Systemic ANS modulation carries incompletely characterized risks: chronic β-blockade may impair adrenergic-dependent emergency myelopoiesis and antimicrobial defense; VNS in uncontrolled inflammatory contexts may risk possible paradoxical myeloid activation through afferent circuit engagement, though it remains a conceptual concern. Pan-adrenergic or pan-cholinergic interventions affect neurons, stromal cells, and immune cells simultaneously, precluding straightforward mechanistic interpretation of clinical outcomes. How CAN activity[70] during psychological stress[105] reaches peripheral myeloid compartments via sympathetic efferents, and how splenic nerve stimulation[189] devices engage specific myeloid populations at single-cell resolution, remain underexplored in both mice and humans. Table 3 summarizes murine mechanisms, human evidence, and translational gaps across the lymphoid and non-lymphoid tissues discussed.
Table 3. ANS-myeloid regulation across organs: murine mechanisms, human evidence, and translational gaps.
| Organ | Murine mechanisms | Human evidence | Translational gaps |
| BM | β2-AR/β3-AR control of GMP proliferation and myeloid output; sex-dimorphic β3-AR wiring; ACh/CXCL12 push-pull regulating HSPC quiescence | β-adrenergic myeloid lineage commitment via MAFB/GATA1 in multiple myeloma HSPCs; AChE inhibition reduces circulating inflammatory myeloid cells; catecholaminergic regulation of CD34+ cell migration | Whether sex-dimorphic β3-AR wiring translates to human BM; conditional receptor deletion evidence |
| Thymus | Sympathetic innervation across compartments; age-related axonal degeneration; hypertrophic macrophage contact with dystrophic axons | - | Sympathetic innervation of human thymus and its age-related remodeling essentially uncharacterized |
| Spleen | CAP circuit; β2-AR suppression of MARCO+ phagocytosis; splenic monocyte reservoir mobilization; C1-β2-AR renal protection | Sympathetic innervation conserved with age-related decline in density; VNS clinical efficacy (RESET-RA) | Cholinergic T cell relay not validated in human tissue; myeloid populations promoting clinical VNS response uncharacterized |
| LN | α1b-AR-driven DC migration; β2-AR reshaping of DC cytokine output; VIP/CCR7 migration control | Sympathetic innervation distribution characterized anatomically (human cervical and peripheral LN) | Functional neuro-myeloid data in native human LN niches largely absent |
| Intestine | Compartmentalized sympathetic (muscularis, β2-AR/Arginase 1+) and ENS-cholinergic (α7-nAChR) circuits; CSF1-dependent macrophage maintenance | ENS architecture conserved; VNS clinical efficacy in Crohn's disease and ulcerative colitis | Vagal-ENS-macrophage circuit not directly demonstrated in human intestinal tissue; functional neuro-myeloid data largely absent |
| TME | β2-AR immunosuppression of TAMs, MDSCs, neutrophils; dopaminergic (D3R, D4R, D5R, D1-like) modulation; established in transplanted syngeneic models | D1-like receptor expression on MDSCs from human lung cancer patients; D5R correlating with circulating B cells in cancer patients; β-blocker retrospective clinical associations (NSCLC, breast, prostate) | Dopaminergic and α-adrenergic myeloid targets identified in murine models; human myeloid receptor profiles in tumor contexts uncharacterized; syngeneic models do not recapitulate human tumor complexity |
ACh: acetylcholine; AChE: acetylcholinesterase; ANS: autonomic nervous system; β2-AR/β3-AR: β2-/β3-adrenergic receptor; α1b-AR: α1b-adrenergic receptor; α7-nAChR: α7 nicotinic acetylcholine receptor; BM : bone marrow; CAP: cholinergic anti-inflammatory pathway; CD34: cluster of differentiation 34; CSF1: colony-stimulating factor 1; CXCL12: C-X-C motif chemokine ligand 12; DC: dendritic cell; D1-like/D3R/D4R/D5R: dopamine receptors; ENS: enteric nervous system; GATA1: GATA-binding factor 1; GMP: granulocyte-macrophage progenitor; HSPC: hematopoietic stem and progenitor cell; LN: lymph node. MAFB: musculoaponeurotic fibrosarcoma oncogene homolog B; MARCO: macrophage receptor with collagenous structure; MDSC: myeloid-derived suppressor cell; NSCLC: non-small cell lung cancer; TAM: tumor-associated macrophage; TME: tumor microenvironment; VIP: vasoactive intestinal peptide; VNS: vagus nerve stimulation.
2.5.4 Emerging tools
The mechanistic questions raised throughout this review have been largely intractable with sympathectomy[72,120,160], pharmacological receptor manipulation, and bulk cytokine measurement. Anterograde and retrograde viral circuit tracing and optogenetic or chemogenetic manipulation[85,161,190,191] may help enable the mapping and causal testing of neuro-myeloid circuits when combined with immune cell-resolved readouts. Spatial transcriptomics and integrative computational approaches provide tools that could map neurotransmitter receptor expression across tissue-resident myeloid populations in their native niches[192-194], revealing the molecular basis for organ-specific ANS sensitivity.
3. Conclusion
Myeloid cells are primary effectors in neuro-immune communication whose activation state, migratory behavior, antigen handling capacity, and immunological output are shaped by sympathetic, parasympathetic, and enteric signals across tissues and disease contexts. The CAP in the spleen, long presented as a paradigmatic neuro-immune circuit, remains mechanistically contested by the unresolved necessity of a T cell relay and by the identification of parallel adrenergic and neuropeptide-mediated routes converging directly on myeloid cells. In the intestine, the ENS interposes as an obligatory relay between vagal efferents and lamina propria macrophages, a structural distinction whose disruption in enteric neuropathy has not been investigated as a mechanism of mucosal immune dysregulation. In the TME, the same sympathetic signal that suppresses intratumoral CD163+ protumorigenic macrophage accumulation in PDAC drives the systemic mobilization of immunosuppressive myeloid cells from the spleen in stress-exposed hosts.
How ANS signals differentially regulate cross-presentation, endogenous MHC-I, and MHC-II pathways across myeloid subsets and tissue contexts is unresolved, with direct implications for antitumor immunity and vaccine design. The specific myeloid populations targeted by implanted and non-invasive splenic nerve stimulation devices remain uncharacterized at single-cell resolution. The role of the CAN integrating cognitive, emotional, and visceromotor inputs in shaping myeloid cell output through efferent autonomic pathways is mechanistically unexplored, as is the possibility that ANS dysregulation during critical developmental windows contributes causally to the myeloid immune phenotypes observed in neurodevelopmental conditions.
The afferent limb of neuro-myeloid communication, including how NAMs and myeloid cells signal back to the CNS and CAN, remains an open question whose systematic investigation will be necessary for a complete account of bidirectional neuro-immune regulation.
Acknowledgements
The authors used Claude Sonnet (Anthropic) for language editing and stylistic harmonization across sections written by different authors. All scientific content, data interpretation, arguments, references, figures, and conclusions are original and were not generated using AI tools.
Authors contribution
Hartmann, M: Conceptualization, writing-original draft, writing-review & editing.
Hamel Y, Laforge M, Delclaux C: Writing-original draft.
van Endert P: Conceptualization, writing-original draft.
Mauvais FX: Conceptualization, writing-original draft, writing-review & editing, supervision.
Conflicts of interest
The authors declare no conflicts of interest.
Ethical approval
Not applicable.
Consent to participate
Not applicable.
Consent for publication
Not applicable.
Availability of data and materials
Not applicable.
Funding
This work was supported by the French government through the Agence Nationale de la Recherche under the France 2030 investment plan, grant reference ANR-23-IAHU0010 and through the Agence Nationale de la Recherche, grant reference ANR-26-CE15-5133 (SPLENIC-NET).
Copyright
© The Author(s) 2026.
References
-
1. Wang T, Tufenkjian A, Ajijola OA, Oka Y. Molecular and functional diversity of the autonomic nervous system. Nat Rev Neurosci. 2025;26(10):607-622.[DOI]
-
3. Bellinger DL, Millar BA, Perez S, Carter J, Wood C, ThyagaRajan S, et al. Sympathetic modulation of immunity: Relevance to disease. Cell Immunol. 2008;252(1-2):27-56.[DOI]
-
7. Wieduwild E, Girard-Madoux MJ, Quatrini L, Laprie C, Chasson L, Rossignol R, et al. β2-adrenergic signals downregulate the innate immune response and reduce host resistance to viral infection. J Exp Med. 2020;217(4):e20190554.[DOI]
-
10. Hervé J, Dubreil L, Tardif V, Terme M, Pogu S, Anegon I, et al. β2-adrenoreceptor agonist inhibits antigen cross-presentation by dendritic cells. J Immunol. 2013;190(7):3163-3171.[DOI]
-
29. Mashimo M, Takeshima S, Okuyama H, Matsurida A, Murase M, Ono S, et al. α7 nAChRs expressed on antigen presenting cells are insensitive to the conventional antagonists α-bungarotoxin and methyllycaconitine. Int Immunopharmacol. 2020;81:106276.[DOI]
-
35. Naseri B, Masoumi J, Abdolzadeh S, Abedimanesh S, Baghbani E, Hatami-Sadr A, et al. Dopamine receptor agonist cabergoline promotes immunogenic phenotype in human monocyte-derived dendritic cells. Cell Biochem Funct. 2024;42(4):e4067.[DOI]
-
36. Liu Q, Zhang R, Zhang X, Liu J, Wu H, Li Y, et al. Dopamine improves chemotherapeutic efficacy for pancreatic cancer by regulating macrophage-derived inflammations. Cancer Immunol Immunother. 2021;70(8):2165-2177.[DOI]
-
37. Wu Y, Zhu L, Li S, Liu L, Wang Y, Yang Y, et al. DA-DRD5 signaling reprograms B cells to promote CD8+ T cell-mediated antitumor immunity. Cell Rep. 2025;44(3):115364.[DOI]
-
39. Gopinath A, Mackie PM, Phan LT, Mirabel R, Smith AR, Miller E, et al. Who knew? Dopamine transporter activity is critical in innate and adaptive immune responses. Cells. 2023;12(2):269.[DOI]
-
41. Kobori N, Moore AN, Redell JB, Dash PK. Caudal DMN neurons innervate the spleen and release CART peptide to regulate neuroimmune function. J Neuroinflammation. 2023;20(1):158.[DOI]
-
44. Benitez R, Delgado-Maroto V, Caro M, Forte-Lago I, Duran-Prado M, O’Valle F, et al. Vasoactive intestinal peptide ameliorates acute myocarditis and atherosclerosis by regulating inflammatory and autoimmune responses. J Immunol. 2018;200(11):3697-3710.[DOI]
-
54. Moura M, Miranda A, Campos J, Pinho AG, Rito-Fernandes S, Soares-Cunha C, et al. Macro- and microanatomy of the sympathetic innervation of the spleen in rodents. J Comp Neurol. 2025;533(9):e70086.[DOI]
-
56. Yeung ST, Damani-Yokota P, Thannickal SA, Bartnicki E, Bernier ED, Barnett CR, et al. Nerve- and airway-associated interstitial macrophages mitigate SARS-CoV-2 pathogenesis via type I interferon signaling. Immunity. 2025;58(5):1327-1342.e5.[DOI]
-
58. Stakenborg N, Viola MF, Boeckxstaens G. Intestinal neuron-associated macrophages in health and disease. Nat Immunol. 2025;26(7):1004-1013.[DOI]
-
59. Gonzalez-Hurtado E, Leveau C, Li K, Mishra M, Qu R, Goldberg EL, et al. Nerve-associated macrophages control adipose homeostasis across lifespan and restrain age-related inflammation. Nat Aging. 2025;5(9):1828-1843.[DOI]
-
61. Park MD, Silvin A, Ginhoux F, Merad M. Macrophages in health and disease. Cell. 2022;185(23):4259-4279.[DOI]
-
62. Lazarov T, Juarez-Carreño S, Cox N, Geissmann F. Physiology and diseases of tissue-resident macrophages. Nature. 2023;618(7966):698-707.[DOI]
-
63. Bosteels V, Janssens S. Striking a balance: New perspectives on homeostatic dendritic cell maturation. Nat Rev Immunol. 2025;25(2):125-140.[DOI]
-
65. Reel JM, Abbadi J, Cox MA. T cells at the interface of neuroimmune communication. J Allergy Clin Immunol. 2024;153(4):894-903.[DOI]
-
68. Eid SA, Rumora AE, Beirowski B, Bennett DL, Hur J, Savelieff MG, et al. New perspectives in diabetic neuropathy. Neuron. 2023;111(17):2623-2641.[DOI]
-
81. Al-Shalan HAM, Hu D, Nicholls PK, Greene WK, Ma B. Immunofluorescent characterization of innervation and nerve-immune cell neighborhood in mouse thymus. Cell Tissue Res. 2019;378(2):239-254.[DOI]
-
83. Hu D, Al-Shalan HAM, Shi Z, Wang P, Wu Y, Nicholls PK, et al. Distribution of nerve fibers and nerve-immune cell association in mouse spleen revealed by immunofluorescent staining. Sci Rep. 2020;10:9850.[DOI]
-
88. Viola MF, Chavero-Pieres M, Modave E, Delfini M, Stakenborg N, Estévez MC, et al. Dedicated macrophages organize and maintain the enteric nervous system. Nature. 2023;618(7966):818-826.[DOI]
-
90. Rice PA, Boehm GW, Moynihan JA, Bellinger DL, Stevens SY. Chemical sympathectomy alters numbers of splenic and peritoneal leukocytes. Brain Behav Immun. 2002;16(1):62-73.[DOI]
-
93. Meng X, Fan Z, Cai Z, Xie M, Su J, Luo S, et al. Long-term vagus nerve stimulation synergized with rapamycin elicits neuroimmune modulation to prolong skin allograft survival. IScience. 2026;29(4):115189.[DOI]
-
100. Straub RH, Schaller T, Miller LE, von Hörsten S, Jessop DS, Falk W, et al. Neuropeptide Y cotransmission with norepinephrine in the sympathetic nerve: Macrophage interplay. J Neurochem. 2000;75(6):2464-2471.[DOI]
-
101. Maestroni G. The sympathetic nervous influence on hematopoiesis up to date. J Neuroimmune Pharmacol. 2025;20(1):61.[DOI]
-
105. Poller WC, Downey J, Mooslechner AA, Khan N, Li L, Chan CT, et al. Brain motor and fear circuits regulate leukocytes during acute stress. Nature. 2022;607(7919):578-584.[DOI]
-
106. Bernal A, Cuminetti V, Serulla M, Florit A, Konieczny J, Golnarnik G, et al. Bone marrow sympathetic neuropathy is a hallmark of hematopoietic malignancies and it involves severe ultrastructural damage. Exp Hematol Oncol. 2025;14(1):31.[DOI]
-
111. Cano G, Sved AF, Rinaman L, Rabin BS, Card JP. Characterization of the central nervous system innervation of the rat spleen using viral transneuronal tracing. J Comp Neurol. 2001;439(1):1-18.[DOI]
-
118. Bratton BO, Martelli D, McKinley MJ, Trevaks D, Anderson CR, McAllen RM. Neural regulation of inflammation: No neural connection from the vagus to splenic sympathetic neurons. Exp Physiol. 2012;97(11):1180-1185.[DOI]
-
124. Kato KT, Ferreira GCS, Fonseca DLM, Moretti EH, Trzan IFL, Filgueiras IS, et al. The greater splanchnic nerve preferentially regulates neutrophils over macrophages in a rat model of septic peritonitis. Brain Behav Immun. 2025;129:30-41.[DOI]
-
131. Heusch G, Kleinbongard P. The spleen in ischaemic heart disease. Nat Rev Cardiol. 2025;22(7):497-509.[DOI]
-
132. Ismahil MA, Zhou G, Rajasekar S, Gao M, Bansal SS, Patel B, et al. Splenic CD169+ Tim4+ marginal metallophilic macrophages are essential for wound healing after myocardial infarction. Circulation. 2025;151(24):1712-1729.[DOI]
-
138. Williams DW, Engle EL, Shirk EN, Queen SE, Gama L, Mankowski JL, et al. Splenic damage during SIV infection role of T-cell depletion and macrophage polarization and infection. Am J Pathol. 2016;186(8):2068-2087.[DOI]
-
149. Stakenborg N, Labeeuw E, Gomez-Pinilla PJ, De Schepper S, Aerts R, Goverse G, et al. Preoperative administration of the 5-HT4 receptor agonist prucalopride reduces intestinal inflammation and shortens postoperative ileus via cholinergic enteric neurons. Gut. 2019;68(8):1406-1416.[DOI]
-
150. Rahman AA, Stavely R, Pan W, Ott L, Ohishi K, Ohkura T, et al. Optogenetic activation of cholinergic enteric neurons reduces inflammation in experimental colitis. Cell Mol Gastroenterol Hepatol. 2024;17(6):907-921.[DOI]
-
154. Ndjim M, Gasmi I, Herbert F, Joséphine C, Bas J, Lamrani A, et al. Tuft cell acetylcholine is released into the gut lumen to promote anti-helminth immunity. Immunity. 2024;57(6):1260-1273.e7.[DOI]
-
156. Sahn B, Pascuma K, Kohn N, Tracey KJ, Markowitz JF. Transcutaneous auricular vagus nerve stimulation attenuates inflammatory bowel disease in children: A proof-of-concept clinical trial. Bioelectron Med. 2023;9(1):23.[DOI]
-
158. Yang H, Xia L, Chen J, Zhang S, Martin V, Li Q, et al. Stress–glucocorticoid–TSC22D3 axis compromises therapy-induced antitumor immunity. Nat Med. 2019;25(9):1428-1441.[DOI]
-
160. Guillot J, Dominici C, Lucchesi A, Nguyen HTT, Puget A, Hocine M, et al. Sympathetic axonal sprouting induces changes in macrophage populations and protects against pancreatic cancer. Nat Commun. 2022;13:1985.[DOI]
-
161. Thiel V, Renders S, Panten J, Dross N, Bauer K, Azorin D, et al. Characterization of single neurons reprogrammed by pancreatic cancer. Nature. 2025;640(8060):1042-1051.[DOI]
-
165. Fjæstad KY, Johansen AZ, Linder H, Baker KJ, Schattefor M, Czajkowski NK, et al. β-adrenergic signaling blockade attenuates metastasis through activation of cytotoxic CD4 T cells. Nat Commun. 2025;16:10063.[DOI]
-
166. Fjæstad KY, Rømer AMA, Goitea V, Johansen AZ, Thorseth ML, Carretta M, et al. Blockade of beta-adrenergic receptors reduces cancer growth and enhances the response to anti-CTLA4 therapy by modulating the tumor microenvironment. Oncogene. 2022;41(9):1364-1375.[DOI]
-
171. Kozik P, Gros M, Itzhak DN, Joannas L, Heurtebise-Chrétien S, Krawczyk PA, et al. Small molecule enhancers of endosome-to-cytosol import augment anti-tumor immunity. Cell Rep. 2020;32(2):107905.[DOI]
-
174. Mauvais FX, Hamel Y, Silvin A, Mulder K, Hildner K, Akyol R, et al. Metallophilic marginal zone macrophages cross-prime CD8+ T cell-mediated protective immunity against blood-borne tumors. Immunity. 2025;58(4):843-860.e20.[DOI]
-
179. García-García A, Korn C, García-Fernández M, Domingues O, Villadiego J, Martín-Pérez D, et al. Dual cholinergic signals regulate daily migration of hematopoietic stem cells and leukocytes. Blood. 2019;133(3):224-236.[DOI]
-
181. Scheiermann C, Kunisaki Y, Lucas D, Chow A, Jang JE, Zhang D, et al. Adrenergic nerves govern circadian leukocyte recruitment to tissues. Immunity. 2012;37(2):290-301.[DOI]
-
183. Druzd D, Matveeva O, Ince L, Harrison U, He W, Schmal C, et al. Lymphocyte circadian clocks control lymph node trafficking and adaptive immune responses. Immunity. 2017;46(1):120-132.[DOI]
-
184. Godinho-Silva C, Domingues RG, Rendas M, Raposo B, Ribeiro H, da Silva JA, et al. Light-entrained and brain-tuned circadian circuits regulate ILC3s and gut homeostasis. Nature. 2019;574(7777):254-258.[DOI]
-
186. Tesser JRP, Crowley AR, Box EJ, June JP, Wickersham PB, Valenzuela GJ, et al. Vagus nerve-mediated neuroimmune modulation for rheumatoid arthritis: A pivotal randomized controlled trial. Nat Med. 2026;32(1):369-378.[DOI]
-
188. Zhang Z, Lin W, Yan J, Wang X, Wang J, Wang F, et al. Prenatal electroacupuncture modulates maternal-fetal immune activation via a brain-to-splenic signal. Cell Rep. 2025;44(11):116576.[DOI]
-
192. Jung N, Kim TK. Spatial transcriptomics in neuroscience. Exp Mol Med. 2023;55(10):2105-2115.[DOI]
-
193. De Filippo R, Schmitz D. Transcriptomic mapping of the 5-HT receptor landscape. Patterns. 2024;5(10):101048.[DOI]
Copyright
© The Author(s) 2026. This is an Open Access article licensed under a Creative Commons Attribution 4.0 International License (https://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, sharing, adaptation, distribution and reproduction in any medium or format, for any purpose, even commercially, as long as you give appropriate credit to the original author(s) and the source, provide a link to the Creative Commons license, and indicate if changes were made.
Publisher’s Note
Science Exploration remains a neutral stance on jurisdictional claims in published
maps
and institutional affiliations. The views expressed in this article are solely those
of
the author(s) and do not reflect the opinions of the Editors or the publisher.
Share And Cite


Science Exploration Style
Hartmann M, Hamel Y, Laforge M, Delclaux C, van Endert P, Mauvais FX. Autonomic control of myeloid cell biology across tissues. Myeloid Cells. 2026;1:202608. https://doi.org/10.70401/mc.2026.0010
Tips
Copy completed.
Submit a Manuscript
Author Instructions
Cite this Article
Article Metrics
0
View
0
Download
Cited
Article Updates

 Get citation
Science Exploration Style

Hartmann M, Hamel Y, Laforge M, Delclaux C, van Endert P, Mauvais FX. Autonomic control of myeloid cell biology across tissues. Myeloid Cells. 2026;1:202608. https://doi.org/10.70401/mc.2026.0010
copy
Share Link
copy